Off
View Post
MVC’s Updated Common Conditions Report Now Available to Hospital Members

MVC’s Updated Common Conditions Report Now Available to Hospital Members

Earlier this month, the MVC Coordinating Center distributed a refreshed version of MVC’s common conditions report. This report delivered a comprehensive analysis of care episodes for six prevalent medical and surgical conditions frequently targeted for quality improvement initiatives within MVC hospitals. The included conditions were chronic obstructive pulmonary disease (COPD), congestive heart failure (CHF), coronary artery bypass graft (CABG), percutaneous coronary intervention (PCI), pneumonia, and sepsis. MVC generated hospital-level reports for 106 members, with tailored versions for general acute care hospital (GACH) and Critical Access Hospital (CAH) members.

Report pages focused on 30-day total episode payments, post-acute care utilization, readmission rates, and common reasons for readmissions. The report continued to highlight payments and outcomes for a two-year window, but the date range was updated to reflect claims from Jan. 1, 2024, through Dec. 31, 2025, for Blue Cross Blue Shield of Michigan (BCBSM)/Blue Care Network (BCN) Commercial, BCBSM/BCN Medicare Advantage (MA), and Michigan Medicaid; Medicare Fee-for Service (FFS) claims from the period of Jan. 1, 2024, through June 30, 2025, were used.

To ensure member reports had a sufficient sample from which to draw meaningful conclusions, MVC continued to apply case count inclusion criteria for the condition-specific pages. Previously, MVC required a site to have 11 episodes per year for both years to receive a condition-specific page; this year, condition-specific pages were included for all conditions with at least 20 episodes in the reporting period. This update expanded both the number of hospitals eligible for their report and report pages per hospital. For CAH members, MVC also expanded the reporting period for the CAH reports to Jan. 1, 2023, through Dec. 31, 2025, for all conditions.

The report began with a summary of patient population characteristics (Figure 1), comparing demographics, risk factors, readmission diagnoses, and comorbidities across each eligible cohort. The table was provided to help hospitals better understand the patient populations underlying the reporting for these six conditions/procedures.

Figure 1. Sample Blinded Table for a Hospital’s Patient Population Snapshot, Common Reasons for Readmission, and Frequent Comorbidities
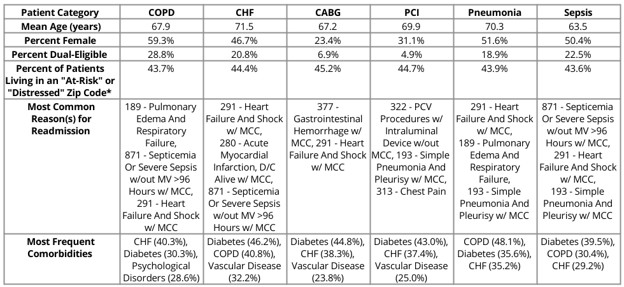
Comparison table summarizes demographics, risk factors, readmission diagnoses, and comorbidities across COPD, CHF, CABG, PCI, pneumonia, and sepsis patient categories. Mean age ranges from 63.5 years for sepsis to 71.5 for CHF; frequent readmission reasons include respiratory failure, heart failure or shock, gastrointestinal hemorrhage, myocardial infarction, and septicemia, while common comorbidities include CHF, diabetes, COPD, and chronic kidney disease.

The remainder of the report was comprised of condition-specific pages. MVC provided benchmarking figures for average 30-day risk-adjusted, price-standardized total episode payment and 30-day inpatient readmission rate for each condition. MVC price standardized total episode payments to Medicare FFS amounts so that comparisons could be made across hospitals and over time. Payments were risk-adjusted for patient age, gender, payer, comorbidities, and high or low prior healthcare utilization/payments. These figures showcased a given hospital’s position relative to all other eligible MVC hospitals in the collaborative and provided the average total episode payment within a hospital’s region and statewide.

Across the collaborative, CABG had the highest average total episode payment at $53,183 (Figure 2), followed by sepsis and CHF. The collaborative-wide average total episode payment for all conditions did not vary significantly between the 2025 report and the 2026 report. Readmissions were observed to be highest across the collaborative at 19.1% for patients hospitalized for CHF (Figure 3), followed by patients hospitalized for sepsis or COPD. Readmission rates were lowest across the collaborative at 5.4% among patients who underwent a PCI procedure.

Figure 2. Average 30-Day Risk-Adjusted, Price-Standardized Total Episode Payment Among Patients Hospitalized for CABG (Blinded Report)
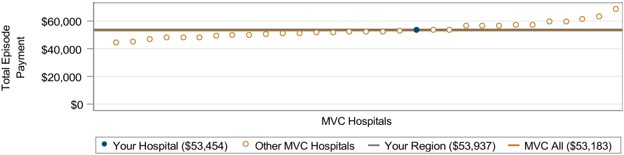
Caterpillar plot compares average 30-day risk-adjusted, price-standardized total episode payments for CABG patients across MVC hospitals. Orange circles show other hospitals trending upward from about $45,000 to $70,000, while markers identify Your Hospital at $53,454, Your Region at $53,937, and MVC All at $53,183.

Figure 3. 30-Day Readmission Rate Among Patients Hospitalized for CHF (Blinded Report)
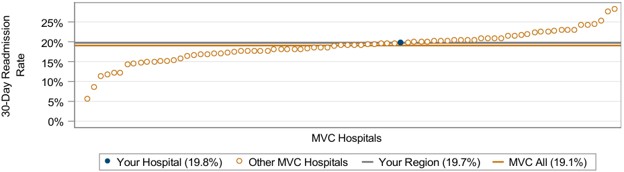
Caterpillar plot compares 30-day CHF readmission rates across MVC hospitals, with orange open circles rising from about 6% to 28%. Blue marker shows Your Hospital at 19.8%, while horizontal reference lines mark Your Region at 19.7% and MVC All at 19.1%.

The final figures on the condition-specific pages worked in tandem to display the utilization and cost components that made up a hospital’s average price-standardized, risk-adjusted post-acute care (PAC) payments in the 30 days following discharge. Most hospitals received a figure displaying the breakdown of 30-day risk-adjusted, price-standardized post-acute care payments by payer categories (Figure 4). All payer categories with at least 11 episodes during the reporting period were reflected, including a “Dual-Eligible” category representing patients eligible for both Medicare and Medicaid coverage; as such, Medicare and Medicaid categories did not include dual-eligible patients when that category was included. The post-acute care categories for both figures included home health care, skilled nursing facility (SNF) care, inpatient rehab, outpatient rehab, emergency department (ED) care, long-term acute care hospitals (LTACH), and outpatient services.

Figure 4. Breakdown by Payer of 30-Day Risk-Adjusted, Price-Standardized Total Post-Acute Care Payments Among Patients Who Had a CABG Procedure (Blinded Report)
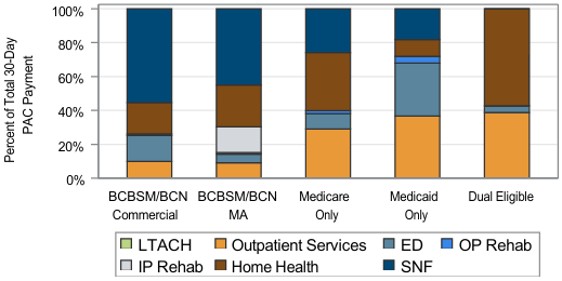
Stacked bar chart compares payer-specific shares of risk-adjusted, price-standardized 30-day post-acute care payments following CABG. Seven color-coded services show SNF dominating Commercial and Medicare Advantage payments, outpatient services prominent for Medicare Only, Medicaid Only, and Dual Eligible groups, and Home Health comprising most Dual Eligible payments.

Beyond offering insights into payments by payer and post-acute care category, this figure can offer additional insights and context when considered alongside Figure 5 showing post-acute care utilization rates. The two figures together served to provide a clearer understanding of the relationship between rates of utilization and percent of episode spending for each post-acute care category, illustrating whether spending aligns with utilization frequency. For example, payment categories with a high percentage of post-acute care payment in Figure 4 and a low overall utilization rate in Figure 5 may be indicative of low volume, high-cost outliers within a given condition at that hospital.

Figure 5. 30-Day Post-Acute Care Utilization Among Patients who had a CABG Procedure (Blinded Report)
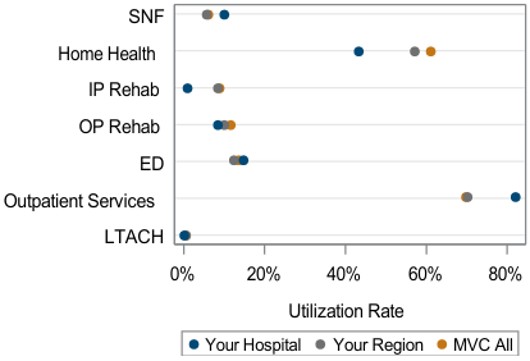
Dot plot compares 30-day post-acute care utilization after CABG across SNF, Home Health, IP Rehab, OP Rehab, ED, Outpatient Services, and LTACH. Blue, gray, and orange markers represent Your Hospital, Your Region, and MVC All; Outpatient Services shows highest utilization, while LTACH and IP Rehab remain near 0%.

MVC is dedicated to regularly updating its commons conditions report, aiming to equip collaborative partners with insightful data that can drive and reinforce meaningful advancements in healthcare quality. Please contact MVC with any questions or related analytic requests. If you require any digital accessibility accommodation, please let us know and we will be happy to provide alternative formats.

Off
View Post
MVC September Workgroup Highlights Sepsis Improvement Journey

MVC September Workgroup Highlights Sepsis Improvement Journey

In September, the Michigan Value Collaborative (MVC) hosted a sepsis workgroup featuring a presentation by McLaren Flint Hospital highlighting their sepsis improvement journey. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action. View the full 2027 MVC event calendar here.

Sepsis Workgroup: McLaren Flint Hospital

During this month’s sepsis workgroup, Kerri Tomasi-Herman, RN and Ali Arthur, BSN, RN, CCRN, Quality Improvement Specialist RNs at McLaren Flint, presented on the hospital’s work to strengthen sepsis processes over the past two years. Their presentation offered practical examples of how the team has used dashboards, daily auditing, nursing checklists, provider education, and interdisciplinary collaboration to address sepsis performance challenges.

McLaren Flint is a 378-bed hospital and Level III Trauma Center with high emergency department and inpatient volumes. Tomasi-Herman and Arthur began their presentation with a description of a significant transition in sepsis quality improvement beginning in 2025.

Previously, McLaren Flint relied on an on-site clinical abstractor and sepsis coordinator who reviewed sepsis patients, supported completion of the Centers for Medicare and Medicaid Services (CMS) sepsis bundle, and provided real-time assistance to nurses and providers. While they acknowledged this role as an important resource, the team recognized that relying heavily on one individual could mask underlying process issues.

In 2025, McLaren centralized sepsis abstraction across the hospital system. This shifted the role of the local quality improvement team toward real-time monitoring, intervention, feedback, and use of data to drive improvement.

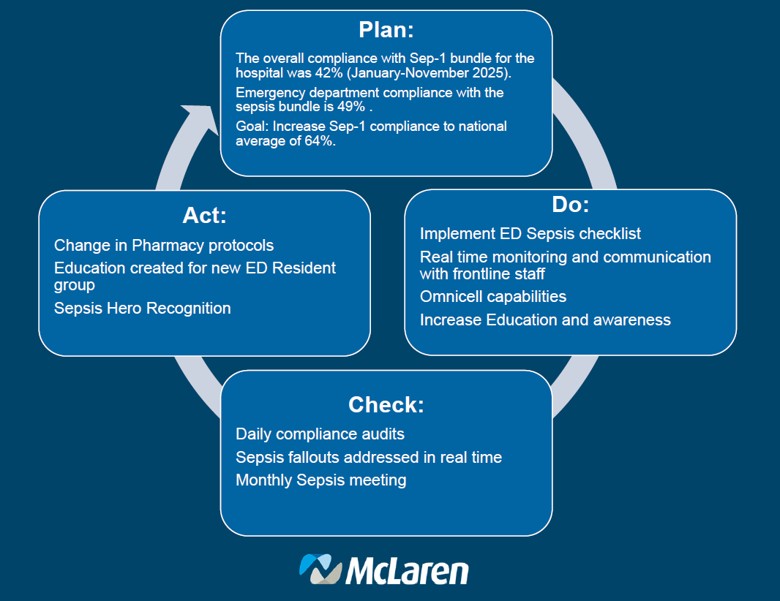
Figure 1. McLaren Flint’s PDCA Cycle Approach to Sepsis Improvement

Four-stage Plan, Do, Check, Act cycle diagram outlines a hospital sepsis-compliance improvement plan, using blue rounded boxes and gray circular arrows labeled Plan, Do, Check, and Act. Plan reports 42% Sep-1 bundle compliance, 49% emergency-department sepsis-bundle compliance, and a goal of reaching 64% national average; Do lists checklist implementation and monitoring, Check lists audits and monthly meetings, and Act lists pharmacy-protocol changes, resident education, and Sepsis Hero recognition.

Using Dashboard Data to Identify Opportunity for Improvement

Considering this shift towards real-time monitoring, a tool Tomasi-Herman and Arthur highlighted as key to their new workflow was the McLaren sepsis performance dashboard. The dashboard allows the quality team to see overall compliance as well as performance across different areas, including the emergency department (ED) and inpatient units.

The team uses this information during its monthly sepsis and quality improvement meetings across various clinical areas. Pareto charts help identify the most common causes of sepsis measure fallouts by service area to further pinpoint opportunities for improvement. This more detailed breakdown allows the team to tailor improvement strategies to specific departments and processes. For example, using this data they have found that within the ED, antibiotic administration most commonly contributes to sepsis fallouts, while for inpatient the most common issue is timely initial lactate orders.

The presenters emphasized that making this information visible to providers and hospital leaders has helped create greater awareness of performance and opportunities for improvement. McLaren Flint’s sepsis committee currently includes representatives from quality, medical staff, nursing, emergency medicine, intensive care unit, pharmacy and laboratory services with additional participants engaging when a specific fallout involves their department.

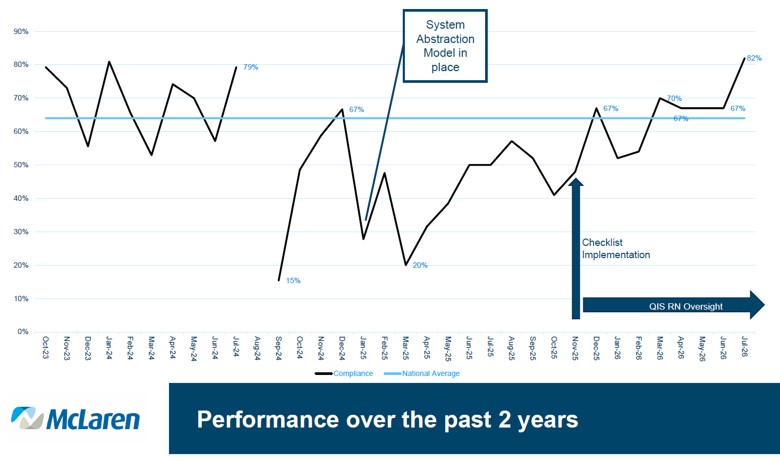
Figure 2. McLaren Flint’s Sepsis Performance Over the Past 2 Years

Line chart titled “Performance over past 2 years,” comparing compliance percentages against a 65% national average. Black compliance line fluctuates from 15% in Sept. 2024 to 82% in July 2026, indicating improvement since QI implementation. Callouts mark System Abstraction Model implementation in Jan. 2025 and Checklist Implementation and QIS RN Oversight in Nov. 2025.

Real-Time Monitoring Helps to Avoid Fallouts

Another major component of McLaren Flint’s approach is daily real-time monitoring. Each morning, the quality improvement team reviews their internal electronic medical record (EMR) sepsis worklist, which identifies patients meeting sepsis-related criteria. The team then follows patients in real time, monitoring whether appropriate orders for blood cultures, antibiotics and other elements of the bundle are completed.

When a potential delay is identified, the team provides real-time reminders to appropriate nurses and providers. They also review cases retrospectively and send follow-ups or documentation addendum requests when appropriate. This combination of real-time intervention and retrospective review allows the team to address individual cases while also identifying recurring process issues.

Reviewing individual fallout cases minute-by-minute offers the opportunity to determine whether the underlying issue was related to workflow, documentation, laboratory processes, or another factor. One example provided by the presenters involved antibiotic orders that were not being reviewed quickly enough by pharmacy. After identifying and bringing this item to the attention of the sepsis committee, the pharmacy department adjusted its process to prioritize validation of antibiotics associated with sepsis and infection-related orders. Since this process has changed, the turnaround time for medication validation has decreased to less than 10 minutes.

Introduction of ED Sepsis Checklist

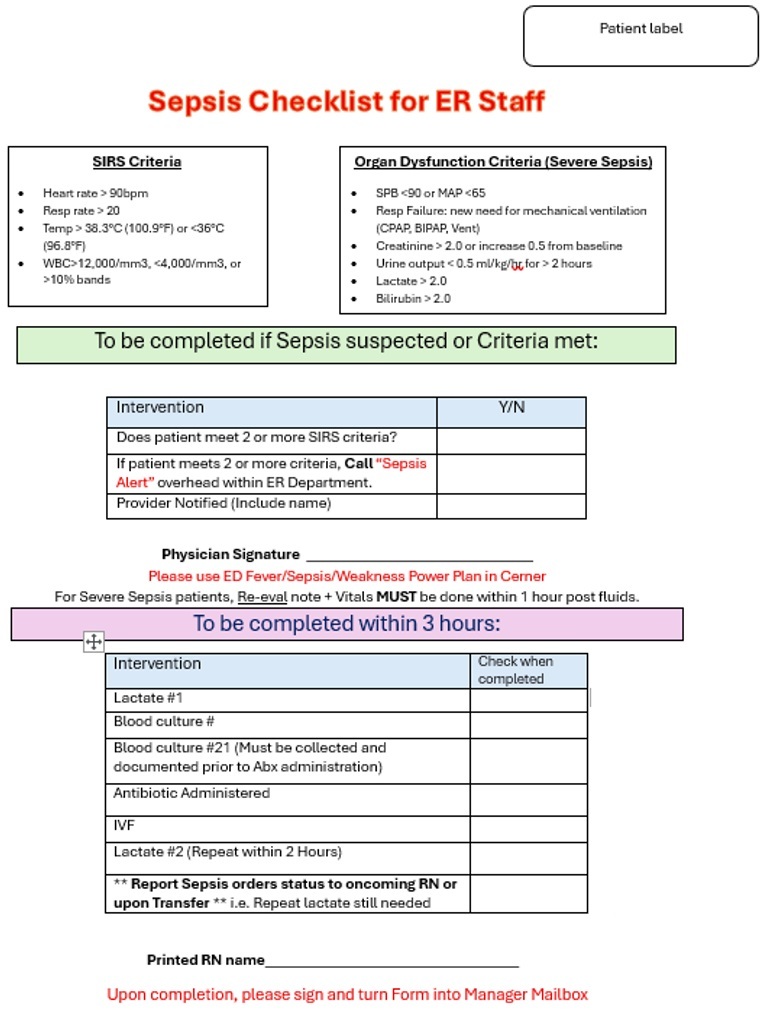
Because McLaren’s EMR system does not include a built-in sepsis nursing flowsheet or navigator, the team decided to design a paper-based tool. McLaren Flint implemented this sepsis checklist first within their ED. The checklist highlights systemic inflammatory response syndrome (SIRS). SIRS criteria checks for organ disfunction and is intended to prompt nurses to bring potential sepsis concerns to their physician as early as possible.

The checklist has gone through several revisions based on feedback from frontline staff. Together, they have worked to create a simplified tool that functions as a practical guide for nursing staff. These checklists are collected at the end of shifts and compared to patients identified through the EMR worklist to monitor utilization and compliance among staff.

Figure 3. McLaren Flint’s Sepsis Checklist for Emergency Room (ER) Staff

Clinical checklist form titled “Sepsis Checklist for ER Staff,” designed to screen suspected sepsis using SIRS and severe organ-dysfunction criteria. Red, green, blue, and purple sections organize patient labeling, SIRS thresholds, sepsis-alert instructions, physician signature, and three-hour interventions including lactate tests, blood cultures, antibiotics, and IV fluids.

Engagement of Frontline Staff

In addition to engaging frontline staff with the development of the sepsis checklist, McLaren Flint shared a creative strategy for building engagement: the Sepsis Hero Award.

This award was revived to recognize nurses and providers who demonstrate strong sepsis performance and engagement. A recent recipient was acknowledged for high checklist compliance, positive attitude, and having no sepsis fallouts.

This recognition has become a source of positive competition among ED staff, with team members becoming increasingly interested in being recognized for their contributions. This demonstrates the power recognition can have on complimenting data and education by making improvement efforts visible and celebrating frontline participation.

Looking Ahead to Continuous Improvement

Near the end of the workgroup, Tomasi-Herman and Arthur reflected that while McLaren Flint has made great progress, they continue to identify areas for improvement. One challenge they have identified is that their EMR-based automated sepsis alerts do not always align with CMS sepsis requirements, resulting in some false alerts. They have also identified limitations to their EMR configuration and opportunities to strengthen the recognition of sepsis patients receiving care on inpatient floors, particularly when a patient’s condition evolves after admission.

Looking ahead, McLaren Flint plans to continue educating ED staff, including their new medical resident program, promote standardized sepsis documentation, and monitor inpatient sepsis alerts.  The team is also working to recruit frontline nurses or providers to serve as sepsis champions and participate in monthly sepsis meetings, continuing to bring frontline perspectives into the hospital’s quality improvement work.

Key Takeaways for MVC Members:

McLaren Flint’s presentation offered several practical strategies that other hospitals may consider when aiming to strengthen their sepsis improvement efforts:

  1. User performance data to identify specific process opportunities – rather than relying solely on compliance rate
  2. Pair real time monitoring with retrospective review – to address potential gaps before they become measurable fallouts
  3. Create simple frontline tools – when EHR functionality does not fully support a desired workflow
  4. Celebrate staff contributions – through recognition and awards
  5. Bring multiple disciplines together – to identify and address system-level barriers
  6. Share performance transparently – with providers, managers, and clinical leaders to build awareness and accountability

MVC Sepsis Workgroup: Sept. 15, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to the Coordinating Center by email if you are interested in being a workgroup presenter or submit a presentation proposal here.

Off
View Post
Fall Collaborative-Wide Meeting Agenda, Speakers Announced

Fall Collaborative-Wide Meeting Agenda, Speakers Announced

The MVC Coordinating Center is excited to announce the agenda for its fall collaborative-wide meeting on Friday, October 9, 2026, from 10 a.m. – 3 p.m., at Vistatech in Livonia, MI. This meeting’s theme is “Unlocking Data for QI Impact: Translating Insights into Action” and will feature opportunities to learn about the various ways in which MVC's members are leveraging MVC data and resources to drive quality improvement locally and across Michigan. Those interested in attending MVC's fall 2026 collaborative-wide meeting must register here by Tuesday, September 22.

MVC Director Mark Bradshaw, MSc, will kick off the day with updates on MVC’s Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This will be followed by a presentation by MVC Medical Director, Hari Nathan, MD, PhD, “From Performance to Action: Putting MVC Data to Work.” A poster session with presentations from McLaren Greater Lansing Hospital, Trinity Health Grand Haven Hospital, Bronson Methodist Hospital, Henry Ford Hospital, Oaklawn Hospital, and MVC will follow Dr. Nathan’s presentation.

After the poster session, Dr. Kevin Bohnsack and Belinda Dokic, CPhT, BA, MBA, from Trinity Health of Michigan will take the podium to present their work on “Reducing Readmissions Through Data and Analytics.” Attendees will then have time to network with peers over lunch before transitioning into two consecutive breakout sessions.

The four breakout topics will cover:

  • Holland Hospital’s Transitional Heart Failure Program (THFP). Holland Hospital credits THFP as a primary driver of their success on MVC’s congestive heart failure (CHF) episode spending and 7-day follow up measure.
  • Corewell Health System’s approach to engaging with MVC and leveraging MVC data as a unified system.
  • DMC Huron Valley Sinai's partnership with Michigan Surgical Quality Collaborative (MSQC) and MVC to strengthen adherence to evidence-based quality measures in colorectal cancer surgery and drive better short- and long-term outcomes for patients.
  • Key principles and available resources that support strategic metric selection for the MVC component of the BCBSM P4P Program to help MVC members identify their greatest opportunities for improvement across MVC metrics.

MVC Site Engagement Coordinator Rachel Folk, MHA, will close out the day and discuss next steps for MVC’s Component of the BCBSM P4P Program.

The last day to register for MVC’s fall 2026 collaborative-wide meeting is Tuesday, September 22. We look forward to seeing you there!

Off
View Post
MVC Coordinating Center: Serving the Community Through Service Days

MVC Coordinating Center: Serving the Community Through Service Days

Over the years, the MVC Coordinating Center has spent time creating a set of fundamental principles that we strive to underpin our everyday culture. Our core values of collaboration, respect, curiosity, and courage continue to prove extremely valuable in helping guide our ongoing activity and shape how we work and interact with MVC members and other stakeholders. One such way in which the MVC team has put these core values into action over the last twelve months is through our regular volunteering efforts with the local community. In the last year, the MVC team has spent time partnering with the Ronald McDonald House, MHealthy, and Ann Arbor Parks and Recreation to build connections, strengthen relationships, and extend impact beyond our four walls.

The Ronald McDonald House in Ann Arbor (RMHCAA) is a special place that provides a supportive home away from home for families of children receiving treatment. Since opening three decades ago, RMHCAA has welcomed over 26,000 families, offering comfortable living spaces in close proximity to the hospital so that family members can take care of themselves knowing their child is just minutes away. As part of this support, families are not only provided with a place to stay but are also cared for in many other ways, including the provision of hot meals. These dinners provide families with a break from the hospital and time away to connect with others going through similar experiences.

Towards the end of last year, the MVC team were fortunate to spend some time supporting this great endeavor. Representatives from MVC participated in the program’s “Chef for a Day” initiative, planning, shopping, and delivering a home-cooked meal for the families. This volunteering experience was extremely meaningful and reminded us of what remains at the center of MVC’s daily work – ensuring patients and caregivers in Michigan receive the right care and feel supported throughout their care journey. We’ll be back volunteering with RMHCAA towards the end of this year and if you too are interested in sharing your time or donating, you can find out more here.

Photograph of MVC Coordinating Center team volunteering at RMHCAA wearing blue aprons standing behind a kitchen counter filled with multiple meal prep containers of food.

MVC Coordinating Center team volunteering at RMHCAA

Fast forward to summer (if only…) and our next volunteering event took us to supporting MHealthy’s “Project Healthy Schools” (PHS) program. PHS is a school-based health promotion program designed to prevent childhood obesity and improve the present and future health of youth. For two decades, PHS has used interactive lessons and wellness activities to help middle school students and staff increase physical activity, eat healthier, and truly understand how nutrition and exercise can influence lifelong health.

In April of this year, the MVC team spent time supporting the organization’s “Maize and Blue Health U” event at the Big House. This gave us the chance to prove we are all still athletes at heart, partnering with University of Michigan student athletes to deliver engaging and fun physical activity exercises to over 330 students from four different middle schools. We might have been sore the next morning but as a team, we found great value in extending our commitment to sustainable, high-value healthcare beyond the clinical setting and into the student community.

Photograph of MVC Coordinating Center team on the football field of University of Michigan "Big House"

MVC Coordinating Center team volunteering for MHealthy’s “Project Healthy Schools” (PHS) “Maize and Blue Health U” event at the Big House

Our most recent volunteering activity with Ann Arbor Parks and Recreation took us to Leslie Park for a park cleanup day. Our local parks and built environment play a key role in creating accessible spaces for people to play, exercise, connect, and quite simply, spend time outdoors. This, in turn, impacts directly on physical health and mental wellbeing. Spending time as a team to support park cleanup is a simple and effective way of investing in the health of those in our community. After a good few hours picking weeds, the park’s play structure was ready for action again, providing a fun space for kids (and their adults) to get outside and be active.

Photograph of MVC Coordinating Center team volunteering with Ann Arbor Parks and Recreation at Leslie Park posing on and around playground equipment.

To learn more about the organizations mentioned, please visit the websites of Ronald McDonald House Ann Arbor, Project Healthy Schools, and Ann Arbor Parks and Recreation. If your team has a similar partnership in place with a local community-based organization then please let us know – we would be happy to highlight this work on your behalf. Similarly, if you are interested in partnering with the MVC team on an upcoming volunteering activity, we would love to explore a potential collaboration.

Off
View Post
MVC Thanks Presenters from the First Half of 2026

MVC Thanks Presenters from the First Half of 2026

The MVC Coordinating Center wishes to express its heartfelt appreciation for the 39 generous healthcare professionals who stepped forward to present during MVC’s first and second quarter virtual workgroups, spring collaborative-wide meeting, and Michigan Cardiac Rehabilitation network (MiCR) virtual forums on telehealth rehabilitation. The MVC Coordinating Center would not be able to deliver the variety of high-quality educational opportunities without the contribution of these dedicated volunteer presenters. We know that MVC’s members and partners have many demands on their time from within their own organizations and beyond. Nonetheless, these 39 guest speakers shared their data, innovative approaches, best practices, and insights to support our shared goals of peer learning and high-value care delivery for Michigan patients. We appreciate you contributing in this important way. You DO make a difference!

Join us in giving these folks a well-deserved round of applause:

Cardiac Rehab Workgroup

  • Robert Berry, MS, ACSM-CEP, FAACVPR, Clinical Coordinator Cardiac Rehabilitation, Henry Ford Health Henry Ford Hospital
  • Zach Johnson, BS, ACSM-CEP, Lead Exercise Physiologist for Cardiac and Pulmonary Rehab Programs, Corewell Health
  • Steven Keteyian, PhD, Bioscientific Clinical Staff, Division of Cardiovascular Medicine, Henry Ford Health Henry Ford Hospital
  • Laura Meiste, RN, BSN, Manager of Cardiac and Pulmonary Rehab, Holland Hospital
  • Greg Scharf, BS, CEP, CCRP, Cardiopulmonary Rehab System Manager, MyMichigan Health
  • Mike Thompson, PhD, FAHA Associate Professor of Cardiac Surgery, Michigan Medicine
  • Tyelor Wymer, CEP, BS, Cardiology Supervisor, University of Michigan Health-Sparrow

Health in Action Workgroup

  • Jennifer Hengy, BSN, RN, Internal Quality Improvement Specialist Sr., Corewell Health Farmington Hills
  • Alexander Janke, MD, MHS, MSc, Assistant Professor of Emergency Medicine, University of Michigan
  • Eugene Laveroni, MD, Chief of Surgery, Corewell Health Farmington Hills
  • Florian Schmitzberger, MD, MS, Clinical Assistant Professor of Emergency Medicine, University of Michigan
  • Leslie Smith, RPh, JD, BCPS, BCIDP, Clinical Pharmacist Specialist, Corewell Health Farmington Hills

Post-Discharge Follow-Up Workgroup

  • Steven Frazier, BA, RN, ACM-RN, Director of Quality and Patient Safety Post-Acute, MyMichigan Health System
  • John Hagan, DO, Medical Director - Care Coordinating Center, MyMichigan Health System

Rural Health Workgroup

  • Heather Baumeister, BSN, RN, CRHCP, Director of Healthcare Practices, McKenzie Health System

Sepsis Workgroup

  • Tami Garcia, MSN, RN, Sepsis Process Lead, Michigan Medicine
  • Carly Redstone, MSN, RN, Sepsis Coordinator, Michigan Medicine

Spring Collaborative-Wide Meeting Panelists

  • Alex Callaway, MBA, CPHQ, CPPS, Regional Quality Director, Munson Health System
  • Emily Nerreter, MBA, CPC, CRC, Pay for Performance & Registries Manager, Henry Ford Health System
  • Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Analysis & Enhancement, MyMichigan Health

Spring Collaborative-Wide Meeting Breakout Session Speakers

  • Belinda Dokic, CPhT, BA, MBA, Post-Acute Care Manager, Trinity Health Alliance of Michigan
  • Cindy Ingersoll, RN, BSN, CCM, Post-Acute Care Manager, Trinity Health Alliance of Michigan
  • Adrien Ross, MSN, RN, CPHQ, Lead, Quality Improvement Specialist, Corewell Health
  • Heidi Steinhebel, RN, BSN, CCM, Senior Associate Director of Care Management, Trinity Health IHA Medical Group
  • Caitlin Valley, MHA, MPH, CHES, Director of Quality and Population Health, Trinity Health IHA Medical Group
  • Larrea Young, MDes, Multimedia Design Project Manager, Healthy Behavior Optimization for Michigan

Spring Collaborative-Wide Meeting Poster Presenters

  • Jennifer Bennett, MBA, BSN, RN, Lead Quality and Patient Safety Coordinator, Henry Ford Health Madison Heights-Warren Hospital
  • Sara Hagerman, BSN, RN, Community Hospital Quality Lead, University of Michigan Health – Sparrow Carson
  • Ginger Johnson, OTR, Manager Post-Acute Care, Populance, Henry Ford Health System
  • Mike Johnson, Primary Care Practice Administrator, Munson Healthcare East Region
  • Liz Monk, System Director of Patient Care Manager, Munson Healthcare
  • Gloria Rey, PA-C, MPH, Director Post-Acute Care, Populance, Henry Ford Health System
  • Audra Stoker, PMP, Manager Post-Acute Care Network Development, Populance, Henry Ford Health System

Virtual Networking Event

  • Richard Wylde, MSc, Deputy Director of Improvement at Leeds and York Partnership NHS Foundation Trust

MiCR Virtual Forums on Telehealth Cardiac Rehabilitation

  • Robert Berry, MS, ACSM-CEP FAACVPR, Clinical Coordinator of Cardiac Rehabilitation, Henry Ford Health
  • Samantha Fink, BS, Administrative Manager, Domino’s Farms Cardiology, Michigan Medicine
  • Steven J. Keteyian, PhD, Bioscientific Clinical Staff, Division of Cardiovascular Medicine, Henry Ford Hospital
  • Diane Perry, MS, ACSM-CCEP, CHWC, Certified Clinical Exercise Physiologist, Michigan Medicine
  • Kat Steenson, MS, Clinical Exercise Physiologist, Henry Ford Health
Graphic design featuring silhouettes of eight business people standing above bold text reading "THANK YOU" on a blue bokeh background. Two circular shapes contain Michigan Value Collaborative logo on left and text "From all of us at MVC" on right, expressing gratitude from the organization.

The MVC members and partners who attend MVC events appreciated these presenters, too. Here are just a few of the many glowing survey responses MVC received about presenters and their content in the first half of 2026.

Screenshot of five positive testimonial quotes about MVC workgroups and collaborative-wide meetings, displayed in white text with orange quotation mark icons on a blue background. Quotes highlight benefits such as insightful content, flexible conversation, valuable information sharing, and practical application for sepsis process development in emergency department triage.

As a reminder, past workgroups and virtual networking event recordings can be viewed on MVC’s YouTube channel, and presentation slides and materials from MVC’s spring collaborative-wide meeting can be viewed here.

Do you have valuable information to share?

Whether you are new to presenting or a seasoned pro, the MVC Coordinating Center is here to support you every step of the way. From exploring topic ideas to preparing information and managing event logistics, our team makes the experience of presenting easy and comfortable. The P4P points you can earn as a presenter are a great benefit to your organization, too. For more information about presenting, contact the MVC Coordinating Center or submit a proposal here.

Off
View Post
Key Takeaways from MiCR’s First Telehealth Cardiac Rehab Forum

Key Takeaways from MiCR’s First Telehealth Cardiac Rehab Forum

Since 2019, the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2) and the Michigan Value Collaborative (MVC) have worked together to improve cardiac rehabilitation utilization in Michigan. This collaboration led to the founding of the Michigan Cardiac Rehabilitation network (MiCR) in 2022, a partnership that endeavors to increase participation in cardiac rehab for all eligible individuals in Michigan through clinical practice sharing, networking, data benchmarking, and the dissemination of resources.

On April 17, MiCR invited practitioners from across Michigan to discuss the evolving role of virtual and hybrid cardiac rehabilitation programming amidst recent legislative wins. In February, Congress advanced the Consolidated Appropriations Act, 2026 (H.R. 7148), which extends Medicare telehealth and in-home cardiopulmonary rehabilitation flexibilities through December 31, 2027. With this extension, cardiac, intensive cardiac, and pulmonary rehab programs in both hospital outpatient and physician office settings can continue delivering services virtually using two-way audio and video technology through the end of 2027. This two-year window gives programs the opportunity to launch or expand hybrid rehab models, try new approaches to reach patients who have difficulty attending in-person sessions, and plan with greater confidence while longer-term policy solutions are explored.

MiCR kicked off the forum emphasizing its mission and the progress made to date in statewide enrollment, with participation rates for eligible cardiac patients across the collaborative increasing from 24% in 2020 to 35% in 2024. Despite progress being made, the state is still short of the MiCR goal of 40% enrollment within 90 days of discharge from eligible procedures (Figure 1), as well as the Million Hearts goal of 70% enrollment.

Figure 1. Trends in cardiac rehab enrollment within 90 days of discharge from AMI, CABG, PCI, SAVR, or TAVR encounter

Line graph showing yearly trends in cardiac rehab participation within 90 days of discharge from various cardiac procedures between 2020 and 2024. The graph compares actual MVC participation rates, increasing from 24% in 2020 to 35% in 2024, against a constant MiCR goal of 40%, highlighting a gradual upward trend.

MiCR conducted a short survey in 2025 about telehealth programming in cardiac rehab to better understand opportunities to close the enrollment gap using telehealth, and how leaders and care teams feel about offering telehealth options. Of the 27 cardiac rehab sites that responded, only two were currently offering some form of virtual cardiac rehab, while some others expressed interest in launching or further investigating virtual service options.

Defining Cardiac Rehab Delivery Models

Prior to initiating a discussion, MiCR reviewed several key definitions to clarify terminology surrounding evolving cardiac rehab delivery models:

  • Traditional in-center delivery: synchronous, in-person care
  • Virtual delivery: synchronous, real-time, audio-visual communication
  • Remote delivery: asynchronous communication between patients and providers
  • Hybrid delivery: use of more than one of the methods noted above.

The forum focused primarily on virtual and hybrid delivery approaches given insurance reimbursement stipulations. MiCR emphasized how hybrid models may offer optimal opportunities for organizations to balance flexibility, patient engagement, and clinical oversight.

Health Systems Share Real-World Virtual Cardiac Rehab Experiences

The forum next featured presentations from two Michigan hospitals currently offering virtual or hybrid cardiac rehab programming.

Henry Ford Health

Steven Keteyian, PhD, Bioscientific Clinical Staff in the Division of Cardiovascular Medicine, and Kat Steenson, MS, Clinical Exercise Physiologist, shared insights into Henry Ford Health’s hybrid cardiac rehab model, including their group virtual session structure.

Dr. Keteyian spoke to the importance of designing a virtual program as similar to current in-center facility programming as possible – including using the same forms, outcome measures, even times that the classes are offered. He noted that this simple mindset may help to streamline implementation and workflows. Additionally, Dr. Keteyian encouraged programs considering virtual care to engage physician champions and optimize internal billing support when getting started.

Steenson discussed her experience delivering both traditional in-center and virtual cardiac rehab care and highlighted the important opportunity virtual delivery offers to extend services to patients facing transportation, scheduling, or geographic barriers. She also encouraged sites to develop virtual programming in line with current in-person practices, noting that this makes it easier on the staff ultimately delivering the services.

Michigan Medicine

Next, Samantha Fink, Administrative Manager of Domino’s Farms Cardiology, and Diane Perry, MS, ACSM-CCEP, CHWC, Certified Clinical Exercise Physiologist, outlined Michigan Medicine’s participation in a research pilot for virtual cardiac rehab delivery over the last two years.

Fink highlighted the importance of combining operational planning, process improvement, and patient accessibility initiatives when initially building virtual programs. She noted that while their patients expressed significant interest in virtual options, not all were set up for success—lacking reliable technology, exercise equipment, or appropriate health screenings prior to starting virtual cardiac rehab. Fink also encouraged sites to establish clear emergency protocols and steps for assessing the appropriateness of virtual care.

Perry then shared her perspective as an exercise physiologist on adapting patient support, exercise guidance, and engagement strategies for the virtual environment. She also endorsed a hybrid program, and she spoke in more detail about the importance of in-person initial assessments to confirm the appropriateness of virtual cardiac rehab.

Telehealth as a Tool to Improve Access

After introducing example programs, MiCR Co-Directors Jessica Golbus, MD, MS, and Michael Thompson, PhD, MPH, facilitated a panel discussion on future implementation opportunities, reimbursement considerations, and collaborative learning across Michigan programs.

Throughout the discussion, the panelists repeatedly emphasized that virtual cardiac rehab is not intended to replace traditional in-center rehab but rather enhance access and reduce long-standing barriers to participation. The panelists pointed out that virtual and hybrid approaches may help programs better serve patients with access barriers, such as rural patients, individuals with transportation limitations, working adults, caregivers, and patients with scheduling challenges. Discussion also reinforced that flexibility in care delivery models may improve patient adherence and completion rates. Lastly, the panelists underscored that successful digital transformation in healthcare is less about chasing trends and more about building practical, individualized programs that improve visibility, efficiency, and accessibility.

The webinar concluded with a call for continued innovation and collaboration as health systems explore new ways to improve cardiac rehab participation. With the extension of federal telehealth flexibilities through the end of 2027, presenters encouraged hospitals to consider this time as an opportunity to pilot, expand, and evaluate virtual cardiac rehab programs. For those interested in learning more about virtual cardiac rehab, the following resources may assist your organization’s journey:

Additionally, you can reference the recording of this forum via YouTube.

MiCR will host a second virtual forum discussion on Tues., June 9, from 12-1 p.m. featuring a demonstration of Henry Ford Health’s group virtual cardiac rehab programming. Registration is available now.

Off
View Post
MVC 2026 Spring Collaborative-Wide Meeting Summary – From Innovation to Impact: Advancing Care Across Health Networks

MVC 2026 Spring Collaborative-Wide Meeting Summary – From Innovation to Impact: Advancing Care Across Health Networks

The Michigan Value Collaborative (MVC) held its spring 2026 collaborative-wide meeting on Fri., May 8, in Traverse City, Michigan. A total of 84 attendees representing 48 hospitals, 16 multi-hospital systems, and seven physician organizations from throughout the state of Michigan explored strategies for elevating quality across integrated health networks through the lens of system-wide alignment and data-driven improvement.

MVC Director Mark Bradshaw, MSc, began Friday’s meeting with updates on the MVC Coordinating Center and the MVC Component of the BCBSM P4P Program [see slides]. He first introduced attendees to MVC’s newest team members, Senior Faculty Advisor Ryan Howard, MD, MS, and Lead Analyst Megan Heath, PhD. Bradshaw then provided an update on recent MVC reporting since the fall collaborative-wide meeting, including 12 hospital-level custom reports, a push report focused on follow-up utilization, and the P4P Program Year (PY) 2025 final scorecards. It was further announced that MVC’s registry was recently updated with new payer data, including three new months of BCBSM/BCN claims and three new quarters of Medicare FFS claims.

He also provided an update on MVC’s new site coordinator education program. With a total of 31 site coordinators enrolled thus far in 2026, he encouraged those interested in starting in Q4 of 2026 or Q1 of 2027 to join the waitlist for this individualized educational offering [registration link].

Bradshaw next summarized updates on the Michigan Cardiac Rehab network’s (MiCR) efforts to improve cardiac rehabilitation utilization. These include an upcoming MiCR virtual forum featuring a group cardiac rehab demo [registration link], a third round of NewBeat material orders, and Heart-to-Heart patient stories. Additionally, he summarized the status of MiCR’s medication management initiative. If interested in participating in an interview on this topic, please contact MVC via email [email link].

After providing MVC Coordinating Center updates, Bradshaw moved on to provide insights into final scoring of P4P PY 2025 (see Figures 1-3), which included slight increases in average total points scored from PY 2024, some improvements in engagement point scoring, and continued scoring success for value metrics tied to MVC’s value-based initiatives (e.g., cardiac rehab and preoperative testing metrics).

Figure 1. Distribution of MVC’s P4P PY 2025 Total Points

Line chart displays final scores of MVC hospitals participating in PY 24-25 program, with scores plotted as blue dots ranging from 2 to 10. Horizontal lines indicate mean score of 6.7 in orange and median score of 6.0 in gray, highlighting most hospitals scoring above median with several reaching 10 out of 10.

Figure 2. MVC’s P4P PY 2025 Scoring Breakdown by Episode Spending and Value Metric Selections

Horizontal bar chart comparing PY 25 episode spending scores and value metric scores across medical conditions and procedures. Spending scores range from 1.5 for Pneumonia to 2.9 for CABG, while value metric scores range from 2.0 for 7-day follow-up after Pneumonia to 3.7 for Preoperative Testing, with mean and median values indicated for each group.

Figure 3. MVC’s P4P PY 2025 Engagement Point Distribution

Scatter plot showing engagement scores of MVC hospitals participating in PY 24-25 program, with individual hospital scores represented by blue dots and a mean score of 1.8 marked by an orange horizontal line. Most hospitals achieve or exceed the mean score, with several reaching the maximum score of 2.0, indicating high engagement levels across participants.

After reviewing hospital performance in 2025, Bradshaw looked to the PY 2026-2027 cycle, announcing a one-time alternative point opportunity for PY 2026 to earn credit for MVC’s new health outcome variation (HOV) metric. Additional details on submission requirements and timelines will be announced to site coordinators in the coming weeks. Following this, he noted the many opportunities to earn engagement points remaining in calendar year 2026 including virtual workgroups, networking dinners, and MVC’s fall collaborative-wide meeting in Livonia. For a complete schedule of events and registration, please visit MVC’s events webpage. Bradshaw reminded members that PY 2026 mid-year scorecards are expected in Q3 2026, and hospitals will be asked to make metric selections for PYs 2028-2029 in Q4 2026.

The meeting then featured an MVC data presentation by MVC Medical Director Hari Nathan, MD, PhD, and MVC Analyst Janet Zhang, MPH, on reporting and benchmarking outcomes across Michigan health systems. Dr. Nathan began with a discussion on the gradual, structural shift over the last two decades from independent ownership towards health system affiliation, noting that Michigan has outpaced national averages for system affiliation. He then reviewed the current state of MVC’s system-level reporting and outlined other measures of system variation from the literature not currently utilized in MVC reporting (Figure 4), emphasizing the need for MVC and its membership to co-design a path for measuring system-level quality in the future.

Zhang supplemented the presentation by sharing unblinded data on variation in hospital-level risk-adjusted 30-day readmission rates within hospital systems. She outlined traditional methods of showcasing variation using caterpillar plots and demonstrated how MVC might leverage hospital-level data to calculate a single index value for systems to support tracking variation over time. Zhang and Dr. Nathan both emphasized the importance of considering quality in outcomes and variation in outcomes as they evaluate their system-level performance.

Figure 4. Sample Approaches to Measuring System Variation

Table presenting system characteristics, relevant metrics, and rationales for surgical care quality assessment. It includes metrics like Herfindahl–Hirschman Index for centralization, case volume percentages for surgery avoidance and selective referral, and ambulatory surgery distribution, highlighting standards, care optimization, and resource allocation.

Building on the data presentation, a panel discussion led by Dr. Nathan further explored what “systemness” and system quality of care mean in practice and how stronger integration can improve quality, outcomes, and access across health systems and networks. Panelists included Alex Callaway, MBA, CPHQ, CPPS, Regional Quality Director of Munson Health System; Emily Nerreter, MBA, CPC, CRC, Pay for Performance & Registries Manager of Henry Ford Health System; and Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Analysis & Enhancement of MyMichigan Health. Each panelist brought unique perspectives and experience to the discussion, presenting compelling evidence to support the optimization of system-level resources, data, and cooperation.

Attendees then spent the remainder of the morning in breakout sessions [see breakout session slides] learning from peers, sharing intervention success stories, and brainstorming approaches to measuring quality in both small, stand-alone hospitals and large multi-hospital systems:

  • Catalyst Community for Improvement: Transforming Performance Together (Corewell)
  • Roadmap to Building Strong Post-Acute Care Network (Trinity Health Alliance)
  • Developing a Heart Failure Care Management Program (Trinity Health IHA)
  • Rural & Critical Access Hospital Claims Data Reporting Strategies (MVC)
  • Advancing System-Level Quality Improvement: Exploring Concepts for New MVC Metrics (MVC)

Following a networking lunch and a second session of breakouts, attendees came back together for the presentation of MVC awards by Engagement Manager Jessica Souva, MSN, RN, C-ONQS. The 2025 Engagement Award recipients included:

  • Henry Ford Health – 2025 Most Engaged System
  • Primary Care Partners, Inc. - 2025 Most Engaged Physician Organization
  • Scheurer Health – 2025 Most Engaged Critical Access Hospital
  • University of Michigan Health-West – 2025 Most Engaged General Acute Care Hospital

Souva also announced the winner of the poster contest, which was identified through member voting during the afternoon poster session. University of Michigan Health – Sparrow Carson won “best poster” for their “Rural Sepsis Initiative: Timely Care, Better Outcomes” poster submission. The poster was presented by Sara Hagerman, BSN.

The meeting closed with a reflection of the day’s themes and sessions, and reminders about upcoming meetings and events.

What are attendees saying about the meeting?

“The interactive sessions were great, and so was the location.”

“Today was a really great day, filled with a lot of discussion, networking and interactive activities.”

“This was my first meeting. I appreciate the information shared and opportunity.”

“I liked the panel discussion today. In the past, I also like the different tables of presenters to allow for smaller group discussion. Overall, lots of good discussion on how to work in a system.”

“Always love coming to MVC collaborative wide meetings as they’re so informative and a great way to network with others who have the same or very similar goals and outcomes!”

“The information presented was highly applicable across systems and independents.”

If you have questions about any of the topics discussed at MVC’s spring collaborative-wide meeting or are interested in following up for more details, please email the MVC Coordinating Center. MVC’s next collaborative-wide meeting will be held in person on Fri., Oct. 9, 2026, in Livonia, Michigan.

Off
View Post
April Workgroup Features Preoperative Testing Multipayer Report Registry Demonstration

April Workgroup Features Preoperative Testing Multipayer Report Registry Demonstration

In April, the Michigan Value Collaborative (MVC) hosted a virtual preoperative testing workgroup featuring a presentation by the MVC Coordinating Center focused on utilizing MVC’s multi-payer preoperative testing registry reports. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Preoperative Testing Workgroup – MVC Coordinating Center

The MVC registry includes many different reports for members to utilize when investigating various conditions, procedures, and outcomes. One of the more recent additions includes the preoperative testing reports which include claims data from multiple payers in one location. Reports that were highlighted in the preoperative testing workgroup included the preoperative testing table report, preoperative testing trends report, and preoperative testing utilization rankings report.

Each report offers members multiple filters to modify the data shown including episode start dates, payer selection, specific conditions (or the option to choose all), several common preoperative tests, such as blood tests, cardiac tests, chest x-ray, electrocardiography (EKG), pulmonary function tests, and urinalysis, and patient demographics (age, gender, race/ethnicity, comorbidities).

MVC Site Engagement Coordinator and workgroup presenter Emily Bair, MS, MPH, RDN, introduced the workgroup by sharing a preoperative testing utilization trend graph that included data on all MVC members and all available payers. The graph demonstrated that since the implementation of the preoperative testing value-based initiative in 2020, MVC members have seen a 6% decrease in unnecessary preoperative testing utilization for specific low-risk procedures. Based on available claims data, preop testing rates across the collaborative have declined from approximately 44% to 38% since 2022.

MVC’s preoperative testing measure definition includes the following:

  1. Numerator: episodes of care where preoperative testing (e.g., urinalysis, pulmonary function, chest x-ray, electrocardiography, certain blood tests, and certain cardiac tests) occurred in the 30 days prior to MVC-defined low-risk laparoscopic cholecystectomy, inguinal hernia repair, and lumpectomy procedures.
  2. Denominator: Elective and outpatient MVC-defined cholecystectomy, inguinal hernia repair and lumpectomy episodes with length of stay between 0 – 2 days.

The preoperative testing initiative, known as the RITE-Size initiative, has been an ongoing collaborative effort between MVC, the Michigan Surgical Quality Collaborative (MSQC), Anesthesiology Performance Improvement and Reporting Exchange (ASPIRE), and the Michigan Program on Value Enhancement (MPrOVE). MVC and MSQC data registries were updated with preoperative testing metrics to improve visibility for members, give access to diverse data, and offer unique customization tools for preoperative testing reports. The MVC engagement team has an ongoing effort to engage and educate members on all of the resources available to them through our registry and data reports. To learn more about attendee usage of MVC data, Bair polled participants to assess whether they had accessed the preoperative testing reports, and if so, whether they used the data in any quality improvement (QI) efforts at their site or system (Figures 1 and 2).

Figure 1. Poll: Have You Accessed MVC’s Multi-payer Reports?

Bar chart showing participant responses to accessing MVC's multi-payer reports, with three horizontal bars labeled "Yes," "No," and "Don't have access." The chart indicates 45% answered "No," 35% "Yes," and 15% "Don't have access," highlighting a majority have not accessed the reports.

Figure 2. Poll: Have You Used MVC’s Multi-payer Reports to Support QI?

Horizontal bar chart showing responses to using MVC's multi-payer reports for supporting QI, with three categories: "No" at about 38%, "Don't have access" at about 32%, and "Yes" at about 23%. Chart uses orange bars with percentage labels on the x-axis ranging from 0% to 45%, highlighting majority respondents either do not use or lack access to the reports.

The polling discussion revealed that while many attendees had registry access, 44% had not utilized these multi-payer reports for quality improvement work. Those that did utilize the reports (23%) shared that they use them for efforts such as system-level benchmarking across their hospitals.

Following the polling results, Bair shared unblinded data from Bronson Health System’s MVC multi-payer registry reports and MVC common conditions push report, covering how differing case counts can impact preoperative testing rate performance, especially when looking at conditions separately. Case volume is a common concern for smaller hospitals, such as critical access sites, when trying to extrapolate useful claims data. As larger health systems are acquiring smaller hospitals like critical access sites, though, they may need to shift how the data can and should be interpreted. Using yearly trending can increase the denominator for case data and give a more accurate visual representation of utilization or performance over time, whereas looking at data on a monthly or quarterly timeframe can show volatility due to case counts having high variability over short time ranges.

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us by email if you are interested in being a workgroup presenter or submit an online presentation proposal.

Off
View Post
Reducing Unnecessary Preoperative Testing: Progress on RITE-Size Partnership

Reducing Unnecessary Preoperative Testing: Progress on RITE-Size Partnership

For many patients preparing for surgery, the process begins long before they enter the operating room. Blood tests, lab visits, and diagnostic screenings often become routine steps in preoperative care—even for patients undergoing low-risk procedures. In many cases, these tests add extra appointments and costs without changing how care is delivered.

Research suggests that as many as one in three patients evaluated for low-risk surgery receive tests that are not clinically necessary, and those results rarely influence clinical decisions. Improving the appropriateness of testing is therefore an important opportunity to improve the patient experience while reducing inefficiencies in surgical care.

For the last few years, the Michigan Value Collaborative has engaged its suite of offerings – from dedicated registry pages and push reports to workgroups and performance-based incentives – to support hospitals across the state in aligning their preoperative protocols with evidence-based guidelines.

Progress on the RITE-Size Trial

Another key component in the success of improved preoperative testing appropriateness in Michigan is the Right-Sizing Testing Before Elective Surgery (RITE-Size) trial, supported by the Michigan Program on Value Enhancement (MPrOVE), the Michigan Surgical Quality Collaborative (MSQC), the Anesthesiology Performance Improvement and Reporting Exchange (ASPIRE), and MVC.

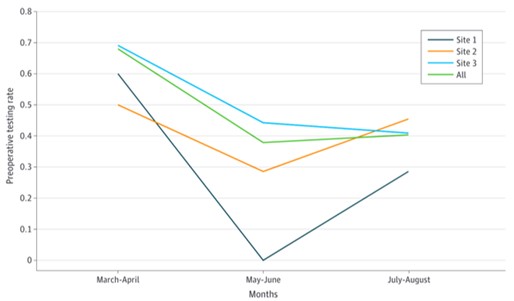
RITE-Size is an Agency for Healthcare Research and Quality (AHRQ)-funded, multi-institutional quality improvement trial. RITE-Size launched a pilot in March 2024 at three hospitals in Michigan. The study aimed to meet criteria in several areas such as feasibility (implementation in the appropriate amount of time), testing rates (reduction), and acceptability and appropriateness (results from interviews). By August 2024, the desired milestones had been achieved, showing a 68% average reduction in unnecessary testing by the three participating sites (Figure 1). All three sites saw significant decreases in their testing rates following implementation of the multi-component intervention.

Figure 1. MVC RITE-Size Pilot Program Testing Rates Over Time Across All Three Sites from March-April 2024 to July-August 2024

line graph depicting reduction in unnecessary preoperative testing at three pilot sites

This was followed by a larger trial in 2025 with six new hospitals. Each site participated in a site visit, personalized coaching, and evaluation of their data in consultation with the RITE-Size team to guide on-site efforts to improve the appropriateness of their preoperative testing. In 2026, the RITE-Size partners are looking to enroll 12-15 hospitals and ambulatory surgery centers (ASCs) across Michigan.

Along the way, some of the successes, tools, and challenges from sites participating in the trial have been featured in MVC’s preoperative testing workgroups, where clinical and quality leaders have come together to learn from one another and share best practices. In one of those recent workgroups, for example, Lake Huron Medical Center shared insights into their experience in the trial and its impact on their preoperative protocols. A collated list of MVC’s preoperative testing workgroups can be found on MVC’s YouTube channel.

The work is also contributing to the broader evidence base on reducing low-value care. Nicole Mott, MD, MSCR, a National Clinician Scholar at the University of Michigan supported by the Veterans Administration and a general surgery resident at the University of Colorado, was the lead author on a recently published paper in JAMA Network Open that described the components and impact of the trial.

Leveraging Partner Operations for Recruitment

Over the past year, the RITE-Size partnership has worked to strengthen alignment between the trial’s activities with those operational activities of the partner organizations.

For instance, participation in the RITE-Size initiative is now tied to MSQC’s BCBSM P4P scorecard for preoperative testing, allowing hospitals to receive credit toward their scorecard by engaging in the initiative. MVC is also leveraging its new ambulatory surgery center (ASC) dataset to identify additional sites beyond the hospital setting that may benefit from participating in the initiative, with recruitment efforts under way with six eligible ASCs. Three new hospitals joined the trial at the start of 2026, and additional sites are engaged in conversations and related information sessions as they consider participating.

Supporting Hospitals in Practice Change

Participating hospitals are approaching preoperative testing improvement from a variety of starting points. For some, the initiative has helped validate practices that were already evolving. For others, it has created an opportunity to revisit long-standing protocols and bring them in line with current evidence.

At Lake Huron Medical Center, participation in the RITE-Size initiative helped uncover an important opportunity for improvement. While staff had already begun reducing unnecessary preoperative testing in practice, the hospital discovered that its formal documentation had not kept pace with these changes. The pre-anesthesia testing protocol used by staff still included outdated materials and handwritten updates accumulated over time.

Through the collaborative work of the RITE-Size initiative, the hospital was able to review and modernize its protocol, ensuring that documentation reflects current practice and provides clear guidance for clinical teams. This type of operational refinement—aligning written protocols, data reporting, and frontline practice—is a common step for organizations working to improve the appropriateness of preoperative testing.

Kelly Lewton, RN, BSN quote

The collaborative structure of the initiative has also proven valuable. Participating hospitals are able to share implementation strategies, learn from peers facing similar challenges, and access guidance from project partners as they refine their approaches.

Looking Ahead

As this work continues, MVC is also using its claims-based data to examine the broader impact of reducing unnecessary testing. The MVC Coordinating Center is currently partnering with MSQC to explore the impact and value of MSQC’s preoperative testing metric since its inclusion in their scorecard. The aims of this analysis are to better understand the statewide improvement in the measure as well as the potential financial and operational benefits associated with improvements.

Insights from this analysis will help the RITE-Size partners better understand the impact of an incentive-based measure on testing outcomes as well as related cost savings that may accompany on-the-ground improvements.

As the RITE-Size trial continues into its next phase, the trial partners remain committed to supporting hospitals through shared data, collaborative learning, and practical implementation resources. Together, these efforts aim to ensure that preoperative testing is used when it adds clinical value.

Hospitals interested in learning more about their preoperative testing rates and opportunities can contact the MVC team.

Off
View Post
MVC Virtual Networking Event: Relational Coordination in Healthcare Quality Improvement

MVC Virtual Networking Event: Relational Coordination in Healthcare Quality Improvement

In February, MVC hosted its first virtual networking event of 2026 with a special presentation on relational coordination by MVC Project Manager Emily Woltmann, PhD, MSW, and Richard Wylde, MSc, Deputy Director of Improvement at Leeds and York Partnership, National Health Service (NHS) Foundation Trust. With more than 45 attendees, the event introduced members to relational coordination, a framework that can be used to evaluate and strengthen collaboration and teamwork in healthcare settings. Following presentations, participants joined breakout groups to discuss the content and complete a case study activity, followed by a debrief and wrap up discussion. 

Overview of Relational Coordination  

Woltmann kicked off the event with an introduction to relational coordination, which was first introduced by Jody Hoffer Gittell as a mutually reinforcing process of communicating and relating for the purpose of task integration. She introduced participants to the relational coordination framework developed by Braneis University’s Relational Coordination Collaborative (RCC), which showcases how relationships and communication continuously reinforce each other in positive and negative ways. In relational coordination, the main components being considered are whether communication that occurs is happening in a frequent, timely, and accurate manner and is being used with the intention of problem-solving; while relational components reference shared goals and knowledge rooted in mutual respect. 

Relational coordination is a dynamic theory, where many areas influence each other. In addition to communication and relational components, the full framework (Figure 1) describes the types of structural, relational, and work process interventions that may impact communication and relationships to impact downstream outcomes. 

Figure 1. RCC’s Dynamic Theory of Coordination

flow chart

Structural interventions are implemented by leadership roles and include things like shared meetings, huddles, information systems, and boundary spanner roles that cross over multiple departments. Relational interventions focus on directly improving ways people relate to each other, such as cultivating safe spaces for discussion. Finally, work process interventions focus on workflows and sometimes use plan, do, study, act (PDSA) cycles for improvement.

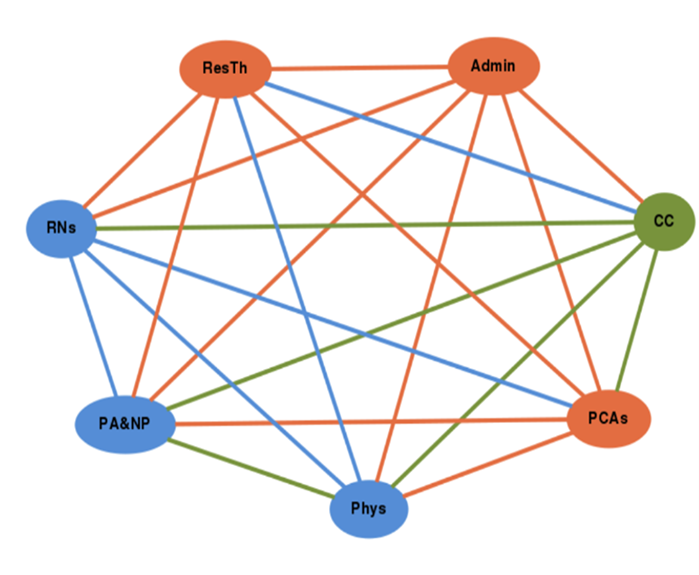
Woltmann highlighted some of the methods available for measuring relational coordination, including a validated quantitative survey to measure role-based coordination between team members. The survey can help evaluate how well relational coordination is working between different roles. Another measurement tool that can be used is relational coordination mapping (Figure 2), which is a visual way to view responses from the relational coordination survey and summarize the strength of relationships between groups. It is designed to encourage deeper engagement and reflection among participants.

Figure 2. Measuring Relational Coordination: Relational Coordination Mapping

Relational Coordination Mapping using a line matrix

Woltmann explained that when relational coordination is working well and is strong, it supports organizations in achieving a wide range of desired performance outcomes such as quality, safety, efficiency, staff well-being, learning, and innovation.

The Maryland and Michigan DECIPHeR Project - Relational Coordination in Community Mental Health Settings

Woltmann also discussed lessons and insights she gleaned about relational coordination from the Maryland and Michigan DECIPHeR Project, which focuses on implementing interventions that decrease cardiovascular disease (CVD) risk factors in people with serious mental illness. Led by Dr. Amy Kilbourne, PhD, MPH, in the Department of Learning Health Sciences at the University of Michigan, and Dr. Gail Daumit, MD, MHS, at Johns Hopkins University, the project focuses on identifying effective interventions shown to address CVD risk factors in persons with a serious mental illness. This broader implementation trial is researching ways to implement a new intervention called IDEAL GOALS in behavioral health homes (BHHs).

While analyzing the qualitative data for this needs assessment phase of the project, Woltmann and colleagues became interested in using relational coordination to understand relational aspects of care coordination in the BHH context. The sample for this study included 14 sites across Michigan and Maryland, with 14 nurses and 32 frontline staff. Sites were given a qualitative designation of “consistently positive” relational coordination, “consistently negative” relational coordination, or “mixed” relational coordination.

Of the 14 sites, Woltmann said five had a consistently positive relational coordination level, six had a consistently negative level, and three had a mixed result. The research team found that sites with consistently positive relational coordination had a variety of structural factors in place to support RC. Boundary spanner roles were seen as particularly important in achieving good relational coordination, as they take on the role that crosses the gap in care for patients – in this instance community mental health staff to primary care providers. Results from the study indicated there were many kinds of strategies that sites used to develop functional RC, and that the most imperative component to building positive relationships was having a strong sense of trust.

Relational Coordination in Mental Health Services – The National Health System

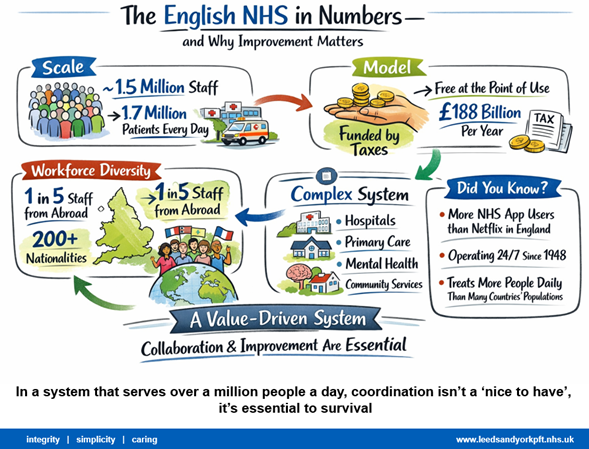
Following Woltmann’s presentation, Richard Wylde, Deputy Director of LYPFT, provided participants with an in-depth look at how relational coordination is being utilized in his work at the National Health System (NHS) of England and emphasized how important coordination is in a large healthcare system. The NHS employs 1.5 million staff to care for roughly 1.7 million patients daily. With a tax funded healthcare model, each patient’s care is financially covered (£188 Billion per year) (Figure 3).

Figure 3. The English NHS in Numbers and Why Improvement Matters

Illustration of why improvement matters in healthcare

The NHS has a complex system of hospitals, primary care clinics, mental health clinics, and community services. Wylde is a part of the Leeds and York Partnership NHS Foundation Trust (LYPFT) which provides specialist mental health and learning disability services to the people in Leeds West Yorkshire, England. They have 48 locations, including 408 beds, see over 25,000 new patients, and have contact with over 270,000 people in the community per year.

Wylde shared that the NHS relationship coordination journey began with senior leadership who had previous experience with relational coordination, introducing the concept and promoting it to other leaders and the board. He recounted that there was slow organizational uptake of relational coordination theory within the system initially. However, as other leadership saw the benefits, they were able to implement strategies at other organizational levels.

Within the community mental health services system, the LYPFT program wanted to look at how young people transition to adult mental health services. They found that it was important to provide a safe space for players in the system to come together to better coordinate this process, and to be mindful of the many different perspectives and power imbalances present. One of the barriers they experienced, Wylde said, was the difficulty in balancing the need for human relationships and trust building timelines versus the systems' need for quick answers.

Wyle highlighted several key lessons learned through implementing relational coordination at multiple levels of a system, including:

  1. Governance at the board level can have limitations on time for developing a relational space
  2. Relational coordination worked best when senior leaders had a collectively shared understanding of what relational coordination was and how they could use it
  3. Relational coordination was more successful when it had clear framing and context to the program/service/team
  4. It was important for all levels to understand how the relational coordination dynamic functions at the smallest level of a system (between people)
  5. Relational coordination is both a relationship and a process
  6. Strong relationships enable strong processes and vice versa

Breakout Session Debrief

During the breakout session portion of the networking event, participants were guided through a patient case study that demonstrated how breakdowns in staff communication and relationships could negatively impact patient outcomes. The breakout groups had engaging conversations that focused on building trust, relational coordination interventions, explaining the “why” to help teams develop shared goals, understanding the impact of staff-to-patient ratios on communication, and other tools and frameworks that have helped teams improve their communication.

MVC was glad to highlight this topic and the expertise of these presenters to support shared learning and continuous improvement within healthcare teams. MVC welcomes presenters to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members, which cultivates a community of peers looking to collaborate in a non-competitive space. Please reach out to MVC by email if you are interested in being a presenter or submit a presentation proposal online.