Off
View Post
CQI Spotlight: Michigan Radiation Oncology Quality Consortium

CQI Spotlight: Michigan Radiation Oncology Quality Consortium

Cancer treatment is complex, and for many patients, radiation therapy is a critical part of their care journey. Yet the delivery of radiation therapy—how much is given, how often, and with what level of precision—can vary widely across providers, with meaningful implications for outcomes, side effects, and overall patient experience.

The Michigan Radiation Oncology Quality Consortium (MROQC) was founded in 2011 in partnership with Blue Cross Blue Shield of Michigan (BCBSM) to better understand and reduce variation in radiation therapy practices across Michigan - specifically related to the use of advanced technologies such as 3D conformal radiation therapy (3D-CRT) and intensity-modulated radiation therapy (IMRT) in breast and lung cancer treatment. The BCBSM-funded CQIs play a crucial role in driving healthcare quality improvement in Michigan. MVC is excited to continue highlighting the innovative contributions of individual CQIs like MROQC and the ways in which MVC’s data support high-value care initiatives across the portfolio.

At the time of MROQC’s founding, there was growing interest in understanding how these technologies were being used across institutions and ensuring that newer, more complex approaches were being applied appropriately and consistently. By bringing radiation oncology providers together in a statewide collaborative, MROQC created a platform to compare treatment patterns, share best practices, and evaluate how different approaches affected patient outcomes. Over time, the work of MROQC expanded beyond treatment utilization to focus on broader quality improvement and value-based care initiatives. Today, the consortium supports multiple disease-site quality initiatives, collects patient-reported outcomes, and collaborates with clinicians and health system partners to improve the safety, effectiveness, and patient-centeredness of radiation therapy across Michigan.

Services and Benefits to MROQC Members

One of the most unique aspects of MROQC is its strong culture of collaboration across institutions that would traditionally be competitors. Radiation oncologists, medical physicists, nurses, dosimetrists, radiation therapists, abstractors, and administrators from across Michigan work together to analyze data, identify opportunities for improvement, and implement changes that benefit patients statewide. It is through this collaborative infrastructure that MROQC supports radiation oncology providers, hospitals, and care teams across Michigan.

Members benefit from:

  • Participation in statewide quality improvement initiatives across multiple disease sites
  • Access to real-time performance dashboards and benchmarking data
  • Collaborative working groups where clinicians share best practices and develop new quality measures
  • Educational opportunities and training resources
  • Support for research, publications, and national presentations
  • Participation in innovative incentive programs such as the BCBSM Gold Card program, which reduces prior authorization burden for high-performing facilities.

Through this collaborative model, the MROQC Coordinating Center team (Figure 1) enables clinicians and institutions to learn from each other, implement best practices more quickly, and continuously improve patient care. This has allowed Michigan to become a national leader in radiation oncology quality improvement, demonstrating how data-driven partnerships between member providers and payers can improve outcomes, reduce costs, and enhance patient experience.

Figure 1. MROQC Coordinating Center Team

Photo of 23 MROQC team members standing outside in front of a building

MROQC’s Key Initiatives and Achievements

Several initiatives highlight how MROQC’s collaborative model has been translated into meaningful improvements for patients and providers across Michigan.

Expanding use of shorter, evidence-based radiation treatments

MROQC has helped increase the adoption of hypofractionated radiation therapy, which delivers effective treatment in fewer sessions. For example, the use of accelerated whole breast radiation therapy has increased by more than 60% statewide, reducing treatment burden for patients while maintaining excellent outcomes.

Similarly, initiatives promoting shorter treatment courses for bone metastases have helped 78% of MROQC patients receive effective pain relief with fewer visits to the clinic, improving quality of life while reducing healthcare costs.

Improving treatment safety by reducing radiation exposure to critical organs

Through collaborative treatment planning initiatives, MROQC members have worked to reduce radiation exposure to organs such as the heart and esophagus during cancer treatment. These efforts have helped lower the risk of treatment-related complications and improve the safety of radiation therapy across the state.

Reducing administrative burden through the Gold Card program

In partnership with BCBSM, MROQC helped develop and implement the Gold Card program in 2017, which allows high-performing radiation oncology facilities to receive automatic prior authorization approval for radiation therapy treatments. This program rewards facilities that consistently meet quality improvement criteria and has significantly reduced administrative burden while allowing clinicians to begin treatment more quickly for patients.

Together, these successes demonstrate how statewide collaboration and real-world data can drive improvements in patient outcomes, treatment efficiency, and value-based care (Figure 2).

Figure 2. MROQC Performance: The Right Treatment at the Right Time

Infographic presents key statistics on radiation treatment effectiveness and advancements for breast, lung, bone metastases, and prostate patients from 2015 to 2024. Uses blue icons and bold percentages to highlight milestones such as 16K breast patients receiving targeted radiation, 89% lung patients avoiding esophagus radiation, 78% bone metastases patients benefiting from treatment reducing time and improving quality of life, and over 1K prostate patients receiving high precision radiation.

MROQC’s current initiatives focus on advancing high-value radiation therapy while strengthening the data infrastructure needed to support statewide quality improvement. Across its disease-site working groups - breast, lung, prostate, and metastatic cancer - MROQC continues to promote initiatives that improve treatment quality, reduce variation in care, and support evidence-based practice. Current efforts include improving treatment planning standards, expanding the use of shorter radiation therapy courses when appropriate, and monitoring treatment safety measures that reduce toxicity and improve patient outcomes.

MROQC is also expanding its quality improvement work to include brain metastases, building on the success of the existing metastases working group. This effort will help better understand treatment patterns and outcomes for patients receiving radiation therapy for brain metastases and identify opportunities to standardize and improve care.

For prostate cancer, MROQC partners with the Michigan Urological Surgery Improvement Collaborative (MUSIC) to better understand care across the full patient journey - from diagnosis through treatment. This collaboration allows the teams to link data across specialties and identify opportunities to improve coordination and outcomes for prostate cancer patients across Michigan.

Together, these initiatives ensure that MROQC continues to support clinicians across Michigan with the data, collaboration, and infrastructure needed to improve radiation therapy care for patients statewide.

Graphic quote from Lori Pierce, MD, highlighting MROQC as a unique radiation oncology-based collaborative quality initiative. The text emphasizes MROQC's role in setting standards for radiation-associated healthcare outcomes and efficient use of healthcare dollars in treating breast, lung, prostate cancers, and metastatic disease.

Addressing Non-Medical Drivers of Health Outcome Variation

Another important focus area is improving access to care for all Michigan cancer patients. MROQC is addressing variation in care through both data collection and targeted quality improvement efforts. The consortium collects data on demographic and social factors that may influence access to care or treatment outcomes. These data allow the collaborative to identify patterns of variation across facilities and patient populations and develop targeted interventions to address those outcome gaps. In addition, MROQC established the M-EQUAL committee, which focuses specifically on improving access to high-quality cancer care. The committee works to expand non-medical drivers of care data collection, is aiming to develop barriers-to-care quality measures and provides education and resources to member institutions to improve access and outcomes for all patients. Ultimately, MROQC’s efforts to leverage statewide data with collaborative learning translate into tangible benefits for patients: shorter and more convenient treatment courses, fewer complications, and more consistent care regardless of where they are treated.

Looking Ahead: Strengthening Data Infrastructure and Member Engagement

MVC and MROQC are currently partnering to explore a new data opportunity using claims-based analysis. This effort is looking to evaluate whether reduced fraction palliative radiotherapy for painful bone metastases among MROQC-participating sites results in lower overall healthcare utilization compared to episodes of care attributed to non-MROQC sites.

MROQC knows from experience that quality improvement requires more than collecting data - it requires building trust among clinicians, ensuring data accuracy, and creating opportunities for teams to learn from one another. Over the years, MROQC has seen how powerful a collaborative model can be when clinicians across institutions come together around shared goals. That is why the MROQC Coordinating Center continues to strengthen member engagement and is investing heavily in data infrastructure and reporting tools to support the collaborative with trustworthy, accurate data. These efforts include improving dashboards and reporting capabilities for participating facilities and preparing for a transition to a more scalable data platform to support future growth, analytics, and research. Visit the MROQC website to learn more about its team, offerings, and successes.

Off
View Post
CQI Spotlight: Obstetrics Initiative

CQI Spotlight: Obstetrics Initiative

In 2018, Michigan was facing a concerning reality: nearly one in three births in the state occurred by cesarean delivery, a rate that exceeded the national average and signaled opportunities to improve the safety, experience, and value of childbirth care. Behind every data point were real families navigating some of the most important moments of their lives and clinicians striving to deliver the best possible care within a complex maternity landscape. The need for change was personal, urgent, and increasingly difficult to ignore.

As such, patients, clinicians, and employers began voicing concerns about rising cesarean rates affecting patients’ recoveries, long-term health, and trust in the healthcare system. Recognizing the scope of the problem and the opportunity to address it, Blue Cross Blue Shield of Michigan (BCBSM) turned to clinician leaders at University of Michigan to help design a statewide response, which leveraged Michigan Value Collaborative (MVC) claims data on childbirth episodes. In 2018, this collaboration laid the groundwork for what would become a dedicated effort to transform maternity care in Michigan.

Formally launched in 2019, the Obstetrics Initiative (OBI) emerged as one of BCBSM’s 21 Collaborative Quality Initiatives (CQIs). At that time more than 70 hospitals joined together under OBI’s vision to support safer deliveries, reduce unnecessary cesarean deliveries, use resources more wisely, and improve the overall culture of care. Today, OBI continues to build on that foundation by ensuring that every birth in Michigan is supported by the best evidence, the best practices, and a shared commitment to healthier beginnings.

Services and Benefits for OBI Members

To support its members in successfully implementing quality improvement (QI) initiatives, OBI supports its members using four primary offerings (Figure 1). One of those offerings is OBI’s robust, real-time benchmarking data that enables actionable insights. OBI’s registry is a best-in-class source of clinically credible data and compelling data stories that inspire change. A second core offering is direct support and expertise on specific QI interventions, including the development of best practice protocols and resources that advance evidence-based care. A third core offering is the transformational learning that occurs at OBI’s collaborative-wide meetings and other activities that are key to networking, partnership building, and collective learning across maternity units in Michigan. Finally, a fourth core offering is the intentional collection and incorporation of patient stories and experiences in all ongoing activities.

Figure 1: OBI Member Service Offerings

OBI service offerings: data and analytics, learning, QI evaluation, collaboration with patients

OBI Program Director Michelle Moniz, MD, MSc, recognizes how OBI’s tailored approach to QI support helps sites achieve a shared purpose of high-quality perinatal care that improves the lives of current and future generations. In her words:

“Every large-scale QI initiative faces a vexing unsolved problem: how best to support hospitals and clinicians who aren’t responding. Our routine QI support approaches—group meetings, webinars, online toolkits, performance incentives—can fall short for sub-optimally responding sites/clinicians, and leave patients vulnerable to low-quality, low-value healthcare. OBI imagines a future where CQIs deliver the right support, to the right hospital/clinician, at the right time, to achieve highest-quality care across all CQI members. This vision—which we call Precision QI—leverages scarce resources most efficiently to achieve evidence-based healthcare at scale for all patients.” 

OBI’s "precision QI” offers personalized QI support for each hospital. Just as precision medicine accounts for individual patient differences in developing a treatment plan, OBI’s precision QI support model (Figure 2) is adaptive, diagnosing and responding to the unique needs of each OBI member and may include:

  • Performance Measurement: Offering observed, risk-adjusted, and peer-comparative data
  • Performance Feedback: Incorporating individualized goal setting and data for hospitals and individual providers
  • Outreach: Offering augmented support when performance deteriorates or is stably poor
  • Engagement: Offering a suite of resources for key target audiences, including hospital leadership, QI leader, bedside clinicians, and patients

Figure 2. Mechanisms for OBI’s Precision QI Support Model

performance measurement, performance feedback, outreach, engagement

OBI’s Key Initiatives and Achievements

OBI is now a unique asset for quality improvement in Michigan and beyond. Having built a vibrant community of multidisciplinary teams at currently 65+ hospitals across Michigan, OBI generates the evidence base needed for more effective, transformational quality improvement in obstetrics.

Putting that framework into action, OBI achieved noteworthy successes over the years. Since OBI’s inception, their flagship initiative, Safely Averting Cesarean Births, has focused on safely lowering the primary cesarean rate in Michigan. In 2023, OBI launched Patient Voices, a statewide survey to assess childbirth experiences and patient-reported outcomes related to birth. OBI then launched another statewide initiative, Bringing Our Patients COMFORT, in 2024, to promote best practices for managing pain after childbirth.

To reduce first-birth term cesareans – also known as nulliparous term singleton vertex (NTSV) cesareans, OBI’s Safely Averting NTSV Cesarian Births initiative successfully reduced the statewide cesarean rate from a historic high of 28.9% in 2023 to 26.9% as of September 2025. This improvement reflects years of effort to increase compliance with national diagnostic criteria for labor arrest disorders (which increased from 37.9% in 2020 to 77.1% in 2025). Increased compliance was aided using an algorithm to guide fetal management in labor, resulting in significant improvement from 47.3% compliance in 2022 to 93.2% in 2025.

Pain management is another area where OBI has made meaningful progress. Successful promotion of the use of scheduled nonopioid prescribing after cesarean births through OBI’s Bringing Our Patients COMFORT quality initiative boosted a compliance rate of 86.1% in 2024 to 96.8% compliance in 2025. Analyses are ongoing to evaluate corresponding reductions in opioid prescribing rates and amounts.

OBI’s third quality initiative Better Births for All aims to ensure that every OBI member has the tools and support to consistently implement evidence-based obstetric practices while fostering psychological safety and respectful, person-centered care for all during labor and birth. The path to accomplish that is threefold. First, OBI partners with a Patient and Community Action Board (PCAB) to center patient and community experiences in its QI initiatives. The OBI PCAB reviews patient-facing materials and has decision-making power over OBI’s selection of QI initiatives and operationalization of initiative measures in OBI’s incentive packages. OBI further centers patients’ perspectives in its work by measuring and improving collection of patient-reported outcomes and experience data to ensure that patients’ voices are embedded in daily QI work. OBI also educates and trains clinicians on patient-centered approaches and practices they can bring to their own daily work.

"Relationships are at the heart of what we do. We have a shared belief that our goals will be better met when we advance toward them together." Helen Costis, MSHA, Program Manager, OBI

What’s Next for OBI?

In 2026, OBI will launch a new Induction of Labor initiative to promote evidence-based management of induction of labor (IOL), the procedure to start labor before it begins on its own. This procedure occurs in more than 30% of all births, and yet the use of evidence-based techniques occurs in less than 10% of all inductions with wide variation across sites in Michigan (Figures 3 and 4).

Figure 3. Pathways for Evidence-Based Induction of Labor

Induction of labor pathways: Dual-Agent Ripening; Early Amniotomy
Rate of use graph of evidence-based induction of labor techniques. Patients who get both recommended techniques is 7.1%.

OBI is incredibly proud to be a part of the 25+ year history of the Value Partnership portfolio in Michigan, including its long-standing partnership with MVC. OBI and MVC are currently collaborating on several analyses to drive quality improvement, such as evaluating statewide variation in complications and expenditures for different patient groups and modes of delivery, improving the timeliness and quality of prenatal care, evaluating the association between social vulnerability and surgical management of early pregnancy loss. MVC is also working with OBI to estimate the impact and associated cost savings of OBI’s efforts to safely reduce cesarean birth rates in Michigan as well as the impact of OBI’s opioid management work on prescribing rates and costs in Michigan.

The BCBSM-funded CQIs play a crucial role in driving healthcare quality improvement in Michigan. MVC is excited to continue highlighting the innovative contributions of individual CQIs and the ways in which MVC’s data are supporting high-value care initiatives across the portfolio. Please reach out to MVC by email if you are interested in learning more.

Off
View Post
Celebrating 2025 Successes and Setting the Stage for 2026

Celebrating 2025 Successes and Setting the Stage for 2026

On behalf of the MVC Coordinating Center, let me first start this end-of-year blog by thanking you all for your partnership and continued support throughout 2025. In case you blinked and its now December – don’t worry, you’re not alone! The last year has flown by with plenty of twists and turns along the way. Before we get caught up in the holidays and planning for 2026, we wanted to step back and celebrate the successes we achieved together over the last 12 months.

In writing my reflection piece last year, I highlighted that both our engagement participation and analytics utilization were far above previous years. While this gave us a hard act to follow, we are delighted to share that this trend continued upwards in 2025. Over the last year, we welcomed two new hospital members to the collaborative, delivered 23 virtual workgroups with an average attendance of 41, facilitated 24 different member presentations, completed 9 site visits, delivered 14 custom analytic requests, and supported 106 new users in gaining access to our online registry. On top of all of this, we held two collaborative wide meetings in Midland and Livonia, with 197 member representatives joining us to share stories, spotlight successes, and support one another in navigating all of the challenges which 2025 decided to bring.

These flagship numbers only tell one part of the story; the true value of each of the activities detailed above comes from the relationships and partnerships developed as a result of the time spent together. We hope you all have taken as much benefit from these collaborations as our group has during this time. Which brings me to another highlight…the MVC Coordinating Center. Let’s take a moment to celebrate the people who not only help make all of the above possible but that make this such a great place to work. Thank you to the entire MVC team for your hard work and commitment to supporting our members throughout 2025. I’m excited for what the next year will hold. Speaking of which, here’s a sneak peek of a few things that will be taking place in 2026.

Collaborative Wide Meetings, Networking Events, and Virtual Workgroups

MVC’s 2026 engagement events calendar is now live. Our spring collaborative wide meeting will take place on Friday, May 8 in Traverse City and we will be returning to Livonia for our fall meeting on Friday, October 9. These forums continue to be supported by virtual and in-person networking activities and dinners throughout the year, and dates for our regular suite of virtual workgroups can also be found on the 2026 calendar. Save the dates - we look forward to seeing you at each of these events!

MVC Site Visits

We visited a number of you in 2025, providing the opportunity to strengthen our understanding of member activities, priorities, and system-level practices. This effort will continue next year, and members can participate in these site visits in either a virtual or in-person capacity, with P4P engagement points on offer for taking part. If you are interested in getting on the calendar for 2026, please don’t hesitate to reach out.

MVC Site Engagement Coordinator Education Program

In response to member feedback, MVC will be launching a new Site Coordinator Education Program in 2026, designed to offer a flexible, individualized, rolling training curriculum to provide members with a stronger understanding of MVC data, share tools to help evaluate metric progress, and facilitate peer collaborations. This program is in high demand with capacity already met for the first round of registration. Additional opportunities to participate in this new education program will open throughout the calendar year – more communications to follow!

New MVC Component of the BCBSM P4P Program PY26/27 Registry Pages & Webinars

As with previous cycles, new P4P pages will be launched at the turn of the year to correspond with the changes implemented for PY26/27. These pages will look and feel similar to those currently available with a few important updates to reflect changes to our episode spending and value metric menu options and the introduction of MVC’s new Health Outcome Variation Measure. The latter reflects a new metric to the MVC Component, and to support members in navigating and utilizing these new registry pages, dedicated explainer webinars will be held in January.

MVC Push Reports and Custom Analytics

As highlighted above, MVC’s push reports and offer of custom analytics were well utilized by members in 2025, and to reflect member feedback, efforts will be spent strengthening this offering for member benefit in 2026. Remember, if you are interested in working with the Coordinating Center on a custom build, reach out to us by email. [LINK]

Thank you again for your continued partnership throughout the last year and we look forward to more successes in 2026. Have a great holiday and a happy new year when it rolls around.

Off
View Post
November Workgroups Highlight Mobile Health and Patient Storytelling

November Workgroups Highlight Mobile Health and Patient Storytelling

In November, MVC hosted two virtual workgroup presentations – the first, a rural health workgroup, featured Hillsdale Hospital’s mobile health unit initiative. The second, a post-discharge follow-up workgroup, continued a presentation started at MVC’s February 2025 health in action workgroup on patient journey mapping and introduced a joint patient storytelling project by Healthy Behavior Optimization for Michigan (HBOM) and Michigan Cardiac Rehab Network (MiCR). The MVC Coordinating Center hosts workgroup presentations twice per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehab, rural health, preoperative testing and health in action.

Rural Health Workgroup – Hillsdale Hospital 

The first workgroup of the month provided a review of Hillsdale Hospital’s mobile health unit, which aims to deliver essential health services to patients living in rural communities who may otherwise struggle physically or financially to reach traditional care settings.

As Lindsey Crouch, Director of Outpatient Clinics, Home Care, and Durable Medical Equipment for Hillsdale Hospital explained, rural communities face higher health outcome variation, transportation issues, limited accessibility to primary care providers, and high unnecessary emergency department (ED) utilization (Figure 1).

Figure 1. Hillsdale County Community Health Needs Assessment (CHNA) Survey Data: Difficulty Finding or Getting Transportation to a Doctor in 2024, 2022, 2019, and 2016

vertical bar graph: Hillsdale County Community Health Needs Assessment (CHNA) Survey Data: Difficulty Finding or Getting Transportation to a Doctor in 2024, 2022, 2019, and 2016

During the Covid-19 pandemic, Hillsdale County’s health department purchased a mobile health unit in an effort to close the gap in healthcare access for their community. However, despite continued need, utilization of the mobile unit has waned in recent years.

Hillsdale Hospital aimed to revitalize the mobile health unit to:

  1. Bridge access gaps in rural areas. For many rural residents, distance to hospitals or clinics, limited transportation, and infrastructure challenges can hinder timely access to care. A mobile health unit can bring services to patients rather than requiring patients to travel long distances. This helps to reduce one significant non-medical barrier to care.
  2. Focus on preventive and ongoing care. The mobile unit’s design supports not just acute care, but preventive services — screenings, check-ups, chronic disease management — especially helpful for rural populations that may have higher chronic disease burden and less frequent access to routine care.
  3. Address gaps in health outcomes between communities. By delivering care directly to underserved communities, this model aligns with broader efforts to ensure that where a person lives does not determine whether they receive high-value, quality healthcare.

Throughout this program, Hillsdale Hospital aimed to improve health outcome variation with a goal to achieve a 15% improvement in selected chronic disease metrics (e.g., blood pressure control) while also establishing partnerships with local organizations for sustainability.

Throughout the presentation and follow-up discussion, participants addressed several key considerations related to implementing and operating the mobile health unit including:

  • Logistical planning & scheduling. Which rural towns or areas will be served? How often do visits occur? How to communicate the schedule to residents to maximize utilization?
  • Service offerings. What mix of services beyond basic triage should be included? Considerations may include screenings, chronic disease management, preventive care, and referrals when needed to ensure the mobile unit meaningfully supplements local rural healthcare capacity.
  • Coordination with local providers. What existing local hospitals, clinics, and community health organizations should be involved to ensure continuity of care? Consider these, especially follow-up and referrals, for more advanced services.
  • Addressing rural-specific challenges. What unique barriers impact your community? Consider transportation, limited staffing, and supply chain constraints.

Hillsdale Hospital’s mobile health unit embodies a vision for bringing high-value, high-quality care to rural Michigan. By lowering access barriers and delivering preventive and ongoing services directly to patients in their communities, this initiative can help improve health outcomes, reduce reliance on emergency services, and foster trust in healthcare among rural residents.

Insights from this workgroup have several practical implications for other rural hospitals and provider organizations across Michigan:

  • Expansion is possible through mobile care. Rural hospitals can leverage mobile health units as an extension of their current clinical outreach, helping to connect with populations that may rarely visit brick-and-mortar facilities.
  • Support chronic disease management. By delivery of routine care and screenings, mobile units can help stabilize chronic conditions earlier, reducing acute exacerbations and potentially reducing avoidable ED visits.
  • Enhance care coordination. Partnering with mobile health teams and community resources can help coordinate follow-up appointments, testing, and specialty referrals to create a more continuous care experience for rural patients.
  • Advance population health goals. Mobile services can function as a tool within a hospital’s broader population health strategy, align with value-based initiatives, community health needs assessments, and provide the opportunity for all people to achieve optimal health goals.
  • Gather meaningful community insights. Regular presence in rural communities can help hospitals better understand local barriers, non-medical drivers of health, and other care gaps which may inform program planning, grant proposals, and collaborative partnerships.

MVC Rural Health Workgroup: Nov. 4, 2025

Post-Discharge Follow-Up Workgroup – MVC and HBOM

The second MVC workgroup of November featured a joint presentation by MVC’s Associate Program Manager, Jana Stewart, MPH and HBOM’s Informatics Design Lead, Noa Kim, MSI. The workgroup kicked off with an overview of the rationale behind placing a greater emphasis on post-discharge follow-up – particularly how timely and effective follow-up care can reduce readmissions, improve patient outcomes, and ease transitions from inpatient to outpatient or home settings.

Next, as a continuation of the February 2025  health in action workgroup presentation on patient journey mapping, Stewart showed how mapping can be used to highlight key moments in a coronary heart failure (CHF) patient’s journey where there may be opportunities for post-discharge care coordination improvement – e.g., medication reconciliation, patient knowledge, frequent rehospitalization, low follow-up rates, and lack of social and community support.

An important strategy for combating these challenges for CHF patients is engagement in cardiac rehabilitation. And yet, patients rarely optimize this opportunity. Patient storytelling can help patients recall details, model scenarios a patient may experience in the future, and reduce the burden of information provided during a visit and may be a strategy to optimize cardiac rehab enrollment.

Under the umbrella of Michigan Cardiac Rehab (MiCR), a collaboration between the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2), MVC, and HBOM, several initiatives have been developed aimed at optimizing guideline-directed medical therapy including the development of NewBeat materials and now the Heart-to-Heart storytelling campaign (Figure 2).

Figure 2. Examples of MiCR Guideline-Directed Medical Therapy Campaigns

NewBeat materials and the Heart-to-Heart storytelling campaign

As Kim explained, the goals of the Heart-to-Heart project are to collect diverse first-person accounts of cardiac rehab in video, audio, and photo formats from patients and clinicians from across Michigan to produce a compelling, free, reusable story library for use by cardiac rehab advocates across Michigan and beyond.

For hospitals and health systems across Michigan seeking to improve post-discharge outcomes, insights from this workgroup offer the following next steps:

  1. Use journey mapping and storytelling in quality improvement. By mapping patient journeys and capturing patient experiences, providers can better identify and address systemic barriers to safe discharge and recovery.
  2. Adopt standardized discharge-to-follow-up workflows. Hospitals should ensure that discharge planning includes scheduling follow-up appointments, medication reconciliation, and clear communication of next steps before patients leave the hospital.
  3. Prioritize high-risk patients for post-discharge support. Patients with chronic illness, limited social support, or social determinants that might hinder recovery deserve extra attention during discharge planning and follow-up scheduling.
  4. Assign care coordinators or navigators. Especially for high-risk or complex patients, dedicated staff to oversee follow-up care – manage appointments, support communication, track adherence, and offer resources – may reduce readmissions and improve outcomes.
  5. Leverage post-discharge care as part of value-based care strategy. Effective follow-up after discharge supports long-term patient health, reduces avoidable costs, and aligns with goals of high-value care frameworks.

MVC Post-Discharge Follow-Up Workgroup: Nov. 20, 2025

If you are interested in pursuing a healthcare quality improvement project, MVC has data specialists available to help you navigate our data resources and create custom analytics reports to support your efforts. Please reach out to us by email [LINK] if you would like to learn more about MVC data or engagement offerings!

Off
View Post
MVC 2025 Fall Collaborative-Wide Meeting Summary – Adapting Together in 2025 and Beyond: High-value Care for All in a Changing Landscape

MVC 2025 Fall Collaborative-Wide Meeting Summary – Adapting Together in 2025 and Beyond: High-value Care for All in a Changing Landscape

The Michigan Value Collaborative (MVC) held its fall 2025 collaborative-wide meeting on Friday, Oct. 10, in Livonia. A total of 91 attendees representing 64 hospitals, three physician organizations, and 13 healthcare systems from across the state of Michigan came together to share strategies for mitigating the impact of non-medical drivers on health outcomes.

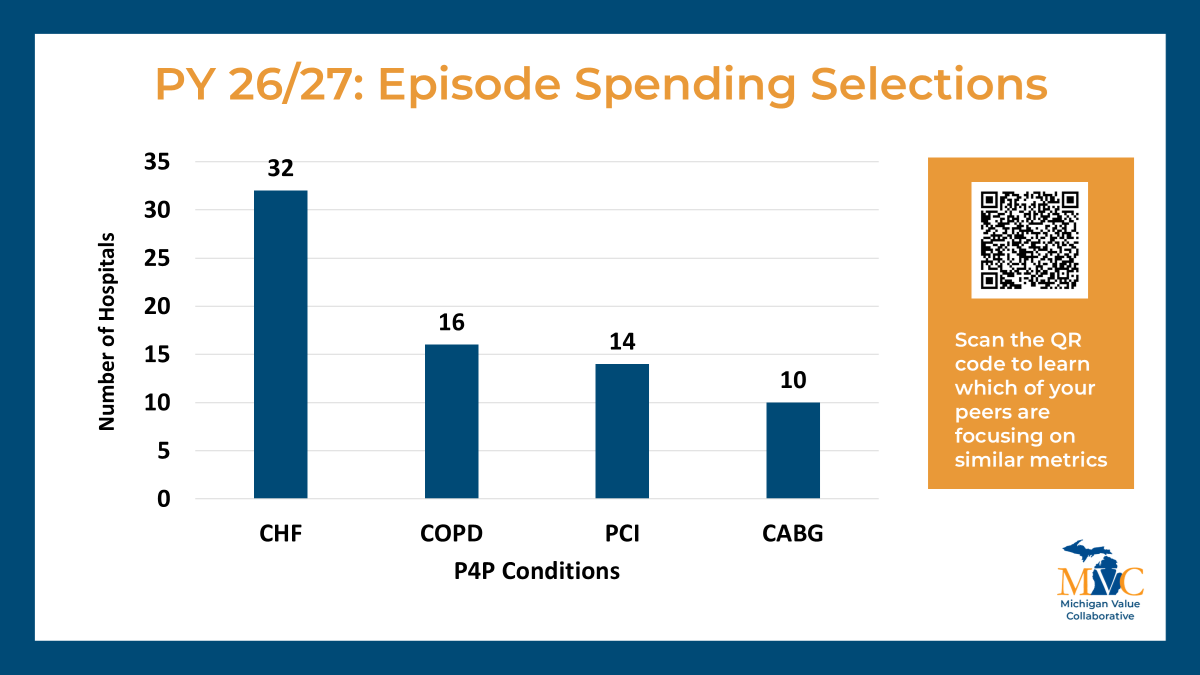
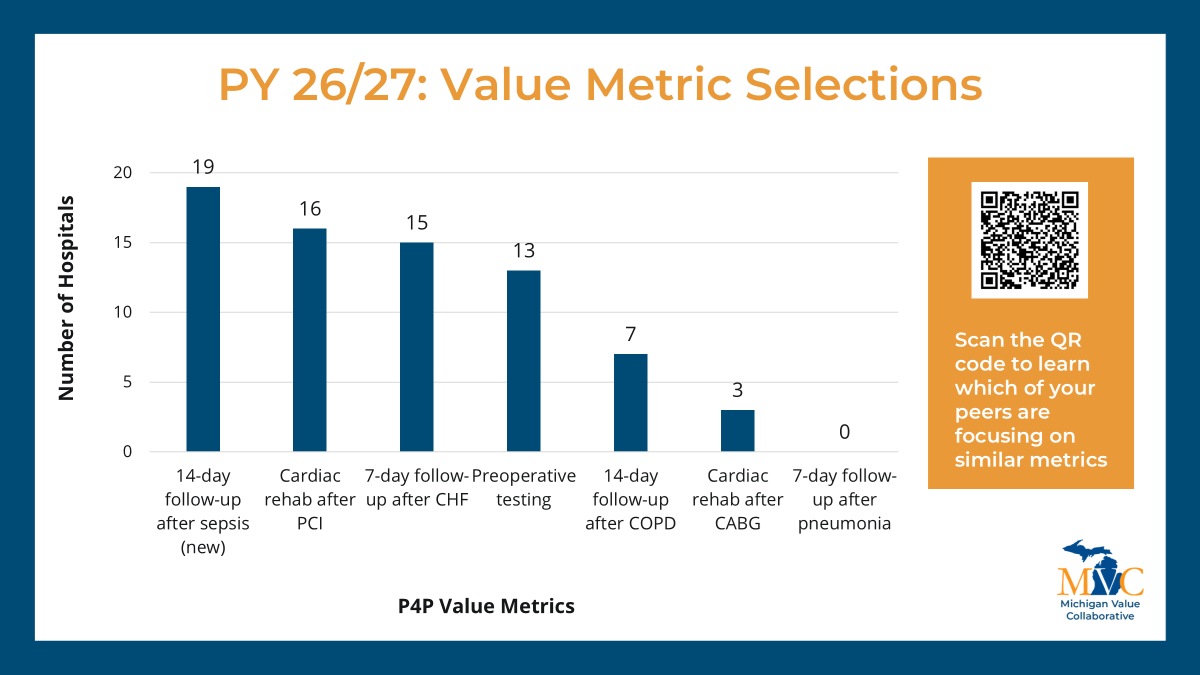
MVC Director Mark Bradshaw, MSc, kicked off Friday’s meeting with updates on the MVC Coordinating Center [See slides]. He introduced MVC’s newest team members, Manager of Data Analytics Ian Raxter, MPH, and Project Manager Emily Woltmann, PhD, MSW, as well as announced the promotion of Julia Mantey, MPH, MUP, to Lead Analyst. Bradshaw encouraged sites to register for the 2025 Michigan Cardiac Rehab network (MiCR) fall meeting at Corewell Health Troy Hospital by the Oct. 31 deadline. He also provided an update on Phase II of the RITE-Size preoperative testing trial and recent MVC reporting since MVC’s spring meeting, including refreshed common conditions push reports, the new health outcome variation push report, and the P4P Program Year 2025 mid-year scorecards. Bradshaw provided insights on the content included in the health outcome variation push report and the P4P Program Year 2025 mid-year scorecards before reviewing Program Year (PY) 2026-2027 cycle changes and member selections (Figure 1 and Figure 2).

Figure 1.

vertical bar graph of PY 26/27 episode spending selections for CHF, COPD, PCI, CABG

Figure 2.

vertical bar chart of PY 26/27 value metric selections for seven metrics

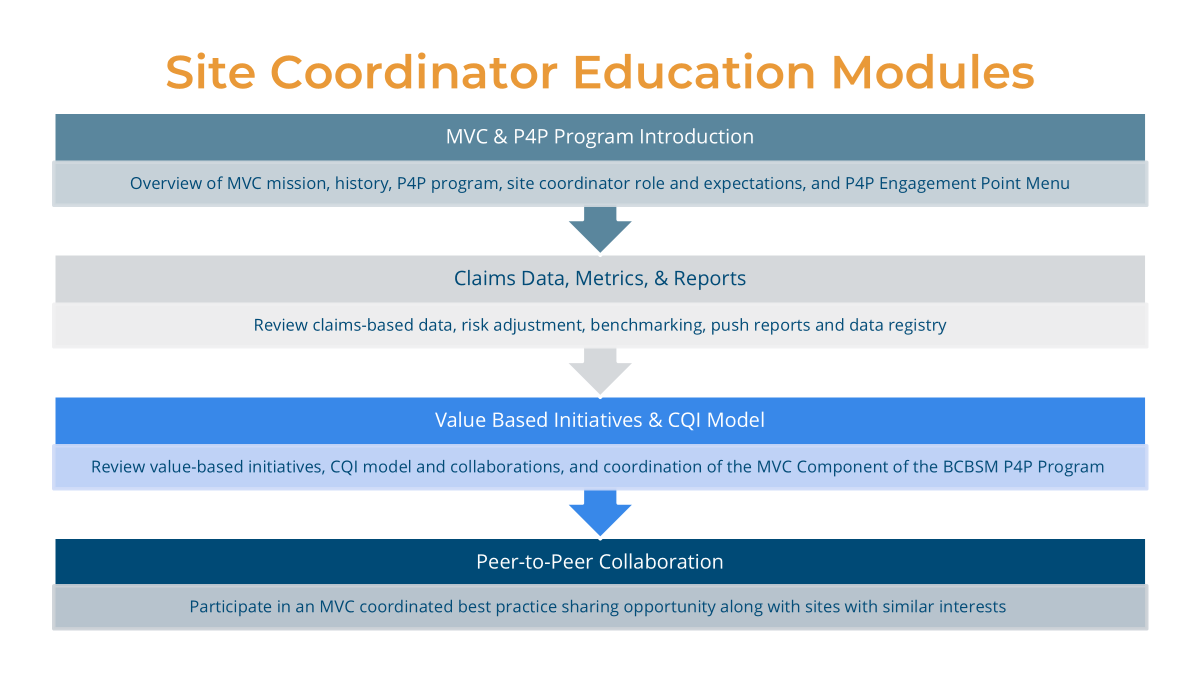
Following Bradshaw’s announcement that MVC’s 2026 engagement point menu is now posted on MVC’s P4P webpage, MVC Engagement Manager Jessica Souva, MSN, RN, C-ONQS, highlighted the differences from previous versions of MVC’s engagement point menu. Souva noted that most of the changes to the engagement point menu were adjustments to the point values; however, Souva introduced the addition of a site coordinator education modules offering (Figure 3). Details on these modules will be shared with MVC site coordinators in the coming months via email.

Figure 3.

Site coordinator education modules

The meeting then featured a presentation from the MSHIELD CQI, including Program Manager Julia Weinert, MPH, and Bradley Iott, PhD, MPH, on implications of non-medical drivers of health for quality improvement. Weinert and Iott presented research evidence on the importance of addressing upstream drivers of health outcomes, MSHIELD implementation toolkits, and resources available on the MSHIELD website.

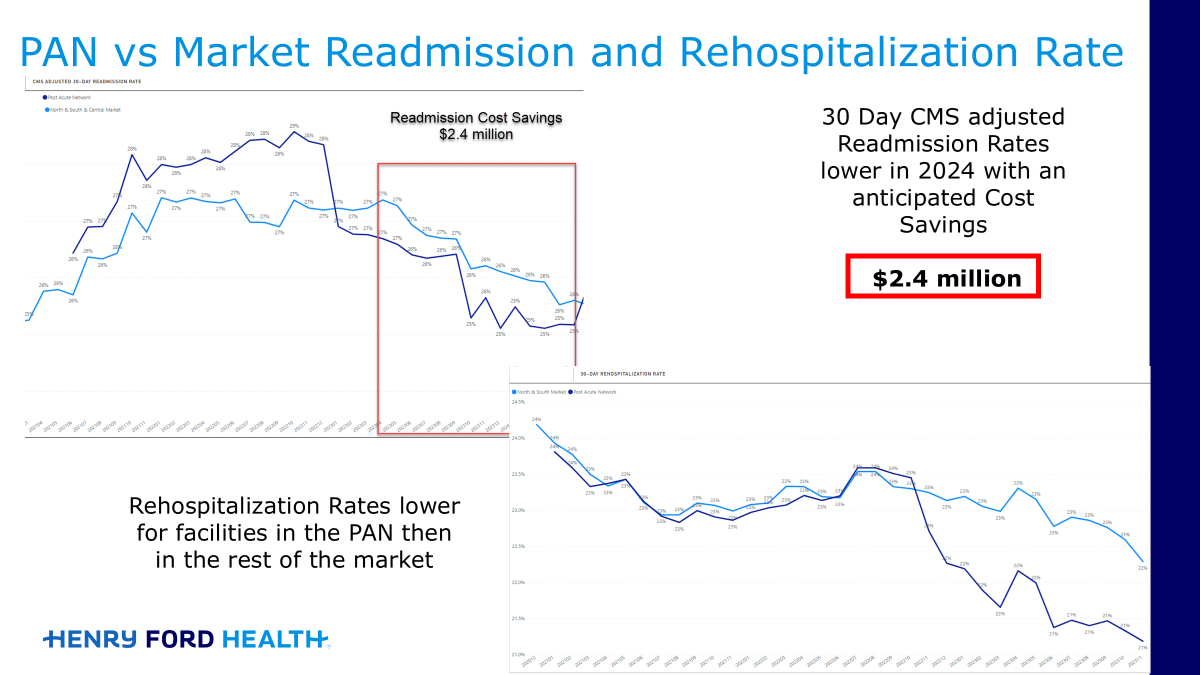
MVC’s keynote presentation was delivered by Gloria Rey, PA-C, MPH, Director of Post-Acute Care for Henry Ford Health/Populance. Her presentation detailed Henry Ford Health’s approach to developing and maintaining strong relationships with post-acute care providers [See slides]. Rey went on to demonstrate how these relationships have improved patient outcomes and cost savings (Figure 4).

Figure 4.

depiction of Henry Ford Health's rehospitalization rates lower for facilities in the post-acute network (PAN) than in the rest of the market

After a networking lunch, MVC Medical Director Hari Nathan, MD, PhD, and MVC Analyst Kushbu Narender Singh, MDS, MPH, delivered an MVC data presentation focused on MVC’s new health outcome variation measure [See slides]. During the presentation, Narender Singh supplemented Dr. Nathan’s explanation of the measure definition (Figure 5), benefits, and rollout timeline with MVC member unblinded data and case scenarios. An introductory video for the health outcome variation measure is available on MVC’s P4P webpage.

Figure 5.

explanation of the health outcome variation measure definition, benefits, and rollout timeline

Attendees spent time in the afternoon in various breakout sessions (Figure 6) learning about strategies from other MVC members to address non-medical drivers of health outcomes [See slides].

Figure 6.

breakout session titles and descriptions

The meeting closed with a reflection of the day spent together and reminders about upcoming meetings and events [See slides].

What are the attendees saying about the meeting?

“I gained a lot of insight and ideas to take back to my organization to review with others.”

“I learned that patients can be in home care and cardiac rehab at the same time which is a game changer for us.”

“Enjoyable to see the multi-faceted approaches that are being used throughout the state's regions for decreasing readmissions.”

“I really enjoyed the breakout sessions and discussions!”

“Loved the ability to talk with other groups and learn from each other. Like the unblinded data, it was more meaningful to what was being discussed.”

If you have questions about any of the topics discussed at MVC’s fall collaborative-wide meeting or are interested in following up for more details, email the MVC Coordinating Center. MVC’s next collaborative-wide meeting will be in person on Fri., May 8, 2026, in Traverse City.

Off
View Post
Fall Collaborative-Wide Meeting Agenda, Speakers Announced

Fall Collaborative-Wide Meeting Agenda, Speakers Announced

The MVC Coordinating Center is excited to announce the agenda for its fall collaborative-wide meeting on Fri., Oct. 10, 2025, from 10 a.m. – 3 p.m., at the Vistatech Center in Livonia, MI. This meeting’s theme is “Adapting Together in 2025 and Beyond: High-Value Care for All in a Changing Landscape.” This meeting will highlight the various ways in which MVC's members identify gaps in outcomes, adapt to ensure all patients receive the highest quality care, and establish partnerships and programs that mitigate non-medical drivers of health outcomes. Those interested in attending MVC's fall 2025 collaborative-wide meeting must register here by Thurs., Sept. 25.

MVC Director Mark Bradshaw, MSc, will kick off the day with Coordinating Center updates as well as announcements about the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This will be followed by updates about 2026 engagement offerings presented by MVC Engagement Manager Jessica Souva, MSN, RN, C-ONQS.

MVC will then invite its first guest speakers of the day to the podium: Julia Weinert, MPH, MSHIELD Program Manager, and Brad Iott, PhD, MPH, MSHIELD Content Expert in Health Informatics and Social Care Integration. The MSHIELD team will lay the foundation for the day by discussing non-medical drivers of health and related implications for quality improvement teams, including examples of metrics that help evaluate care across all patients and interventions that can help reduce gaps in patient outcomes.

The event keynote will follow with a presentation by Gloria Rey, PA-C, MPH, Director of Post-Acute Care, Henry Ford Health. She will present on Henry Ford’s post-acute care (PAC) transition program, and the ways in which their team partners with PAC groups to ensure effective, individualized handoffs and care delivery for all patients.

Following lunch and networking, MVC Medical Director Hari Nathan, MD, PhD, will co-present with MVC Analyst Kushbu Narender Singh, MDS, MPH, for MVC’s Data in Action presentation. This data presentation will focus on MVC’s newest health outcome variation measure, including how it was developed, its use cases and benefits, a timeline for related data sharing, and unblinded data. This measure was a new addition to the MVC Component of the BCBSM P4P Program, with scoring on this measure beginning in Program Years 2026-2027.

Attendees will then transition into the afternoon breakout sessions, all led by guest hospital presenters. To showcase how members are addressing variation in outcomes, MVC invited presenters to discuss recent initiatives and successes across a range of focus areas, such as partnerships with community-based organizations, systematic approaches to referrals, and predictive analytics and assessment tools in EPIC. View a summary of all five breakout presentations here. Attendees will attend two breakout sessions before returning to the main ballroom for closing remarks and next steps.

The deadline to register for MVC’s fall 2025 collaborative-wide meeting is tomorrow, Sept. 25. We look forward to seeing you there!

Off
View Post
Push Report Details New MVC Measure that Quantifies Gaps in Patient Outcomes

Push Report Details New MVC Measure that Quantifies Gaps in Patient Outcomes

MVC distributed a new push report on Aug. 28, highlighting the components and methods for MVC’s newest measure: health outcome variation for all-cause readmissions. The goals of the recently distributed push reports are to familiarize hospital members with the measure methodology as well as provide a first look at their hospital’s performance.

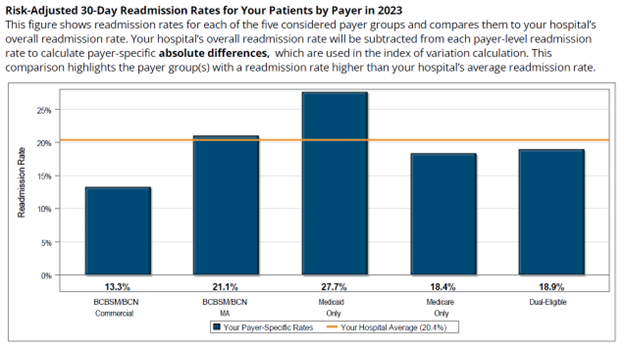
This measure was developed with the goal of addressing common challenges by MVC’s members in identifying and addressing gaps in health outcomes within their patient populations. A survey distributed to the MVC collaborative in 2024 identified barriers such as insufficient data and insufficient financial investments as key causes for lingering variation across their patient population. With the introduction of MVC’s health outcome variation measure, MVC seeks to quantify the magnitude of hospital-level variation in all-cause readmission rates between payer groups using an index of variation calculation. Readmission rates are risk adjusted for patient demographic and comorbidity data, as well as for non-medical drivers of health.

The first two pages of the push report provide a step-by-step walkthrough of the index calculation, beginning with the calculation of absolute differences in hospital-level readmission rates by payer group compared to the hospital-level average readmission rate. The five payer groups included in these calculations are BCBSM and BCN Commercial, BCBSM and BCN Medicare Advantage, Medicaid only, Medicare FFS only, and patients dual-eligible for Medicaid and Medicare; dual-eligible patients have been pulled out of the Medicaid only and Medicare only categories. This initial step helps to highlight which payer group(s) have a higher readmission rate than the hospital’s average rate (Figure 1).

Figure 1.

vertical bar chart of calculation of absolute differences in hospital-level 30-day readmission rates by payer group compared to the hospital-level average readmission rate

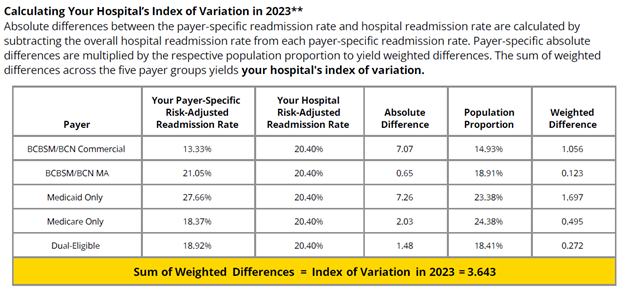
The next step in the methodology is to calculate a hospital’s index of variation using absolute differences in payer-specific risk-adjusted readmission rates compared to the hospital’s risk-adjusted average readmission rate. These payer-specific absolute differences are multiplied by the respective payer population proportion to yield weighted differences (Figure 2). The sum of those weighted differences across all five payer groups yields the hospital’s index of variation. This index calculation indicates the magnitude of payer-specific differences in risk-adjusted readmission rates within a hospital. A higher value indicates a larger spread in a hospital’s payer-specific risk-adjusted readmission rates as well as opportunities to develop strategies that reduce gaps in care across patient groups. A lower value is desired and indicates less variation in a hospital’s risk-adjusted readmission rates across payers.

Figure 2.

table: demonstration calculation a hospital’s index of variation using absolute differences in payer-specific risk-adjusted readmission rates compared to the hospital’s risk-adjusted average readmission rate

MVC first announced this measure at its fall 2024 collaborative-wide meeting, where Senior Advisor Jim Dupree, MD, MPH, announced its inclusion in the next cycle of the MVC Component of the BCBSM Pay-for-Performance (P4P) Program. Scoring on this measure will be offered in the Program Year (PY) 2025 scorecards with no points attached and thereafter will be worth one point in the PY 2026-2027 cycle.

Similar index or composite measures have been utilized by other health organizations, and MVC’s risk-adjusted measure can help identify hospital-level preventable differences in readmissions. Hospitals will earn the health outcome variation point by improving relative to their own baseline index or by performing well relative to their peers (i.e., having an index at or below the collaborative-wide median index).

As hospitals review their provided push report and become familiar with this new health outcome variation measure, they are encouraged to reach out to MVC with any questions.

Off
View Post
Overcoming Non-Medical Drivers of Health: A Success Story at Marshfield Medical Center-Dickinson

Overcoming Non-Medical Drivers of Health: A Success Story at Marshfield Medical Center-Dickinson

In recent years, the pursuit of high-quality healthcare has pushed an increasing number of organizations to consider how tailored approaches can reduce variation in health outcomes, increase the value of care, and enhance patient experiences with the healthcare system. Reflecting this growing recognition, the Michigan Value Collaborative (MVC) surveyed its members in 2024 to better understand how members were identifying gaps in care and responding to non-medical drivers of health. With questions focused on data collection, strategic planning, and programming, MVC gleaned a wealth of impactful and innovative solutions already under way in hospitals across the state.

For the majority of the surveyed hospitals, the most common focus areas for programming were enhancing provider availabilitiy (i.e., telehealth, mobile units, and nontraditional clinic hours), improving access to reliable transportation, offering financial support, and providing translated materials. Although it is common for hospitals to have strategies in place in these areas, the specific approaches are often as varied as the communities they serve.

At Marshfield Medical Center-Dickinson, for example, one way they approach gaps in preventative care within the community is through dental care programming. Recent studies have established a clear link between oral health and overall health, underscoring the importance of proper dental hygiene as a preventive measure against serious health complications. According to the Mayo Clinic, poor oral health can lead to significant conditions such as endocarditis, cardiovascular disease, pregnancy complications, and pneumonia. Consequently, effective dental hygiene education and preventive care can provide substantial health benefits that extend well beyond oral health alone.

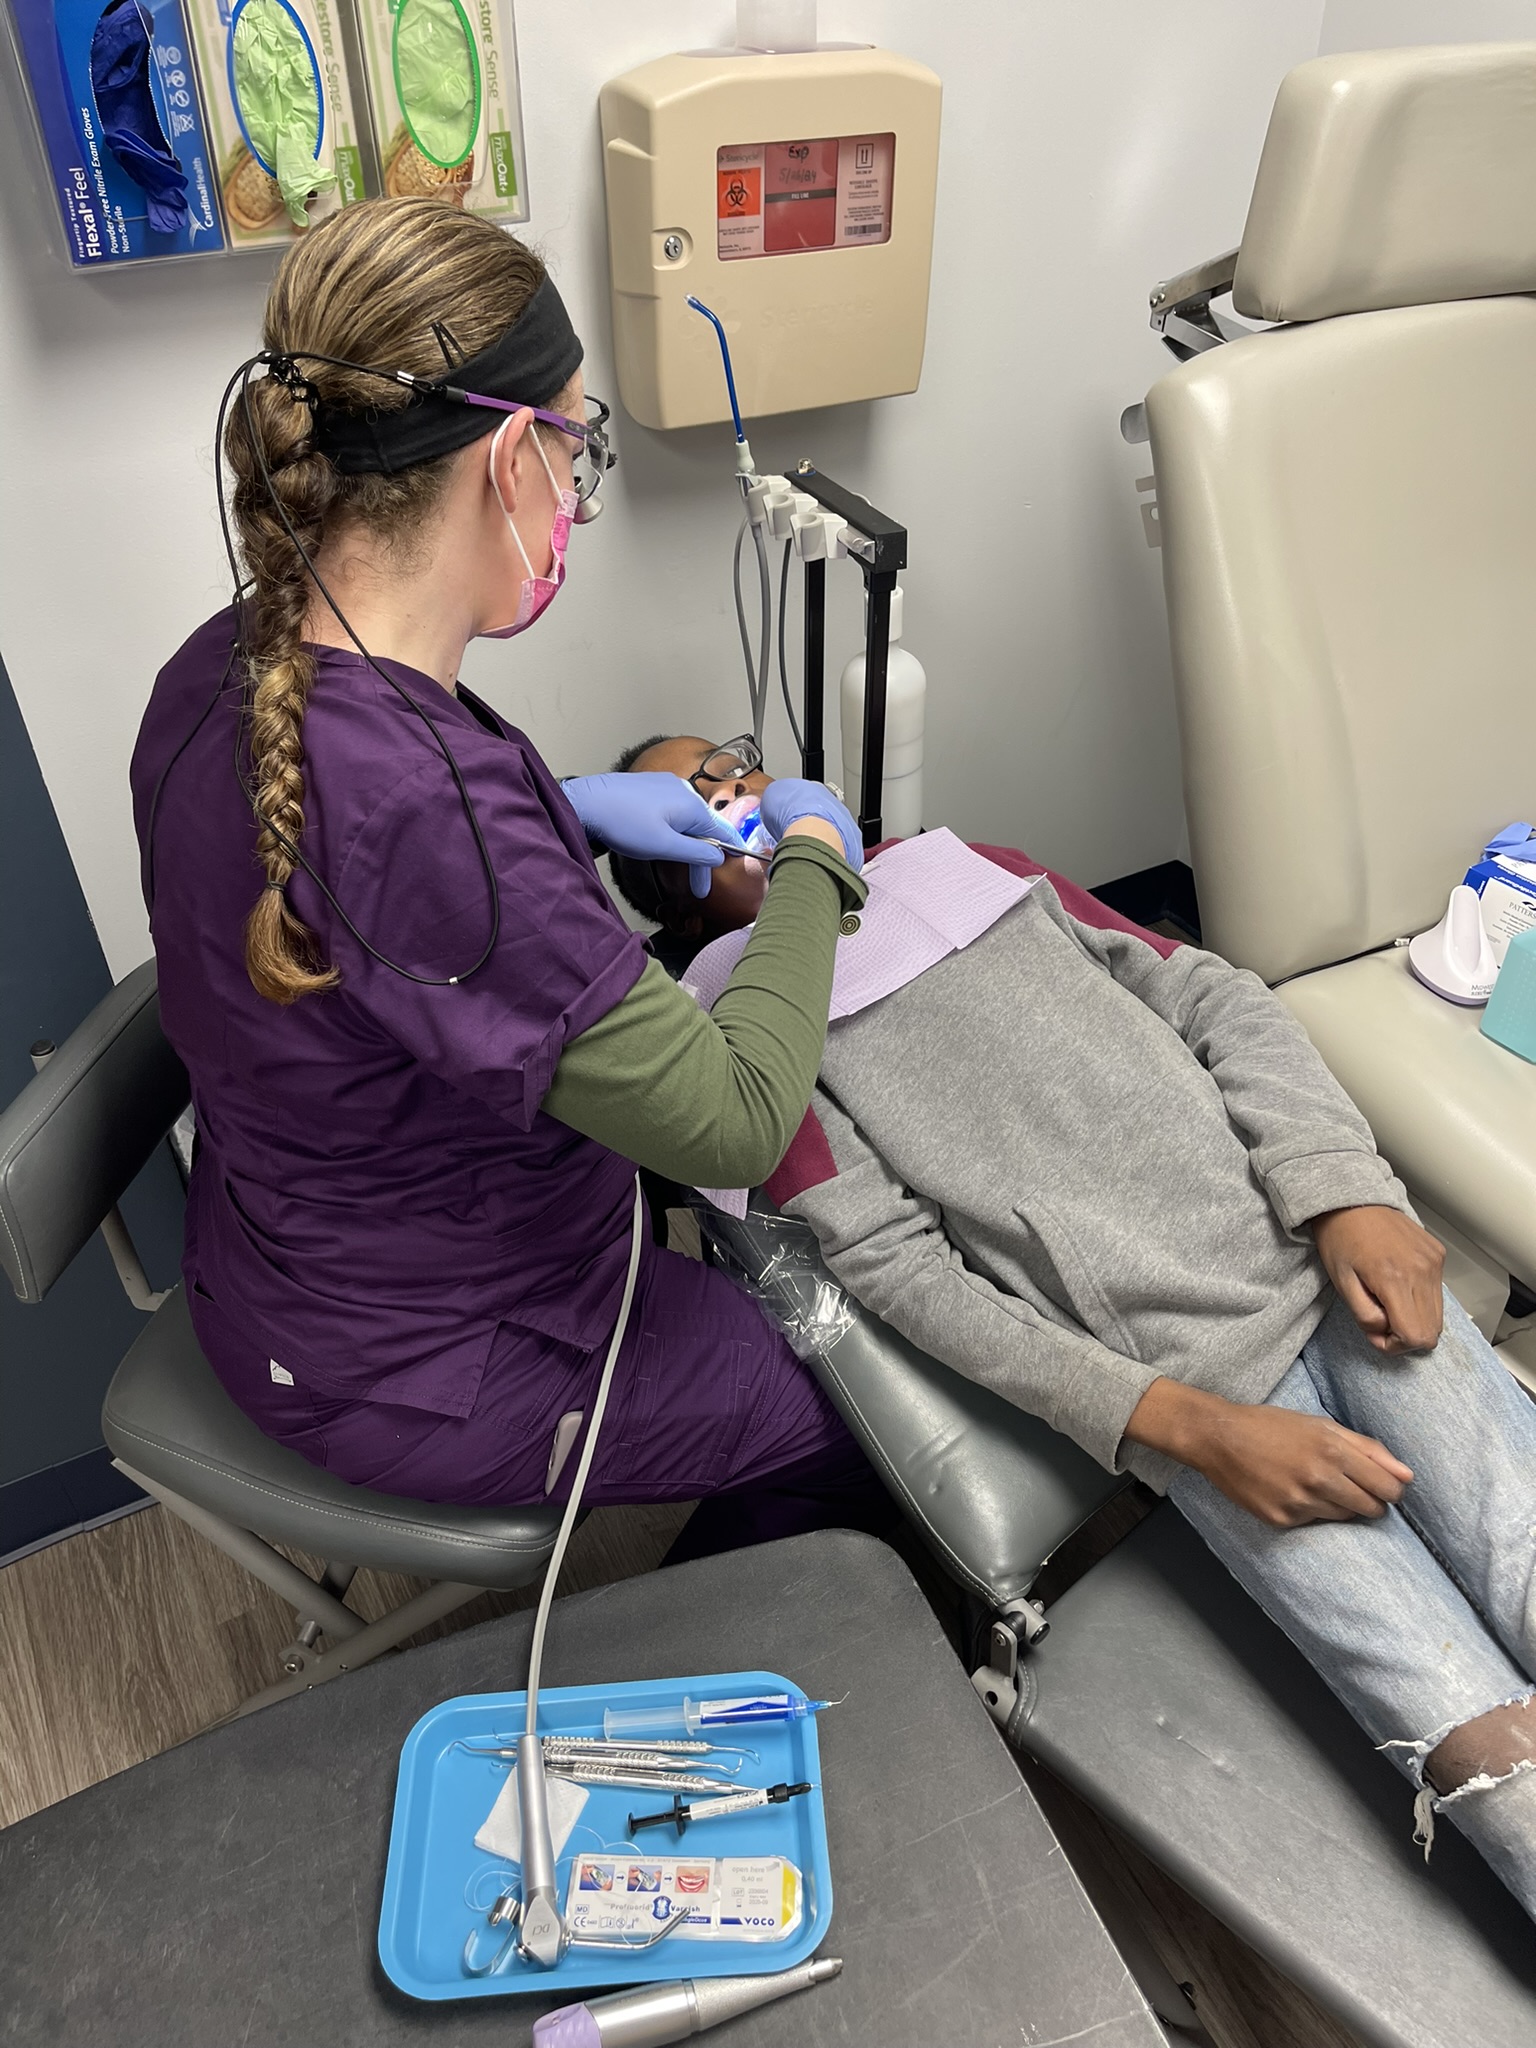
Recognizing the multifaceted benefits of accessible oral healthcare, Marshfield has partnered with Smiles on Wheels to offer monthly dental services—including cleanings, sealants, and fluoride treatments—at their primary care clinic, regardless of insurance. This initiative has been especially beneficial for young children and parents who face financial challenges related to transportation, and helps Marshfield to more effectively ensure high-value care for all patients. It also helps families avoid future costs associated with more complex treatments that may result from a lack of preventive care. The program has received positive feedback from the patient population, with many community members expressing their gratitude for the support it provides.

Figure 1. Smiles on Wheels provides dental care services to Marshfield Medical Center-Dickinson patients during wellness care visits.

photo: Smiles on Wheels providing dental care services to Marshfield Medical Center-Dickinson patient during wellness care visit

Photo courtesy of Marshfield Medical Center-Dickinson

Dr. Alexis Cirilli Whaley, MMC-D Pediatrician said, “We are fortunate to have Smiles on Wheels offering dental care to our local children, particularly for those families needing additional support due to economic stressors. The initiative allows for increased access to dental treatment, conveniently scheduled during wellness care visits."

By partnering with Smiles on Wheels, Marshfield Medical Center-Dickinson is leveraging existing resources to create a meaningful impact. This collaboration optimizes the use of available assets and showcases an effective strategy that harnesses the strengths of community partners. Stories like that of Marshfield Medical Center-Dickinson highlight the power of community partnerships in bridging known gaps in care and making a significant difference.

If your hospital or organization has an initiative they would like to share, please contact the Coordinating Center at Michigan-Value-Collaborative@med.umich.edu – we would love to hear from you.

Off
View Post
Health Equity in Action: Using Data to Drive Systematic Change

Health Equity in Action: Using Data to Drive Systematic Change

In the United States, disproportionate rates of chronic disease and illness are commonly documented among communities of color. National Minority Health Month (NMHM) takes place throughout April as a way to raise awareness about health disparities among minority groups and how racism and barriers to healthcare access have historically marginalized such groups. According to the CDC, health equity is “the state in which every individual has a fair and just opportunity to attain their highest level of health.” To achieve such a state, extensive efforts are necessary to address systematic injustices and support equitable access to healthcare.

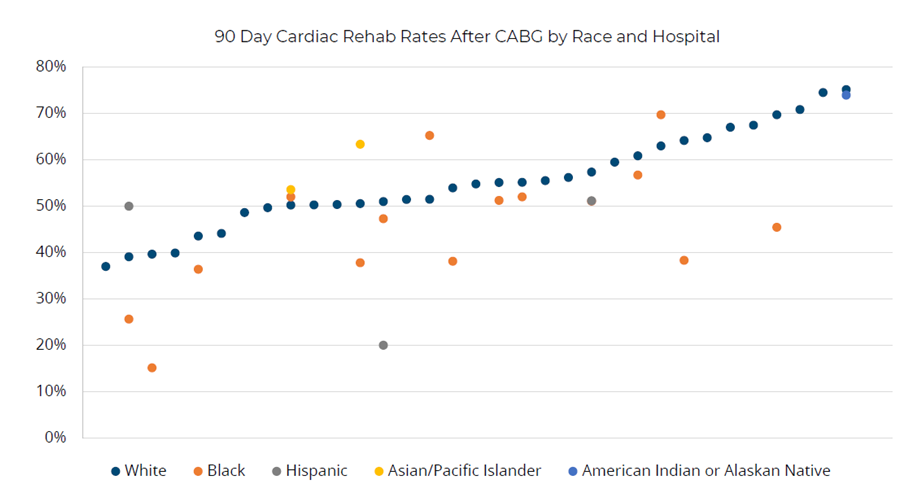
At MVC, emphasizing this vast issue and supporting change begins with one critical step: identifying and quantifying current disparities within patient communities in Michigan. MVC is utilizing claims-based data analytics to identify differences in care for specific patient demographic groups. For instance, in a recent analysis of MVC claims, MVC found differences by race in the rates of patients attending cardiac rehabilitation after a coronary artery bypass graft (CABG), with lower average utilization rates among some minority groups compared to patients who are white and higher average utilization rates among other minority groups (Figure 1). There are also significant disparities in cardiac rehabilitation utilization rates after CABG by gender and payer categories. Highlighting the landscape of current healthcare utilization may help quality improvement teams understand where disparities exist within their patient populations and prompt discussions about the social and environmental circumstances that may contribute to such findings.

Figure 1.

MVC also recently collected surveys from its members on their health equity priorities, challenges, and initiatives to date. The survey results will be summarized at MVC’s upcoming spring collaborative-wide meeting, and some of the survey responses will be further expanded upon and shared with members as blogs and case studies to provide real-world examples of the work happening in hospitals across the state. Since health equity is a strategic priority for many healthcare teams, MVC’s recent survey was developed to help members understand what others are doing and facilitate shared learning on this topic.

However, there is also much to learn from national examples and strategies. In December 2022, for example, Blue Cross Blue Shield of Massachusetts announced the creation of payment contracts that provide financial rewards to practices addressing racial and ethnic inequities in healthcare delivery. Dr. Mark Friedberg, Senior Vice President, Performance Measurement and Improvement at Blue Cross explained, “This encourages health care systems to increase their investments in developing, expanding and sustaining programs that produce measurable improvements in equity.” This financial investment is a huge breakthrough for Blue Cross which will allow healthcare providers and organizations to learn what barriers to care exist and methods of resolution.

Financial incentives focused on equity are also a large component of State Medicaid strategies. In California, Medicaid plans could earn incentive funds by demonstrating improvement in the two race/ethnicity groups with the lowest baseline vaccination rates. In Michigan, there are financial incentives for using withheld funds for improvement on a subset of quality measures within the African American and Hispanic population groups. As more states and systems begin to invest in financial incentives with equity goals, MVC is working to re-evaluate the methodologies and metrics of the MVC Component of the BCBSM Pay-for-Performance (P4P) Program for opportunities to similarly incentivize and reward achievement and/or improvement in equitable care delivery.

As health equity activity continues to grow and evolve, MVC is committed to expanding its data sources and reporting to support members' understanding of the needs of their patients. Studies emphasize that disparate health outcomes are closely related to social determinants/influencers of health (SDOH/SIOH), with social factors often predicting the incidence of illness and disease. It is for this reason that MVC has continued to incorporate Distressed Communities Index (DCI) data into patient demographic tables in MVC push reports, in addition to stratifying select outcome measures by relevant demographic categories. MVC continues to explore opportunities to integrate additional supplemental SDOH data sets into its analyses – a recent example was shared at MVC’s October collaborative-wide meeting presentation (see slides), which focused on the relationship between county-level social need indicators and post-discharge care utilization.

Organizational strategies and investments are rapidly growing and evolving within healthcare, and will likely be necessary for years to achieve meaningful improvements. MVC is eager to support member activity in this space to achieve high-value care for all and will continue to highlight the excellent work and success stories happening across its membership. If you have a success story to share or would like to request a custom analysis focused on a specific patient population, please contact the MVC Coordinating Center.

Off
View Post
MVC Celebrates National Rural Health Day with MyMichigan Workgroup Presentation

MVC Celebrates National Rural Health Day with MyMichigan Workgroup Presentation

Today is National Rural Health Day. Since 2010, the National Organization of State Offices of Rural Health set aside the third Thursday of every November to highlight the unique healthcare challenges facing residents within rural communities and celebrate providers who deliver innovative, affordable, and coordinated rural healthcare. MVC’s current membership includes 44 hospitals based in rural communities, 22 of which are designated as Critical Access Hospitals (CAHs). In tribute to National Rural Health Day and the needs of its growing rural membership, MVC hosted a special rural health workgroup yesterday.

The workgroup featured a guest presentation by Stephanie Pins, MSA, CPHQ. Pins is the Director of Quality, Risk, and Compliance for MyMichigan Medical Center Sault, formerly War Memorial Hospital, and is co-leading the Health Equity Council for MyMichigan Health. She led the creation of a transportation program for War Memorial Hospital by working with local transportation companies and applying for grants to cover the cost of the program.

This guest presentation focused on how MyMichigan is supporting rural communities through their Non-Emergency Medical Transportation (NEMT) Project, and the steps their team took to develop this program. Beginning in 2024, CMS will require that hospitals screen admitted patients for five social determinants of health (SDOH) domains. One of those five required domains is transportation needs since access to transportation and distance to care have a significant impact on healthcare outcomes.

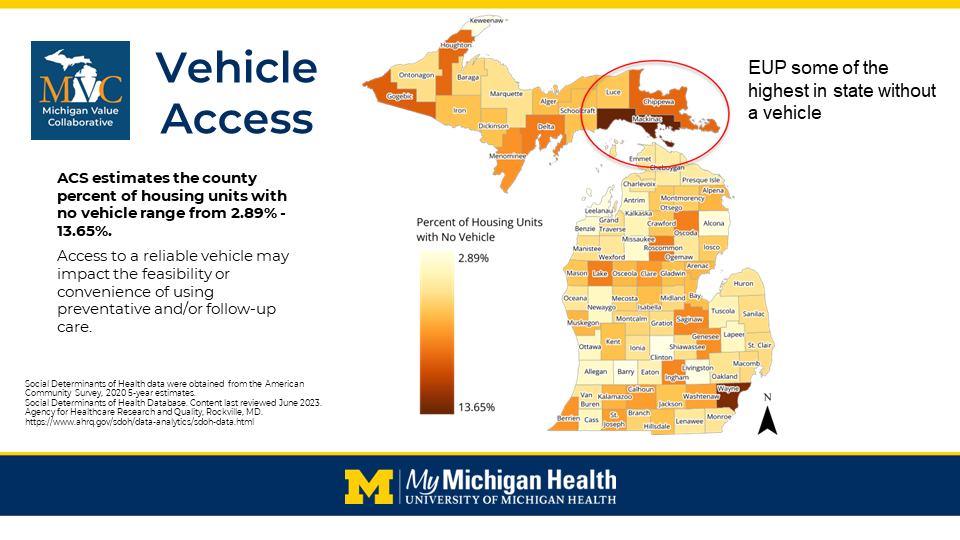
MyMichigan Medical Center Sault primarily services the very rural communities of Chippewa, Luce, and Mackinac counties, located in the eastern Upper Peninsula of Michigan. A resident of Drummond Island—part of Chippewa County—may have to drive as many as 70 miles each way to get to an appointment at MyMichigan Medical Center Sault. Limited vehicle access in this part of the state was highlighted recently at MVC’s fall collaborative-wide meeting; the eastern Upper Peninsula had some of the highest rates in the state for housing units with no vehicle (Figure 1).

Figure 1.

While presenting, Pins emphasized that once MyMichigan identifies a need through screening, the next step is to find a way to connect those patients with the assistance they need to access medical care. One transportation solution utilized by MyMichigan Medical Center Sault is the Road-to-Recovery program, offered in partnership with McLaren Northern Michigan in Petoskey. The MyMichigan Medical Center Sault location offers some oncology cancer treatment services, but not radiation, so patients may need to travel to Petoskey—a distance of over 90 miles—to receive radiation therapy as part of their cancer treatment. The fully funded Road-to-Recovery program is available five days a week free of charge to anyone in the eastern Upper Peninsula. A hospital-owned van is driven by a volunteer driver from the MyMichigan Medical Center Sault location to scheduled pick-up locations along the I-75 corridor to Petoskey. Service times are coordinated with McLaren Northern Michigan’s oncology group so all the patients using this service have aligned appointment times. Pins shared that one noteworthy ancillary benefit of this program has been the peer support and relationship building that resulted from patients traveling together for extended periods while going through a similar treatment experience.

A second transportation solution utilized by MyMichigan Medical Center Sault is the Rides-to-Wellness Program, a partnership effort with local transportation companies and Connect UP. Patients can use this service to travel to other appointments or patient care services and serves as a critical stopgap in ensuring patients have somewhere to turn for time-sensitive transportation needs. Pins shared that the patient testimonials from those utilizing the service are helpful evidence of its value to the eastern Upper Peninsula (Figure 2).

Figure 2.

MyMichigan Medical Center Sault identified several lessons learned from delivering its Rides-to-Recovery Program over the last 10 years and applied many of those lessons to the development of its more recent Rides-to-Wellness Program. Pins also shared several tips for starting similar hospital-based transportation support programs at other locations throughout the state (Figure 3).

Figure 3.

Those who missed the workgroup and would like to learn more about these two programs, how they are managed, and how they were developed can review the full recording here. MVC is excited to offer a new rural health workgroup series quarterly in 2024. Contact MVC if you are interested in receiving invitations to those workgroups.