Off
View Post
Hospitals Receive PY 2026 Mid-Year Scorecards for MVC Component of BCBSM P4P Program

Hospitals Receive PY 2026 Mid-Year Scorecards for MVC Component of BCBSM P4P Program

Earlier this month the Michigan Value Collaborative (MVC) distributed mid-year scorecards for Program Year (PY) 2026 of the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. PY 2026 marks the first year of the two-year (PY 26-27) P4P cycle, and includes Medicaid claims as well as the newly introduced health outcome variation measure in the scoring. This report provided hospitals with their current standing for PY 2026.

Each participating hospital received a mid-year score out of a total of 10 points, including 0 to 3 points for their selected total episode payment metric, 0 to 4 points for their selected value metric, 0 to 1 point for health outcome variation measure and 0 to 2 points for completed eligible engagement activities. PY 2026 scores achievement and improvement points for each metric using index admissions from 2025 performance year data against admissions in 2023 as the baseline year. Hospitals are awarded the higher of their achievement and improvement point scores.

The performance data timeframes included in mid-year PY 2026 scoring were index events 1/1/2025 – 12/31/2025 for BCBSM PPO Commercial, BCBSM Medicare Advantage (MA), BCN HMO Commercial, BCN HMO MA, Medicaid and index events from 1/1/2025 – 6/30/2025 for Medicare FFS. For the health outcome measure, the performance data included were index events from 1/1/1015 – 6/30/2025 to reflect the most recent date range for all payers. The engagement points accrued represent all completed activities from 1/1/2026 – 9/2/2026. All scores are subject to change in the final scorecards as the remaining 2025 performance data becomes available and additional 2026 P4P engagement activities are completed and recorded for this year.

Figure 1 illustrates the current distribution of total points out of 10 across the collaborative. The average points scored across the mid-year scorecards was 5.2 out of 10 and ranged between 0.5 and 10 points. This average is 1.5 points lower than the average points scored at the conclusion of PY 2025.

Figure 1. PY26 Mid-Year Distribution of Total Points Out of 10 Across the Collaborative

Dot plot ranks MVC Hospitals participating in PY26–27 P4P Program by PY26 mid-year score, with scores ranging from roughly 0.5 to 10. Blue hospital markers rise steadily across rankings, while an orange horizontal line marks mean and median at 5.2.

Figure 2 illustrates the breakdown of scoring on average by each program component (i.e., episode spending metric, value metric, health outcome variation measure and engagement points). Hospitals could earn up to three points for their episode spending, four points for their value metric selections, one point for health outcome variation measure and up to two points for engagement activities completed in 2026. Across collaborative, the average points scored for episode spending and value metrics were 1.0 point, and 2.2 points respectively. For the newly introduced health outcome variation measure, the average was 0.6 points and the average for engagement activities was 1.4 points.

Figure 2. PY26 Mid-Year Scoring on Average by Each Program Component

Bar chart showing average points scored across hospitals by category, with y-axis ranging 0–10 points. Blue bars show Episode Spending 1.0/3, Value Metrics 2.2/4, Health Outcome Variation 0.6/1, Engagement 1.4/2, and Total Points 5.2/10.

Figure 3 illustrates the breakdown of the average points by episode spending conditions. Coronary Artery Bypass Grafting (CABG) and Congestive Heart Failure (CHF) were both the highest scoring episode spending conditions with an average of 1.3 points, and this was followed by chronic obstructive pulmonary disease (COPD) with 1 point. The lowest scoring episode spending condition was pneumonia with hospitals earning 0.4 points on average.

Figure 3. PY26 Mid-Year Average Points by Episode Spending Conditions

Bar chart compares average points scored across episode spending conditions: CABG 1.3, CHF 1.3, COPD 1.0, and PCI 0.4. Blue patterned bars use a 0–3 vertical scale, with mean and median both marked as 1.0.

Figure 4 illustrates the breakdown of average points by value metrics. Consistent with PY 2025, the highest scoring value metric was preoperative testing with 3.5 points, followed by 90-day cardiac rehabilitation after CABG with 3.0 points. All follow up metrics had an average score of below 2 points with the lowest scoring value metric being 14-day follow up after COPD with 1.1 points.

Figure 4. PY26 Mid-Year Average Points by Value Metrics

Bar chart compares average points scored across value metrics for preoperative testing and follow-up categories. Dark blue bars decline from 3.5 for preoperative testing to 1.1 for 14-day follow-up after COPD, with mean 2.2 and median 2.0 marked at upper right.

These PY 2026 P4P mid-year scores are subject to change as new data is added. The final scores will be distributed after all 2025 claims are incorporated into the calculations. The full methodology for this program cycle can be found in the PY2026-2027 technical document. Hospitals can also track their score via the P4P PY 2026-2027 dashboard reports on the MVC registry, which provides all relevant scoring information for both improvement and achievement points. These registry reports can be filtered by selected conditions/metrics to make tracking of P4P points easier. You can also contact the MVC Coordinating Center by email for a walkthrough of your hospital’s PY 2026 mid-year scorecard or P4P registry reports.

0
View Post
MVC July Workgroups Highlight Sepsis Discharge Planning in CAHs and MVC’s Follow-Up Push Report

MVC July Workgroups Highlight Sepsis Discharge Planning in CAHs and MVC’s Follow-Up Push Report

In July, the Michigan Value Collaborative (MVC) hosted two virtual workgroup presentations. The first, a rural health workgroup focused on MyMichigan Health’s system-wide sepsis discharge planning follow-up initiative implementation at critical access hospital (CAH) sites. The second, a post-discharge follow-up workgroup, provided a walk-through of MVC’s recent Follow-Up push report including recommendations on practical applications of the report to identify opportunities for improvement. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action.

Rural Health Workgroup: MyMichigan

During MVC’s first workgroup of July, Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Based Care for MyMichigan Health System, shared how their health system developed and implemented a standardized post-discharge follow-up process for patients hospitalized for sepsis. Recognizing the lasting physical and cognitive effects many sepsis patients experience after discharge, Pins-Schallip explained how this initiative was designed to target care transitions, reinforce discharge education, and connect patients with appropriate follow-up care across all MyMichigan Health hospitals. Pins-Schallip also explained how this initiative aimed to drive at both MVC and Michigan Hospital Medicine Safety Consortium (HMS) goals and found ways to benefit sites within the system not engaged with these CQI incentive programs.

Rather than developing separate workflows at each hospital, MyMichigan Health pursued a standardized, system-wide approach. This allowed hospitals of varying sizes, including rural and critical access facilities, to implement consistent practices while also leveraging shared resources. The first step of the initiative was identifying a reliable phone number to provide on discharge paperwork that would connect patients to “on call” Hospitalist providers. By utilizing the health system’s existing 24/7 Transfer Center phone number and nurses already staffing this communication center hub, this minimized the need for additional personnel while also providing patients with a reliable point of contact after leaving the hospital.

Figure 1. Process for 24/7 Transfer Center Calls

A text-based process list outlining steps for patient follow-up after sepsis diagnosis, including discharge, post-discharge questions, 24/7 bed placement call, messaging to hospitalist, and hospitalist follow-up. The list is presented with a MyMichigan Health University of Michigan Health footer in blue and yellow colors.

Pins-Schallip reviewed a selection of sepsis patient calls to the Transfer Center noting that the volume of calls since initiation of the program have been fewer than five. However, the time between a patient calling and resolution of their question is estimated to be on average less than one hour. To date, patient concerns primarily revolve around antibiotic prescription questions.

Throughout implementation, Pins-Schallip noted that the team emphasized collaboration across departments, including hospitalists, nursing, care management, information technology, and executive leadership. Strong physician engagement and support from MyMichigan’s chief medical officer were instrumental in successfully implementing standardized workflows across the health system. With a relatively recent “go live” for this program of July 2026, Pins-Schallip explained that regular feedback gathered from frontline staff and patient data will allow the team to continue to refine the process over time and adapt workflows based on operational experiences.

During the discussion portion of the workgroup, participants enquired about adapting the workflow for other patient populations, implementation at smaller or independent hospitals, and strategies for gaining physician buy-in. Pins-Schallip encouraged organizations to begin with existing resources whenever possible, noting that many hospitals already have personnel or infrastructure that can be leveraged for post-discharge outreach. The importance of executive sponsorship and continuous evaluation were also identified as key strategies to ensure new workflows remain sustainable and effective.

MVC Rural Health Workgroup: July 14, 2026

Post-Discharge Follow-Up Workgroup: MVC Coordinating Center

The second workgroup in July featured a walkthrough of MVC’s new Follow-Up push report, presented by Janet Zhang, MPH, MVC Data Analyst, and Rachel Folk, MHA, MVC Site Engagement Coordinator. Developed to support hospitals interested in further understanding opportunities for improvement, the report provides hospital- and system-level insights into post-discharge follow-up patterns for patients hospitalized with congestive heart failure (CHF), chronic obstructive pulmonary disease (COPD), pneumonia, and sepsis. The report evaluates patterns of follow-up completed within three, seven, and 14-days after discharge using claims data from Blue Cross Blue Shield of Michigan and the Centers for Medicare & Medicaid Services.

Figure 2. MVC Follow-Up Push Report Details

Report details slide presents data parameters for a 30-day inpatient episode analysis covering four MVC conditions: CHF, COPD, Pneumonia, and Sepsis, with payer data date ranges for BCBSM PPO, MA, BCN HMO, BCN HMO MA, Medicare FFS, and Medicaid. Outcome measures include follow-up rates at 3, 7, and 14 days post-index, excluding visits after readmission, inpatient procedures, emergency visits, skilled nursing admissions, or inpatient rehabilitation..

To begin, Zhang reviewed the design of the report outlining how hospitals can use the system-level report to identify variation in follow-up performance across hospitals within the same system. At the system level this report can help leaders recognize opportunities to share successful practices across sites. At the hospital level, the report provides additional context through patient demographic information, non-medical drivers of health, and analyses stratified by payer and follow-up status. Together, these visualizations help members identify where opportunities to optimize follow-up may exist and prioritize improvement efforts.

Next, using a blinded sample report, Folk demonstrated how members can translate their own report findings into actionable quality improvement opportunities. Using the sample blinded report as a template, the remainder of the presentation guided participants through the next steps to finding actionable insights including the identification of areas of opportunity. In this particular report, Folk identified the following areas of opportunity:

  1. Sepsis has the lowest overall follow-up rates at three, seven and 14-days after discharge.
  2. All conditions show lower rates of seven and 14-day follow-up for Medicaid FFS and Dual Eligible payers.
  3. COPD and sepsis patients that attend follow-up within 14-days after discharge have lower 30-day risk-adjusted, price-standardized total episode payments.

As a next step, Folk walked participants through samples of related goal setting and suggested action items for two priority metrics: COPD 7-day follow-up and sepsis 14-day follow-up.

Between COPD and sepsis, the evidence-based action items reviewed included:

  • Schedule follow-up appointments before discharge
  • Confirm medication and follow-up provider access prior to discharge
  • Referral placement for smoking cessation and rehab as indicated
  • Document and review medical care action plans
  • Connect high-risk patients to care management follow-up
  • Flag patients discharged to home without home health as high priority

As part of an interactive discussion, participants were asked to vote on the follow-up intervention they’d most likely implement to drive further discussion.

Figure 3. Screenshot of Follow-Up Intervention Interactive Discussion

Diagram of five color-coded sticky notes outlining steps to improve post-discharge patient care, including scheduling follow-ups, outreach workflows, discharge planning barriers, clinic coordination, and data analysis. Each note features check marks and symbols in various colors, highlighting high interest and key focus areas for high-risk patients and priority conditions.

Throughout the discussion, participants shared experiences and challenges related to improving post-discharge follow-up within their organizations. While several members identified building structured outreach workflows for high-risk patients and scheduling follow-up appointments before discharge as high-priority areas, others discussed practical barriers to these interventions including coordinating care with independent primary care practices, transportation challenges, and difficulty reaching patients by telephone after discharge. Participants also exchanged ideas such as utilizing nurses on light duty to conduct follow-up calls, incorporating virtual and remote monitoring for rural populations, and partnering with home health agencies to reinforce patient education.

The discussion also highlighted opportunities to maximize the value of MVC reports by combining claims data-based insights with internal quality dashboards and other collaborative initiatives. Members expressed continued interest in additional education on integrating MVC reports with other quality improvement efforts and using benchmarking data to communicate opportunities and progress with organizational leadership.

MVC Post-Discharge Follow-Up Workgroup: July 23, 2026

For MVC members seeking additional support related to claims data, please reach out to us by email. MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. If you are interested in being a workgroup presenter please submit a presentation proposal here.

Off
View Post
MVC Push Report Benchmarks Follow-Up Rates for CHF, COPD, Pneumonia, and Sepsis Patients

MVC Push Report Benchmarks Follow-Up Rates for CHF, COPD, Pneumonia, and Sepsis Patients

The Michigan Value Collaborative (MVC) distributed hospital-level follow-up push reports recently intended to support the evaluation of long-term trends as well as the identification of gaps in follow-up care across differing patient demographics. This report focused on follow-up care after hospitalization for congestive heart failure (CHF), chronic obstructive pulmonary disease (COPD), pneumonia, and sepsis—four of MVC’s value metrics for Program Years 2026-2027 of the MVC Component of the BCBSM Pay-for-Performance (P4P) Program.

While MVC also provides reporting on its P4P value metrics via scorecards and registry reports, this push report provided additional data on follow-up care at member hospitals by showcasing variability across a longer analytic timeframe and more detailed stratifications for its 30-day CHF, COPD, pneumonia, and sepsis episodes. MVC defined follow-up as episodes where a patient had an outpatient follow-up visit (in person or by telehealth) within 30 days or before a readmission, inpatient procedure, emergency department visit, skilled nursing facility admission, or visit for inpatient rehabilitation.

Contained in each hospital’s report was a page dedicated to follow-up following hospitalizations for each condition. On those report pages, MVC hospitals received comparisons to their peers on outpatient follow-up rates and 30-day risk-adjusted total episode payments, as well as their hospital’s outpatient follow-up rates stratified by payer.

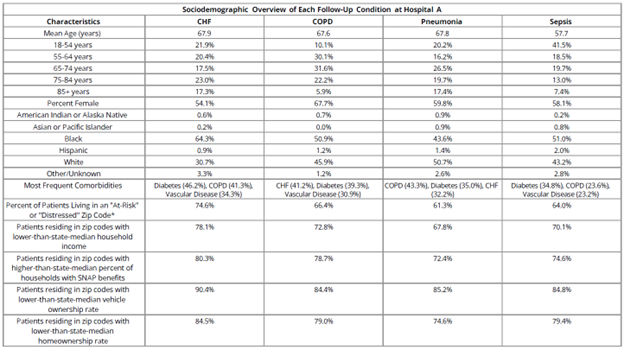
The report also featured a patient population snapshot table that highlighted demographic data for patients in each condition cohort. These tables (see Figure 1) provided each hospital with information on race, mean age, common comorbidities, and several indicators of non-medical drivers of health.

Figure 1. Sociodemographic Overview of Patients Receiving Follow-Up Following Discharge for CHF, COPD, Pneumonia, or Sepsis at Hospital A

Table presenting sociodemographic overview of follow-up conditions at Hospital A, including CHF, COPD, pneumonia, and sepsis. It details age groups, race/ethnicity percentages, common comorbidities, and socioeconomic indicators such as diabetes prevalence and living conditions, with data organized in rows and columns for comparison across conditions.

*Patient zip codes categorized as prosperous, comfortable, mid-tier, at-risk, or distressed according to the Economic Innovation Group's Distressed Communities Index 2018-2022, which incorporates economic indicators such as education, employment, and income.

Each figure reflected index admissions between 1/1/2023-12/31/2024 in BCBSM PPO Commercial, BCBSM PPO Medicare Advantage, BCN HMO Commercial, BCN HMO Medicare Advantage, and Medicare Fee-for-Service claims, and between 1/1/2023-9/30/2024 in Michigan Medicaid claims. Individuals insured by both Medicare and Medicaid were categorized as dual-eligible in the payer-specific figures. Hospital reports included pages for each condition if they met the threshold of at least 11 qualifying episodes in each year of data for that condition.

There was wide variation in follow-up rates across the collaborative for all four conditions, with some member follow-up rates averaging less than 20% to greater than 60% among CHF, COPD, and pneumonia patients, and between less than 30% to greater than 70% among sepsis patients.

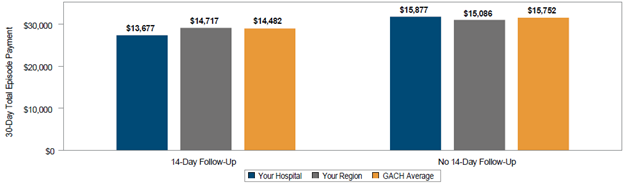
Among general acute care hospitals, there were consistent decreases in average follow-up rates across the collaborative compared to previous reporting; MVC provided reporting on these same follow-up measures in a Q1 2025 push report based on 2022-2023 claims. Using the updated 2023-2024 timeframe, the collaborative-wide average 14-day follow-up rate for patients hospitalized for COPD fell from 55.3% to 51%. A similar trend was observed for seven-day follow-up after CHF (decreased from 44.8% to 43.1%), seven-day follow-up after pneumonia (decreased from 42.7% to 41.6%), and 14-day follow-up after sepsis (decreased from 58% to 52.5%). Follow-up rates were often lowest among the Medicaid and dual-eligible patient populations (Figure 2), and are therefore a patient group that likely needs additional support and outreach. Additionally, across all four conditions the average risk-adjusted price-standardized total episode payment at general acute care hospitals was higher among patients who did not receive follow-up than among patients who received follow-up care (see COPD example in Figure 3).

Figure 2. 3-Day, 7-Day, and 14-Day Follow-Up Rate Among Patients Hospitalized for Sepsis by Payer for Hospital A

Bar chart comparing follow-up rates across five insurance categories with three time intervals: 3-day, 7-day, and 14-day follow-ups, represented by blue, gray, and orange bars respectively. Notable trends include consistently higher follow-up rates at 14 days, with Commercial insurance showing the highest rates.

Figure 3. Average 30-Day Risk-Adjusted, Price-Standardized Total Episode Payment Among Patients Hospitalized for COPD by 14-Day Follow-Up Status for Hospital A

Bar chart comparing 30-day total episode payments for 14-day and no 14-day follow-up periods across three categories: Your Hospital (blue), Your Region (gray), and GACH Average (orange). No 14-day follow-up shows higher payments overall.

MVC member hospitals who classify as Critical Access Hospitals (CAHs) received alternate versions of the report, which used the averages of other CAHs as their comparison group in addition to MVC region. Similar to general acute care hospitals, the collaborative observed decreases in average follow-up rates among its CAH members for patients hospitalized for CHF (decrease from 39% to 38.2%), pneumonia (37.4% to 32.5%), and sepsis (44.7% to 43.9%). Among patients hospitalized for COPD at a CAH, however, there was an observed increase in the average 14-day follow-up rate from 44.9% to 47.2%. CAHs also observed similar trends of lower follow-up rates among Medicaid and dual-eligible patients.

Members can similarly benchmark the values and data provided in their recent report pages to the previously distributed follow-up push report from Q1 2025.

In addition to providing data on follow-up care, the MVC Coordinating Center offers a regular post-discharge follow-up workgroup series where members and partners share strategies and insights to help improve follow-up performance. The next workgroup will take place on Thurs., July 23, from 12-1 p.m. More information about upcoming MVC events can be found on the MVC events page.

If you have any suggestions on how these reports can be improved or have additional data requests to help support your quality improvement projects, please reach out to the MVC Coordinating Center.

Off
View Post
September MVC Workgroups Highlight Initiatives for COPD Readmissions, High-Value Care for All

September MVC Workgroups Highlight Initiatives for COPD Readmissions, High-Value Care for All

Since its founding, a core component of MVC’s strategy has been organizing opportunities to collaborate with and learn from peers, leading to the ongoing facilitation of MVC workgroups. MVC has hosted workgroup presentations twice per month in recent years, and this year’s workgroups are focused on six topic areas: post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action. Going forward, MVC will publish a monthly blog to highlight key takeaways and shared resources from the prior month’s presentations. In doing so, all MVC members and partners may utilize and benefit from the content regardless of their live participation.

September Post-Discharge Follow-Up Workgroup

MVC hosted a post-discharge follow-up workgroup on Sept. 10 featuring a presentation by Brian Leideker, RRT, COPD Navigator for Trinity Health Oakland Hospital. Leideker’s presentation summarized Trinity Heath Oakland Hospital’s progress since initiating an A3 COPD readmission committee in June 2021, including the key interventions their team has implemented to date.

One initial intervention was the hiring of a COPD navigator. Leideker described how his unique role as a respiratory therapist involved in case management has allowed him to be “a middleman between respiratory physicians and other entities trying to deliver and support services” for COPD patients.

Following several root cause analyses, the COPD committee identified that nearly 90% of patients readmitted for COPD at Trinity Health Oakland Hospital had an interruption in intended continuation of pharmacotherapy and/or non-pharmacotherapy treatments. This finding encouraged Leideker’s team to work to improve the education of patients, providers, and the greater healthcare community on ambulatory treatment for COPD as well as reviewing the testing and documentation needed to ensure coverage of durable medical equipment (DME) post-discharge.

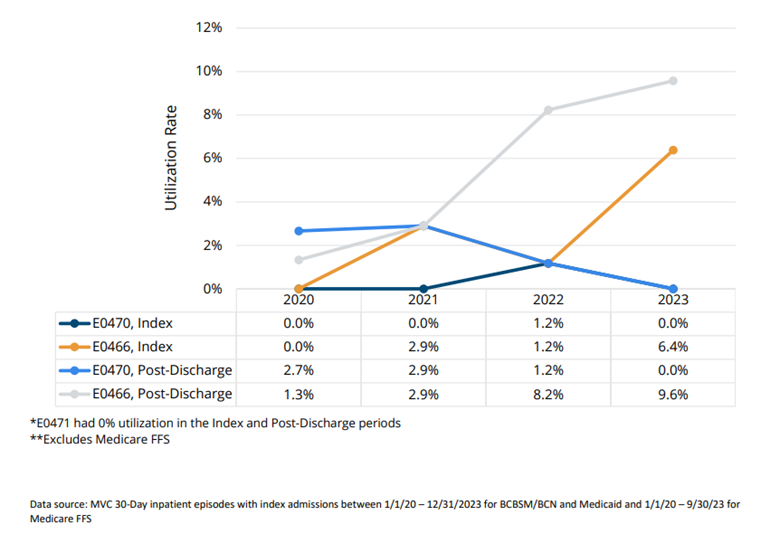
With the help of an MVC custom analytic report, Leideker was able to trend DME utilization rates for patients hospitalized with COPD since the initiation of these interventions, as seen in Figure 1.

Figure 1. Annual Select* DME Utilization Rates During the Index and 30-Day Post-Discharge Period Among Patients Hospitalized for COPD at Trinity Health Oakland (2020-2023)**

Generally, the utilization rate of post-discharge non-bi-level home ventilators (E0466) was found to increase over time, while bi-level home ventilator (E0470) utilization has decreased. Leideker noted that this was somewhat expected since patients routinely report difficulty with the utilization of bi-level home ventilators (BiPAP) and often move on to non-bi-level home ventilators (CPAP). Additionally, based on Trinity Health Oakland’s internal analyses as of May 2024, their COPD three-day readmission rates have been reduced to <18% for all payers.

Sept. 10 Post-Discharge Follow-Up Workgroup

September Rural Health Workgroup

MVC hosted a rural health workgroup on Sept. 26 featuring a presentation by Brent Mikkola, MBA, PMP, Manager of Community Health at MyMichigan Health. Mikkola’s presentation summarized MyMichigan Health’s strategic approach to ensuring high-value care for all and an overview of some specific community programs currently in place. MyMichigan Health’s strategic approach is currently focused on evaluating opportunities to overcome non-medical drivers of health in an “assess, analyze, and address” model.

Some unique community partnerships that resulted from this process include:

  • Gratiot County Public Transit voucher program
  • Rx 4 Health – partnership with Michigan State Extension and specific grocery suppliers including SpartanNash, SaveALot, and Meijer
  • Food Pharmacies & Weekend Kits - partnership with the Greater Lansing Food Bank and the Food Bank of Eastern Michigan
  • Bridge to Belonging - virtual series on loneliness and social connection
  • Continuing Care Clinic Pilot with Community Health Workers (CHWs)
  • Intervention for Nicotine Dependence: Education, Prevention, Tobacco and Health (INDEPTH) Suspension Diversion Program

In addition, Mikkola described how MyMichigan Health delved into the data collection, analysis, and quality improvement work surrounding gaps in healthcare outcomes. For example, after initially integrating CHWs into community practices and inpatient services, MyMichigan Health further integrated CHWs following the WHO’s CHW Lifecycle Approach. CHWs have become instrumental to MyMichigan’s assessment of non-medical drivers of health as required by CMS and JCAHO mandates; they have done so by filling gaps in system workflows and in the expansion of the Continuing Care Clinic Pilot. To date, nearly 500 well visit appointments have been completed by CHWs at MyMichigan. Of those patients, 34% were identified as experiencing gaps in care and 50% of those positive screens have now reportedly been met through connections to community support services.

To learn more about the efforts showcased by Trinity Health Oakland and MyMichigan Health, or to view past workgroup presentations, visit MVC’s YouTube channel here.

October’s workgroups will include a health in action presentation on Oct. 8 about the University of Michigan’s Hospital Care at Home program, as well as a sepsis presentation on Oct. 17 by Garden City Hospital. You can view the complete 2024 calendar of events and register for workgroups here. To learn more about MVC workgroups or other presentation opportunities, contact the MVC Coordinating Center by emailing us here.

Off
View Post
MVC Publishes its 2024 QECP Annual Report as a Qualified Entity

MVC Publishes its 2024 QECP Annual Report as a Qualified Entity

Recently, the MVC Coordinating Center published its annual Qualified Entity Certification Program (QECP) public report for 2024. This report [PDF] was published in a new QECP section on the MVC website’s Data/Registry page and is an annual requirement for MVC as a qualified entity with the Centers for Medicare & Medicaid Services (CMS). This was MVC’s third public QECP report and continued to provide unidentified aggregated data about Michigan hospital performance on two measures: rates of 30-day rehospitalizations following start of home health care, and rates of outpatient follow-up received after hospitalization for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD).

All measures in the report were created using data from MVC claims-based episodes of care initialized by inpatient hospitalizations or surgeries between Jan. 1, 2018 and Dec. 31, 2022. Claims were incorporated from all MVC payer sources, including Medicare Fee-for-Service, Blue Cross Blue Shield of Michigan, Blue Care Network, and Michigan Medicaid.

The reported overall rate of 30-day unplanned rehospitalizations after the start of post-acute home health care among episodes beginning at MVC hospitals in Michigan was 11.6% for 2018-2022. Risk-adjusted rates by index hospital ranged from 2.5% to 17.2%. By home health provider, risk-adjusted rates ranged from 0.0% to 23.5% (Figure 1). Patients whose episode of care began with an index event for endocarditis, COPD, CHF, or percutaneous coronary intervention (PCI) were more likely than patients with other index conditions to experience an unplanned rehospitalization in the 30 days after they started home health care. Patients with a joint replacement episode of care were least likely to have an unplanned rehospitalization following the start of home health care.

Figure 1. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by Home Health Provider

Results for the outpatient follow-up metrics remained similar to findings from previous annual reports. Across episodes of care for index events in 2018-2022 at the 106 MVC hospitals in Michigan, the unadjusted rate of patients receiving outpatient follow-up within 7 days after hospitalization for CHF was 44% (Figure 2). Following index hospitalizations for COPD, 36% of patients received outpatient follow-up within 7 days (Figure 3). For both conditions, there was wide variation across hospitals in Michigan in their 7-day follow-up rates after hospitalization, with rates ranging between less than 10% to over 60%. Rates of follow-up were fairly steady over time.

Figure 2. 7-Day Follow-Up After CHF Hospitalization by MVC Hospital

Figure 3. 7-Day Follow-Up After COPD Hospitalization by MVC Hospital

For more information and the entire set of findings we invite you to read the full 2024 report, available here.

QE certification status allows MVC to provide hospital members with additional data from Medicare Fee-for-Service (FFS) claims at a level of granularity which would not otherwise be available under standard CMS data use agreements. Reports located under the “QE Medicare” icon on the MVC registry allow hospital registry users to see unsuppressed Medicare data including case counts <11 as well as utilization rates and average payments based on case counts <11. In addition, on any QE Medicare registry report, members can click on specific data points to load a list of all episodes underlying that data point. From that episode list it is possible to view drilldown information on individual episodes to learn more about the claims and price-standardized payments comprising that episode.

Members may contact the MVC Coordinating Center by emailing Michigan-Value-Collaborative@med.umich.edu to learn more about data available through MVC’s QECP reports and to receive the forms necessary to gain access on the registry.

Off
View Post
Refreshed Hospital-Level, ED-Based Episode Push Reports Coming Soon to Members

Refreshed Hospital-Level, ED-Based Episode Push Reports Coming Soon to Members

The MVC Coordinating Center will soon distribute refreshed hospital-level versions of its push report utilizing emergency department-based episodes (“ED-based episodes”). MVC generated separate versions for acute care hospitals and Critical Access Hospitals (CAHs) with tailored comparison groups. In addition to reflecting more recent data across all included payers, these refreshed hospital-level reports differ from prior versions due to the addition of three high-volume ED conditions and the incorporation of Michigan Medicaid claims.

Each page of the report is dedicated to a specific condition with the same metrics throughout, such as risk-adjusted, price-standardized 30-day total episode spending, inpatient admission rates, and rates of post-ED utilization. Reports feature each hospital’s own attributed ED-based episode data for eight high-volume ED conditions: abdominal pain, cellulitis, chest pain (nonspecific), congestive heart failure (CHF), chronic obstructive pulmonary disease (COPD), diabetes with long-term complications (including renal, eye, neurological, or circulatory), diabetes with short-term complications (including ketoacidosis, hyperosmolarity, or coma), and urinary tract infection (UTI). The three new conditions included in this year’s refresh include diabetes with long-term complications, diabetes with short-term complications, and UTI.

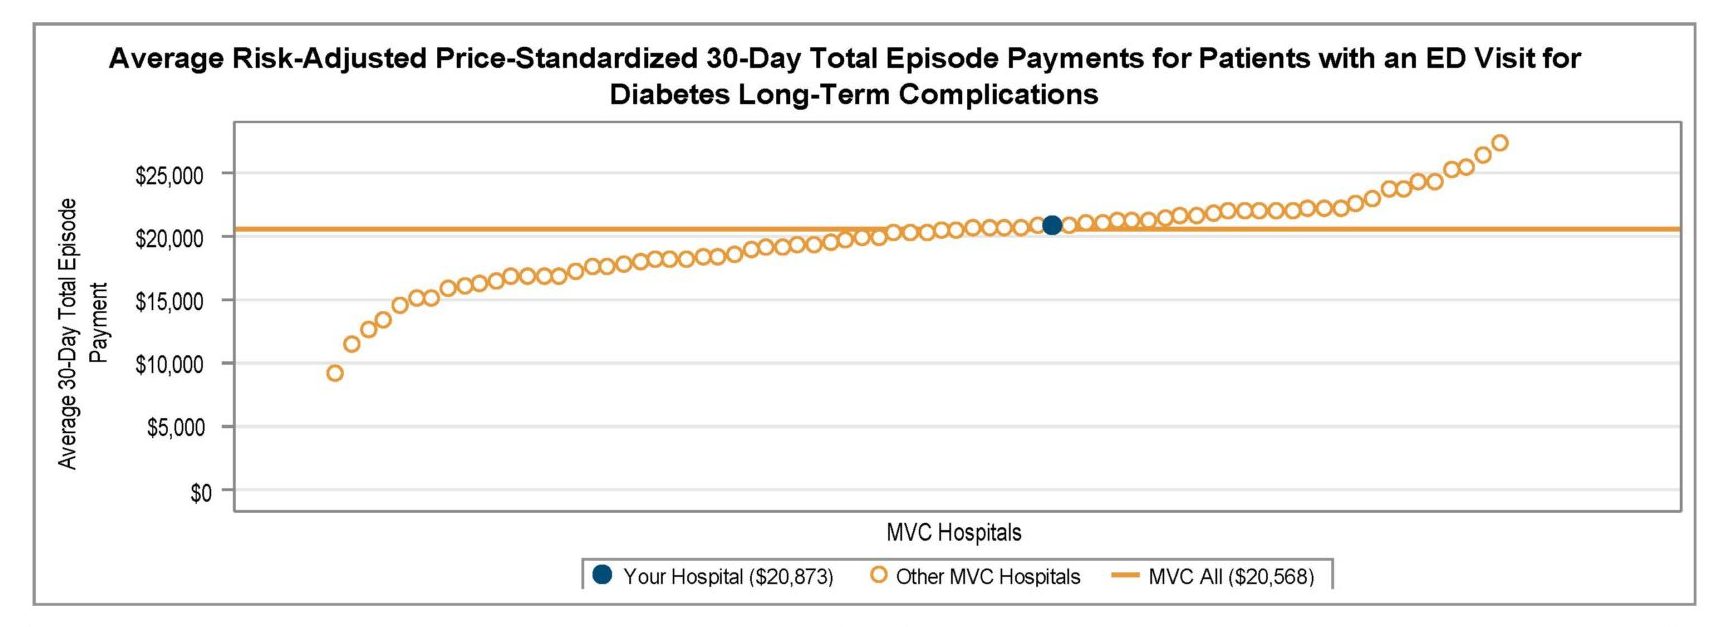
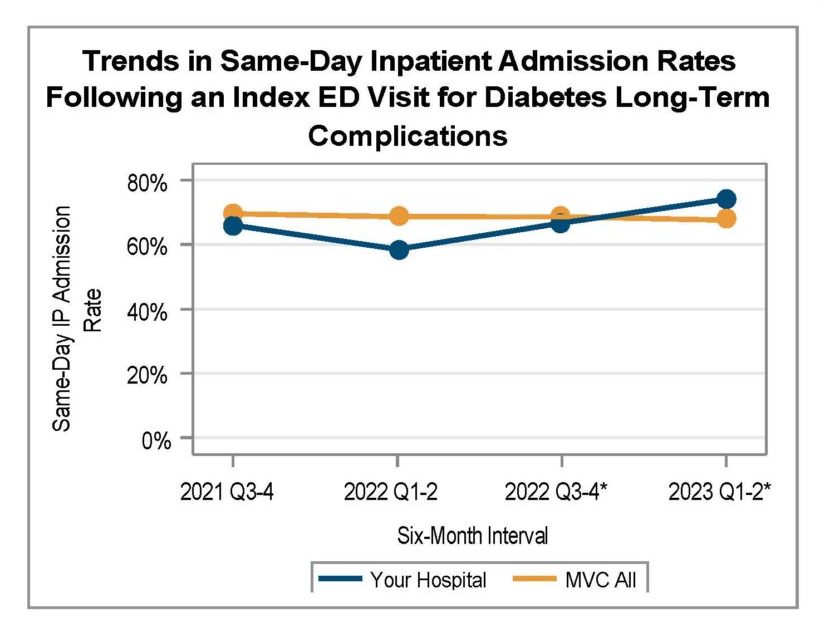
Among general acute care hospitals receiving a report, the average risk-adjusted, price-standardized 30-day total episode payment (Figure 1) for the reported conditions is highest for diabetes with long-term complications ($20,568), CHF ED-based episodes ($17,245), diabetes with short-term complications ($12,087), and COPD ED-based episodes ($10,289). The collaborative-wide average is lowest for chest pain ($3,111) and abdominal pain ($3,123) ED-based episodes. Within each condition, MVC 30-day total episode payments are consistently higher for episodes in which the patient had a same-day inpatient admission compared to episodes in which the patient did not have an inpatient stay beginning on the date of their ED visit. With that information in mind, hospital members can also use their individualized reports to track their same-day inpatient admission rate at six-month intervals using trend graphs for each included ED-based condition (Figure 2).

Figure 1.

Figure 2.

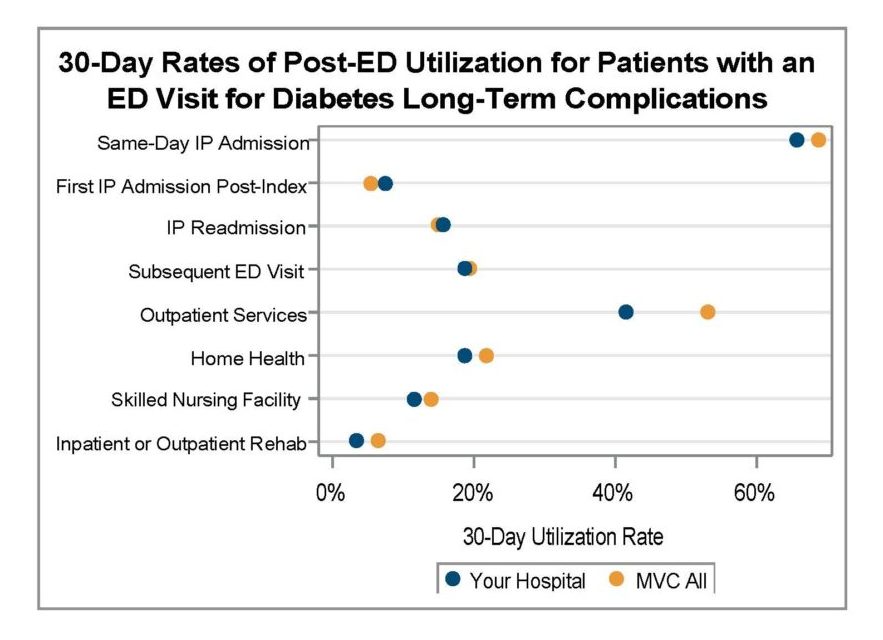
A key goal for these ED-based episode reports is to provide insight into healthcare utilization following index ED visits. Therefore, reports continue to include a dot plot (Figure 3) comparing patient post-ED utilization at a member hospital against their peer comparison group. Dot plots provide information on what percent of episodes had a same-day inpatient admission, what percent did not have a same-day inpatient admission but did see the patient admitted in the 1 to 30 days following the index ED visit, and the percent of patients who had two or more inpatient admissions (thus, at least one readmission) during the episode of care. Also provided are rates of subsequent ED visits, receipt of outpatient services, home health, skilled nursing facility care, and inpatient or outpatient rehab.

Figure 3.

These ED-based episodes are built using MVC’s most recent medical claims data from Medicare FFS, Blue Cross Blue Shield of Michigan PPO Commercial and Medicare Advantage plans, Blue Care Network HMO Commercial and Medicare Advantage plans, and Michigan Medicaid.

ED-based episodes utilize MVC’s newest episode of care data structure, which was developed last year in collaboration with the Michigan Emergency Department Improvement Collaborative (MEDIC), a BCBSM-funded Collaborative Quality Initiative with the goal of improving care and patient outcomes in Michigan emergency departments. MVC and MEDIC team members worked closely to develop 30-day episodes of care initialized by a patient’s visit to the ED and including all claims-documented care received in the 30 days following a patient’s index ED visit.

Please share your feedback with the MVC team if certain report measures are helpful or if you wish to see additional ED-based episode reporting for certain conditions and metrics. MVC is now also accepting custom report requests using its new ED-based data. Contact MVC to learn more.

Off
View Post
MVC’s Refreshed Common Conditions Report Coming to Hospital Members Soon

MVC’s Refreshed Common Conditions Report Coming to Hospital Members Soon

MVC members will receive their next batch of updated push reports in the coming days with a refreshed version of MVC’s common conditions report. These reports provide insight into episodes of care for eight medical and surgical conditions that are commonly a focus for quality improvement efforts at MVC hospitals: acute myocardial infarction (AMI), chronic obstructive pulmonary disease (COPD), colectomy (non-cancer), congestive heart failure (CHF), coronary artery bypass graft (CABG), total knee and hip (joint) replacement, pneumonia, and spine surgery. MVC’s general acute care hospital and Critical Access Hospital (CAH) members will receive tailored versions of the report, with each group receiving benchmark data specific to their own category of hospitals.

Although the metrics provided vary by condition and case count, report pages generally focus on 30-day total episode payments, readmission rates, common reasons for readmissions, and post-acute care utilization. MVC price standardizes total episode payments to Medicare FFS amounts so that comparisons can be made across hospitals and over time. Payments are risk adjusted for patient age, gender, payer, comorbidities, and high or low prior healthcare utilization/payments.

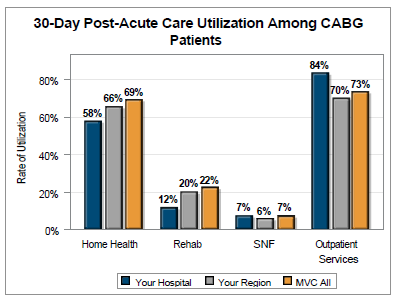
Post-acute care utilization benchmarking for each of the eight medical and surgical conditions includes graphs displaying the percentage of each hospital’s patients who used home health care, inpatient/outpatient rehab, skilled nursing facility care, outpatient services, or emergency department care in the 30 days following their index hospitalization or surgery. Across the collaborative, reports show high use of 30-day home health care and outpatient services for these common conditions. For patients initiating their episode of care at a general acute care hospital within the collaborative, the home health care utilization rate was highest following CABG (69%) and joint replacement (50%).

Patients with a CABG episode were also high utilizers of outpatient services in the 30 days post-index (Figure 1), with a 73% average utilization rate. Patients with episodes for CHF (58%) and AMI (53%) were also high utilizers of outpatient services. Across conditions, use of outpatient services in the 30 days post-index was generally higher among episodes originating at CAHs than among episodes originating at general acute care hospitals.

Figure 1.

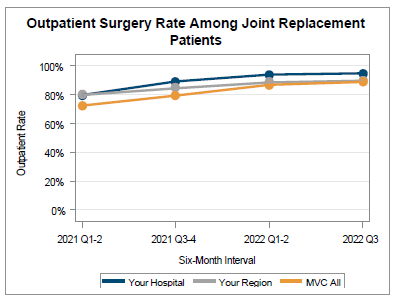
Reports also assess the setting of care for joint replacements and spine surgeries. For total knee and hip replacements, MVC data shows that the percent of joint replacements performed in an outpatient setting at general acute care hospitals across Michigan continued to rise from January 2021 through September 2022 (Figure 2).

Figure 2.

The patient population in these reports comprises adult patients who had surgery or an inpatient hospitalization at an MVC-participating hospital between January 2021 and September 2022. Measures are based on 30-day inpatient and surgical-based episodes of care data, incorporating paid claims from Blue Cross Blue Shield of Michigan and Blue Care Network Commercial and Medicare Advantage plans as well as paid claims from Medicare Fee-for-Service. Episodes meeting any of the following criteria were excluded from calculations: patients transferred to another acute care hospital or to hospice, patients who died during their index stay, and patients with a primary diagnosis of COVID-19 received in an inpatient setting at any point during their 30-day episode.

We hope our collaborative participants find these reports valuable, and as always, we welcome MVC members to contact MVC with any questions or analytic requests.

Off
View Post
MVC’s 2023 Chronic Disease Management Follow-Up Reports Coming to Members Soon

MVC’s 2023 Chronic Disease Management Follow-Up Reports Coming to Members Soon

MVC will soon distribute the 2023 version of its chronic disease management follow-up reports to members. This refreshed version provides summary data on patients eligible for follow-up care after discharge from hospitalizations for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD).

MVC defines timely follow-up care as receipt of an in-person or remote outpatient follow-up visit within 30 days of hospital discharge to home or home health care and before any readmission, emergency department (ED) visit, or procedure. Patients admitted to a skilled nursing facility, long-term acute care hospital, or inpatient rehab within the 30-day episode were excluded. MVC’s follow-up analyses was performed using claims-based episodes of care with index hospital admissions between 7/1/2019 and 06/30/2022 for Blue Cross Blue Shield of Michigan (BCBSM) PPO Commercial and Medicare Advantage (MA), Blue Care Network (BCN) HMO Commercial and MA, and Medicare Fee-for-Service insurance plans. For each of the two chronic conditions included in the report, hospitals with at least 11 episodes per year for a given condition received that condition-specific data.

The report offers a comparison of demographic characteristics for CHF and COPD patients who received a follow-up visit within 30 days versus those who did not receive follow-up. Demographic characteristics tabulated for each condition include the percent of patients living in “at-risk” or “distressed” Zip codes as defined by the Economic Innovation Group’s Distressed Community Index, patients’ average number of comorbidities, the mean age of patients, and the distribution of race and ethnicity. MVC recently refined and expanded its reporting of race and ethnicity identities, and these updates were reflected in the report. Patients are grouped as Hispanic if their insurance provider categorized their combined race/ethnicity as Hispanic or their ethnicity as Hispanic. Additionally, MVC no longer combines smaller groups and discontinued its use of the terms “other” and “unknown.”

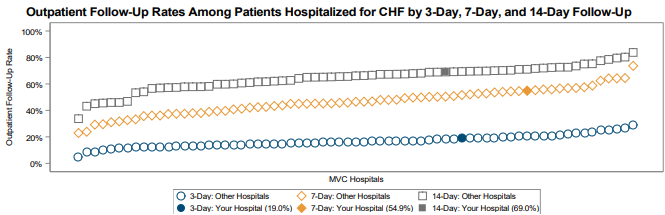
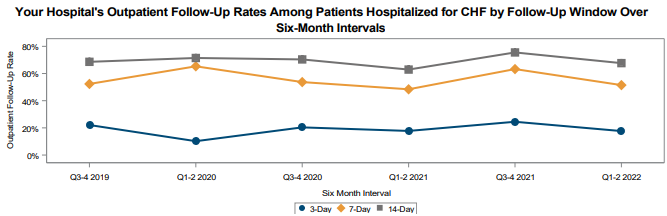
On the first page provided for each condition, hospital follow-up rates are provided for three windows of time compared to those at other MVC hospitals (Figure 1), as well as trends over time for each follow-up window (Figure 2). For CHF, follow-up rates are provided in 3-day, 7-day, and 14-day time windows. For COPD, follow-up rates are provided in 7-, 14-, and 30-day time windows.

Figure 1.

Figure 2.

The second page of condition-specific feedback includes a summary of average 30-day risk-adjusted, price-standardized total episode payments by follow-up status compared to statewide and regional averages. Among general acute care hospitals included in the analysis, the statewide total average payment for CHF episodes was $17,235 for patients who received follow-up and $20,069 for those who did not; for COPD episodes, the statewide average payments were $13,815 among those with follow-up and $16,056 among those without. In reports generated for Critical Access Hospitals (CAHs), payments were compared to averages across all MVC CAH members. Rates of 30-day follow-up were also compared by payers across the same groups.

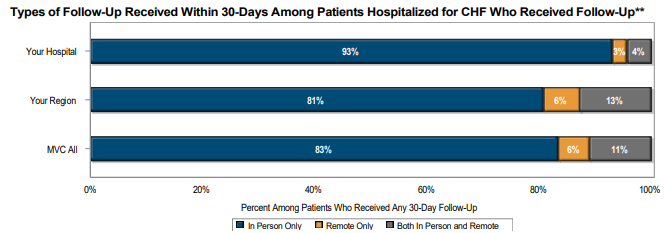
The final figure (Figure 3) in the report for each condition is a summary of follow-up method among those who received any follow-up care. Patients who received follow-up were categorized as having received only in-person follow-up visit(s), only remote follow-up, or both in-person and remote follow-up. MVC found that more than 80% of CHF and COPD patients statewide exclusively received in-person follow-up after a hospitalization.

Figure 3.

If you have any questions or feedback about this report, please contact the MVC Coordinating Center.

Off
View Post
MVC Publishes its 2023 QECP Public Report as a Qualified Entity

MVC Publishes its 2023 QECP Public Report as a Qualified Entity

Today the MVC Coordinating Center published its annual Qualified Entity Certification Program (QECP) public report for 2023. One of the requirements of being a qualified entity (QE) with the Centers for Medicare & Medicaid Services (CMS) through the QECP is the annual dissemination of a public report created using claims data. MVC shared its first public report last year, making the 2023 report the second iteration.

As with last year, the 2023 MVC QECP Public Report provides unidentified aggregated data on Michigan hospitals for two measures: rates of 30-day rehospitalizations following start of home health care, and rates of outpatient follow-up received after hospitalization for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD). Both measures were created using data from episodes of care initialized by inpatient hospitalizations or surgeries between 1/1/2018 and 12/31/2021.

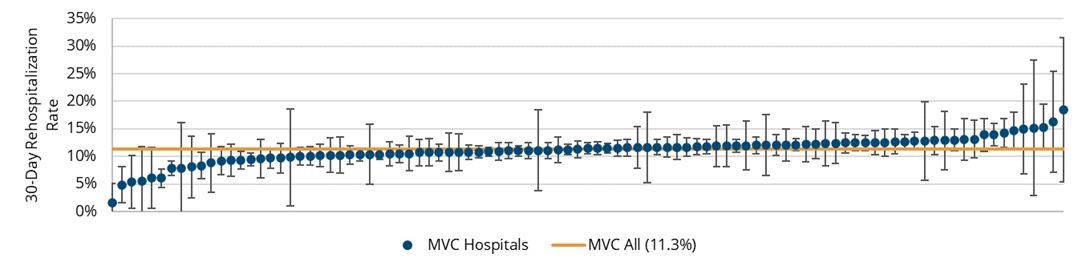
For 2018-2021, the overall rate of 30-day unplanned rehospitalizations from home health among MVC member hospitals in Michigan was 11.3%. Risk-adjusted rates by index hospital ranged from 1.6% to 18.5% (Figure 1). By home health provider, risk-adjusted rates ranged from 2.0% to 23.6%. Patients whose episode of care began with an index event for endocarditis, COPD, CHF, or percutaneous coronary intervention (PCI) were more likely than patients with other index conditions to experience an unplanned rehospitalization in the 30 days after they started home health care.

Figure 1. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by MVC Hospital

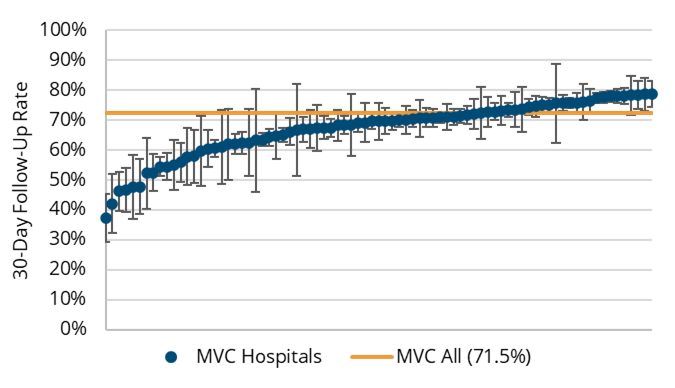
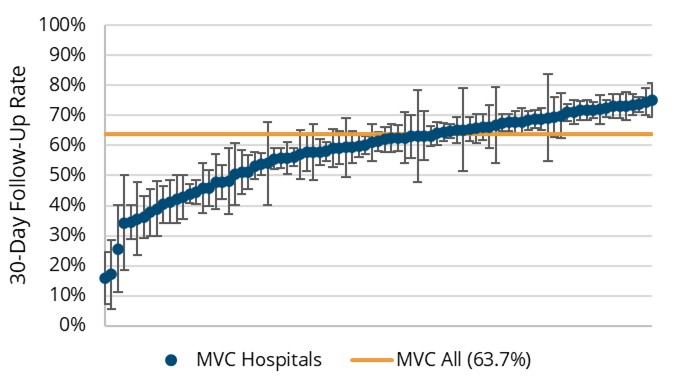
Across the 102 MVC hospitals with attributed episodes of care data underlying this report, the unadjusted rates of patients receiving outpatient follow-up were higher following index hospitalizations for CHF than for COPD (Figures 2 and 3). This was the case whether follow-up occurred three days (16% vs. 13%), seven days (45% vs. 37%), 14 days (63% vs. 54%), or 30 days (72% vs. 64%) after discharge.

Figure 2. 30-Day Follow-Up After CHF by MVC Hospital

Figure 3. 30-Day Follow-Up After COPD by MVC Hospital

For more information and the entire set of findings, we invite you to read the full report, which is available online to any member of the public on the MVC Resources page or directly here.

QE certification status allows MVC to provide hospital members with additional data from Medicare Fee-for-Service (FFS) claims at a level of granularity not otherwise available under standard CMS data use agreements. Reports located under the “QE Data” icon on the MVC registry allow hospital registry users to see unsuppressed data that include case counts <11 as well as utilization rates and average payments based on case counts <11. In addition, on any QE Data registry report, members can click on specific data points to load a list of all episodes underlying that data point. From that episode list, it is possible to view drill-down information on any individual listed episode to learn more about the claims and price-standardized payments comprising that episode.

MVC members representing one or more MVC-participating hospitals can send an email to Michigan-Value-Collaborative@med.umich.edu to learn more about data available through MVC’s QECP reports and to receive the forms necessary to gain access to those registry reports.

Off
View Post
MVC Shares New COPD Report with Physician Organizations

MVC Shares New COPD Report with Physician Organizations

This week the Michigan Value Collaborative (MVC) introduced a new push report for its physician organization (PO) members focused on chronic obstructive pulmonary disease (COPD), providing a tailored version for each of MVC’s 40 PO members. This new push report was created in response to member interest in improving the quality of care for chronic diseases. It utilized 30-day claims-based COPD episodes from Medicare Fee-For-Service, Blue Cross Blue Shield of Michigan (BCBSM) PPO Commercial, and BCBSM Medicare Advantage with index admissions from 1/1/19 to 6/30/21.

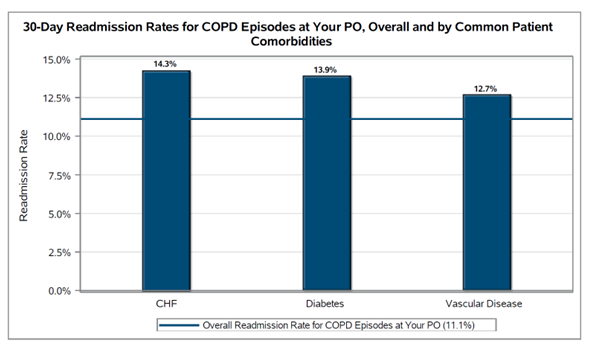
One feature the MVC Coordinating Center is excited to highlight is the inclusion of 30-day readmission rates by major comorbidity categories for COPD. Rates were assessed for a PO’s attributed COPD patients overall as well as for attributed patients with congestive heart failure, diabetes, and vascular disease (see Figure 1). These comorbidities are assessed using diagnosis codes on claims in the six months prior to the patient’s index hospitalization.

Figure 1.

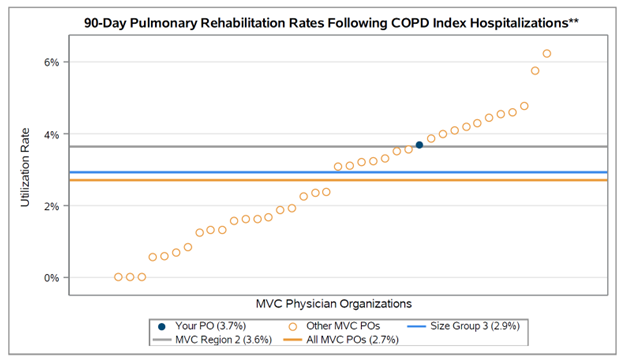
Also featured in this report were 90-day rates of pulmonary rehabilitation utilization following COPD index hospitalizations. This is the first time MVC has included a measure of pulmonary rehabilitation utilization in a collaborative-wide report, and the Coordinating Center hopes that this metric will encourage increased use of this important program across Michigan. Across all COPD episodes in the report, the collaborative-wide rate of pulmonary rehabilitation for PO-attributed patients was 2.7% (see Figure 2).

Figure 2.

Due to the low collaborative-wide rate, the Coordinating Center assessed 90-day utilization of pulmonary rehabilitation rather than 30-day utilization. However, the American Thoracic Society recommends the initialization of pulmonary rehabilitation within three weeks following hospitalization. Click here to learn more about American Thoracic Society recommendations for pulmonary rehabilitation and other care following COPD hospitalization.

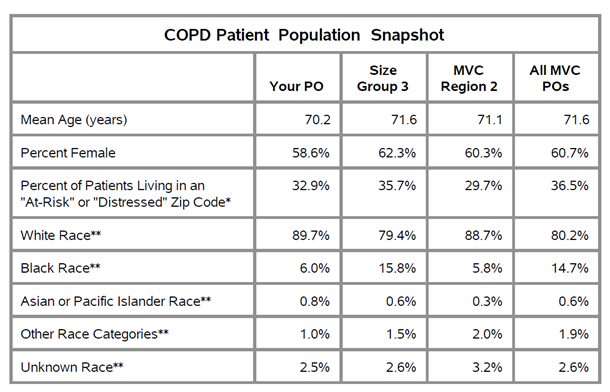
Each PO’s complete report also includes figures illustrating average price-standardized risk-adjusted 30-day total episode payments, average index hospitalization length of stay, trends in readmission rates, rates and payments of post-acute care utilization, rates of outpatient follow-up, and patient population demographics. A patient population snapshot table details several demographic variables, including a variable based on data from the Economic Innovation Group’s Distressed Communities Index (DCI). It identifies the proportion of patients living in an “at-risk” or “distressed” zip code across all payers (see Figure 3). The DCI is derived from the U.S. Census Bureau’s Business Patterns and American Community Survey.

Figure 3.

A second table provides information on index hospital locations of care for the PO’s attributed patients, comparing the percent of patients treated at each site as well as each index hospital’s average 30-day total episode payment.

The COPD PO report is also being shared with members of the newly established lung care Collaborative Quality Initiative, commonly referred to as INHALE (Inspiring Health Advances in Lung Care). INHALE focuses on patients with asthma and COPD. They disseminate strategies to improve outcomes in these patient populations and reduce the costs associated with asthma/COPD care.

MVC also partnered with a fellow Collaborative Quality Initiative to provide POs with a provider resource that may be relevant to their work with COPD patients. The Healthy Behavior Optimization for Michigan (HBOM) team provided its Quit Smoking Resource Guide to send alongside MVC’s report. HBOM aims to ensure that all smokers who are interested in quitting receive the support and resources they need to be successful. Read more about HBOM’s materials and efforts on the HBOM website or in MVC’s May spotlight blog.

If you have any suggestions on how these reports can be improved or the data made more actionable, the Coordinating Center would love to hear from you. MVC is also seeking feedback on how collaborative members are using this information in their quality improvement projects. Please reach out at Michigan-Value-Collaborative@med.umich.edu.