
Off
View Post
MVC August Workgroups Highlight Preop Testing Reduction with RITE-Size and QI to Improve Outcomes for ICH Stroke Patients

MVC August Workgroups Highlight Preop Testing Reduction with RITE-Size and QI to Improve Outcomes for ICH Stroke Patients

In August, the Michigan Value Collaborative (MVC) hosted two virtual workgroup presentations, a preoperative testing workgroup focused on Henry Ford Health Genesys’ preoperative testing reduction initiative and a health in action workgroup presentation by DMC Detroit Receiving Hospital on their intracranial hemorrhage quality initiative. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action.

Preoperative Testing Workgroup: Henry Ford Health Genesys

During this month's preoperative testing workgroup, Henry Ford Health’s (HFH) Brooke Wagner, RN, BSN, Clinical Quality Facilitator II, SCQR, and Megan Wadowski, RN, BSN, Principal Quality Consultant, shared how HFH Genesys achieved significant improvement in reducing unnecessary preoperative testing prior to low-risk surgical procedures (e.g., inguinal hernia, lumpectomy, and cholecystectomy) by participating in the RITE-Size initiative.

HFH Genesys became involved in RITE-Size following outreach from the Michigan Surgical Quality Collaborative (MSQC), who indicated the HFH Genesys was eligible to participate in the RITE-Size initiative. HFH Genesys saw this as an opportunity for improvement and met with the RITE-size team for an initial site visit and kick-off meeting.

RITE-Size Coaching & Implementation Strategies

After initial discussions, the RITE-size and HFH Genesys teams identified two areas for improvement: 1) ordering practices and 2) provider workflows. The desired outcome/goal was to reduce unnecessary preoperative testing to better align with evidence-based (EBP) system-wide practices at HFH.

Wagner shared that HFH Genesys was able to pull together a multi-disciplinary team to meet with the RITE-size team, including clinical quality staff, the surgeon champion, chief of staff, and nurse manager for preadmission testing. Their team met and reviewed organizational data and workflows, discussed barriers, and considered ideas for long-term sustainability. By sharing perspectives from providers, nursing, anesthesia, and leadership, they were able to develop action plans and strategies to support continued improvement.

As the HFH Genesys team participated in regular coaching sessions throughout the project with the RITE-size team, they were able to increase awareness and give team members the opportunity to ask questions. Throughout the project, they were able to track fallouts, review trends, and maintain continuous process improvement.

Leveraging MVC Data

Part of the process of educating and increasing awareness among team members included sharing data from a MVC custom report completed earlier this year on HFH Genesys’ historical preoperative testing rates from 2023 – 2025 (partial data). Through this report, they discovered that despite changing from open surgery to robotic hernia surgery in early 2024, historical preoperative testing practices persisted (Figure 1). The team was able to develop an action plan and education for surgical providers where they presented evidence-based best practices for preoperative testing in relation to robotic hernia repairs and quickly saw a reduction in testing rates by the second half of the year.

Figure 1. Preoperative Testing Rates for Outpatient Laparoscopic Cholecystectomy, Inguinal Hernia Repair, and Lumpectomy in the 30 Days Prior to Admission at Henry Ford Genesys, 2023-2025 by Half-Year, All Payers
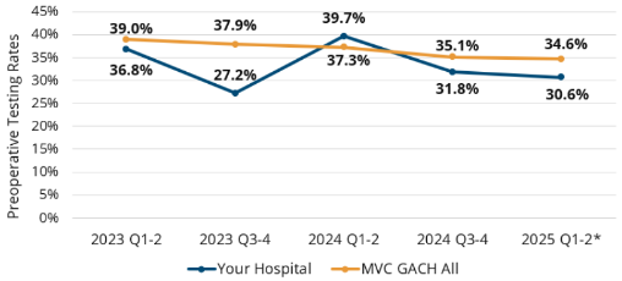
Line chart compares preoperative testing rates for Your Hospital and MVC GACH All across 2023 Q1–2 through 2025 Q1–2*. Blue hospital rates fluctuate from 36.8% to 30.6%, peaking at 39.7% in 2024 Q1–2, while orange comparison rates steadily decline from 39.0% to 34.6%.

*Reflects BCBSM/BCN claims through June 30, 2025, and Medicare FFS through March 31, 2025. Michigan Medicaid was provided through Dec. 31, 2024.

In addition to the clinical metrics HFH Genesys utilized, the custom report MVC provided included data for non-medical drivers of health that gave greater insight into their patient populations being treated for these low-risk procedures. Data tables helped HFH Genesys identify a large portion of patients undergoing low-risk hernia repair as patients living in zip codes with multiple barriers to care.

Identifying these barriers allowed HFH Genesys to restructure and simplify discharge instructions to better meet the needs of the patient population by incorporating patient-centered language and clear guidance on setting up follow-up appointments.

Process Change Efforts

By reviewing MVC and MSQC data together, HFH Genesys was able to identify multiple opportunities for improvement. After evaluating existing preoperative testing order sets, they found the original set was outdated and no longer aligned with evidence-based practice recommendations. By updating the electronic medical record (EMR) system, HFH Genesys was able to make a comprehensive update to the order set and preoperative testing policy for their teams.

This updated policy was then implemented across the organization and shared through trainings for providers and associated staff on appropriate testing guidelines and the revised preoperative testing workflows. To maintain continuous improvement through this process, the HFH Genesys team also established ongoing communication with surgical teams to reinforce adherence to the updated processes, which included orientations for new nursing or physician staff. Sharing the policy during the orientation allowed new staff to ask questions, and for the site to provide in-depth explanations on the effectiveness of the preoperative testing policy.

Barriers, Opportunities, and Next Steps

Wagner shared that though they have accomplished improvements in their preoperative testing process, there are barriers the organization continues to experience that may impact 100% adherence to the new policy. Those barriers range from unpredictable staffing fluctuations, administrative associate turnover, and variability in practice patterns among providers.

Despite ongoing setbacks, HFH Genesys looks forward to the future and opportunities ahead. By implementing Epic EMR in November of this year, they will provide enhanced clinical decision support for staff with the updated preoperative testing process coded into the EMR while creating standardized order sets for providers to easily use. These updates will further support adherence to the policy and provide a strong foundation for continued improvement. HFH Genesys will continue to provide communication and collaboration opportunities with providers and leadership on the “why” of the preoperative testing process change. This will be supported by ongoing monitoring and feedback processes to ensure sustained improvement through the Epic EMR implementation in November.

MVC Preoperative Testing Workgroup: Aug. 11, 2026

Health in Action Workgroup: DMC Detroit Receiving Hospital

During the August health in action workgroup, DMC Detroit Receiving Hospital’s Maryam Hakemi-King, MSN, AGNP, Stroke Program Lead Nurse Practitioner, presented on DMC Detroit Receiving Hospital’s participation in the American Heart Association’s (AHA) Intracranial Hemorrhage (ICH) Initiative, which focuses on advancing care and improving outcomes for patients with ICH.

ICH Stroke Facts & AHA ICH Initiative

Hakemi-King led the presentation by defining essential facts about hemorrhagic strokes to lay a foundation for the “why” of DMC Detroit Receiving’s participation, including:

  1. Hemorrhagic strokes account for approximately 13% of all strokes; but despite being less common, they are responsible for more than 40% of stroke-related deaths
  2. ICH is associated with a high early mortality rate of 30 – 40%
  3. Recent studies have shown a nationwide increase in ICH incidence among young and middle-aged adults
  4. There has been significant improvement in the care of ischemic stroke over the years, but similar progress has not been seen in the care of ICH patients.

As a result, AHA is actively partnering with 15 sites across the nation to participate in a two-year initiative to improve care and outcomes for ICH patients. The chosen sites are led by physician champions of the initiative and are focused on implementing national models of effective ICH care, including using procedures such as minimally invasive parafascicular surgery (MIPS) and aligning with ICH metrics and measures through AHA’s stroke focused Get with the Guidelines (GWTG) program. DMC teams are working to identify successful models of care through process mapping activities and continuously evaluating ongoing quality improvement initiatives. Participating sites like DMC are focusing on areas such as:

  • ICH patient triage process
  • Patient selection criteria for MIPS procedure
  • Surgical timing and post-operative care
  • Staff training and education
  • Evaluating outcomes

Sites discuss and review strengths and barriers to care while investigating all opportunities within each of these domains.

DMC Detroit Receiving Hospital Stroke Program

DMC Detroit Receiving Hospital has a comprehensive stroke center and program, which has seen a 43% increase in ICH admission cases from 2023 to 2025. The stroke center offers comprehensive, around-the-clock care supported by neurointensivists, specially trained neurosurgeons, and close collaboration with the ED, neurology, Neuro ICU, and neurosurgery teams. Its coordinated approach includes a dedicated stroke activation and paging system, a designated PACU holding area, 24/7 minimally invasive brain interventions for eligible patients, and AI-assisted identification of intracerebral hemorrhage (ICH). Structured documentation, quality audits, and monthly case reviews further support continuous improvement and high-quality patient care.

DMC Detroit Receiving worked to integrate the ICH methodology into their program by implementing specific metrics and measures, conducting a more in-depth analysis of patients receiving surgical intervention and their level of functioning at discharge, development of specific ICH consult note documentation and code ICH activation process, and continuing research while developing a new framework for ICH management (Figure 2).

Figure 2. DMC Detroit Receiving Hospital’s Integration of the ICH Initiative into Clinical Practice
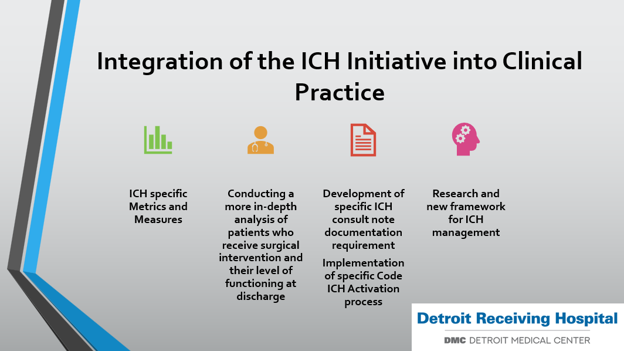
Infographic outlines integration of ICH Initiative into clinical practice at Detroit Receiving Hospital. Four color-coded stages cover ICH-specific metrics and measures, more in-depth patient analysis, documentation and implementation of specific Code ICH Activation process, and research for new framework for ICH management.

ICH Initiative

Hakemi-King expressed how incorporating the AHA ICH initiative’s metrics and measures are an important focus for DMC Detroit Receiving. As they work to align with the national initiative, several ICH metrics and measures are being tracked, such as timing of patients being taken from arrival to the ED to imaging, taking the patient’s blood pressure in less than 120 minutes of arrival at the ED, and ensuring the ICH severity score is completed less than 6 hours before an intervention (Figure 3).

Figure 3. ICH Metrics and Measures
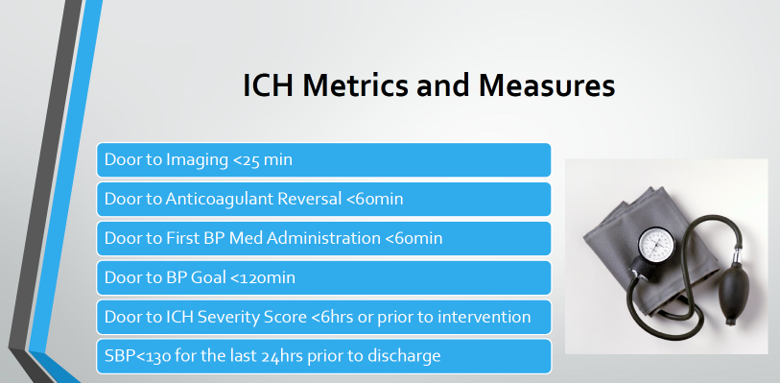
Slide showing ICH Metrics and Measures: door to Imaging in less than 25 minutes, door to anticoagulant reversal in less than 60 minutes, door to first blood pressure medication administration in less than 60 minutes, door to blood pressure goal less than 120 minutes, door to ICH severity score less than 6 hours or prior to intervention

These established care timeframes help ensure patients receive appropriate care on time. By structuring the patient’s care pathway from imaging to medication administration and blood pressure management, the stroke team prepares the patient to have a more successful discharge process.

The ICH quality initiatives currently in progress include tracking patient door to neuro intensive care unit (NICU) bed timing; tracking and identifying ICH presenting symptoms, which can be different than typical stroke symptoms; introducing early physical, occupational, and speech therapy interventions within the first 24 hours of admission (patient progress reported at monthly meeting); and completing a Pre-Morbid Modified Rankin Score (mRS) on patients at admission, discharge, and 90-days post-admission.

DMC Detroit Receiving Hospital is also in the process of implementing their Code ICH protocol. Code ICH is like other traditional Code Stroke processes but is specifically developed to focus on ICH patient care and is activated upon positive identification of a brain bleed on imaging. According to Hakemi-King, the introduction of the new protocol at their site has so far seen an increased rate of identification of ICH patients upon admission, a significant reduction in time from door to NICU bed, and improvement in care coordination and efficiency for these patients. Hakemi-King also shared that their site has just submitted their abstract on this research project to AHA for the 2027 International Stroke Conference and will be able to highlight more specific outcomes once the research timeframe has concluded.

Next Steps

Overall, Hakemi-King said the initiative is strengthening care for patients at Detroit Receiving with intracerebral hemorrhage (ICH) across the continuum—from improving ED workflows through Code ICH to conducting 90-day follow-up calls that assess functional outcomes and recovery interventions. The program focuses specifically on patients presenting through the ED, with strong frontline engagement supported by hands-on leadership, staff education, and regular review of performance gaps. Although exact patient volumes are not yet available, recent data suggest a relatively young population with a roughly even male-to-female distribution. For smaller hospitals preparing patients for transfer to a comprehensive stroke program, Hakemi-King emphasized two critical priorities: promptly managing systolic blood pressure to the recommended range and, when possible, initiating anticoagulant reversal before transfer.

MVC Health in Action Workgroup: Aug. 27, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to the Coordinating Center by email if you are interested in being a workgroup presenter or submit a presentation proposal here.

0
View Post
MVC July Workgroups Highlight Sepsis Discharge Planning in CAHs and MVC’s Follow-Up Push Report

MVC July Workgroups Highlight Sepsis Discharge Planning in CAHs and MVC’s Follow-Up Push Report

In July, the Michigan Value Collaborative (MVC) hosted two virtual workgroup presentations. The first, a rural health workgroup focused on MyMichigan Health’s system-wide sepsis discharge planning follow-up initiative implementation at critical access hospital (CAH) sites. The second, a post-discharge follow-up workgroup, provided a walk-through of MVC’s recent Follow-Up push report including recommendations on practical applications of the report to identify opportunities for improvement. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action.

Rural Health Workgroup: MyMichigan

During MVC’s first workgroup of July, Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Based Care for MyMichigan Health System, shared how their health system developed and implemented a standardized post-discharge follow-up process for patients hospitalized for sepsis. Recognizing the lasting physical and cognitive effects many sepsis patients experience after discharge, Pins-Schallip explained how this initiative was designed to target care transitions, reinforce discharge education, and connect patients with appropriate follow-up care across all MyMichigan Health hospitals. Pins-Schallip also explained how this initiative aimed to drive at both MVC and Michigan Hospital Medicine Safety Consortium (HMS) goals and found ways to benefit sites within the system not engaged with these CQI incentive programs.

Rather than developing separate workflows at each hospital, MyMichigan Health pursued a standardized, system-wide approach. This allowed hospitals of varying sizes, including rural and critical access facilities, to implement consistent practices while also leveraging shared resources. The first step of the initiative was identifying a reliable phone number to provide on discharge paperwork that would connect patients to “on call” Hospitalist providers. By utilizing the health system’s existing 24/7 Transfer Center phone number and nurses already staffing this communication center hub, this minimized the need for additional personnel while also providing patients with a reliable point of contact after leaving the hospital.

Figure 1. Process for 24/7 Transfer Center Calls

A text-based process list outlining steps for patient follow-up after sepsis diagnosis, including discharge, post-discharge questions, 24/7 bed placement call, messaging to hospitalist, and hospitalist follow-up. The list is presented with a MyMichigan Health University of Michigan Health footer in blue and yellow colors.

Pins-Schallip reviewed a selection of sepsis patient calls to the Transfer Center noting that the volume of calls since initiation of the program have been fewer than five. However, the time between a patient calling and resolution of their question is estimated to be on average less than one hour. To date, patient concerns primarily revolve around antibiotic prescription questions.

Throughout implementation, Pins-Schallip noted that the team emphasized collaboration across departments, including hospitalists, nursing, care management, information technology, and executive leadership. Strong physician engagement and support from MyMichigan’s chief medical officer were instrumental in successfully implementing standardized workflows across the health system. With a relatively recent “go live” for this program of July 2026, Pins-Schallip explained that regular feedback gathered from frontline staff and patient data will allow the team to continue to refine the process over time and adapt workflows based on operational experiences.

During the discussion portion of the workgroup, participants enquired about adapting the workflow for other patient populations, implementation at smaller or independent hospitals, and strategies for gaining physician buy-in. Pins-Schallip encouraged organizations to begin with existing resources whenever possible, noting that many hospitals already have personnel or infrastructure that can be leveraged for post-discharge outreach. The importance of executive sponsorship and continuous evaluation were also identified as key strategies to ensure new workflows remain sustainable and effective.

MVC Rural Health Workgroup: July 14, 2026

Post-Discharge Follow-Up Workgroup: MVC Coordinating Center

The second workgroup in July featured a walkthrough of MVC’s new Follow-Up push report, presented by Janet Zhang, MPH, MVC Data Analyst, and Rachel Folk, MHA, MVC Site Engagement Coordinator. Developed to support hospitals interested in further understanding opportunities for improvement, the report provides hospital- and system-level insights into post-discharge follow-up patterns for patients hospitalized with congestive heart failure (CHF), chronic obstructive pulmonary disease (COPD), pneumonia, and sepsis. The report evaluates patterns of follow-up completed within three, seven, and 14-days after discharge using claims data from Blue Cross Blue Shield of Michigan and the Centers for Medicare & Medicaid Services.

Figure 2. MVC Follow-Up Push Report Details

Report details slide presents data parameters for a 30-day inpatient episode analysis covering four MVC conditions: CHF, COPD, Pneumonia, and Sepsis, with payer data date ranges for BCBSM PPO, MA, BCN HMO, BCN HMO MA, Medicare FFS, and Medicaid. Outcome measures include follow-up rates at 3, 7, and 14 days post-index, excluding visits after readmission, inpatient procedures, emergency visits, skilled nursing admissions, or inpatient rehabilitation..

To begin, Zhang reviewed the design of the report outlining how hospitals can use the system-level report to identify variation in follow-up performance across hospitals within the same system. At the system level this report can help leaders recognize opportunities to share successful practices across sites. At the hospital level, the report provides additional context through patient demographic information, non-medical drivers of health, and analyses stratified by payer and follow-up status. Together, these visualizations help members identify where opportunities to optimize follow-up may exist and prioritize improvement efforts.

Next, using a blinded sample report, Folk demonstrated how members can translate their own report findings into actionable quality improvement opportunities. Using the sample blinded report as a template, the remainder of the presentation guided participants through the next steps to finding actionable insights including the identification of areas of opportunity. In this particular report, Folk identified the following areas of opportunity:

  1. Sepsis has the lowest overall follow-up rates at three, seven and 14-days after discharge.
  2. All conditions show lower rates of seven and 14-day follow-up for Medicaid FFS and Dual Eligible payers.
  3. COPD and sepsis patients that attend follow-up within 14-days after discharge have lower 30-day risk-adjusted, price-standardized total episode payments.

As a next step, Folk walked participants through samples of related goal setting and suggested action items for two priority metrics: COPD 7-day follow-up and sepsis 14-day follow-up.

Between COPD and sepsis, the evidence-based action items reviewed included:

  • Schedule follow-up appointments before discharge
  • Confirm medication and follow-up provider access prior to discharge
  • Referral placement for smoking cessation and rehab as indicated
  • Document and review medical care action plans
  • Connect high-risk patients to care management follow-up
  • Flag patients discharged to home without home health as high priority

As part of an interactive discussion, participants were asked to vote on the follow-up intervention they’d most likely implement to drive further discussion.

Figure 3. Screenshot of Follow-Up Intervention Interactive Discussion

Diagram of five color-coded sticky notes outlining steps to improve post-discharge patient care, including scheduling follow-ups, outreach workflows, discharge planning barriers, clinic coordination, and data analysis. Each note features check marks and symbols in various colors, highlighting high interest and key focus areas for high-risk patients and priority conditions.

Throughout the discussion, participants shared experiences and challenges related to improving post-discharge follow-up within their organizations. While several members identified building structured outreach workflows for high-risk patients and scheduling follow-up appointments before discharge as high-priority areas, others discussed practical barriers to these interventions including coordinating care with independent primary care practices, transportation challenges, and difficulty reaching patients by telephone after discharge. Participants also exchanged ideas such as utilizing nurses on light duty to conduct follow-up calls, incorporating virtual and remote monitoring for rural populations, and partnering with home health agencies to reinforce patient education.

The discussion also highlighted opportunities to maximize the value of MVC reports by combining claims data-based insights with internal quality dashboards and other collaborative initiatives. Members expressed continued interest in additional education on integrating MVC reports with other quality improvement efforts and using benchmarking data to communicate opportunities and progress with organizational leadership.

MVC Post-Discharge Follow-Up Workgroup: July 23, 2026

For MVC members seeking additional support related to claims data, please reach out to us by email. MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. If you are interested in being a workgroup presenter please submit a presentation proposal here.

Off
View Post
MVC June Workgroups Highlight Cardiac Rehab Telehealth & Using AI for Physician Feedback and QI in the ED

MVC June Workgroups Highlight Cardiac Rehab Telehealth & Using AI for Physician Feedback and QI in the ED

In June, the Michigan Value Collaborative (MVC) hosted two virtual workgroup presentations. The first was a cardiac rehabilitation (CR) workgroup that doubled as a Michigan Cardiac Rehab network (MiCR) telehealth forum focused on virtual group CR programming with a live action demonstration. The second workgroup, health in action, focused on how artificial intelligence (AI) can be utilized to improve follow-up care for patients. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including CR, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action.

Cardiac Rehab – MiCR Telehealth Forum

MVC and the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2) co-lead MiCR, an initiative to improve CR utilization across Michigan. In April, MiCR launched a new virtual forum series to help programs implement and sustain telehealth services under recently extended Medicare reimbursement policies. MVC’s June workgroup hosted the second MiCR telehealth forum in the series, this time featuring a demonstration of group virtual CR by Henry Ford Health’s Steven Keteyian, PhD, Director of Cardiac Rehabilitation & Preventive Cardiology, and Robert Berry, MS, ACSM-CEP FAACVPR, Clinical Coordinator for Cardiac Rehabilitation. The demonstration was followed by a discussion led by MiCR’s Co-Directors, Jessica Golbus, MD, MS, and Mike Thompson, PhD, MPH.

Telehealth Group Example

The workgroup began with a live mock CR telehealth session led by Berry and Keteyian. Three actors representing patients (played by MVC’s Jessie Souva, MSN, RN, C-ONQS; Emily Woltmann, PhD, MSW; and Rachel Folk, MHA) were guided through a simulated telehealth group CR session.

After presenter introductions, Berry began the group CR class greeting the patient actors, who each represented a specific patient profile and common cardiac condition (Figure 1).

Figure 1. Patient Profiles for Cardiac Rehabilitation Mock Session

Illustration featuring three female characters representing patients with heart conditions, each accompanied by brief medical histories and personal details. Key information includes ages, specific diagnoses like myocardial infarction, coronary artery bypass surgery, and chronic heart failure, along with lifestyle notes and emotional states, presented with distinct colors and icons for clarity.

To begin the session, Berry checked in with each patient on the Zoom session to document the type of exercise or equipment they would be using. As Figure 2 shows, the group session looked similar to a Zoom meeting with all patients exercising simultaneously from locations they established with their instructor in advance. Each patient confirmed their exercise modality, weight, and heart rate as they engaged in their chosen activity. Throughout the exercise process, patients were asked questions about how the exercise was feeling and whether it was causing any pain or discomfort. If a patient was having symptoms, Berry would follow up with more specific questions to help pinpoint the problem area and would give advice for either modifying the exercise, utilizing intentional breathing techniques, or taking a break.

Figure 2. Screenshot of Mock Telehealth CR Session

Screen capture showing what a virtual cardiac rehabilitation group session looks like. Shows three female participants and one clinical professional.

The patients had an opportunity to ask Berry follow-up questions before the end of the session such as:

  1. How will I know when it’s safe to push harder?
  2. Should I continue with CR exercises if my energy level is low today?
  3. When/how do I share my tracked vitals and symptoms with my providers?
  4. How do I get in touch with you between sessions?
  5. Can I still participate in virtual sessions if I’m at my home in Florida?

Following the live demonstration, Golbus and Thompson led participants in a question-and-answer discussion that further clarified how virtual and telehealth CR programs can work. Keteyian and Berry shared that patients must be at their home address for certain payers (Medicare/Medicaid), but patients with other insurance such as Blue Cross Blue Shield of Michigan (BCBSM) can be at any location within the state of Michigan.

Some attendees wondered about confidentiality considerations during the group session. Henry Ford Health said their programming has not required participants to sign an additional Health Information Portability Insurance Portability and Accountability Act (HIPAA) release form; however, they do remind patients to be aware of what information they share in the presence of others during the group session. For people who may be uncomfortable sharing personal information such as weight, different wording can be used. For example, “has your weight changed since your last visit?”

For patients who are unsure about participating in a virtual setting, Keteyian pointed out that they often have the patient come into the facility for the first session to participate as if they were at home in a virtual environment. This often alleviates any concerns about fully participating in a telehealth setting in the future. For those patients who do not have exercise equipment at home, Berry shared that patients can usually find some form of exercise equipment to borrow from a family member, church, or neighbor, or will choose to walk during their session.

A poll of participants showed the current state of CR programming for sites represented at the forum (Figure 3-4), with most sites indicating an interest in exploring both group and individual telehealth CR.

Figure 3. Polling Question: What format of virtual CR is your site considering?

Polling bar chart showing frequency of four formats of virtual cardiac rehab being utilized: Both, Group, Individual, and Neither. Both has highest value near 19, followed by Neither at 13, Group at 8, and Individual at 7, with vertical axis ranging from 0 to 20.

Figure 4. Polling Question: What best describes your site's status on starting a virtual CR program?

Pie chart displays stages of virtual cardiac rehabilitation (CR) implementation among organizations. Largest segment (21) represents organizations considering virtual CR, followed by 12 having conversations with staff or leadership, and smaller segments of 3 each for program development and piloting or delivering virtual CR, with color-coded legend for clarity.

According to the polls, most workgroup participants are still considering CR program development and starting to have conversations with staff and leadership. The MiCR team encouraged participants to take these poll questions back to their teams and leadership to inspire discussion on developing a hybrid or telehealth CR program.

MiCR Telehealth Virtual Forum: June 9, 2026

Health in Action Workgroup – Michigan Medicine

MVC was joined by the University of Michigan’s Alexander Janke, MD, MHS, MSc, Assistant Professor of Emergency Medicine, and Florian Schmitzberger, MD, MS, Clinical Assistant Professor of Emergency Medicine, for the health in action workgroup. Their presentation focused on how AI can be used for clinical feedback and quality improvement workflows in various healthcare settings.

Janke shared that emergency clinicians often make high-stakes clinical decisions when treating patients but then have limited feedback on how their patients do as they move through their care pathway. The rapid patient traffic through the emergency department (ED) continuously pulls these providers into new patient cases, preventing them from having the time to manually review past patient charts. A feedback loop project was intended to help address practice variation, missed learning opportunities, and potential quality blind spots. In preparation for the launch of the project, Michigan Medicine sought approval from the institutional review board (IRB), utilized a large language model (LLM) that is HIPAA compliant, and completed a health information technology services review. They also gathered clinical intelligence committee input, Epic database integration support, and input from the division of clinical informatics.

Methods

Previous approaches to reviewing patient progress included manual chart reviews (time consuming), self-imposed reminders via Epic’s in-basket messaging system, or by hearing about a patient’s follow-up by word-of-mouth. With the introduction of AI as a feedback tool, clinicians would have access to LLMs that can read charts faster than a human reviewer, create tailored summaries for the emergency medicine context, and provide another means for learning by supporting clinicians within their limited time. The AI feedback process follows this flow:

  1. Flag the case – A clinician marks a patient of interest during the shift via a health education research (HER)-integrated workflow
  2. Wait – A specified time later—three to 14 days—the platform queries downstream documentation
  3. AI summary – The University of Michigan generative pre-trained transformer (GPT) Toolkit (HIPAA-compliant LLM) generates a tailored clinical summary with a structured prompt
  4. Deliver – An email arrives in the clinician’s institutional inbox and includes a patient identifier for recall, an emergency medicine-focused summary, and answers to any free-text questions
  5. Reflect – The clinician reviews, learns from the outcome, and adjusts future practice enabling the adaptive learning cycle

The process begins with the provider flagging a patient case they would like educational feedback on in the future. Flagging a case is done in the “Disposition View” of the clinician decision tree in Epic (Figure 5). After the waiting period of the patient progressing through levels of care and finally discharging from the hospital, the HIPAA compliant UM GPT will send the provider a summary directly to their institutional email.

Figure 5. Disposition View in Epic MyChart

Screenshot of a medical software interface showing a disposition view with color-coded task categories and a follow-up order section. Tasks include work/school/sport excuses and patient portal letters in green and blue boxes, with a follow-up question form on the right allowing email summary timing selection and additional patient questions.

To validate that the AI summary was providing impactful and meaningful patient information, Schmitzberger and Janke developed a structured validation procedure for 200 AI-generated case summaries measuring for accuracy, conciseness, helpfulness, and completeness. The initial scoring showed that the AI summaries were quite accurate and helpful (Figure 6). This early positive feedback has prompted continued work on developing the use of this program in other areas of the institution.

Figure 6. Structured Validation of 200 AI-Generated Case Summaries

A table displays four performance metrics for validation of 200 AI-generated case summaries with scores out of 5: Accuracy (4.79), Conciseness (4.86), Helpfulness (4.60), and Completeness (4.28). Each metric is labeled in red text below the blue numerical scores.

Results

Currently the program includes 170+ unique users including faculty, residents, and physician assistants, who are averaging approximately 40 – 70 requests each week, and 30+ power users (a clinical or other staff member who maximizes Epic electronic health record (EHR) efficiency using advanced tools and navigation).

The top three case follow up themes for requested summaries included diagnosis/etiology (~40%), disposition/course/ICU (~17%), and test/imaging results (~10%). With strong approval in the emergency department and endorsement from other committees, the goal is to expand this feedback program to multiple areas within the institution.

Next Steps & Discussion

Janke presented two pathways in which they would like to proceed with expanding the AI feedback program. The first would be horizontal scaling across the institution, including integration into the graduate medical education program for internal medicine/hospitalist care. Second, they would like to apply their approach to a quality measure from the Michigan Emergency Department Improvement Collaborative (MEDIC).

The presenters addressed participant questions about sharing learnings between providers, patient record privacy, and potential applications in other areas like pediatric care and fall prevention, with participants suggesting connections with the Michigan Hospital Medicine Safety Consortium (HMS) metrics and exploring CEUs as incentives for provider participation.

MVC Health in Action Workgroup: June 25, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us by email if you are interested in being a workgroup presenter or submit a presentation proposal here.

Off
View Post
MVC Thanks Presenters from the First Half of 2026

MVC Thanks Presenters from the First Half of 2026

The MVC Coordinating Center wishes to express its heartfelt appreciation for the 39 generous healthcare professionals who stepped forward to present during MVC’s first and second quarter virtual workgroups, spring collaborative-wide meeting, and Michigan Cardiac Rehabilitation network (MiCR) virtual forums on telehealth rehabilitation. The MVC Coordinating Center would not be able to deliver the variety of high-quality educational opportunities without the contribution of these dedicated volunteer presenters. We know that MVC’s members and partners have many demands on their time from within their own organizations and beyond. Nonetheless, these 39 guest speakers shared their data, innovative approaches, best practices, and insights to support our shared goals of peer learning and high-value care delivery for Michigan patients. We appreciate you contributing in this important way. You DO make a difference!

Join us in giving these folks a well-deserved round of applause:

Cardiac Rehab Workgroup

  • Robert Berry, MS, ACSM-CEP, FAACVPR, Clinical Coordinator Cardiac Rehabilitation, Henry Ford Health Henry Ford Hospital
  • Zach Johnson, BS, ACSM-CEP, Lead Exercise Physiologist for Cardiac and Pulmonary Rehab Programs, Corewell Health
  • Steven Keteyian, PhD, Bioscientific Clinical Staff, Division of Cardiovascular Medicine, Henry Ford Health Henry Ford Hospital
  • Laura Meiste, RN, BSN, Manager of Cardiac and Pulmonary Rehab, Holland Hospital
  • Greg Scharf, BS, CEP, CCRP, Cardiopulmonary Rehab System Manager, MyMichigan Health
  • Mike Thompson, PhD, FAHA Associate Professor of Cardiac Surgery, Michigan Medicine
  • Tyelor Wymer, CEP, BS, Cardiology Supervisor, University of Michigan Health-Sparrow

Health in Action Workgroup

  • Jennifer Hengy, BSN, RN, Internal Quality Improvement Specialist Sr., Corewell Health Farmington Hills
  • Alexander Janke, MD, MHS, MSc, Assistant Professor of Emergency Medicine, University of Michigan
  • Eugene Laveroni, MD, Chief of Surgery, Corewell Health Farmington Hills
  • Florian Schmitzberger, MD, MS, Clinical Assistant Professor of Emergency Medicine, University of Michigan
  • Leslie Smith, RPh, JD, BCPS, BCIDP, Clinical Pharmacist Specialist, Corewell Health Farmington Hills

Post-Discharge Follow-Up Workgroup

  • Steven Frazier, BA, RN, ACM-RN, Director of Quality and Patient Safety Post-Acute, MyMichigan Health System
  • John Hagan, DO, Medical Director - Care Coordinating Center, MyMichigan Health System

Rural Health Workgroup

  • Heather Baumeister, BSN, RN, CRHCP, Director of Healthcare Practices, McKenzie Health System

Sepsis Workgroup

  • Tami Garcia, MSN, RN, Sepsis Process Lead, Michigan Medicine
  • Carly Redstone, MSN, RN, Sepsis Coordinator, Michigan Medicine

Spring Collaborative-Wide Meeting Panelists

  • Alex Callaway, MBA, CPHQ, CPPS, Regional Quality Director, Munson Health System
  • Emily Nerreter, MBA, CPC, CRC, Pay for Performance & Registries Manager, Henry Ford Health System
  • Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Analysis & Enhancement, MyMichigan Health

Spring Collaborative-Wide Meeting Breakout Session Speakers

  • Belinda Dokic, CPhT, BA, MBA, Post-Acute Care Manager, Trinity Health Alliance of Michigan
  • Cindy Ingersoll, RN, BSN, CCM, Post-Acute Care Manager, Trinity Health Alliance of Michigan
  • Adrien Ross, MSN, RN, CPHQ, Lead, Quality Improvement Specialist, Corewell Health
  • Heidi Steinhebel, RN, BSN, CCM, Senior Associate Director of Care Management, Trinity Health IHA Medical Group
  • Caitlin Valley, MHA, MPH, CHES, Director of Quality and Population Health, Trinity Health IHA Medical Group
  • Larrea Young, MDes, Multimedia Design Project Manager, Healthy Behavior Optimization for Michigan

Spring Collaborative-Wide Meeting Poster Presenters

  • Jennifer Bennett, MBA, BSN, RN, Lead Quality and Patient Safety Coordinator, Henry Ford Health Madison Heights-Warren Hospital
  • Sara Hagerman, BSN, RN, Community Hospital Quality Lead, University of Michigan Health – Sparrow Carson
  • Ginger Johnson, OTR, Manager Post-Acute Care, Populance, Henry Ford Health System
  • Mike Johnson, Primary Care Practice Administrator, Munson Healthcare East Region
  • Liz Monk, System Director of Patient Care Manager, Munson Healthcare
  • Gloria Rey, PA-C, MPH, Director Post-Acute Care, Populance, Henry Ford Health System
  • Audra Stoker, PMP, Manager Post-Acute Care Network Development, Populance, Henry Ford Health System

Virtual Networking Event

  • Richard Wylde, MSc, Deputy Director of Improvement at Leeds and York Partnership NHS Foundation Trust

MiCR Virtual Forums on Telehealth Cardiac Rehabilitation

  • Robert Berry, MS, ACSM-CEP FAACVPR, Clinical Coordinator of Cardiac Rehabilitation, Henry Ford Health
  • Samantha Fink, BS, Administrative Manager, Domino’s Farms Cardiology, Michigan Medicine
  • Steven J. Keteyian, PhD, Bioscientific Clinical Staff, Division of Cardiovascular Medicine, Henry Ford Hospital
  • Diane Perry, MS, ACSM-CCEP, CHWC, Certified Clinical Exercise Physiologist, Michigan Medicine
  • Kat Steenson, MS, Clinical Exercise Physiologist, Henry Ford Health
Graphic design featuring silhouettes of eight business people standing above bold text reading "THANK YOU" on a blue bokeh background. Two circular shapes contain Michigan Value Collaborative logo on left and text "From all of us at MVC" on right, expressing gratitude from the organization.

The MVC members and partners who attend MVC events appreciated these presenters, too. Here are just a few of the many glowing survey responses MVC received about presenters and their content in the first half of 2026.

Screenshot of five positive testimonial quotes about MVC workgroups and collaborative-wide meetings, displayed in white text with orange quotation mark icons on a blue background. Quotes highlight benefits such as insightful content, flexible conversation, valuable information sharing, and practical application for sepsis process development in emergency department triage.

As a reminder, past workgroups and virtual networking event recordings can be viewed on MVC’s YouTube channel, and presentation slides and materials from MVC’s spring collaborative-wide meeting can be viewed here.

Do you have valuable information to share?

Whether you are new to presenting or a seasoned pro, the MVC Coordinating Center is here to support you every step of the way. From exploring topic ideas to preparing information and managing event logistics, our team makes the experience of presenting easy and comfortable. The P4P points you can earn as a presenter are a great benefit to your organization, too. For more information about presenting, contact the MVC Coordinating Center or submit a proposal here.

Off
View Post
May Workgroup Highlights Building and Sustaining a Systemwide Sepsis Team

May Workgroup Highlights Building and Sustaining a Systemwide Sepsis Team

In May, the Michigan Value Collaborative (MVC) hosted a virtual sepsis workgroup featuring a presentation on the evolution of Michigan Medicine’s enterprise-wide sepsis initiative and the lessons learned while building a sustainable, multidisciplinary sepsis program. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Sepsis Workgroup – Michigan Medicine

Sepsis remains one of the leading drivers of mortality across healthcare systems, including Michigan Medicine. When sepsis can be treated, this not only reduces patient mortality, but also length of stay, readmissions, morbidities, and overall health of patients, so it comes as no surprise that Michigan Medicine recognized the need to make modifications to their current approach to sepsis management. Presenter Tami Garcia, MSN, RN, Sepsis Team Manager at Michigan Medicine explained how they began by moving away from siloed approaches to care. Early efforts focused on understanding existing workflows across Michigan Medicine’s enterprise and identifying inconsistencies in sepsis care. This included the recognition, escalation, and treatment of sepsis across adult, maternal, emergency and inpatient care settings.

While the team had a foundation set up with dashboards and procedural guides for screening, there had never been a team dedicated to ensuring consistent sepsis care across the system. Rather than immediately deploy new tools or mandates, this new team prioritized “Gemba walking” to meet providers where they work to better understand barriers, workflows, and frontline realities. As Garcia explained, “we need to build changes with our staff, not to our staff.” Garcia credited this approach to helping the sepsis team identify opportunities to standardize care while also building trust with bedside clinicians.

Building Trust as a Quality Improvement Strategy

A major theme throughout Garcia’s presentation was the importance of developing trust in quality improvement work. She emphasized that credibility and relationships became foundational to the success of this sepsis initiative. In addition to Gemba walking, the team focused on:

  • Maintaining a visible unit presence
  • Responding quickly to staff concerns
  • Closing communication loops
  • Listening to frontline staff frustrations
  • Incorporating clinician feedback into workflow design

Figure 1. Michigan Medicine’s Sepsis Team Standard Work and Governance Framework

Flowchart diagram illustrating sepsis coordinator rounding process and workflow reliability in a healthcare setting. It includes labeled boxes for standard work steps (Recognize, Huddle/escalate, Execute sepsis bundle), clear ownership by program team and units, and feedback loops showing stages of communication (What we heard, What changed, What we measured).

One notable outcome of this approach involved the reduction in excessive Epic alerts that historically contributed to alarm fatigue among nursing staff. Rather than dismissing the concerns, the team partnered with clinicians and informatics specialists to reduce unnecessary alerts and improve usability. This example is related to just one of the four main lessons learned by the sepsis team:

  1. Trust-building is a deliverable
  2. Tools must fit a workflow, otherwise they become workarounds
  3. Sustainment requires ownership
  4. Reducing burden (e.g., alarms) is improvement, not compromise

Standardizing Sepsis Recognition and Response

Following this period of learning and trust-building, the Michigan Medicine sepsis team began implementing a series of targeted interventions designed to improve reliability and timeliness of care.

Some key initiatives included:

  • Re-establishing multidisciplinary sepsis huddles in the adult emergency department
  • Enhancing Epic tools and workflows (adult, pediatric, etc.)
  • Launching maternal sepsis screening and nurse-initiated patient care orders
  • Implementing non-invasive fluid responsiveness technology in ICUs
  • Establishing nurse sepsis champions and physician ambassador programs
  • Creating neonatal sepsis response workflows in the NICU

Figure 2. Michigan Medicine’s ER Workflow and Sepsis Huddle Process Map

Flowchart illustrating ER workflow and Sepsis Huddle process for Michigan Medicine, detailing steps from initial sepsis screen to reassessment and monitoring. Key elements include color-coded boxes for tasks like RN paging for Sepsis Huddle, provider actions, and code sepsis activation, with timelines and criteria for bundle completion and reassessment.

Garcia highlighted the adult emergency department sepsis huddles as one of the team’s most impactful initiatives. The huddles bring nurses and providers together immediately after a positive sepsis screen to rapidly determine next steps and initiate treatment plans. This converts concern into coordinated action and normalizes escalation. Combined with streamlined order workflows and decision-support tools, timeliness of care and collaboration between disciplines have been improved.

Measurable Improvements in Sepsis Outcomes

Measurable improvements in both process and outcome measures since the formation of the dedicated sepsis team in 2022 were then reviewed. The reported improvements included:

  • Adult emergency department SEP-1 bundle compliance increased from approximately 50% in 2022 to almost 80% in 2026
  • Severe sepsis and septic shock mortality rates decreased from 26.2% in 2022 to 20.1% in 2025
  • Maternal sepsis screening rates exceeded 90% for OB triage and 78% for inpatient screens
  • Pediatric sepsis alert burden was reduced significantly from over 35,000 OPA’s in 2022 to just under 20,000 in 2025
  • Reduced the frequency of first antibiotic administration in neonatal populations at >120 minutes from over 40% to under 15% between the beginning and end of 2025

Garcia repeatedly credited frontline teams for these successes, emphasizing that sustained improvement depended on empowering all team members, especially clinicians, rather than relying solely on centralized oversight.

Expanding Frontline Ownership Through Sepsis Champions

One of the most promising developments discussed was the creation of the RN Sepsis Champion Program. Nurses serving as sepsis champions support local reliability, providing peer-to-peer education, reinforcing workflows, and helping to disseminate best practices within their units. Garcia described how this program has expanded rapidly across the Michigan Medicine organization and has already demonstrated improvements to bundle compliance and mortality outcomes in pilot units. Champions are especially important given high turnover rates and shifting operational pressures in healthcare. With monthly meetings, shared educational resources, and ongoing collaboration, champions help maintain momentum and create local ownership of sepsis improvement efforts.

Looking ahead, Michigan Medicine plans to sustain workflows, expand sepsis huddles, and strengthen support for sepsis champions and physician ambassadors. Garcia closed the presentation by reinforcing that successful sepsis improvement, or perhaps any quality improvement initiative, depends on partnership, humility, and continuous learning. As Garcia explained, “We really want to continue to partner with our teams to make sure they understand why we’re here, that they trust we’re here for the best of everybody -them and their patients.”

MVC Sepsis Workgroup: May 21, 2026

MVC welcomes presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members through various best-practice sharing platforms. Please reach out to us by email if you are interested in being a workgroup presenter or submit an online presentation proposal.

Off
View Post
April Workgroup Features Preoperative Testing Multipayer Report Registry Demonstration

April Workgroup Features Preoperative Testing Multipayer Report Registry Demonstration

In April, the Michigan Value Collaborative (MVC) hosted a virtual preoperative testing workgroup featuring a presentation by the MVC Coordinating Center focused on utilizing MVC’s multi-payer preoperative testing registry reports. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Preoperative Testing Workgroup – MVC Coordinating Center

The MVC registry includes many different reports for members to utilize when investigating various conditions, procedures, and outcomes. One of the more recent additions includes the preoperative testing reports which include claims data from multiple payers in one location. Reports that were highlighted in the preoperative testing workgroup included the preoperative testing table report, preoperative testing trends report, and preoperative testing utilization rankings report.

Each report offers members multiple filters to modify the data shown including episode start dates, payer selection, specific conditions (or the option to choose all), several common preoperative tests, such as blood tests, cardiac tests, chest x-ray, electrocardiography (EKG), pulmonary function tests, and urinalysis, and patient demographics (age, gender, race/ethnicity, comorbidities).

MVC Site Engagement Coordinator and workgroup presenter Emily Bair, MS, MPH, RDN, introduced the workgroup by sharing a preoperative testing utilization trend graph that included data on all MVC members and all available payers. The graph demonstrated that since the implementation of the preoperative testing value-based initiative in 2020, MVC members have seen a 6% decrease in unnecessary preoperative testing utilization for specific low-risk procedures. Based on available claims data, preop testing rates across the collaborative have declined from approximately 44% to 38% since 2022.

MVC’s preoperative testing measure definition includes the following:

  1. Numerator: episodes of care where preoperative testing (e.g., urinalysis, pulmonary function, chest x-ray, electrocardiography, certain blood tests, and certain cardiac tests) occurred in the 30 days prior to MVC-defined low-risk laparoscopic cholecystectomy, inguinal hernia repair, and lumpectomy procedures.
  2. Denominator: Elective and outpatient MVC-defined cholecystectomy, inguinal hernia repair and lumpectomy episodes with length of stay between 0 – 2 days.

The preoperative testing initiative, known as the RITE-Size initiative, has been an ongoing collaborative effort between MVC, the Michigan Surgical Quality Collaborative (MSQC), Anesthesiology Performance Improvement and Reporting Exchange (ASPIRE), and the Michigan Program on Value Enhancement (MPrOVE). MVC and MSQC data registries were updated with preoperative testing metrics to improve visibility for members, give access to diverse data, and offer unique customization tools for preoperative testing reports. The MVC engagement team has an ongoing effort to engage and educate members on all of the resources available to them through our registry and data reports. To learn more about attendee usage of MVC data, Bair polled participants to assess whether they had accessed the preoperative testing reports, and if so, whether they used the data in any quality improvement (QI) efforts at their site or system (Figures 1 and 2).

Figure 1. Poll: Have You Accessed MVC’s Multi-payer Reports?

Bar chart showing participant responses to accessing MVC's multi-payer reports, with three horizontal bars labeled "Yes," "No," and "Don't have access." The chart indicates 45% answered "No," 35% "Yes," and 15% "Don't have access," highlighting a majority have not accessed the reports.

Figure 2. Poll: Have You Used MVC’s Multi-payer Reports to Support QI?

Horizontal bar chart showing responses to using MVC's multi-payer reports for supporting QI, with three categories: "No" at about 38%, "Don't have access" at about 32%, and "Yes" at about 23%. Chart uses orange bars with percentage labels on the x-axis ranging from 0% to 45%, highlighting majority respondents either do not use or lack access to the reports.

The polling discussion revealed that while many attendees had registry access, 44% had not utilized these multi-payer reports for quality improvement work. Those that did utilize the reports (23%) shared that they use them for efforts such as system-level benchmarking across their hospitals.

Following the polling results, Bair shared unblinded data from Bronson Health System’s MVC multi-payer registry reports and MVC common conditions push report, covering how differing case counts can impact preoperative testing rate performance, especially when looking at conditions separately. Case volume is a common concern for smaller hospitals, such as critical access sites, when trying to extrapolate useful claims data. As larger health systems are acquiring smaller hospitals like critical access sites, though, they may need to shift how the data can and should be interpreted. Using yearly trending can increase the denominator for case data and give a more accurate visual representation of utilization or performance over time, whereas looking at data on a monthly or quarterly timeframe can show volatility due to case counts having high variability over short time ranges.

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us by email if you are interested in being a workgroup presenter or submit an online presentation proposal.

Off
View Post
March Workgroups Highlight Rural Remote Patient Monitoring and Post-Discharge Follow-Up Innovations

March Workgroups Highlight Rural Remote Patient Monitoring and Post-Discharge Follow-Up Innovations

In March, the Michigan Value Collaborative (MVC) hosted two workgroups highlighting innovative strategies to improve care transitions and expand access to care across Michigan. A rural health workgroup explored how McKenzie Health System implemented remote patient monitoring to support patients with chronic conditions. MVC’s post-discharge follow-up workgroup featured a presentation from MyMichigan Health on the development of a continuing care clinic designed to improve post-discharge follow-up and reduce hospital readmissions.

Together, these presentations demonstrated how healthcare organizations can leverage care coordination, technology, and new care delivery models to improve patient outcomes across the continuum of care. The MVC Coordinating Center hosts one to two workgroup presentations per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Rural Health Workgroup – McKenzie Remote Patient Monitoring

The first workgroup of the month featured a presentation led by Heather Baumeister, BSN, RN, CRHCP, Director of Healthcare Practices at McKenzie Health System, who shared how her organization implemented a remote patient monitoring (RPM) program to better support patients living in rural communities.

McKenzie Health System includes a 25-bed critical access hospital (CAH) located in Sandusky, Michigan. The organization also operates six primary care clinics across multiple communities throughout the Thumb region offering several specialty services such as gastroenterology, orthopedic care, general surgery, and behavioral health. Like many rural health systems, McKenzie serves a geographically dispersed patient population where travel distance and limited healthcare resources can make frequent in-person visits difficult. To help bridge these gaps, Baumeister said, the organization relies heavily on care coordination.

McKenzie currently employs three full-time and one part-time registered nurse care coordinators who support primary care clinics across the system. Baumeister described how these coordinators conduct daily follow-ups with patients seen in the emergency department and help connect patients without an established primary care provider to appropriate outpatient care. Care coordinators also participate in monthly readmission review meetings to identify patients who may benefit from additional care management services and reduce avoidable hospitalizations.

Launching a Remote Patient Monitoring Program

To expand its ability to monitor patients between visits, McKenzie Health System participated in an 18-month pilot program focused on RPM for rural health systems. After completing the pilot, McKenzie established a long-term partnership with an RPM vendor to manage several operational aspects of McKenzie’s RPM program, including device shipping, monitoring, nurse outreach for readings outside clinical thresholds, uploading data into the electronic health record (EHR), and billing services. Baumeister said this helped clinicians at McKenzie to integrate RPM into their care model without needing to manage the technical infrastructure internally.

Providers refer patients to the program through the organization’s EHR. After receiving a referral, the RPM vendor enrolls the patient and distributes the appropriate monitoring devices. Patients enrolled in the program receive connected monitoring devices that automatically transmit readings directly to the monitoring platform after patients begin taking measurements. Devices currently used include blood pressure cuffs, weight scales, blood glucose monitors, and pulse oximeters. If readings fall outside predetermined ranges, a monitoring nurse contacts the patient to assess symptoms and determine whether clinical intervention is needed. If necessary, the nurse escalates the case to the patient’s provider according to established care protocols.

Implementing the program in a rural context presented several challenges. Baumeister described how unreliable internet near Michigan’s lakeshore, difficulty reaching patients by phone, and excessive measurement were challenges in delivering the program.

Benefits of RPM Program

Baumeister said the RPM program is particularly beneficial for patients managing chronic conditions like congestive heart failure, diabetes, hypertension, chronic obstructive pulmonary disease, and obesity. This is because remote monitoring enables care teams to detect early warning signs of health deterioration that might otherwise go unnoticed between routine visits so providers can intervene proactively. Baumeister gave examples such as adjusting medications, scheduling follow-up appointments, or providing additional education before conditions worsen.

She also noted that many patients became more engaged in their own care through the program, as regular monitoring helped them better understand how lifestyle choices affect their health. View the complete workgroup recording using the video below.

MVC Rural Health Workgroup: March 3, 2026

Post-Discharge Follow-Up Workgroup – MyMichigan Health Continuing Care Clinic

MVC’s second March workgroup featured a presentation by Steven Frazier, MHA, BA, RN, ACM-RN, Director of Quality and Patient Safety for Post-Acute Services at MyMichigan Health, and Dr. John Hagan, DO, Family Medicine Physician and Medical Director of the Continuing Care Clinic at MyMichigan Health. Their presentation highlighted the MyMichigan Health Continuing Care Clinic (CCC), a program designed to ensure patients receive timely follow-up care after hospitalization and to reduce hospital readmissions. Frazier previously presented about the establishment of the CCC program at MVC’s May 2024 collaborative-wide meeting, and this month provided a number of updates on progress in the program to date.

MyMichigan Health serves more than one million Michigan residents across a 26-county region, with multiple medical centers and roughly 1,100 hospital beds. Despite this extensive network, MyMichigan recognized that many patients faced barriers to obtaining timely follow-up care after leaving the hospital, citing limited appointment availability with primary care providers as well as patients without established providers struggling to navigate the healthcare system.

Frazier and Hagan said internal MyMichigan data revealed hospital readmissions were often occurring 12-13 days after discharge, highlighting a critical window when follow-up care could potentially prevent complications. Research also suggested that follow-up with a physician within seven days of discharge could significantly reduce both readmission and mortality risk for patients hospitalized with conditions such as heart failure, myocardial infarction, and COPD.

Launching and Evolving the Continuing Care Clinic

To address these gaps in care, MyMichigan Health opened the CCC in Midland, Michigan in August 2023. The clinic now operates with two locations (Midland and Alma) and three providers, supported by a multidisciplinary care team. The clinic was designed to function as a transitional care bridge, ensuring patients receive follow-up care within seven days after discharge while they wait to reconnect with their primary care providers. Services currently range from follow-up visits and assistance with establishing a primary care provider to behavioral health support and advance care planning.

Since its launch, the clinic’s role has expanded beyond its original focus on hospital discharge visits to support patients who are transitioning between primary care providers, are new to the community’s providers, need additional support navigating the healthcare system, or are seeking follow-up after emergency or urgent care visits. This evolution has allowed the clinic to function as a comprehensive transitions-of-care hub within the MyMichigan Health system.

Early Results and Impact

According to Frazier and Hagan, the CCC has already demonstrated encouraging results, saying that the program helped the health system achieve lower readmission rates compared to peers and maintain short scheduling lead times for follow-up appointments. Additionally, MyMichigan has seen an improvement in operational efficiency and budget performance with the expansion of services to additional geographic regions within the system. The program has also helped bring new patients to the MyMichigan Health network by connecting individuals without primary care providers with internal ongoing care relationships.

Patient feedback has been an important indicator of the clinic’s success, the presenters noted. Patient testimonials were shared during the presentation that emphasized how the clinic helped patients better understand their diagnoses, feel supported during recovery, and access care more easily after discharge. Patients described the clinic as a valuable resource that provided compassionate care and guidance during a vulnerable time in their healthcare journey. View the complete workgroup recording using the video below.

MVC Post-Discharge Follow-Up Workgroup: Mar. 19, 2026

Key Takeaways for MVC Members

The March workgroups highlighted two practical approaches to improving patient outcomes across the care continuum, with several key themes emerging. For one, remote patient monitoring is expanding access to care by helping teams identify early warning signs and better manage chronic conditions—especially in rural communities. At the same time, dedicated transition clinics are strengthening post-discharge care by ensuring timely follow-up and support after hospitalization.

Across both models, strong care coordination remains essential, supported by multidisciplinary teams, clear communication, and sometimes newer technologies. Just as important, patient engagement continues to drive better outcomes by empowering individuals to take a more active role in their care.

Through these shared examples, MVC workgroups continued to support collaboration and help organizations across Michigan identify actionable strategies to improve quality, outcomes, and value. If you are interested in pursuing a healthcare quality improvement project, MVC has data specialists available to help you navigate our data resources and create custom analytics reports to support your efforts. Please reach out to us by email [LINK] if you would like to learn more about MVC data, engagement offerings, or would like to present at a future MVC workgroup.


Off
View Post
February Workgroup Highlights Increasing Cardiac Rehabilitation Utilization with a Member Panel and MVC Data

February Workgroup Highlights Increasing Cardiac Rehabilitation Utilization with a Member Panel and MVC Data

In February, the Michigan Value Collaborative (MVC) hosted a virtual cardiac rehabilitation workgroup presentation featuring a panel of cardiac care specialists. The panel focused on discussing chronic heart failure metrics related to the pay for performance (P4P) program and how cardiac rehabilitation (CR) can play a vital part in the recovery process for congestive heart failure (CHF) patients. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Cardiac Rehabilitation Workgroup – MVC and Member Panel 

For this workgroup MVC was joined by panelists Tyelor Wymer, CEP, BS, Cardiology Supervisor at University of Michigan Health (UMH) Sparrow-Clinton; Laura Meiste, RN, BSN, Manager of Cardiac and Pulmonary Rehabilitation at Holland Hospital; Zach Johnson, BS, ACSM-CEP, Lead Exercise Physiologist for Cardiac and Pulmonary Rehabilitation Programs at Corewell Health; Greg Scharf, BS, CEP, CCRP, Cardiopulmonary Rehabilitation System Manager at MyMichigan Health; and Mike Thompson, PhD, MPH, Associate Professor of Cardiac Surgery at Michigan Medicine

CHF Goals and Metrics

MVC’s Site Engagement Coordinator Emily Bair, MS, MPH, RDN, CSP, began the workgroup by reviewing CHF P4P metrics for program years 2026 – 2027, which is part of MVC’s Cardiac Rehabilitation Value-Based Initiative. These included an episode spending metric focused on CHF episodes of care and a value metric that tracks the 7-day follow up care for CHF episodes of care. In addition to discussing the P4P CHF metrics, Bair reviewed current CR standards that MVC uses for measuring the CR value-based initiative, including Michigan Cardiac Rehabilitation Network (MiCR) standards and the Million Hearts Campaign CR goal for CHF patients (Figure 1).

Figure 1. MVC, MiCR and Million Hearts CR Goals for CHF Patients

Presentation slide titled "Goals & Metrics" outlining cardiac rehabilitation follow-up and start rate targets. It lists MVC P4P Metrics with a 7-day follow-up after CHF, Michigan Cardiac Rehab Network aiming for 10% of CHF patients to start CR within 365 days, and Million Hearts with ACC and AHA targeting 70% of eligible patients to start CR within 365 days.

MVC Registry and Data Reports Resources

Bair highlighted some of MVC’s relevant data reports and how the episodes of care are built within the MVC data registry. Bair noted that MVC episodes of care have a slightly different post-discharge window for CHF patients in CR, 365 days (Figure 2), versus the 30 – 90-day windows for patients with cardiac conditions such as percutaneous coronary intervention (PCI)/coronary artery bypass grafting (CABG). The MVC data registry has several useful cardiac related reports including,

Multi-payer CR reports which evaluate CR utilization and other metrics provided in MVC’s hospital-level reports:

  • CR Utilization Rates
  • CR Utilization Rankings
  • Mean Days to First CR Visit
  • Mean Number of CR Visits

Payer specific reports which allow registry users to investigate utilization, readmissions rates, and cost of care including:

  • Episode Payment Report
  • Episode Utilization Rate Report
  • Readmissions Report
  • CR Report

Figure 2. Example of MVC Registry CR Utilization Rate within 365 Days After Discharge for CHF, Jan. 2024 – Mar. 2025 (MVC All, blinded):

Dotted line graph

The graph above shows that from Jan. 2024 – Mar. 2025, the MVC All average was  6% for CR participation within 365-days post-discharge for CHF patients. With the MiCR goal being a 10% CR utilization for CHF patients and the overall utilization range being 0% to 19%, it is clear there is room for improvement across the MVC member portfolio.

Push reports are another useful resource offered by MVC. The Process Measures Report that MVC shared with members in January 2025 had helpful visuals of site and system 7-day follow up data for CHF episodes of care (Figure 3).

Figure 3. MVC Process Measures Report – 7-day follow up after CHF

example of MVC Process Measures Report for 7-Day Follow-Up After CHF content including vertical bar charts and line graphs

Panel Discussion

The focus for the panel discussion centered around how CR services can be utilized to support rehabilitation of CHF patients who may not be able to participate in rehabilitation as quickly as those that have conditions such as PCI or CABG. Bair began the discussion by leading participants through a common care pathway for CHF patients who utilize CR (Figure 4).

Figure 4. CHF Follow-Up and Cardiac Rehabilitation Typical Patient Pathway

Diagram illustrating the typical CHF patient pathway with five key stages: Admission, Discharge, Follow-Up, Cardiac Rehab, and Readmission. Annotations highlight transitions such as patient diagnosis, care shift from inpatient to outpatient, appointment scheduling, referral placement, and follow-up care including rehab and emergency department utilization.

CHF Barriers to Care and Change Concepts

To help organize a solutions-based approach, Bair went on to introduce the Change Concepts Model, 2nd Ed. (Figure 5) adapted from the Million Hearts Initiative to address some of the common barriers seen in CHF care.

From the Million Hearts Change Package, 2nd Ed., some notable barriers to care for CHF follow-up in CR include:

  • Patient or provider lack of awareness
  • Lack of clear and consistent communication
  • No integration of CHF cardiac rehabilitation needs into cardiovascular services or workflows
  • Limited capacity of CR programs
  • Patient transportation, financial burden, competing responsibilities or cultural/language barriers

Figure 5. Million Hearts Change Concepts

Flowchart illustrating four stages of a process: Systems Change, Referrals, Enrollment and Participation, and Adherence.

Systems Level Change

Bair shared some of the ways systems change could be implemented including establishing a hospital CHF champion, engaging hospital administrators and senior staff, securing and maintaining a multidisciplinary workforce, engaging the cardiac care team in the follow-up care and rehabilitation planning, tracking follow-up/CR referrals, enrollment rates, and patient participation as quality-of-care indicators.

UMH Sparrow-Clinton’s Tyelor Wymer shared that they have had success with appointing CHF champions in their centralized cardiac care team. Team members rotate through four to five different UMH Sparrow hospitals, fostering consistent care practices across the health system. MyMichigan Health System’s Greg Scharf shared that they have a similar system wide collaborative team for heart failure care, and they have had great success as well.

At Holland Hospital, Laura Meiste shared that they have a care transitions team that works in the cardiology department and focuses specifically on patient follow-up within seven days of discharge, while also working on maintaining consistent communication with the administrative staff that schedules patient appointments.

Optimizing Referrals

Another opportunity to reduce barriers to care is by improving the referral process itself. This can be done by using data to drive improvements and incorporating referrals into standardized processes. Some examples include:

  • Adding CHF cardiac rehabilitation language to echo reports for patients with reduced ejection fraction (EF) that meet the appropriate criteria for CR
  • Including a referral to CR in order sets for patients with CHF
  • Adding CR to guideline-directed medical therapy algorithms for patients with CHF

Scharf shared that optimizing referrals is an ongoing challenge in MyMichigan Health’s system where there might be a standardized best practice advisory (BPA) for CHF in general, but there is no built-in trigger for flagging a CHF case as CR appropriate. Working in the Epic electronic health record (EHR) program, they can create custom BPAs for this, but it takes time and education.

Meiste shared that at Holland Hospital, an auto-referral process through an order set triggers a case in the system to be sent to clinical staff for CR eligibility screening. If the case meets eligibility criteria, the staff will set up an in-person visit with the patient. Similarly, workgroup participant Karolina Kaser, BSN, RN, MBA, CIC, Quality, Safety and Experience Director for Corewell Health Dearborn, shared that their site utilizes standardized clinical pathways for their cardiac cases. Included in the pathway is an order set that automatically includes a CR referral even for CHF cases. Some other effective processes have been to utilize the cardiac nurses to ensure CHF patients have CR offered if they meet criteria, as well as training administrative and call center staff on the importance of scheduling these follow-up appointments.

Enrollment and Participation

Increasing enrollment is a key goal in the Million Hearts change concept. This may include methods of optimizing care coordination for patients by promoting enrollment into CR at follow-up appointments and reducing delay from discharge to their first CR appointment. This can be done by using data to drive improvement in follow-up appointments and enrollment numbers, and by developing flexible delivery models such as hybrid CR programs. MiCR tools and resources also help to boost CR enrollment.

Supporting Adherence and Reducing Non-Medical Barriers

The next step in the change concept process is finding ways to reduce inconsistent adherence to a CR program. Some recommendations to address this issue included identifying populations at risk for low engagement, accounting for patient needs such as lack of transportation, incorporating motivational incentives, and utilizing automated communications and reminders.

Zach Johnson from Corewell Health System shared that they have a successful support group established that meets quarterly. The group includes a range of patients who have either completed the CR program or those who are just beginning their journey to recovery. To address some of the common barriers for patients, Corewell has partnered with Michigan Rehabilitation Services to help cover a patient’s copay with a contingency that the patient plans to return to work for a minimum of 20 hours per week in the future.

To address transportation barriers, Corewell has partnered with True North which is funded by a family donation fund. If a patient meets the criteria for being at or below poverty level, they will qualify to receive financial assistance to cover the cost of transportation to and from visits. Holland Hospital’s Meiste shared they have utilized a mini grant awarded from the MiCR initiative to fund their heart failure orientation and to offer copay assistance to patients in need.

Opportunities for Further Improvement

Bair rounded out the panel discussion by asking panelists to describe unique challenges they identified when trying to incorporate CHF patients into CR programs. In response to Scharf’s inquiry about strategies to connect with patients who have CHF but have not yet met the 35% EF criteria, MVC Faculty Advisor, Mike Thompson shared that cardiac clinicians at Michigan Medicine are having CR conversations with CHF patients earlier in the disease process.

Additionally, lack of a standardized approach to discussing cardiac rehab for patients at 40% - 35% EF range is a common concern. Wymer shared that UMH Sparrow-Clinton addressed this by encouraging clinicians to urge patients who fall within the 35 – 40% EF range to begin participating in CR before their condition deteriorates further. MVC members can raise awareness by following and reposting BMC2 and MVC on LinkedIn.

MVC Cardiac Rehabilitation Workgroup: Feb. 10, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please email us if you are interested in being a workgroup presenter or submit a presentation proposal online.

Off
View Post
January Workgroups Highlight Using Claims Data to Drive Sepsis QI and Reducing SSIs Through Multidisciplinary Collaboration

January Workgroups Highlight Using Claims Data to Drive Sepsis QI and Reducing SSIs Through Multidisciplinary Collaboration

In January, Michigan Value Collaborative (MVC) kicked off the 2026 workgroup calendar with a sepsis workgroup focused on helping members better understand how to use claims-based data to support sepsis quality improvement (QI) efforts. The session featured an overview of sepsis-related reporting available on the MVC registry followed by an example of how custom analytic reports can be used to dig deeper into areas of clinical interest. The second workgroup of the month, a health in action presentation, featured Corewell Health Farmington Hills Hospital’s multi-year QI initiative aimed at reducing surgical site infections (SSIs) in colorectal surgery. The MVC Coordinating Center hosts one to two workgroup presentations per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Sepsis Workgroup – MVC Coordinating Center

The workgroup opened with a presentation by MVC’s Site Engagement Coordinator Rachel Folk, MHA, who walked participants through the types of sepsis related data available in the MVC registry and how members can use these reports to support local QI initiatives. The presentation emphasized that MVC’s claims-based data registry allows members to examine sepsis episodes of care across multiple payers and care settings, providing a broader view of healthcare utilization and outcomes than many internal data sources alone.

Participants were introduced to several registry reports that are particularly relevant to sepsis analysis, including:

  • Episode Payments Report, which shows total, price-standardized payments for 30- or 90-day episodes and can be used as a proxy for assessments of utilization across inpatient, professional, post-acute, and readmission services.
  • Episode Utilization Rates Report, which breaks down where patients receive care during and after an episode, such as skilled nursing facilities, home health, inpatient rehabilitation, or emergency department visits.
  • Readmissions Report, which allows members to explore readmission rates for patients by time interval and whether patients return to the index hospital or are readmitted elsewhere.
  • Comorbidities Report, which highlights common coexisting conditions among patients and supports a deeper understanding of patient complexity.
  • Payment by Condition Report, which compares case volume and utilization across conditions and helps contextualize sepsis relative to other medical episodes.

The presentation also included a review of sepsis-related Pay for Performance (P4P) reports available in the MVC registry including a Value Metric Summary Report and Value Metric Trends Report, which allow users to assess their current performance, improvement and achievement baselines and trends over time (Figures 1 and 2). Folk explained how these reports can help teams visualize progress relative to peer hospitals and MVC-wide averages.

Figure 1. MVC Data Registry Value Metric Summary – Blinded Report

MVC Data Registry Value Metric Summary table – Blinded Report

Figure 2. MVC Data Registry Value Metric Trends – Blinded Report

MVC Data Registry Value Metric Trends line graph – Blinded Report

Throughout the presentation, Folk additionally highlighted key registry features such as filtering by hospital type, payer, episode length, patient demographics, and episode time frame. She also reviewed case suppression thresholds and reminded participants that MVC’s data are risk adjusted, allowing for fairer comparisons across hospitals with differing patient populations.

Using Claims Data to Support Improvement

A recurring theme of the discussion was the importance of approaching the registry with curiosity. Participants were encouraged to consider the “five W’s” when reviewing their data and to use the available benchmarking opportunities to compare their hospital’s performance against similar hospitals to help identify realistic opportunities for improvement.

Polling during the session revealed that many participants had limited or no prior experience with an MVC registry review. Registry reviews are a dedicated opportunity for MVC staff to walk members through their site-specific data, focusing on the reports and metrics most relevant to their individual goals. These reviews can help teams move beyond high-level trends to more actionable questions about variation, utilization, and outcomes.

If you’re interested in setting up a time to complete a registry review, please email MVC.

Applying Custom Analytics to Sepsis Care

The workgroup concluded with a second presentation by MVC Analyst Janet Zhang, MPH, highlighting how custom analytic reports can be used to explore specific questions not fully addressed by standard registry reports. Using a recent example focused on sepsis patients and the impact of palliative care, Zang demonstrated how tailored analyses can provide deeper insight into care patterns, outcomes, and opportunities for improvement.

MVC encourages members interested in deeper analyses via custom report to submit a request through the Coordinating Center [Link].

MVC Sepsis Workgroup: Jan. 13, 2026

Health in Action Workgroup – Corewell Health Farmington Hills Hospital

MVC’s second workgroup of January featured Jennifer Hengy, BSN, RN, Internal Quality Improvement Specialist, Dr. Eugene Laveroni, Chief of Surgery, and Leslie Smith, RPh, JD, BCPS, BCIDP, Clinical Pharmacist Specialist from Corewell Health Farmington Hills. Together they showcased how a multidisciplinary team used data, evidence-based guidelines, and workflow redesign to drive meaningful improvements in patients’ safety by reducing SSIs in colorectal surgery.

SSIs remain a significant source of patient harm and financial penalty for hospitals nationwide. Despite advances in sterile technique and surgical technology, data from the Centers for Disease Control and Prevention (CDC) continue to show SSIs occur at alarming rates. As Hengy explained, their local data mirrored this challenge with an SSI rate of 9.6% in colorectal surgeries in 2023. This signaled an urgent need for targeted improvement. For Farmington Hills, this started with building the right team.

Building a Team

The initial improvement committee included surgical leadership, quality improvement specialists, pharmacy, nursing education, and anesthesia, with additional stakeholders added as new insights emerged. This diverse group ensured that clinical expertise, frontline workers, and data review were all represented throughout the project. Another key principle of the initiative was fostering a non-punitive culture. Chart reviews and peer discussion focused on learning and system improvement rather than individual blame, helping to sustain engagement across disciplines.

The Discovery Phase: Identifying Key Gaps

The discovery phase proved to be the most challenging but ultimately the most impactful, Hengy shared. The team conducted detailed chart reviews of SSI cases to better understand contributing factors, examining elements including:

  • Use of clean closing gloves, gowns, and closing packs
  • Skin preparation and closure techniques
  • Antibiotic selection, timing, and infusion duration
  • Documentation of infections present at the time of surgery (or PATOS)

Early interventions focused on education about documentation, standardized closing packs, and surgical techniques. While these steps led to modest improvements, they did not produce the level of change the team was seeking so they turned to the experts in antibiotics.

Optimizing Antibiotic Selection and Timing

A deeper dive into perioperative antibiotic practices at Farmington Hills revealed variability in both the antibiotics chosen and their infusion timing. The team identified frequent use of second-line antibiotics in patients with reported penicillin allergies, as well as inconsistencies ensuring antibiotics were fully infused prior to surgical incision.

Smith, a clinical pharmacist specializing in antimicrobial stewardship and a member of Corewell Health Farmington Hills’ SSI workgroup explained that cefazolin remains the preferred first-line prophylactic antibiotic for colorectal surgery and can be safely administered to most patients with reported penicillin allergies. Pharmacy-led education highlighted Cefazolin’s uniquely low risk of cross-reactivity and proven lower SSI rates compared to non-beta-lactam alternatives. Education was delivered through multiple channels, including surgical quality meetings, residents and provider training, newsletters, and real-time feedback to reinforce adherence to standardized protocols.

In addition, the team redesigned workflows to address infusion timing. New processes ensured that antibiotics requiring longer infusion times were started earlier in the preoperative phase. The use of visual job aids, memory tools, and Omnicell alerts reinforced these changes at the point of care (Figures 3 and 4).

Figure 3. Timing of Preoperative Antibiotic Infusion Flyer

Timing of Preoperative Antibiotic Infusion Flyer

Figure 4. Recommended Antibiotic Re-Dosing Interval Guideline Table for Patients Currently Receiving Antibiotics

Recommended Antibiotic Re-Dosing Interval Guideline Table for Patients Currently Receiving Antibiotics

Outcomes and Impact

Following implementation of these antibiotic-focused interventions and revised workflows, Corewell Health Farmington Hills observed a substantial reduction in colorectal SSIs with an infection ratio (SIR) of 0% between February 2024 and August 2024. In conclusion, the presenters emphasized that while zero harm is an aspirational goal, the consistency of guideline adherence and the sustainability of improved practices represented their major successes.

MVC Health in Action Workgroup: Jan. 29, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us via email or by submitting a presentation proposal using this form if you are interested in sharing your work.

Off
View Post
MVC Thanks Presenters from the Second Half of 2025

MVC Thanks Presenters from the Second Half of 2025

The MVC Coordinating Center wishes to express our deep appreciation for the 31 dedicated healthcare professionals who volunteered to present at MVC’s third and fourth quarter 2025 virtual workgroups, fall collaborative-wide meeting, and the Michigan Cardiac Rehabilitation network (MiCR) fall meeting. We know that MVC’s members and partners have many demands on their time from within their own organizations and beyond. Nonetheless, these 31 guest speakers shared their data, innovative approaches, best practices, and lessons learned with MVC members to support our shared goals of peer learning and high-value care delivery for all Michigan patients. We celebrate you for contributing in this important way, some at multiple events. You DO make a difference!

Join us in giving these folks a well-deserved round of applause:

Health in Action Workgroup

  • Amanda Escalera-Torres, RD, Program Director for Hurley Medical Center Food FARMacy Program
  • Leah Julian, BA, Innovation in Behavioral Health (IBH) Specialist, Michigan Department of Health and Human Services (MDHHS)
  • Lindsey Naeyaert, MPH, Service Delivery Transformation Section Manager, MDHHS

Post-Discharge Follow-Up Workgroup

  • Sara Hagerman, BSN, RN, Quality/Performance Improvement Specialist, University of Michigan Health - Sparrow Carson
  • Noa Kim, MSI, Informatics Design Lead, Healthy Behavior Optimization of Michigan (HBOM)
  • Larrea Young, MDes, Human-Centered Design Project Manager, HBOM

Preoperative Testing Workgroup

  • Amy Poindexter, BSN, RN, Performance Improvement Analyst, Holland Hospital
  • Kelly Lewton, RN, BSN, Performance Improvement Coordinator, Lake Huron Medical Center
  • Nicole Mott, MD, MSCR, Resident Physician and Post-Doctoral Fellow, University of Colorado & University of Michigan

Rural Health Workgroup

  • Lindsey Crouch, RN, Program Director, Hillsdale Community Health Center Mobile Health Clinic
  • Victoria Durr, BSN, RN, Infection Prevention Coordinator, Scheurer Health

Sepsis Workgroup

  • Errin Couck, RN, BSN, HMS Sepsis Abstractor, Henry Ford Health Macomb
  • Brandie DeVos, RN, MSN, Sepsis Coordinator, Henry Ford Health Macomb

Fall Collaborative-Wide Meeting Keynote Speaker

  • Gloria Rey, PA-C, MPH, Director of Post-Acute Care, Populance Henry Ford Health

Fall Collaborative-Wide Meeting Podium and Breakout Session Speakers

  • Brad Iott, PhD, MPH, Content Expert in Health Informatics and Social Care Integration, MSHIELD
  • Julia Weinert, MPH, Program Manager, MSHIELD
  • Amanda Biskner, RN, Paramedic, CP-C, Community Paramedicine Coordinator, Tri-Hospital EMS
  • Kelly Clark, MD, Faculty, Munson Family Medicine Residency Program and Clinical Assistant Professor, Department of Family Medicine at Michigan State University
  • Belinda Dokic, CPhT, BA, MBA, Clinically Integrated Network Program Manager, Trinity Health Livonia
  • Michael Gatt, MD, Gynecologist, Trinity Health Livonia
  • Holly Gould, MSN, CNM, RN, Director of Quality Improvement and Organizational Excellence, McLaren Port Huron
  • Nicole Luczak, President and CEO, United Way Bay County
  • Greg Scharf, BS, ACSM-CEP, AACVPR-CCRP, Cardiopulmonary Rehab System Manager, MyMichigan Medical Center - Midland

MiCR Fall In-Person Meeting Keynote Speaker

  • Stacey Greenway, MPH, MS, President of the American Association of Cardiovascular and Pulmonary Rehabilitation (AACVPR)

MiCR Fall In-Person Meeting Podium Speakers

  • Barry Franklin, PhD, Director (Emeritus), Preventive Cardiology and Cardiac Rehabilitation, Corewell Health East, William Beaumont University Hospital
  • Megan Gross, MPH, CHES, ACSMCEP, EIM, Clinical Exercise Physiologist, Holland Hospital
  • Cindy Haskin-Popp, MS, CEP Manager, Cardiology, Corewell Health East
  • Amy Poindexter, BS, CEP, Performance Improvement Analyst, Trinity Ann Arbor
  • Brett Reynolds, MPH, ACSM-CEP, Supervisor of Cardiology, Corewell Health East
  • David Running, BS, CEP, Supervisor-Cardiac Rehab, University of Michigan Health West
  • Amber Steele, ACSM-CEP, Cardiac Rehab Lead, McLaren Bay Region
  • Larrea Young, MDes, Human-Centered Design Project Manager, HBOM
thank you graphic

The MVC members and partners who attend MVC events appreciated these presenters, too. Here are just a few of the many glowing survey responses MVC received about presenters and their content in 2025.

presentation attendee testimonials

As a reminder, past workgroups and virtual networking event recordings can be viewed on MVC’s YouTube channel, and presentation slides and materials from MVC’s fall collaborative-wide meeting can be viewed here.

Do you have valuable information to share?

Whether you are new to presenting or a seasoned pro, the MVC Coordinating Center is here to support you every step of the way. From exploring topic ideas to preparing information and managing event logistics, our team makes the experience of presenting easy and comfortable. The P4P points you can earn as a presenter are a great benefit to your organization, too. For more information about presenting, contact the MVC Coordinating Center or submit a proposal here.
