Off
View Post
MVC’s Updated Common Conditions Report Now Available to Hospital Members

MVC’s Updated Common Conditions Report Now Available to Hospital Members

Earlier this month, the MVC Coordinating Center distributed a refreshed version of MVC’s common conditions report. This report delivered a comprehensive analysis of care episodes for six prevalent medical and surgical conditions frequently targeted for quality improvement initiatives within MVC hospitals. The included conditions were chronic obstructive pulmonary disease (COPD), congestive heart failure (CHF), coronary artery bypass graft (CABG), percutaneous coronary intervention (PCI), pneumonia, and sepsis. MVC generated hospital-level reports for 106 members, with tailored versions for general acute care hospital (GACH) and Critical Access Hospital (CAH) members.

Report pages focused on 30-day total episode payments, post-acute care utilization, readmission rates, and common reasons for readmissions. The report continued to highlight payments and outcomes for a two-year window, but the date range was updated to reflect claims from Jan. 1, 2024, through Dec. 31, 2025, for Blue Cross Blue Shield of Michigan (BCBSM)/Blue Care Network (BCN) Commercial, BCBSM/BCN Medicare Advantage (MA), and Michigan Medicaid; Medicare Fee-for Service (FFS) claims from the period of Jan. 1, 2024, through June 30, 2025, were used.

To ensure member reports had a sufficient sample from which to draw meaningful conclusions, MVC continued to apply case count inclusion criteria for the condition-specific pages. Previously, MVC required a site to have 11 episodes per year for both years to receive a condition-specific page; this year, condition-specific pages were included for all conditions with at least 20 episodes in the reporting period. This update expanded both the number of hospitals eligible for their report and report pages per hospital. For CAH members, MVC also expanded the reporting period for the CAH reports to Jan. 1, 2023, through Dec. 31, 2025, for all conditions.

The report began with a summary of patient population characteristics (Figure 1), comparing demographics, risk factors, readmission diagnoses, and comorbidities across each eligible cohort. The table was provided to help hospitals better understand the patient populations underlying the reporting for these six conditions/procedures.

Figure 1. Sample Blinded Table for a Hospital’s Patient Population Snapshot, Common Reasons for Readmission, and Frequent Comorbidities
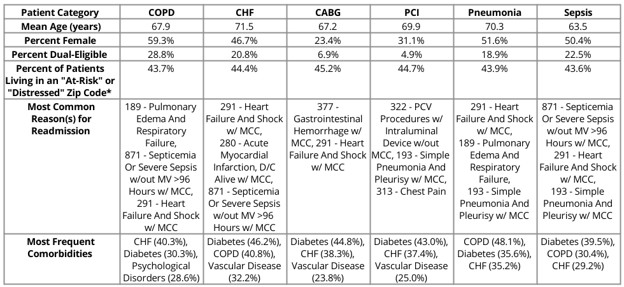
Comparison table summarizes demographics, risk factors, readmission diagnoses, and comorbidities across COPD, CHF, CABG, PCI, pneumonia, and sepsis patient categories. Mean age ranges from 63.5 years for sepsis to 71.5 for CHF; frequent readmission reasons include respiratory failure, heart failure or shock, gastrointestinal hemorrhage, myocardial infarction, and septicemia, while common comorbidities include CHF, diabetes, COPD, and chronic kidney disease.

The remainder of the report was comprised of condition-specific pages. MVC provided benchmarking figures for average 30-day risk-adjusted, price-standardized total episode payment and 30-day inpatient readmission rate for each condition. MVC price standardized total episode payments to Medicare FFS amounts so that comparisons could be made across hospitals and over time. Payments were risk-adjusted for patient age, gender, payer, comorbidities, and high or low prior healthcare utilization/payments. These figures showcased a given hospital’s position relative to all other eligible MVC hospitals in the collaborative and provided the average total episode payment within a hospital’s region and statewide.

Across the collaborative, CABG had the highest average total episode payment at $53,183 (Figure 2), followed by sepsis and CHF. The collaborative-wide average total episode payment for all conditions did not vary significantly between the 2025 report and the 2026 report. Readmissions were observed to be highest across the collaborative at 19.1% for patients hospitalized for CHF (Figure 3), followed by patients hospitalized for sepsis or COPD. Readmission rates were lowest across the collaborative at 5.4% among patients who underwent a PCI procedure.

Figure 2. Average 30-Day Risk-Adjusted, Price-Standardized Total Episode Payment Among Patients Hospitalized for CABG (Blinded Report)
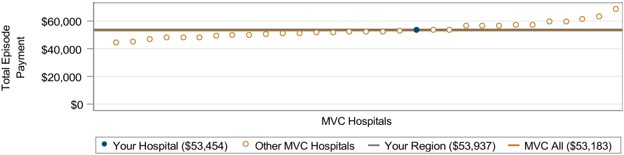
Caterpillar plot compares average 30-day risk-adjusted, price-standardized total episode payments for CABG patients across MVC hospitals. Orange circles show other hospitals trending upward from about $45,000 to $70,000, while markers identify Your Hospital at $53,454, Your Region at $53,937, and MVC All at $53,183.

Figure 3. 30-Day Readmission Rate Among Patients Hospitalized for CHF (Blinded Report)
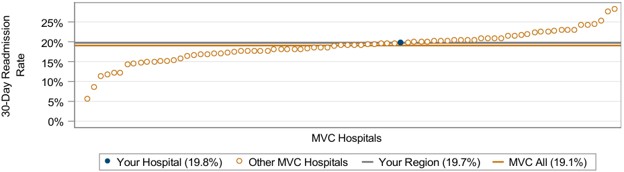
Caterpillar plot compares 30-day CHF readmission rates across MVC hospitals, with orange open circles rising from about 6% to 28%. Blue marker shows Your Hospital at 19.8%, while horizontal reference lines mark Your Region at 19.7% and MVC All at 19.1%.

The final figures on the condition-specific pages worked in tandem to display the utilization and cost components that made up a hospital’s average price-standardized, risk-adjusted post-acute care (PAC) payments in the 30 days following discharge. Most hospitals received a figure displaying the breakdown of 30-day risk-adjusted, price-standardized post-acute care payments by payer categories (Figure 4). All payer categories with at least 11 episodes during the reporting period were reflected, including a “Dual-Eligible” category representing patients eligible for both Medicare and Medicaid coverage; as such, Medicare and Medicaid categories did not include dual-eligible patients when that category was included. The post-acute care categories for both figures included home health care, skilled nursing facility (SNF) care, inpatient rehab, outpatient rehab, emergency department (ED) care, long-term acute care hospitals (LTACH), and outpatient services.

Figure 4. Breakdown by Payer of 30-Day Risk-Adjusted, Price-Standardized Total Post-Acute Care Payments Among Patients Who Had a CABG Procedure (Blinded Report)
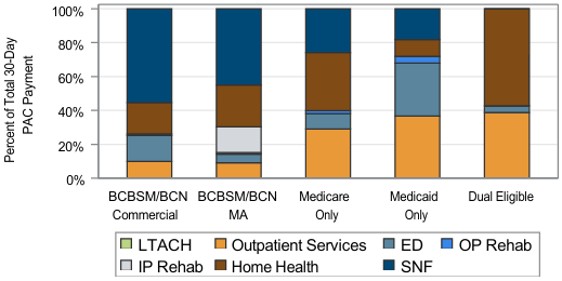
Stacked bar chart compares payer-specific shares of risk-adjusted, price-standardized 30-day post-acute care payments following CABG. Seven color-coded services show SNF dominating Commercial and Medicare Advantage payments, outpatient services prominent for Medicare Only, Medicaid Only, and Dual Eligible groups, and Home Health comprising most Dual Eligible payments.

Beyond offering insights into payments by payer and post-acute care category, this figure can offer additional insights and context when considered alongside Figure 5 showing post-acute care utilization rates. The two figures together served to provide a clearer understanding of the relationship between rates of utilization and percent of episode spending for each post-acute care category, illustrating whether spending aligns with utilization frequency. For example, payment categories with a high percentage of post-acute care payment in Figure 4 and a low overall utilization rate in Figure 5 may be indicative of low volume, high-cost outliers within a given condition at that hospital.

Figure 5. 30-Day Post-Acute Care Utilization Among Patients who had a CABG Procedure (Blinded Report)
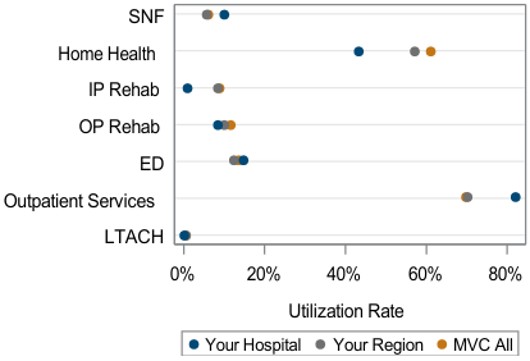
Dot plot compares 30-day post-acute care utilization after CABG across SNF, Home Health, IP Rehab, OP Rehab, ED, Outpatient Services, and LTACH. Blue, gray, and orange markers represent Your Hospital, Your Region, and MVC All; Outpatient Services shows highest utilization, while LTACH and IP Rehab remain near 0%.

MVC is dedicated to regularly updating its commons conditions report, aiming to equip collaborative partners with insightful data that can drive and reinforce meaningful advancements in healthcare quality. Please contact MVC with any questions or related analytic requests. If you require any digital accessibility accommodation, please let us know and we will be happy to provide alternative formats.

Off
View Post
MVC September Workgroup Highlights Sepsis Improvement Journey

MVC September Workgroup Highlights Sepsis Improvement Journey

In September, the Michigan Value Collaborative (MVC) hosted a sepsis workgroup featuring a presentation by McLaren Flint Hospital highlighting their sepsis improvement journey. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action. View the full 2027 MVC event calendar here.

Sepsis Workgroup: McLaren Flint Hospital

During this month’s sepsis workgroup, Kerri Tomasi-Herman, RN and Ali Arthur, BSN, RN, CCRN, Quality Improvement Specialist RNs at McLaren Flint, presented on the hospital’s work to strengthen sepsis processes over the past two years. Their presentation offered practical examples of how the team has used dashboards, daily auditing, nursing checklists, provider education, and interdisciplinary collaboration to address sepsis performance challenges.

McLaren Flint is a 378-bed hospital and Level III Trauma Center with high emergency department and inpatient volumes. Tomasi-Herman and Arthur began their presentation with a description of a significant transition in sepsis quality improvement beginning in 2025.

Previously, McLaren Flint relied on an on-site clinical abstractor and sepsis coordinator who reviewed sepsis patients, supported completion of the Centers for Medicare and Medicaid Services (CMS) sepsis bundle, and provided real-time assistance to nurses and providers. While they acknowledged this role as an important resource, the team recognized that relying heavily on one individual could mask underlying process issues.

In 2025, McLaren centralized sepsis abstraction across the hospital system. This shifted the role of the local quality improvement team toward real-time monitoring, intervention, feedback, and use of data to drive improvement.

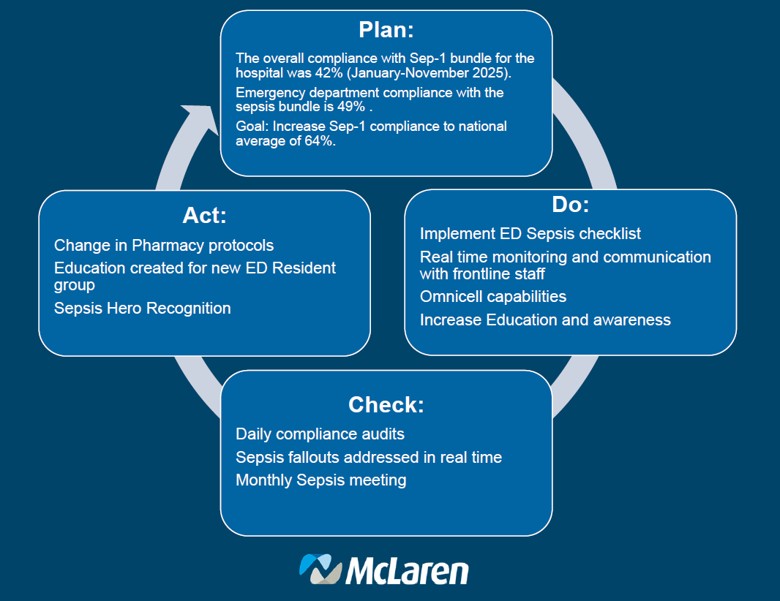
Figure 1. McLaren Flint’s PDCA Cycle Approach to Sepsis Improvement

Four-stage Plan, Do, Check, Act cycle diagram outlines a hospital sepsis-compliance improvement plan, using blue rounded boxes and gray circular arrows labeled Plan, Do, Check, and Act. Plan reports 42% Sep-1 bundle compliance, 49% emergency-department sepsis-bundle compliance, and a goal of reaching 64% national average; Do lists checklist implementation and monitoring, Check lists audits and monthly meetings, and Act lists pharmacy-protocol changes, resident education, and Sepsis Hero recognition.

Using Dashboard Data to Identify Opportunity for Improvement

Considering this shift towards real-time monitoring, a tool Tomasi-Herman and Arthur highlighted as key to their new workflow was the McLaren sepsis performance dashboard. The dashboard allows the quality team to see overall compliance as well as performance across different areas, including the emergency department (ED) and inpatient units.

The team uses this information during its monthly sepsis and quality improvement meetings across various clinical areas. Pareto charts help identify the most common causes of sepsis measure fallouts by service area to further pinpoint opportunities for improvement. This more detailed breakdown allows the team to tailor improvement strategies to specific departments and processes. For example, using this data they have found that within the ED, antibiotic administration most commonly contributes to sepsis fallouts, while for inpatient the most common issue is timely initial lactate orders.

The presenters emphasized that making this information visible to providers and hospital leaders has helped create greater awareness of performance and opportunities for improvement. McLaren Flint’s sepsis committee currently includes representatives from quality, medical staff, nursing, emergency medicine, intensive care unit, pharmacy and laboratory services with additional participants engaging when a specific fallout involves their department.

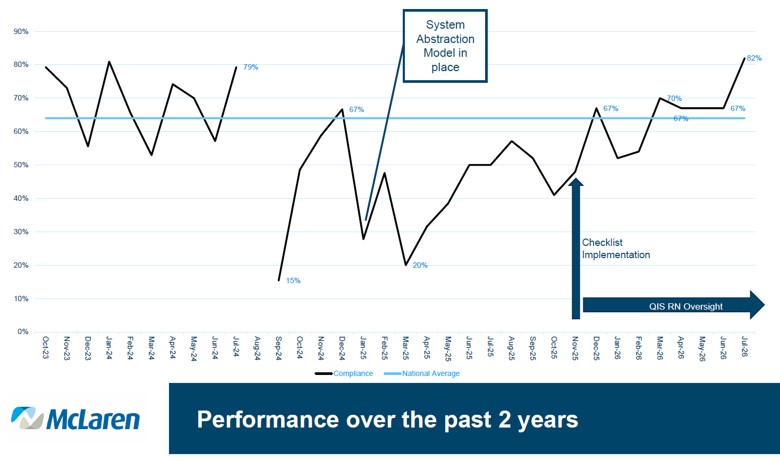
Figure 2. McLaren Flint’s Sepsis Performance Over the Past 2 Years

Line chart titled “Performance over past 2 years,” comparing compliance percentages against a 65% national average. Black compliance line fluctuates from 15% in Sept. 2024 to 82% in July 2026, indicating improvement since QI implementation. Callouts mark System Abstraction Model implementation in Jan. 2025 and Checklist Implementation and QIS RN Oversight in Nov. 2025.

Real-Time Monitoring Helps to Avoid Fallouts

Another major component of McLaren Flint’s approach is daily real-time monitoring. Each morning, the quality improvement team reviews their internal electronic medical record (EMR) sepsis worklist, which identifies patients meeting sepsis-related criteria. The team then follows patients in real time, monitoring whether appropriate orders for blood cultures, antibiotics and other elements of the bundle are completed.

When a potential delay is identified, the team provides real-time reminders to appropriate nurses and providers. They also review cases retrospectively and send follow-ups or documentation addendum requests when appropriate. This combination of real-time intervention and retrospective review allows the team to address individual cases while also identifying recurring process issues.

Reviewing individual fallout cases minute-by-minute offers the opportunity to determine whether the underlying issue was related to workflow, documentation, laboratory processes, or another factor. One example provided by the presenters involved antibiotic orders that were not being reviewed quickly enough by pharmacy. After identifying and bringing this item to the attention of the sepsis committee, the pharmacy department adjusted its process to prioritize validation of antibiotics associated with sepsis and infection-related orders. Since this process has changed, the turnaround time for medication validation has decreased to less than 10 minutes.

Introduction of ED Sepsis Checklist

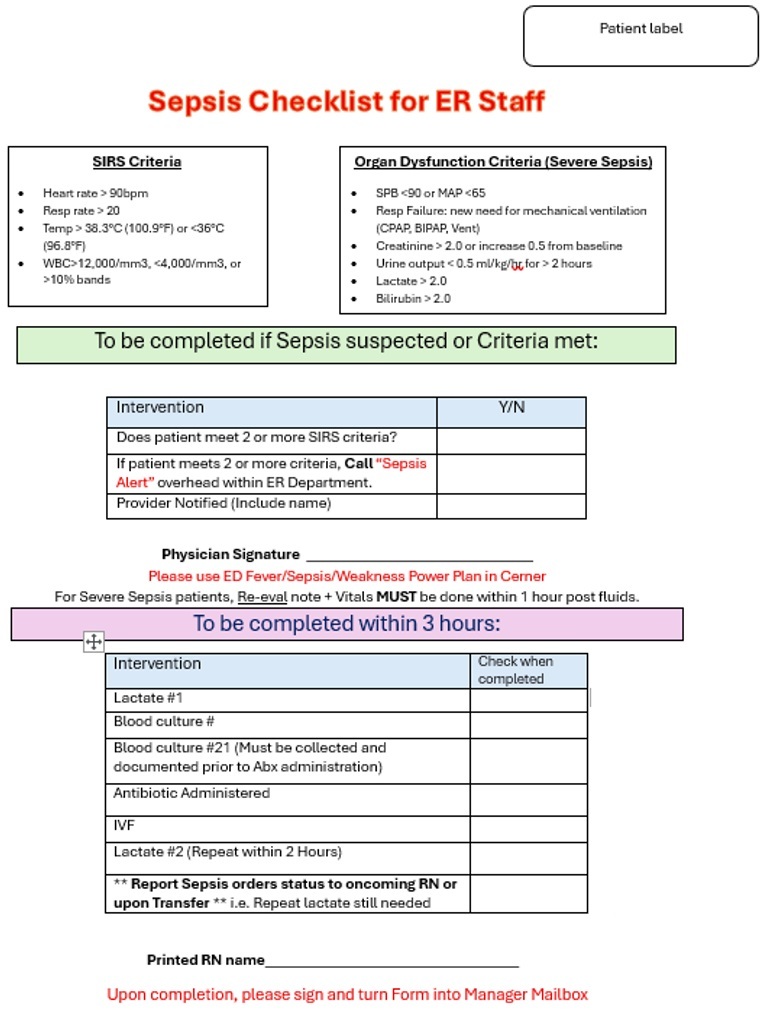
Because McLaren’s EMR system does not include a built-in sepsis nursing flowsheet or navigator, the team decided to design a paper-based tool. McLaren Flint implemented this sepsis checklist first within their ED. The checklist highlights systemic inflammatory response syndrome (SIRS). SIRS criteria checks for organ disfunction and is intended to prompt nurses to bring potential sepsis concerns to their physician as early as possible.

The checklist has gone through several revisions based on feedback from frontline staff. Together, they have worked to create a simplified tool that functions as a practical guide for nursing staff. These checklists are collected at the end of shifts and compared to patients identified through the EMR worklist to monitor utilization and compliance among staff.

Figure 3. McLaren Flint’s Sepsis Checklist for Emergency Room (ER) Staff

Clinical checklist form titled “Sepsis Checklist for ER Staff,” designed to screen suspected sepsis using SIRS and severe organ-dysfunction criteria. Red, green, blue, and purple sections organize patient labeling, SIRS thresholds, sepsis-alert instructions, physician signature, and three-hour interventions including lactate tests, blood cultures, antibiotics, and IV fluids.

Engagement of Frontline Staff

In addition to engaging frontline staff with the development of the sepsis checklist, McLaren Flint shared a creative strategy for building engagement: the Sepsis Hero Award.

This award was revived to recognize nurses and providers who demonstrate strong sepsis performance and engagement. A recent recipient was acknowledged for high checklist compliance, positive attitude, and having no sepsis fallouts.

This recognition has become a source of positive competition among ED staff, with team members becoming increasingly interested in being recognized for their contributions. This demonstrates the power recognition can have on complimenting data and education by making improvement efforts visible and celebrating frontline participation.

Looking Ahead to Continuous Improvement

Near the end of the workgroup, Tomasi-Herman and Arthur reflected that while McLaren Flint has made great progress, they continue to identify areas for improvement. One challenge they have identified is that their EMR-based automated sepsis alerts do not always align with CMS sepsis requirements, resulting in some false alerts. They have also identified limitations to their EMR configuration and opportunities to strengthen the recognition of sepsis patients receiving care on inpatient floors, particularly when a patient’s condition evolves after admission.

Looking ahead, McLaren Flint plans to continue educating ED staff, including their new medical resident program, promote standardized sepsis documentation, and monitor inpatient sepsis alerts.  The team is also working to recruit frontline nurses or providers to serve as sepsis champions and participate in monthly sepsis meetings, continuing to bring frontline perspectives into the hospital’s quality improvement work.

Key Takeaways for MVC Members:

McLaren Flint’s presentation offered several practical strategies that other hospitals may consider when aiming to strengthen their sepsis improvement efforts:

  1. User performance data to identify specific process opportunities – rather than relying solely on compliance rate
  2. Pair real time monitoring with retrospective review – to address potential gaps before they become measurable fallouts
  3. Create simple frontline tools – when EHR functionality does not fully support a desired workflow
  4. Celebrate staff contributions – through recognition and awards
  5. Bring multiple disciplines together – to identify and address system-level barriers
  6. Share performance transparently – with providers, managers, and clinical leaders to build awareness and accountability

MVC Sepsis Workgroup: Sept. 15, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to the Coordinating Center by email if you are interested in being a workgroup presenter or submit a presentation proposal here.

0
View Post
MVC July Workgroups Highlight Sepsis Discharge Planning in CAHs and MVC’s Follow-Up Push Report

MVC July Workgroups Highlight Sepsis Discharge Planning in CAHs and MVC’s Follow-Up Push Report

In July, the Michigan Value Collaborative (MVC) hosted two virtual workgroup presentations. The first, a rural health workgroup focused on MyMichigan Health’s system-wide sepsis discharge planning follow-up initiative implementation at critical access hospital (CAH) sites. The second, a post-discharge follow-up workgroup, provided a walk-through of MVC’s recent Follow-Up push report including recommendations on practical applications of the report to identify opportunities for improvement. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, sepsis, rural health, preoperative testing, and health in action.

Rural Health Workgroup: MyMichigan

During MVC’s first workgroup of July, Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Based Care for MyMichigan Health System, shared how their health system developed and implemented a standardized post-discharge follow-up process for patients hospitalized for sepsis. Recognizing the lasting physical and cognitive effects many sepsis patients experience after discharge, Pins-Schallip explained how this initiative was designed to target care transitions, reinforce discharge education, and connect patients with appropriate follow-up care across all MyMichigan Health hospitals. Pins-Schallip also explained how this initiative aimed to drive at both MVC and Michigan Hospital Medicine Safety Consortium (HMS) goals and found ways to benefit sites within the system not engaged with these CQI incentive programs.

Rather than developing separate workflows at each hospital, MyMichigan Health pursued a standardized, system-wide approach. This allowed hospitals of varying sizes, including rural and critical access facilities, to implement consistent practices while also leveraging shared resources. The first step of the initiative was identifying a reliable phone number to provide on discharge paperwork that would connect patients to “on call” Hospitalist providers. By utilizing the health system’s existing 24/7 Transfer Center phone number and nurses already staffing this communication center hub, this minimized the need for additional personnel while also providing patients with a reliable point of contact after leaving the hospital.

Figure 1. Process for 24/7 Transfer Center Calls

A text-based process list outlining steps for patient follow-up after sepsis diagnosis, including discharge, post-discharge questions, 24/7 bed placement call, messaging to hospitalist, and hospitalist follow-up. The list is presented with a MyMichigan Health University of Michigan Health footer in blue and yellow colors.

Pins-Schallip reviewed a selection of sepsis patient calls to the Transfer Center noting that the volume of calls since initiation of the program have been fewer than five. However, the time between a patient calling and resolution of their question is estimated to be on average less than one hour. To date, patient concerns primarily revolve around antibiotic prescription questions.

Throughout implementation, Pins-Schallip noted that the team emphasized collaboration across departments, including hospitalists, nursing, care management, information technology, and executive leadership. Strong physician engagement and support from MyMichigan’s chief medical officer were instrumental in successfully implementing standardized workflows across the health system. With a relatively recent “go live” for this program of July 2026, Pins-Schallip explained that regular feedback gathered from frontline staff and patient data will allow the team to continue to refine the process over time and adapt workflows based on operational experiences.

During the discussion portion of the workgroup, participants enquired about adapting the workflow for other patient populations, implementation at smaller or independent hospitals, and strategies for gaining physician buy-in. Pins-Schallip encouraged organizations to begin with existing resources whenever possible, noting that many hospitals already have personnel or infrastructure that can be leveraged for post-discharge outreach. The importance of executive sponsorship and continuous evaluation were also identified as key strategies to ensure new workflows remain sustainable and effective.

MVC Rural Health Workgroup: July 14, 2026

Post-Discharge Follow-Up Workgroup: MVC Coordinating Center

The second workgroup in July featured a walkthrough of MVC’s new Follow-Up push report, presented by Janet Zhang, MPH, MVC Data Analyst, and Rachel Folk, MHA, MVC Site Engagement Coordinator. Developed to support hospitals interested in further understanding opportunities for improvement, the report provides hospital- and system-level insights into post-discharge follow-up patterns for patients hospitalized with congestive heart failure (CHF), chronic obstructive pulmonary disease (COPD), pneumonia, and sepsis. The report evaluates patterns of follow-up completed within three, seven, and 14-days after discharge using claims data from Blue Cross Blue Shield of Michigan and the Centers for Medicare & Medicaid Services.

Figure 2. MVC Follow-Up Push Report Details

Report details slide presents data parameters for a 30-day inpatient episode analysis covering four MVC conditions: CHF, COPD, Pneumonia, and Sepsis, with payer data date ranges for BCBSM PPO, MA, BCN HMO, BCN HMO MA, Medicare FFS, and Medicaid. Outcome measures include follow-up rates at 3, 7, and 14 days post-index, excluding visits after readmission, inpatient procedures, emergency visits, skilled nursing admissions, or inpatient rehabilitation..

To begin, Zhang reviewed the design of the report outlining how hospitals can use the system-level report to identify variation in follow-up performance across hospitals within the same system. At the system level this report can help leaders recognize opportunities to share successful practices across sites. At the hospital level, the report provides additional context through patient demographic information, non-medical drivers of health, and analyses stratified by payer and follow-up status. Together, these visualizations help members identify where opportunities to optimize follow-up may exist and prioritize improvement efforts.

Next, using a blinded sample report, Folk demonstrated how members can translate their own report findings into actionable quality improvement opportunities. Using the sample blinded report as a template, the remainder of the presentation guided participants through the next steps to finding actionable insights including the identification of areas of opportunity. In this particular report, Folk identified the following areas of opportunity:

  1. Sepsis has the lowest overall follow-up rates at three, seven and 14-days after discharge.
  2. All conditions show lower rates of seven and 14-day follow-up for Medicaid FFS and Dual Eligible payers.
  3. COPD and sepsis patients that attend follow-up within 14-days after discharge have lower 30-day risk-adjusted, price-standardized total episode payments.

As a next step, Folk walked participants through samples of related goal setting and suggested action items for two priority metrics: COPD 7-day follow-up and sepsis 14-day follow-up.

Between COPD and sepsis, the evidence-based action items reviewed included:

  • Schedule follow-up appointments before discharge
  • Confirm medication and follow-up provider access prior to discharge
  • Referral placement for smoking cessation and rehab as indicated
  • Document and review medical care action plans
  • Connect high-risk patients to care management follow-up
  • Flag patients discharged to home without home health as high priority

As part of an interactive discussion, participants were asked to vote on the follow-up intervention they’d most likely implement to drive further discussion.

Figure 3. Screenshot of Follow-Up Intervention Interactive Discussion

Diagram of five color-coded sticky notes outlining steps to improve post-discharge patient care, including scheduling follow-ups, outreach workflows, discharge planning barriers, clinic coordination, and data analysis. Each note features check marks and symbols in various colors, highlighting high interest and key focus areas for high-risk patients and priority conditions.

Throughout the discussion, participants shared experiences and challenges related to improving post-discharge follow-up within their organizations. While several members identified building structured outreach workflows for high-risk patients and scheduling follow-up appointments before discharge as high-priority areas, others discussed practical barriers to these interventions including coordinating care with independent primary care practices, transportation challenges, and difficulty reaching patients by telephone after discharge. Participants also exchanged ideas such as utilizing nurses on light duty to conduct follow-up calls, incorporating virtual and remote monitoring for rural populations, and partnering with home health agencies to reinforce patient education.

The discussion also highlighted opportunities to maximize the value of MVC reports by combining claims data-based insights with internal quality dashboards and other collaborative initiatives. Members expressed continued interest in additional education on integrating MVC reports with other quality improvement efforts and using benchmarking data to communicate opportunities and progress with organizational leadership.

MVC Post-Discharge Follow-Up Workgroup: July 23, 2026

For MVC members seeking additional support related to claims data, please reach out to us by email. MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. If you are interested in being a workgroup presenter please submit a presentation proposal here.

Off
View Post
May Workgroup Highlights Building and Sustaining a Systemwide Sepsis Team

May Workgroup Highlights Building and Sustaining a Systemwide Sepsis Team

In May, the Michigan Value Collaborative (MVC) hosted a virtual sepsis workgroup featuring a presentation on the evolution of Michigan Medicine’s enterprise-wide sepsis initiative and the lessons learned while building a sustainable, multidisciplinary sepsis program. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Sepsis Workgroup – Michigan Medicine

Sepsis remains one of the leading drivers of mortality across healthcare systems, including Michigan Medicine. When sepsis can be treated, this not only reduces patient mortality, but also length of stay, readmissions, morbidities, and overall health of patients, so it comes as no surprise that Michigan Medicine recognized the need to make modifications to their current approach to sepsis management. Presenter Tami Garcia, MSN, RN, Sepsis Team Manager at Michigan Medicine explained how they began by moving away from siloed approaches to care. Early efforts focused on understanding existing workflows across Michigan Medicine’s enterprise and identifying inconsistencies in sepsis care. This included the recognition, escalation, and treatment of sepsis across adult, maternal, emergency and inpatient care settings.

While the team had a foundation set up with dashboards and procedural guides for screening, there had never been a team dedicated to ensuring consistent sepsis care across the system. Rather than immediately deploy new tools or mandates, this new team prioritized “Gemba walking” to meet providers where they work to better understand barriers, workflows, and frontline realities. As Garcia explained, “we need to build changes with our staff, not to our staff.” Garcia credited this approach to helping the sepsis team identify opportunities to standardize care while also building trust with bedside clinicians.

Building Trust as a Quality Improvement Strategy

A major theme throughout Garcia’s presentation was the importance of developing trust in quality improvement work. She emphasized that credibility and relationships became foundational to the success of this sepsis initiative. In addition to Gemba walking, the team focused on:

  • Maintaining a visible unit presence
  • Responding quickly to staff concerns
  • Closing communication loops
  • Listening to frontline staff frustrations
  • Incorporating clinician feedback into workflow design

Figure 1. Michigan Medicine’s Sepsis Team Standard Work and Governance Framework

Flowchart diagram illustrating sepsis coordinator rounding process and workflow reliability in a healthcare setting. It includes labeled boxes for standard work steps (Recognize, Huddle/escalate, Execute sepsis bundle), clear ownership by program team and units, and feedback loops showing stages of communication (What we heard, What changed, What we measured).

One notable outcome of this approach involved the reduction in excessive Epic alerts that historically contributed to alarm fatigue among nursing staff. Rather than dismissing the concerns, the team partnered with clinicians and informatics specialists to reduce unnecessary alerts and improve usability. This example is related to just one of the four main lessons learned by the sepsis team:

  1. Trust-building is a deliverable
  2. Tools must fit a workflow, otherwise they become workarounds
  3. Sustainment requires ownership
  4. Reducing burden (e.g., alarms) is improvement, not compromise

Standardizing Sepsis Recognition and Response

Following this period of learning and trust-building, the Michigan Medicine sepsis team began implementing a series of targeted interventions designed to improve reliability and timeliness of care.

Some key initiatives included:

  • Re-establishing multidisciplinary sepsis huddles in the adult emergency department
  • Enhancing Epic tools and workflows (adult, pediatric, etc.)
  • Launching maternal sepsis screening and nurse-initiated patient care orders
  • Implementing non-invasive fluid responsiveness technology in ICUs
  • Establishing nurse sepsis champions and physician ambassador programs
  • Creating neonatal sepsis response workflows in the NICU

Figure 2. Michigan Medicine’s ER Workflow and Sepsis Huddle Process Map

Flowchart illustrating ER workflow and Sepsis Huddle process for Michigan Medicine, detailing steps from initial sepsis screen to reassessment and monitoring. Key elements include color-coded boxes for tasks like RN paging for Sepsis Huddle, provider actions, and code sepsis activation, with timelines and criteria for bundle completion and reassessment.

Garcia highlighted the adult emergency department sepsis huddles as one of the team’s most impactful initiatives. The huddles bring nurses and providers together immediately after a positive sepsis screen to rapidly determine next steps and initiate treatment plans. This converts concern into coordinated action and normalizes escalation. Combined with streamlined order workflows and decision-support tools, timeliness of care and collaboration between disciplines have been improved.

Measurable Improvements in Sepsis Outcomes

Measurable improvements in both process and outcome measures since the formation of the dedicated sepsis team in 2022 were then reviewed. The reported improvements included:

  • Adult emergency department SEP-1 bundle compliance increased from approximately 50% in 2022 to almost 80% in 2026
  • Severe sepsis and septic shock mortality rates decreased from 26.2% in 2022 to 20.1% in 2025
  • Maternal sepsis screening rates exceeded 90% for OB triage and 78% for inpatient screens
  • Pediatric sepsis alert burden was reduced significantly from over 35,000 OPA’s in 2022 to just under 20,000 in 2025
  • Reduced the frequency of first antibiotic administration in neonatal populations at >120 minutes from over 40% to under 15% between the beginning and end of 2025

Garcia repeatedly credited frontline teams for these successes, emphasizing that sustained improvement depended on empowering all team members, especially clinicians, rather than relying solely on centralized oversight.

Expanding Frontline Ownership Through Sepsis Champions

One of the most promising developments discussed was the creation of the RN Sepsis Champion Program. Nurses serving as sepsis champions support local reliability, providing peer-to-peer education, reinforcing workflows, and helping to disseminate best practices within their units. Garcia described how this program has expanded rapidly across the Michigan Medicine organization and has already demonstrated improvements to bundle compliance and mortality outcomes in pilot units. Champions are especially important given high turnover rates and shifting operational pressures in healthcare. With monthly meetings, shared educational resources, and ongoing collaboration, champions help maintain momentum and create local ownership of sepsis improvement efforts.

Looking ahead, Michigan Medicine plans to sustain workflows, expand sepsis huddles, and strengthen support for sepsis champions and physician ambassadors. Garcia closed the presentation by reinforcing that successful sepsis improvement, or perhaps any quality improvement initiative, depends on partnership, humility, and continuous learning. As Garcia explained, “We really want to continue to partner with our teams to make sure they understand why we’re here, that they trust we’re here for the best of everybody -them and their patients.”

MVC Sepsis Workgroup: May 21, 2026

MVC welcomes presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members through various best-practice sharing platforms. Please reach out to us by email if you are interested in being a workgroup presenter or submit an online presentation proposal.

Off
View Post
January Workgroups Highlight Using Claims Data to Drive Sepsis QI and Reducing SSIs Through Multidisciplinary Collaboration

January Workgroups Highlight Using Claims Data to Drive Sepsis QI and Reducing SSIs Through Multidisciplinary Collaboration

In January, Michigan Value Collaborative (MVC) kicked off the 2026 workgroup calendar with a sepsis workgroup focused on helping members better understand how to use claims-based data to support sepsis quality improvement (QI) efforts. The session featured an overview of sepsis-related reporting available on the MVC registry followed by an example of how custom analytic reports can be used to dig deeper into areas of clinical interest. The second workgroup of the month, a health in action presentation, featured Corewell Health Farmington Hills Hospital’s multi-year QI initiative aimed at reducing surgical site infections (SSIs) in colorectal surgery. The MVC Coordinating Center hosts one to two workgroup presentations per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Sepsis Workgroup – MVC Coordinating Center

The workgroup opened with a presentation by MVC’s Site Engagement Coordinator Rachel Folk, MHA, who walked participants through the types of sepsis related data available in the MVC registry and how members can use these reports to support local QI initiatives. The presentation emphasized that MVC’s claims-based data registry allows members to examine sepsis episodes of care across multiple payers and care settings, providing a broader view of healthcare utilization and outcomes than many internal data sources alone.

Participants were introduced to several registry reports that are particularly relevant to sepsis analysis, including:

  • Episode Payments Report, which shows total, price-standardized payments for 30- or 90-day episodes and can be used as a proxy for assessments of utilization across inpatient, professional, post-acute, and readmission services.
  • Episode Utilization Rates Report, which breaks down where patients receive care during and after an episode, such as skilled nursing facilities, home health, inpatient rehabilitation, or emergency department visits.
  • Readmissions Report, which allows members to explore readmission rates for patients by time interval and whether patients return to the index hospital or are readmitted elsewhere.
  • Comorbidities Report, which highlights common coexisting conditions among patients and supports a deeper understanding of patient complexity.
  • Payment by Condition Report, which compares case volume and utilization across conditions and helps contextualize sepsis relative to other medical episodes.

The presentation also included a review of sepsis-related Pay for Performance (P4P) reports available in the MVC registry including a Value Metric Summary Report and Value Metric Trends Report, which allow users to assess their current performance, improvement and achievement baselines and trends over time (Figures 1 and 2). Folk explained how these reports can help teams visualize progress relative to peer hospitals and MVC-wide averages.

Figure 1. MVC Data Registry Value Metric Summary – Blinded Report

MVC Data Registry Value Metric Summary table – Blinded Report

Figure 2. MVC Data Registry Value Metric Trends – Blinded Report

MVC Data Registry Value Metric Trends line graph – Blinded Report

Throughout the presentation, Folk additionally highlighted key registry features such as filtering by hospital type, payer, episode length, patient demographics, and episode time frame. She also reviewed case suppression thresholds and reminded participants that MVC’s data are risk adjusted, allowing for fairer comparisons across hospitals with differing patient populations.

Using Claims Data to Support Improvement

A recurring theme of the discussion was the importance of approaching the registry with curiosity. Participants were encouraged to consider the “five W’s” when reviewing their data and to use the available benchmarking opportunities to compare their hospital’s performance against similar hospitals to help identify realistic opportunities for improvement.

Polling during the session revealed that many participants had limited or no prior experience with an MVC registry review. Registry reviews are a dedicated opportunity for MVC staff to walk members through their site-specific data, focusing on the reports and metrics most relevant to their individual goals. These reviews can help teams move beyond high-level trends to more actionable questions about variation, utilization, and outcomes.

If you’re interested in setting up a time to complete a registry review, please email MVC.

Applying Custom Analytics to Sepsis Care

The workgroup concluded with a second presentation by MVC Analyst Janet Zhang, MPH, highlighting how custom analytic reports can be used to explore specific questions not fully addressed by standard registry reports. Using a recent example focused on sepsis patients and the impact of palliative care, Zang demonstrated how tailored analyses can provide deeper insight into care patterns, outcomes, and opportunities for improvement.

MVC encourages members interested in deeper analyses via custom report to submit a request through the Coordinating Center [Link].

MVC Sepsis Workgroup: Jan. 13, 2026

Health in Action Workgroup – Corewell Health Farmington Hills Hospital

MVC’s second workgroup of January featured Jennifer Hengy, BSN, RN, Internal Quality Improvement Specialist, Dr. Eugene Laveroni, Chief of Surgery, and Leslie Smith, RPh, JD, BCPS, BCIDP, Clinical Pharmacist Specialist from Corewell Health Farmington Hills. Together they showcased how a multidisciplinary team used data, evidence-based guidelines, and workflow redesign to drive meaningful improvements in patients’ safety by reducing SSIs in colorectal surgery.

SSIs remain a significant source of patient harm and financial penalty for hospitals nationwide. Despite advances in sterile technique and surgical technology, data from the Centers for Disease Control and Prevention (CDC) continue to show SSIs occur at alarming rates. As Hengy explained, their local data mirrored this challenge with an SSI rate of 9.6% in colorectal surgeries in 2023. This signaled an urgent need for targeted improvement. For Farmington Hills, this started with building the right team.

Building a Team

The initial improvement committee included surgical leadership, quality improvement specialists, pharmacy, nursing education, and anesthesia, with additional stakeholders added as new insights emerged. This diverse group ensured that clinical expertise, frontline workers, and data review were all represented throughout the project. Another key principle of the initiative was fostering a non-punitive culture. Chart reviews and peer discussion focused on learning and system improvement rather than individual blame, helping to sustain engagement across disciplines.

The Discovery Phase: Identifying Key Gaps

The discovery phase proved to be the most challenging but ultimately the most impactful, Hengy shared. The team conducted detailed chart reviews of SSI cases to better understand contributing factors, examining elements including:

  • Use of clean closing gloves, gowns, and closing packs
  • Skin preparation and closure techniques
  • Antibiotic selection, timing, and infusion duration
  • Documentation of infections present at the time of surgery (or PATOS)

Early interventions focused on education about documentation, standardized closing packs, and surgical techniques. While these steps led to modest improvements, they did not produce the level of change the team was seeking so they turned to the experts in antibiotics.

Optimizing Antibiotic Selection and Timing

A deeper dive into perioperative antibiotic practices at Farmington Hills revealed variability in both the antibiotics chosen and their infusion timing. The team identified frequent use of second-line antibiotics in patients with reported penicillin allergies, as well as inconsistencies ensuring antibiotics were fully infused prior to surgical incision.

Smith, a clinical pharmacist specializing in antimicrobial stewardship and a member of Corewell Health Farmington Hills’ SSI workgroup explained that cefazolin remains the preferred first-line prophylactic antibiotic for colorectal surgery and can be safely administered to most patients with reported penicillin allergies. Pharmacy-led education highlighted Cefazolin’s uniquely low risk of cross-reactivity and proven lower SSI rates compared to non-beta-lactam alternatives. Education was delivered through multiple channels, including surgical quality meetings, residents and provider training, newsletters, and real-time feedback to reinforce adherence to standardized protocols.

In addition, the team redesigned workflows to address infusion timing. New processes ensured that antibiotics requiring longer infusion times were started earlier in the preoperative phase. The use of visual job aids, memory tools, and Omnicell alerts reinforced these changes at the point of care (Figures 3 and 4).

Figure 3. Timing of Preoperative Antibiotic Infusion Flyer

Timing of Preoperative Antibiotic Infusion Flyer

Figure 4. Recommended Antibiotic Re-Dosing Interval Guideline Table for Patients Currently Receiving Antibiotics

Recommended Antibiotic Re-Dosing Interval Guideline Table for Patients Currently Receiving Antibiotics

Outcomes and Impact

Following implementation of these antibiotic-focused interventions and revised workflows, Corewell Health Farmington Hills observed a substantial reduction in colorectal SSIs with an infection ratio (SIR) of 0% between February 2024 and August 2024. In conclusion, the presenters emphasized that while zero harm is an aspirational goal, the consistency of guideline adherence and the sustainability of improved practices represented their major successes.

MVC Health in Action Workgroup: Jan. 29, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us via email or by submitting a presentation proposal using this form if you are interested in sharing your work.

Off
View Post
September Workgroups Highlight Sepsis ED Triage Process and MVC’s Common Conditions and Procedures Report & Registry Review

September Workgroups Highlight Sepsis ED Triage Process and MVC’s Common Conditions and Procedures Report & Registry Review

In September, MVC hosted two virtual workgroup presentations – the first, a sepsis workgroup focused on Henry Ford Health Macomb’s efforts to build a structured emergency department (ED) triage process specifically for patients diagnosed with sepsis. The second, a health in action workgroup focused on the recent MVC Common Conditions and Procedures Report and included an overview of how to combine this push report with MVC registry data. The MVC Coordinating Center hosts workgroup presentations twice per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehab, rural health, preoperative testing and health in action.

Sepsis Workgroup September 9, 2025

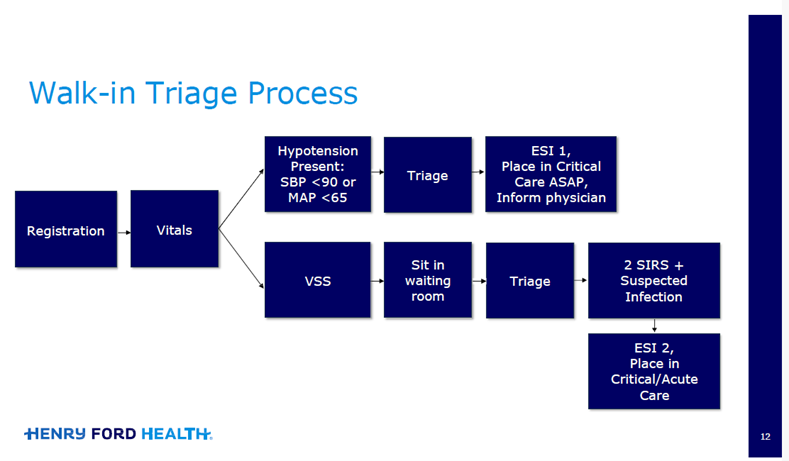
As Brandie DeVos, RN, MSN, Sepsis Coordinator explained at the beginning of the presentation, sepsis continues to challenge hospitals due to its time sensitive nature. Delays in recognition or treatment can lead to worse outcomes. Henry Ford Macomb Hospital’s ED sepsis team – composed of Michigan Hospital Medicine Safety Consortium (HMS) coordinators, internal sepsis program, and ED leadership – was established to combat just this issue. Their mission, to build a structured ED triage process, with specific attention to patients suspected of sepsis who present with abnormal vital signs to ensure the rapid identification, prioritization, and early intervention in suspected sepsis cases (Figure 1).

Co-presenters, DeVos and Errin Couck, BSN, RN, HMS Sepsis Coordinator, emphasized that having a consistent, structured triage process has helped to ensure cases of sepsis are not missed in the chaos of the ED. They recognized that prior to the initiation of a triage process directed at identifying sepsis, patients were being placed throughout the ED regardless of the presence of symptoms, vital signs indicating organ dysfunction, or indications of systemic inflammatory response syndrome (SIRS) criteria.

Figure 1. Walk-In Triage Process for Sepsis

walk-in triage process for sepsis flow chart

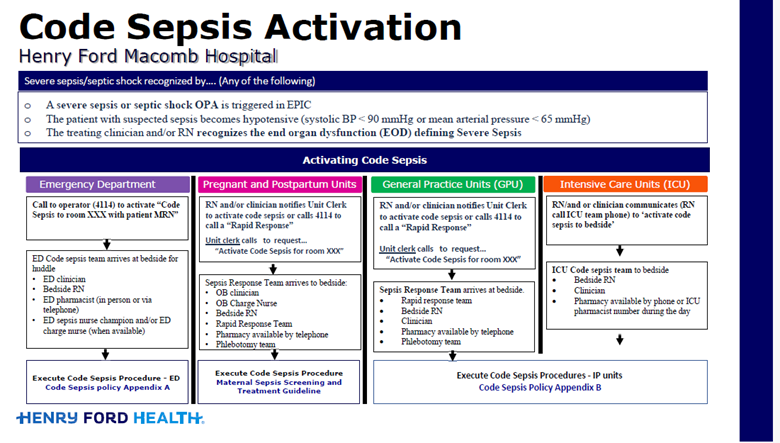
However, the triage system does more than mechanically screen vitals; it incorporates clinical judgement and risk indicators to prioritize patients with abnormal temperatures, elevated heart rate, hypotension, or altered mental status (Figure 2). The optimized identification of at-risk patients increases adherence to evidence-based sepsis bundle elements such as early labs, cultures, antibiotics, and fluid resuscitation within the defined time windows, a crucial step to improving performance in quality metrics.

Figure 2. Code Sepsis Activation Process

Henry Ford McComb Hospital Code Sepsis Activation flow chart

However, in practice, the sepsis program requires the support of a multidisciplinary team. DeVos and Couck note the most common roadblocks to this initiative were staff push back, untrained RNs in the triage area, and RN fatigue. They encourage aligning all stakeholders early and sustaining communication channels. They also noted great success with positive encouragement (i.e., celebrating the small wins), requiring triage RNs to have at least one year of ED experience, and routine triage RN rotations (every four hours).

Since initiating the new triage process, the presenters noted the following positive outcomes:

  • A 36% increase in antibiotics given within three hours of arrival for septic shock patients
  • For emergency medical services (EMS) patients, vital signs are obtained, triage completed, and patients roomed appropriately in an average of 12 minutes
  • 90% of lobby patients have vital signs obtained within 5-10 minutes
  • Overall, less patient triage complaints

The presenters ended the presentation by discussing a challenge they have experienced when attempting to expand their sepsis ED triage process to other sites within their own system. Hospitals differ – in size, resources, patient volume, and staffing. DeVos and Couck encouraged participants to pilot, learn, and iteratively refine their workflows locally.

This workgroup session served as both a practical guide and a rallying call – a structured ED triage for suspected sepsis should not be optional. It’s a critical defense against delays that cost lives.

MVC Sepsis Workgroup Sept. 9, 2025

Health in Action Workgroup September 25, 2025

The September health in action workgroup featured a presentation by MVC’s Site Engagement Coordinator Emily Bair, MS, MPH, RDN, CSP. The presentation focused on the recent MVC Common Conditions and Procedures Report and included an overview of how to utilize the MVC registry to compliment analyses included in this push report.

The Common Conditions and Procedures Report was developed as a structured data tool aimed at providing individualized, comprehensive, high-impact trends in commonly seen chronic conditions and a selection of procedures across participating hospitals. The most recent version of this report was shared with members in July. Two previous versions of the report were shared in 2024 and 2023.

Similar to previous iterations of the report, the most recent Common Conditions report included 30-day inpatient or surgical episodes created from two years of index admissions between January 2023 – December 2024. Exclusions included patients who had an inpatient hospital transfer, died in the hospital during their index hospitalization, or were discharged to hospice. Payors included Blue Care Network HMO Commercial and Medicare Advantage, Blue Cross Blue Shield of Michigan PPO Commercial and Medicare Advantage, Medicare Fee-for-Service, and Michigan Medicaid.

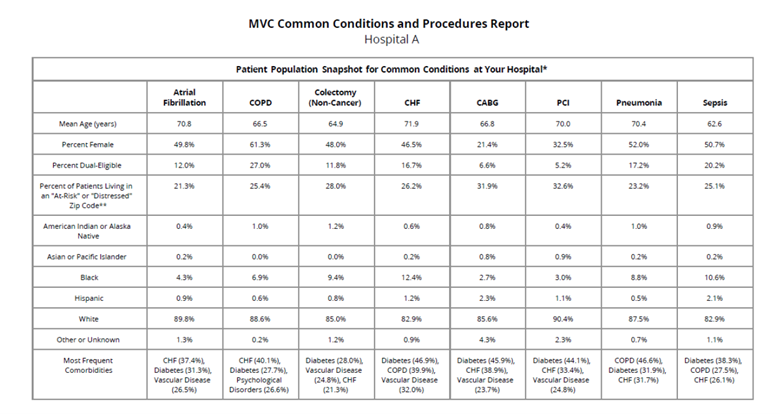
Within each report each site has an individualized patient population overview table that displays the patient population for each common condition (Figure 3). This table illustrates the distribution pattern of the population within each common condition but is not necessarily indicative of the distribution of patient demographics for the outcome of interest. In addition to age, gender, and race/ethnicity categories, the table includes zip code level data based on the Economic Innovation Group’s Distressed Communities Index (DCI) 2015-19, dual-eligible status, and common comorbidities.

Figure 3. Common Conditions Patient Population Snapshot for Hospital A (Blinded Data)

Common Conditions Patient Population Snapshot for Hospital A (Blinded Data) table

The report then features a variety of analyses for each condition/ procedure with an emphasis on:

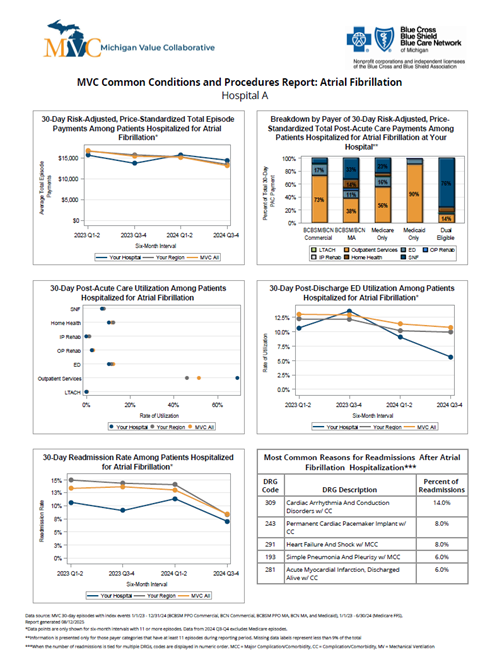
  1. Benchmarking: the report allows each hospital to see how it compares to peers on metrics like readmission rate, post-discharge care utilization, and episode cost
  2. Longitudinal trends: by presenting trends (6-month intervals) hospital leadership can detect historical problems or successes

Figure 4. Common Conditions Report Page for Atrial Fibrillation for Hospital A (Blinded Data)

Common Conditions Report Page for Atrial Fibrillation for Hospital A (Blinded Data): total of six charts and tables

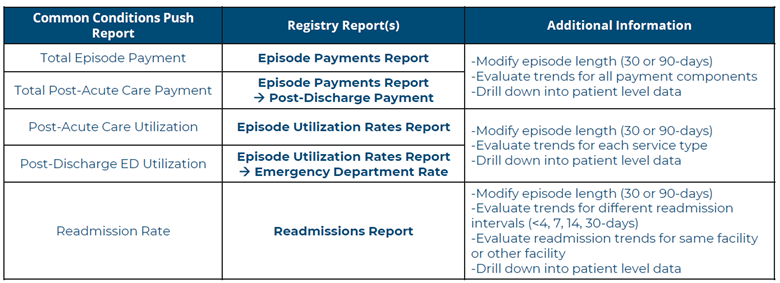
The design of this workgroup is part of MVC’s broader efforts to support hospitals not just with data, but with actionable insights and engagement strategies. As Bair points out, data alone isn’t enough – it’s the interpretation and follow-through that drives real change. Bair followed her review of the Common Conditions report with a walk-through of relevant online data registry reports (Figure 5).

Figure 5. Summary of Relevant Reports on MVC Data Registry

table: Summary of Relevant Reports on MVC Data Registry

In an effort to continue to support hospitals to move from simply viewing data to implementing quality improvements, Bair outlined a few key MVC engagement strategies:

  1. Outreach and coaching: MVC offers one-on-one coaching to support members with data interpretation and connections to peers
  2. Custom analytic report development: MVC may facilitate the development of deeper data analyses
  3. Peer learning and collaboration: MVC aims to catalyze dialogue across sites, encouraging sharing cross-hospital learning
  4. Iterative feedback: MVC welcomes feedback from members to support the evolution of data tools

MVC Health in Action Workgroup Sept. 25, 2025

Interested in access to the MVC data registry?

Ways to request registry access. Email: michigan-value-collaborative@med.umich.edu

Once a registry request is received, the MVC team will confirm your request with your specified site’s MVC Site Coordinator (primary contact). Once confirmed, you will be sent an MVC website confidentiality agreement (WCA), and upon receiving the completed WCA, MVC will provide you with a username and directions to login via email.

If you are interested in pursuing a healthcare quality improvement project, MVC has data specialists available to help you navigate our data resources and create custom analytics reports to support your efforts. Please reach out to us by email if you would like to learn more about MVC data or engagement offerings!

Off
View Post
July Workgroups Highlight Sepsis Compliance Process Improvements and Patient Satisfaction Excellence

July Workgroups Highlight Sepsis Compliance Process Improvements and Patient Satisfaction Excellence

In July, MVC hosted two virtual workgroup presentations – the first, a rural health workgroup focused on how a sepsis compliance initiative was developed and implemented in a critical access hospital setting. The second, a post-discharge follow-up workgroup, presented a small acute care hospital’s journey to patient satisfaction excellence. The MVC Coordinating Center hosts workgroup presentations twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehab, rural health, preoperative testing and health in action.

Rural Health Workgroup July 8, 2025

MVC hosted a rural health workgroup with a presentation by Victoria Durr, BSN, RN, Infection Prevention Coordinator from Scheurer Health. The presentation spotlighted a targeted sepsis compliance initiative and shared key strategies, lessons learned, and outcomes tailored to rural healthcare.

Meeting sepsis bundle compliance requirements set by the Centers for Medicare & Medicaid (CMS) is not only vital for reimbursement and regulatory alignment but also directly tied to improved patient mortality outcomes. As Durr explained, rural hospitals face unique challenges to improving sepsis compliance including agency coverage, fewer staff, and limited diagnostic tools.

As a part of her initial assessment of SEP-1 bundle compliance at Scheurer Health, Durr evaluated her staff’s understanding of the sepsis bundle components and found significant knowledge gaps. Other challenges faced by Schurer Health included limited space to admit directly from the emergency department (ED), an inconsistent sepsis census, and changing admitting privileges. These challenges contribute to downstream impacts to sepsis compliance including limited staff awareness and training, changes to lab orders, and transitions in continuity of care.

In July of 2024, Durr began working through each issue one-by-one with the help of department leadership. She outlined specific strategies Scheurer Health has used to improve compliance including:

  1. Implementation of structured training and process changes to standardize sepsis detection across emergency, inpatient, and inpatient care units
  2. Employed a team-based strategy, pairing clinicians and quality improvement leads to reinforce consistent sepsis protocols across inpatient workflows
  3. Leveraged data analytics to identify gaps and monitor compliance in real time

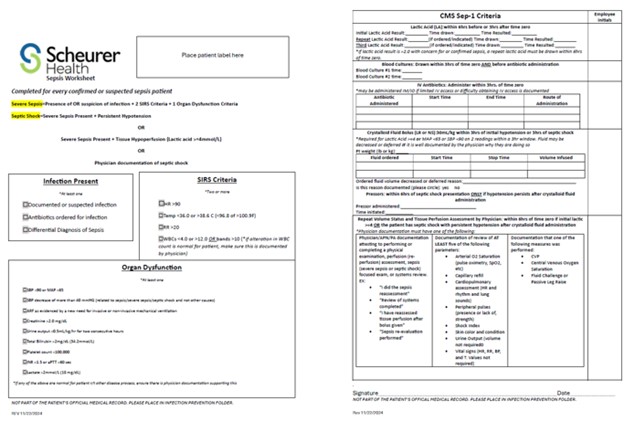
One key proactive tool Durr developed was a step-wise sepsis worksheet for nursing staff to follow in the case of a sepsis patient (see Figure 1, access PDF here). While this form is not required, in those cases when it has been utilized, Durr has found 100% SEP-1 compliance. A similar summary guide was created for physicians to optimize work flows (see PDF here).

Figure 1. Step-Wise Sepsis Worksheet for Nursing

Step-Wise Sepsis Worksheet for Nursing

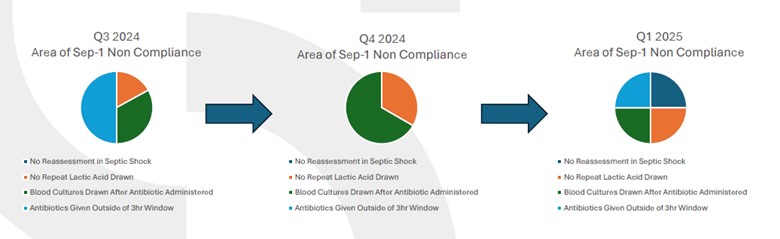
While Durr notes she has only evaluated data for sepsis cases dating back to July of 2024, she has seen a shift in the areas of SEP-1 non-compliance over time. Analysis revealed that some areas of non-compliance have improved while others have worsened (Figure 2). For example, between Q3 2024 and Q4 2024, non-compliance with antibiotic delivery within a three-hour window significantly declined, while non-compliance with blood cultures being drawn after antibiotic administration increased. However, by Q1 2025 when almost all the strategies outlined above had been implemented, the distribution of SEP-1 non-compliance areas became relatively even. Durr notes that real-time tracking has allowed her team to pinpoint manageable areas of improvement and inform their next steps.

Figure 2. Tracking Areas of SEP-1 Non-Compliance

Tracking Areas of SEP-1 Non-Compliance, Q3 2024 - Q1 2025

In the future, Durr notes Scheurer Health will continue to improve SEP-1 compliance through the implementation of a SEP-1 orientation with newly hired ED and acute care unit nurses, the creation of a standardized nurse handoff report, and continued tracking and team report outs on various metrics including length of stay (LOS), mortality, and sepsis related readmissions.

The workgroup presentation and follow-up discussion not only emphasized specific challenges to improving SEP-1 compliance at a rural health center but also offered solutions. Some of the solutions shared with attendees included recommendations to:

  1. Standardize workflows and checklists to build consistency across units
  2. Create on-demand education modules
  3. Utilize checklists available through the electronic medical records (EMR)
  4. Optimize nursing and physician champions
  5. Use data dashboards for real-time feedback

Rural Health Workgroup July 8, 2025 Recording

Post Discharge Follow Up Workgroup July 24, 2025

MVC’s second workgroup in July featured a presentation by Sara Hagerman BSN, RN, Quality Performance Improvement Specialist for University of Michigan Health-Sparrow at the Clinton, Carson, and Lansing sites. The presentation outlined the various pathways UMH Sparrow Carson has taken to improve their Hospital Consumer Assessment of Healthcare Providers and Systems survey (HCAHPS) scores.

HCAHPS is a tool developed by CMS that measures patient satisfaction. The survey consists of 27 questions that measure different aspects of patient care, including communication with providers, hospital environment, medication management, transitions from hospital to home care, and discharge planning. The survey is administered at various points throughout a patient’s stay, and results are used to compare hospitals on a national level.

Hagerman explains that starting about one year ago, the University of Michigan Health-Sparrow Carson devised a plan to not only improve HCAHPS scores but also to decrease readmissions. To do this, they focused on three primary areas:

  1. Evaluation of social determinates of health (SDoH)
  2. Individualized discharge planning
  3. Care facilitator follow-up

After collecting SDoH metrics in the Electronic Health Record (EHR) for about a year, the team aggregated this data to determine the greatest needs within their patient population. They also specifically looked for corresponding readmission cases to determine if readmissions were contributed to by social needs. Hagerman notes they found food insecurity (3.9%), housing instability (4.2%), and transportation needs (3.9%) to be the most common social factors impacting their community.

Transitioning from a micro to a macro-level, University of Michigan Health-Sparrow Carson senior executives next worked with their community partners to support improved transportation and food assistance resources at the local level. They collaborated with local programs to identify new resources for transportation and food assistance and developed pathways to connect patients directly with these resources prior to discharge.

With these resources in place, the team turned to tailoring individualized patient discharge plans. At UMH Sparrow Carson, nearly 90% of patients discharged have a scheduled follow-up appointment with their primary care provider (PCP) prior to leaving the hospital. And for those without a confirmed PCP, teams set a goal to follow-up within 3-7 days or less. Other components of the individualized discharge plans include:

  • Review of SDoH screening and arrangement for appropriate support services
  • Review of home care instructions, medications, and patient education
  • Post-discharge contact information and call-back within 72 hours

Lastly, Hagerman described the third component of their program triad: care facilitators. Care facilitators are nurses embedded in primary care offices whose primary goal is to identify and support chronically ill patients. They can support care transitions, medication management, patient education, and enhance overall experience. Care facilitators can also enroll patients in UMH Sparrow’s Chronic Care Management Program.

Benefits to enrollment in the Chronic Care Management Program include improved care coordination, increased patient engagement, and reduced hospitalizations. Hagerman points to a readmission rate of 5.9% thus far in 2025, compared to a readmission rate in 2024 of 6.95% as evidence of the positive impact this program has had. However, Hagerman notes there are limitations to the availability of this program to patients due to the cost of patient copays.

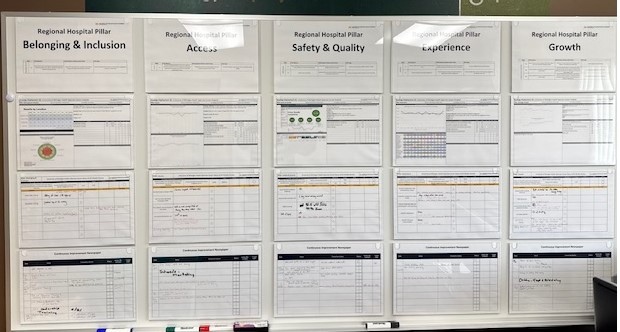
When it comes to improving HCAHPS scores, Hagerman noted that perhaps the most important lesson learned in this process has been to ensure team members are aware of the content of HCAHPS surveys. “It’s important to understand what patients will be asked about in order to better address potential issues up front”, noted Hagerman and she’s encouraged her team to become more knowledgeable about the survey. Additionally, engaging an interdisciplinary team and sharing data is especially useful to ensure communication and continued progress. The UMH Sparrow Carson leadership team meets in person at their strategy huddle board every other week to discuss progress and next steps (Figure 3).

Figure 3. Tier 2 Strategy Huddle Board

UMH Sparrow Carson leadership team strategy huddle board

Post Discharge Follow Up Workgroup July 24, 2025 Recording

MVC’s July workgroups specifically highlighted successful quality initiatives at small rural and acute care hospitals in Michigan. Their insights provide a basic understanding of the unique struggles these hospitals face to implement and maintain quality improvement.

MVC welcomes workgroup presenters from across Michigan to share their expertise, successes, initiatives and solution-focused ideas with fellow MVC members. Interested in presenting? Please reach out to us by email or submit a presentation proposal here.

Off
View Post
May Workgroups Highlight Sepsis Predictive Models and Post-Surgical Early Ambulation

May Workgroups Highlight Sepsis Predictive Models and Post-Surgical Early Ambulation

In May, MVC hosted two virtual workgroup presentations – the first, a sepsis workgroup focused on Covenant Health’s strategies and successes in improving sepsis bundle compliance under Centers for Medicare and Medicaid Services (CMS) reporting standards. The second, a health in action workgroup, focused on Michigan Medicine’s efforts to advance post-surgical recovery through early ambulation with the help of care path and command center supported real-time notifications. The MVC Coordinating Center hosts workgroup presentations twice per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehab, rural health, preoperative testing, and health in action.

Sepsis Workgroup May 13, 2025

Improving CMS sepsis compliance is a national priority; hospitals that succeed not only avoid penalties but – more importantly – save patient lives. In her presentation, Amy Lorenz, RN, BAS, MPA, Lead QI Specialist and Sepsis Team Leader for Covenant Healthcare pointed out that a CMS compliance score review in January 2021 of just 64% predicated their site’s interest in pursuing methods to improve sepsis compliance.

To start, Covenant Healthcare reviewed the number of sepsis Best Practices Advisory (BPA) alerts (or OurPractice Advisory or OPAs) firing in the background of their Electronic Medical Records (EMR) based on Modified Systemic Inflammatory Response Syndrome (SIRS) Criteria. The numerous alerts lead to interruptions in workflow, alert fatigue, and frustration.

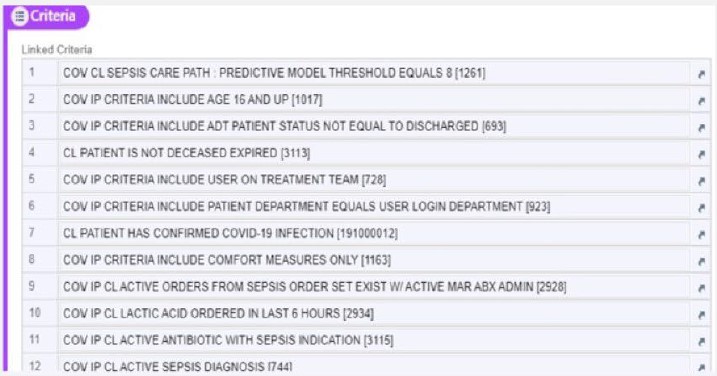
With the help of their EMR and IT teams, Covenant Health decided to research and validate the use of a predictive model available through EPIC called BPA Level 8. The predictive model is a ruled based, logical scoring system that relies on various criteria such as patient medication orders, lab values, age, and comorbidities to assess the risk of sepsis development for any patient. The predictive model also incorporates non-specific SIRS criteria and additional exclusion criteria (Figure 1).

Figure 1. Covenant Healthcare Base Sepsis Care Path Level 8 Criterion for Exclusion

Covenant Healthcare Base Sepsis Care Path Level 8 Criterion for Exclusion

With the replacement of the SIRS Criteria with the Predictive Model in Q3 of 2023, Covenant Health saw the number of interruptive alerts drop from 90-100,000 to just 30,000 per month in 2024. Lorenz notes that this reduction in interruptive alerts alone was a relief to staff. However, they have additionally seen other positive outcomes including:

  • A climbing RN action rate (10% to 24.5%),
  • An increase in accuracy in sepsis diagnosis (9-18% to 50-60%), and
  • A reduction in the number of sepsis flags missed by the model (only 1-2 per month)

These outcomes together suggest that in addition to reducing inefficient alerts, patients are increasingly receiving optimal and appropriate care. Additional outcomes of this initiative highlighted in the presentation included the development of a linked automatic blood culture and/or lactate level order set within the EMR. Additionally, with support from medical leadership, this order set can now be approved by RNs eliminating a common stopgap in care.

A multidisciplinary approach with regular staff feedback, education, and leadership support further drove engagement and compliance of staff. Another Covenant Healthcare team member on the call, Beth Turnbull, Lead Senior EMR Applications Analyst pointed out that nursing leadership was involved in the implementation of this predictive model from the beginning. Nursing also engaged in evaluating data dashboards, routine compliance audits, and collaborative huddles to monitor sepsis bundle adherence and maintain accountability.

While Covenant Healthcare’s predictive model is specific to their EMR program EPIC, attendees noted that there are other predictive model options available. Ultimately, the key takeaways from this presentation used to improve sepsis bundle compliance include:

  1. Identify and analyze fall outs: to prioritize and target education
  2. Deploy an easy-to-access knowledge base to support clinical decision-making: by creating a one-page resource or visual dashboards
  3. Promote transparency: by increasing access to real-time data and routine collaborative huddles to help keep teams accountable
  4. Secure leadership backing: but also empower front-line workers to make quality efforts stick
  5. Measure and validate interventions: based on data and compliance trends

Health in Action Workgroup May 29, 2025

The health in action workgroup featured a joint presentation by Heidi O’Neill, MS, Project Manager Lead; Mary Nowlin, PA-C; and Niki Farquhar, MSE, Project Management Lead from Michigan Medicine. Their presentation centered on the power of interdisciplinary collaboration, data-driven processes, and scalable strategies to embed post-surgical real-time notifications for delayed post-operative ambulation into Michigan Medicine’s post-surgical clinical pathways.

In 2019, Michigan Medicine started a multidisciplinary quality initiative supporting teams across the site to improve outcomes called Advancing Care, Treatment Efficiency, Innovation, Value and Teamwork for Surgical Episodes (or ACTIVATE). O’Neill explained that ACTIVATE places emphasis on teamwork, innovation, and communication to drive patient experience and outcomes. By focusing on units/ services with high observed/expected (O/E) length of stay (LOS >1.0), high surgical volume, and positive leadership engagement; the ACTIVATE team ensured that each unit they invested in had room to improve and support to achieve their goals.

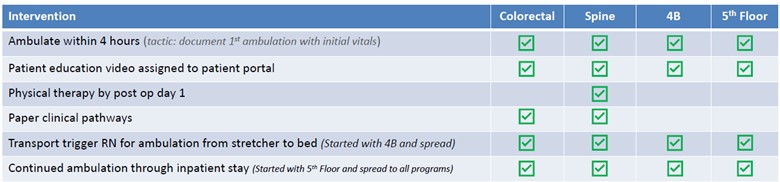
Post-surgical early ambulation, or getting patients up and walking as soon as possible after surgery, has been shown to decrease the length of hospital stay. Common ACTIVATE interventions to promote early ambulation include patient education videos, transport triggers for ambulation from stretcher to bed, documentation of ambulation within four hours, and the development of detailed clinical pathways (see Figure 2).

Figure 2. Common ACTIVATE Interventions to Promote Post-Surgical Early Ambulation

Table: Common ACTIVATE Interventions to Promote Post-Surgical Early Ambulation

Additionally, Nowlin explained that as the ACTIVATE team spread their interventions across various services, from colorectal to spine then to more general surgical units (4B and the 5th floor) they noticed that there wasn’t a consistent order set for early or sustained ambulation. To ensure consistent documentation, the ACTIVATE team developed an early ambulation order set to be used across all units and started tracking their impact.

ACTIVATE’s efforts to outline post-surgical clinical pathways and optimization of documentation of ambulation eventually led to their collaboration with Michigan Medicine’s Capacity Operations Real Time Engagement Center (or M2C2), launched in November 2022. M2C2 is a state-of-the-art command center designed to act as the hub for Michigan Medicine operations and innovation by leveraging real-time visualization of patient milestone achievement based on EPIC data. Their goal is to not only improve LOS but to ultimately increase the percentage of patients who achieve post-surgical milestones (e.g., early ambulation) in a timely manner. Farquhar explained, M2C2’s integration of care paths and responsive actions when patients deviate from their expected progression are paving the way to reduced LOS, safe discharge, and increased bed capacity.

Figure 3. M2C2 Post-Surgical Procedure Care Path Framework

M2C2 Post-Surgical Procedure Care Path Framework

To develop the post-surgical care path framework (Figure 3), Nowlin and Farquhar met with other key stakeholders to ensure that ACTIVATE and M2C2 efforts to optimally progress patients through the early ambulation node of the post-surgical path were synced. Understanding the goal ACTIVATE had previously set for ambulation within four hours of exiting the OR, M2C2 set alerts for patients that had no documented ambulation by three hours post-surgery to allow for a one-hour intervention window. During this period, M2C2 clinical expeditors (CEs) conduct a patient chart review and then contact the nurse and medical provider to discuss barriers to ambulation.

Within the first quarter of the new M2C2 alert for ambulation going live, nearly 1280 alerts were logged: 559 resulting in contact with the care team to assess barriers to ambulation. When compared to baseline data, a 23.1% decrease in median time to first ambulation was observed for ICU post op patients. For non-ICU post-op patients, a 7.1% decrease was observed. Additionally, a 0.34 day decrease in average LOS was observed. These results indicate opportunities for enhanced patient recovery, shorter LOS, and better overall patient outcomes.

Lastly, Farquhar outlined opportunities to continue to progress with early ambulation including:

  1. Refine exclusions for patients that are not appropriate for early ambulation
  2. Improve visibility of ambulation status and timeline in EPIC
  3. Explore improved capture of ambulation in clinical notes
  4. Enhance alert communication to support nursing
  5. Continue to work on nurse-to-nurse APS consult orders for pain management control

MVC’s May workgroups exemplify efforts from two different sites to place value on interdisciplinary teams, the importance of data visibility, and alignment across clinical, operational, and administrative units to ensure optimal quality improvement.

If you are interested in pursuing a healthcare improvement program, MVC has data specialists available to help navigate and create custom analytics reports. Please reach out to us by email if you would like to learn more about MVC data or engagement offerings!

Off
View Post
MVC Virtual Networking Event: Collaborative Learning in Post-Discharge Follow-up for Sepsis Patients

MVC Virtual Networking Event: Collaborative Learning in Post-Discharge Follow-up for Sepsis Patients

On April 16, 2025, MVC hosted a virtual networking event providing members with an opportunity to make professional connections and discuss strategies for improving post-discharge follow-up for sepsis patients. Forty-six MVC members from thirty-three hospitals and seven health systems participated in the ninety-minute event. 

The event kicked off with an ice breaker activity (Figure 1) and an interactive quiz on common sepsis patient demographics, symptoms, and discharge care best practices.  

Figure 1. Best Ways to Prepare a Sepsis Patient for Discharge Poll

Best Ways to Prepare a Sepsis Patient for Discharge open poll

Prior to starting the breakout discussion groups, MVC’s Engagement Manager, Jessica Souva, MSN, RN, C-ONQS presented unblinded hospital-level 14-day follow-up after sepsis rates for 30-day inpatient episodes from July 1, 2023, to June 30, 2024. 

The breakout discussions were structured to engage attendees in conversations about challenges and strategies to addressing barriers in patient follow-up after sepsis. This goal was accomplished by providing groups with specific scenarios and types of approaches to improve follow-up after discharge for sepsis patients (Figure 2).

Figure 2. Challenges and Strategies to Address Barriers in Patient Follow-Up After Sepsis

Challenges and Strategies to Address Barriers in Patient Follow-Up After Sepsis

What challenges are MVC members facing related to follow-up after discharge for sepsis patients? 

MVC members reported that sepsis patients often face challenges in scheduling follow-up appointments, not knowing when to contact their provider for early warning signs and being readmitted before their scheduled post-discharge follow-up appointments. Contributing factors include lack of provider ability, incomplete patient or family education, and sub-optimal discharge dispositions.  

What are MVC members doing to improve their rates of follow-up after discharge for sepsis patients?  

During the breakout discussions, attendees shared that they are addressing the identified challenges through a multifaceted approach focusing on patient education, communication, resource access, team collaboration, and data evaluation. 

Patient Education and Empowerment 

  1. Discharge Paperwork: Include a phone number for patients to call with questions or concerns and to schedule follow-up appointments. This allows patients to seek follow-up care sooner. 
  2. Family Involvement: Educate and involve family members to facilitate follow-up care by ensuring they understand the importance. 
  3. Empowering Survivor Stories: Share stories from patient survivors through interviews, surveys, or patient advisory councils. These stories can be used to educate current patients, their families, and providers. 

Communication and Coordination 

  1. Care Coordinator/Nurse Navigator: Assign a care coordinator or nurse navigator as the point of contact post-discharge. Care Coordinators and Nurse Navigators can help patients understand factors influencing readmission and how to mitigate these factors. 
  2. Continuous Communication: Maintain open communication between inpatient and outpatient case managers regarding transitions of care. 
  3. “Call Back Crew”: Build a team to follow up with patients, reinforce education, and use call centers to identify trends and improve follow-up processes. 

Resource Access 

  1. Scheduling Follow-Up Appointments: When possible, schedule follow-up appointments before discharge. 
  2. Discharge Clinics: Block time for a dedicated provider to staff a clinic for patients who do not have or are unable to get an appointment with their PCP. This type of clinic can reduce return ED visits and readmissions by providing support, education, and resources. 
  3. Educate Staff About Under-utilized Resources: Local Area Agencies on Aging can facilitate access to free or low-cost services to improve the home setting for patients aged 65+. Many insurance providers, like Medicare Advantage/BCBSM provide additional support post-discharge with designated case managers.  

Team Collaboration and Internal Processes 

  1. Multi-Disciplinary Approach: Include care management and various therapies to support patient recovery. Ensure all patients receive a physical and occupational therapy evaluation to screen basic functional needs before discharge and determine the best future care setting. 
  2. Unified Team Message: Ensure therapy, physician, and care management teams provide a unified message to patients. 
  3. Improve Team Reliability and Training: Build internal trust and, consequently, patient trust. Provide physicians with training on how to conduct difficult discussions with patients and their families, ensuring patients understand their situation and the benefits of alternative approaches when recommended by medical professionals. 

Data and Evaluation 

  1. Patient Interviews and Surveys: Include a readmission nurse on the patient care team to interview readmitted patients and learn from their experiences.  The readmission nurse can act as a liaison between quality and hospital care teams, highlighting patients needing special attention and collecting feedback. 
  2. Retrospective Review: Complete a retrospective review of the patient’s journey to identify improvements needed in education and communication upon readmission for the same reason. 
  3. Care Transition Programs: Add sepsis patients to Care Transition Programs to trigger alerts for retrospective review of readmission cases and to identify improvement areas. 

What are members saying about the MVC April Virtual Networking Event? 

  • “Very fun and informational event. I like the smaller break out sessions to foster meaningful conversation and then bringing the ideas of the smaller groups to the entire group.” 
  • “Very well organized. I loved the interactive piece.” 
  • “I enjoyed the pre-break out group survey/quiz questions to help with engagement…it is less intimidating to speak up in the smaller groups than when everyone is in on large group.” 
  • “I enjoyed the networking aspect of this event and look forward to others in the near future. MVC Site Engagement Coordinators did a wonderful job facilitating this event and engaging the participants.” 
  • “It was reassuring to hear that many of the hospitals across the state are having the same issues and working on similar projects. It gave me a sense that my own hospital is on the right path.” 

MVC looks forward to hosting more virtual networking events throughout the year to increase collaboration and connection with MVC’s members. If your hospital or organization has a networking topic they would like to share, please email us. We would love to hear from you.   

Off
View Post
January Workgroups Highlight System-Level Sepsis Efforts and Community Paramedicine

January Workgroups Highlight System-Level Sepsis Efforts and Community Paramedicine

In January, MVC hosted two virtual workgroup presentations – the first a sepsis workgroup focused on the development of a system-level sepsis improvement plan, and a health in action workgroup focused on the implementation of a community paramedicine program. MVC hosts two virtual workgroups per month with topics rotating between post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and heath in action (ad hoc focused topics). Each month, the MVC Coordinating Center publishes key highlights from the past month’s presentations to support resources and best practice sharing across the state.

Sepsis Workgroup January 14, 2025

On Jan. 14, MVC hosted its first sepsis workgroup of 2025 with a presentation on Munson Healthcare’s system-level sepsis improvement plan. Munson representatives who contributed to the presentation included Alex Callaway, MBA, CPHQ, CPPS, Director of Quality & Patient Safety; Diane Barton, MHA/MSN, CPHQ, CPPS, Director of Organizational & Clinical Quality; Jennifer Bentley, RN, BSN, Nursing Quality Coordinator; and Stephanie Bowen, RN, BSN, Nursing Quality Coordinator.

Barton commented that sepsis care became one of Munson Healthcare’s system-level driving strategies several years ago. This focus was partially driven by the system not performing well in comparison to state and national benchmarks but also because sepsis was found to be the number one cause of death for patients across Munson Healthcare.

With a goal to improve both internally as well as in comparison to state and national peers, Barton noted that early on Munson Healthcare identified the CMS SEP-1 bundle as a metric to guide their progress with quality improvement efforts. The CMS SEP-1 bundle is a protocol for treating patients with severe sepsis or septic shock focusing on early intervention and timely recognition of sepsis. It has been directly correlated to reduced mortality and improved patient outcomes.

Barton explained that since Munson is a relatively young system, they utilized an A3 problem solving system to examine the current state of sepsis management across all eight Munson Healthcare sites. With a system-level focus in mind, they created both site and system-level sepsis teams that engaged a variety of team members including representation from direct care providers and support services. The presenters then explained that to ensure provider buy-in, they first needed to develop a standard for monitoring sepsis compliance outcomes and the accompanying feedback pathways to provide up-to-date information to clinicians and quality staff.

At the start, Barton notes they were meeting compliance rates of only 60% but have recently seen less variation in their CMS SEP-1 bundle compliance and are encouraged by this trend. Callaway explained that over time they have modified their approach in response to provider feedback; for example, they eliminated the automated Cerner Sepsis Advisor alert in preference of a Sepsis Power Plan order set. Overall, the presenters noted that the improvement plan implemented by Munson Healthcare has had an overall positive impact on the system.

Following the presentation by Munson Healthcare, MVC Site Engagement Coordinator Emily Bair, MS, MPH, RDN, provided a brief review of the Program Year 2026-2027 sepsis value metric changes for the MVC Component of the BCBSM P4P Program. To better align with HMS sepsis measures, the MVC sepsis value metric transitioned from a readmission measure in PYs 2024-2025 to a follow-up measure in PYs 2026-2027. Bair noted that, following these changes, MVC observed a nearly fourfold increase in the number of participating P4P hospitals that selected the “14-day follow-up after sepsis” value metric.

Blinded MVC data for 14-day outpatient follow-up rates among patients hospitalized for sepsis was then shared with the workgroup attendees (Figure 1). The data showed an MVC All follow-up rate of 57.9% based on claims data for 30- and 90-day inpatient or surgical episodes of care for adults with index admission between 1/1/2022 and 12/31/2023. The hospital-level distribution of 14-day follow-up rates among patients hospitalized for sepsis ranged from 20% to 68% across MVC’s membership.

Figure 1. 14-Day Outpatient Follow-Up Rates Among Patients Hospitalized for Sepsis

Bair closed out the sepsis workgroup by facilitating discussion about 2025 organizational goals related to sepsis and the specific strategies care teams plan to implement in service of those goals. The interventions shared throughout Munson’s presentation and MVC’s blinded data inspired robust discussion about goals and strategies across the collaborative. Common discussion themes for sepsis efforts in 2025 included:

  • Building upon 2024 successes
  • Inclusion of clinical champions to sepsis teams
  • Addition of inpatient sepsis cases into fallout tracking
  • Implementation of data tracking and feedback communication strategies
  • Standardization of documentation and order sets across hospital systems

MVC Sepsis Workgroup Jan. 14, 2025

Health in Action Workgroup January 30, 2025

The second workgroup of 2025 focused on a bird’s eye view of community paramedicine programming. This workgroup featured a presentation by Amanda Biskner, RN, Paramedic, CP-C, the Community Paramedicine Coordinator for Tri-Hospital EMS in St. Clair County, Michigan. The presentation reviewed the benefits and parameters of community paramedicine as well as the steps taken to implement a program in St. Clair County.

The practice of community paramedicine (CP) includes providing “out of hospital” care for non-emergent patients in their own home while also tending to their social determinants of health to improve overall quality of life. The CP’s ability to interface with the 9-1-1 system, extensive education in various topics including acute and chronic care, and license to utilize EMS and CPP protocols prior to PCP contact are just a few items that separate these practitioners from mobile integrated healthcare (MIH) and home health care programs. Bickner summarized the various services that community paramedics may cover within a patient visit (Figure 2).

Figure 2. Community Paramedicine Services

Biskner described the process by which the Tri-Hospital EMS community paramedicine program was initiated, starting with identifying a portion of the objectives for the 2023-2027 St. Clair County Community Health Improvement Plan (CHIP) that could be supported by the program. Next, a pilot program was launched, and between June and October 2024 a total of 12 patients were enrolled and 45 visits completed through the program.

While the established goals for the trial were met –such as increased communication, healthcare access, patient satisfaction, and experience in care transitions – Biskner explained that there remain challenges to program expansion. Even though nearly 100 EMS agencies in 33 states across the U.S. have launched some version of a community paramedicine program, Biskner noted that funding and reimbursement issues are likely to continue since community paramedicine is not yet standardized in its training, licensure, or practice protocols. Increased community education, exposure, and relationships with local healthcare authorities are the primary methods Biskner recommended for expanding community paramedicine opportunities to other communities.

MVC Health in Action Workgroup Jan. 30, 2025

In February, MVC will host two more virtual workgroups. The first workgroup on Tues., Feb. 11 will focus on cardiac rehabilitation, and the next on Thurs., Feb. 27 will feature a health in action workgroup focused on patient journey mapping. To register for these or other future workgroups, please view the 2025 calendar on MVC’s events page [LINK]. If you are interested in leveraging MVC’s robust claims data and data specialists to inform a local or system-level quality improvement effort, reach out to the MVC Coordinating Center [EMAIL].