Off
View Post
Hospitals Receive PY 2026 Mid-Year Scorecards for MVC Component of BCBSM P4P Program

Hospitals Receive PY 2026 Mid-Year Scorecards for MVC Component of BCBSM P4P Program

Earlier this month the Michigan Value Collaborative (MVC) distributed mid-year scorecards for Program Year (PY) 2026 of the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. PY 2026 marks the first year of the two-year (PY 26-27) P4P cycle, and includes Medicaid claims as well as the newly introduced health outcome variation measure in the scoring. This report provided hospitals with their current standing for PY 2026.

Each participating hospital received a mid-year score out of a total of 10 points, including 0 to 3 points for their selected total episode payment metric, 0 to 4 points for their selected value metric, 0 to 1 point for health outcome variation measure and 0 to 2 points for completed eligible engagement activities. PY 2026 scores achievement and improvement points for each metric using index admissions from 2025 performance year data against admissions in 2023 as the baseline year. Hospitals are awarded the higher of their achievement and improvement point scores.

The performance data timeframes included in mid-year PY 2026 scoring were index events 1/1/2025 – 12/31/2025 for BCBSM PPO Commercial, BCBSM Medicare Advantage (MA), BCN HMO Commercial, BCN HMO MA, Medicaid and index events from 1/1/2025 – 6/30/2025 for Medicare FFS. For the health outcome measure, the performance data included were index events from 1/1/1015 – 6/30/2025 to reflect the most recent date range for all payers. The engagement points accrued represent all completed activities from 1/1/2026 – 9/2/2026. All scores are subject to change in the final scorecards as the remaining 2025 performance data becomes available and additional 2026 P4P engagement activities are completed and recorded for this year.

Figure 1 illustrates the current distribution of total points out of 10 across the collaborative. The average points scored across the mid-year scorecards was 5.2 out of 10 and ranged between 0.5 and 10 points. This average is 1.5 points lower than the average points scored at the conclusion of PY 2025.

Figure 1. PY26 Mid-Year Distribution of Total Points Out of 10 Across the Collaborative

Dot plot ranks MVC Hospitals participating in PY26–27 P4P Program by PY26 mid-year score, with scores ranging from roughly 0.5 to 10. Blue hospital markers rise steadily across rankings, while an orange horizontal line marks mean and median at 5.2.

Figure 2 illustrates the breakdown of scoring on average by each program component (i.e., episode spending metric, value metric, health outcome variation measure and engagement points). Hospitals could earn up to three points for their episode spending, four points for their value metric selections, one point for health outcome variation measure and up to two points for engagement activities completed in 2026. Across collaborative, the average points scored for episode spending and value metrics were 1.0 point, and 2.2 points respectively. For the newly introduced health outcome variation measure, the average was 0.6 points and the average for engagement activities was 1.4 points.

Figure 2. PY26 Mid-Year Scoring on Average by Each Program Component

Bar chart showing average points scored across hospitals by category, with y-axis ranging 0–10 points. Blue bars show Episode Spending 1.0/3, Value Metrics 2.2/4, Health Outcome Variation 0.6/1, Engagement 1.4/2, and Total Points 5.2/10.

Figure 3 illustrates the breakdown of the average points by episode spending conditions. Coronary Artery Bypass Grafting (CABG) and Congestive Heart Failure (CHF) were both the highest scoring episode spending conditions with an average of 1.3 points, and this was followed by chronic obstructive pulmonary disease (COPD) with 1 point. The lowest scoring episode spending condition was pneumonia with hospitals earning 0.4 points on average.

Figure 3. PY26 Mid-Year Average Points by Episode Spending Conditions

Bar chart compares average points scored across episode spending conditions: CABG 1.3, CHF 1.3, COPD 1.0, and PCI 0.4. Blue patterned bars use a 0–3 vertical scale, with mean and median both marked as 1.0.

Figure 4 illustrates the breakdown of average points by value metrics. Consistent with PY 2025, the highest scoring value metric was preoperative testing with 3.5 points, followed by 90-day cardiac rehabilitation after CABG with 3.0 points. All follow up metrics had an average score of below 2 points with the lowest scoring value metric being 14-day follow up after COPD with 1.1 points.

Figure 4. PY26 Mid-Year Average Points by Value Metrics

Bar chart compares average points scored across value metrics for preoperative testing and follow-up categories. Dark blue bars decline from 3.5 for preoperative testing to 1.1 for 14-day follow-up after COPD, with mean 2.2 and median 2.0 marked at upper right.

These PY 2026 P4P mid-year scores are subject to change as new data is added. The final scores will be distributed after all 2025 claims are incorporated into the calculations. The full methodology for this program cycle can be found in the PY2026-2027 technical document. Hospitals can also track their score via the P4P PY 2026-2027 dashboard reports on the MVC registry, which provides all relevant scoring information for both improvement and achievement points. These registry reports can be filtered by selected conditions/metrics to make tracking of P4P points easier. You can also contact the MVC Coordinating Center by email for a walkthrough of your hospital’s PY 2026 mid-year scorecard or P4P registry reports.

Off
View Post
Fall Collaborative-Wide Meeting Agenda, Speakers Announced

Fall Collaborative-Wide Meeting Agenda, Speakers Announced

The MVC Coordinating Center is excited to announce the agenda for its fall collaborative-wide meeting on Friday, October 9, 2026, from 10 a.m. – 3 p.m., at Vistatech in Livonia, MI. This meeting’s theme is “Unlocking Data for QI Impact: Translating Insights into Action” and will feature opportunities to learn about the various ways in which MVC's members are leveraging MVC data and resources to drive quality improvement locally and across Michigan. Those interested in attending MVC's fall 2026 collaborative-wide meeting must register here by Tuesday, September 22.

MVC Director Mark Bradshaw, MSc, will kick off the day with updates on MVC’s Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This will be followed by a presentation by MVC Medical Director, Hari Nathan, MD, PhD, “From Performance to Action: Putting MVC Data to Work.” A poster session with presentations from McLaren Greater Lansing Hospital, Trinity Health Grand Haven Hospital, Bronson Methodist Hospital, Henry Ford Hospital, Oaklawn Hospital, and MVC will follow Dr. Nathan’s presentation.

After the poster session, Dr. Kevin Bohnsack and Belinda Dokic, CPhT, BA, MBA, from Trinity Health of Michigan will take the podium to present their work on “Reducing Readmissions Through Data and Analytics.” Attendees will then have time to network with peers over lunch before transitioning into two consecutive breakout sessions.

The four breakout topics will cover:

  • Holland Hospital’s Transitional Heart Failure Program (THFP). Holland Hospital credits THFP as a primary driver of their success on MVC’s congestive heart failure (CHF) episode spending and 7-day follow up measure.
  • Corewell Health System’s approach to engaging with MVC and leveraging MVC data as a unified system.
  • DMC Huron Valley Sinai's partnership with Michigan Surgical Quality Collaborative (MSQC) and MVC to strengthen adherence to evidence-based quality measures in colorectal cancer surgery and drive better short- and long-term outcomes for patients.
  • Key principles and available resources that support strategic metric selection for the MVC component of the BCBSM P4P Program to help MVC members identify their greatest opportunities for improvement across MVC metrics.

MVC Site Engagement Coordinator Rachel Folk, MHA, will close out the day and discuss next steps for MVC’s Component of the BCBSM P4P Program.

The last day to register for MVC’s fall 2026 collaborative-wide meeting is Tuesday, September 22. We look forward to seeing you there!

Off
View Post
Building Confidence in Claims Data: MVC’s Site Coordinator Education Program Continues to Grow

Building Confidence in Claims Data: MVC’s Site Coordinator Education Program Continues to Grow

Helping hospitals turn claims data into meaningful quality improvement (QI) action is central to Michigan Value Collaborative’s (MVC) mission. While MVC has long provided members with access to robust claims-based data and reporting resources, member feedback consistently identified a common challenge: many site coordinators and quality leaders wanted additional support in understanding how to interpret claims data and apply it to their organization’s improvement initiatives.

In response, the MVC Coordinating Center launched a series of site coordinator education modules. This structured learning experience was designed to strengthen claims data literacy while building participants’ confidence in using MVC resources to support local QI efforts. The program combines foundational education with practical application, peer collaboration, and individualized support to create a flexible learning experience that can be tailored to each participants’ needs.

After program registration began in January 2026, interest quickly exceeded expectations leading to the creation of three phased cohorts of quality leaders. To date, 40 site coordinators have enrolled in the program, representing 33 hospitals and 12 health systems, reflecting the growing demand for education focused on translating data into action.

A Four-Module Learning Experience

MVC’s site coordinator education program consists of four live, virtual modules that can be completed sequentially or independently depending on each participant’s experience and learning goals.

Module 1: Understanding MVC Fundamentals

The first module introduces participants to foundational knowledge about MVC including the collaborative’s mission, vision, data resources, P4P program, and engagement opportunities. Participants are additionally encouraged to develop a plan for how to meet yearly engagement goals based on preferred activities.

Module 2: Navigating MVC Data Resources

The second module reviews common claims data terminology and definitions, strengths and limitations of claims data, and explores how claims data can be used to supplement clinical data analyses to support QI efforts. Participants also learn to navigate the MVC registry, interpret push reports and identify meaningful performance measures.

Module 3: Applying MVC Resources to Quality Improvement

The third module examines opportunities to make connections between QI efforts and other aspects of MVC’s programming including fellow CQI collaborations and the MVC Component of the BCBSM P4P Program. This module aims to shift from understanding claims data to identifying applications of MVC resources to QI.

Module 4: Best Practice Sharing and Stakeholder Engagement

The fourth and final module focuses on translating the knowledge gained from the previous modules into the appropriate next steps for QI. Participants will have the opportunity to discuss best practices, challenges, and stakeholder communication strategies with fellow quality leaders engaged in similar areas of QI.

This curriculum is built around four complementary components that reinforce learning and encourage real-word application:

  • Foundational Learning: Live virtual sessions introduce key concepts, data resources, and other programmatic materials
  • Applied Case Studies: Independent exercises using hospital-specific reports help guide data interpretation and identify QI opportunities
  • Individual Coaching: One-on-one support from MVC Coordinating Center offers on-demand assistance with report interpretation and the development of customized reference tools
  • Peer Learning Forums: Integrated opportunities to connect with colleagues across Michigan to share experiences, discuss challenges, and exchange successful strategies

Together, these components create a learning environment that extends beyond traditional education by helping participants immediately apply knowledge to their own QI work.

As an example, following Module 2, participants are encouraged to complete a worksheet designed to apply concepts from the 1:1 session to their own organization’s data. Completed worksheets demonstrate strong engagement with the education framework, with participants identifying meaningful opportunities to improve quality of care in a variety of focus areas including readmissions, care transitions, cardiac rehabilitation utilization, and drivers of higher episode spending. Rather than jumping directly to solutions, participants thoughtfully used MVC claims data to generate hypotheses, identify additional clinical and operational information needed, and defined realistic next steps for QI.

A common theme across submissions is recognition that claims data can serve as a starting point for inquiry but must be combined with other data resources to drive QI strategies. Participants frequently identified the need to pair MVC data registry findings with health record data, chart reviews, frontline staff feedback, and internal quality dashboards to better understand underlying drivers. Participants also outlined practical next steps such as engaging multidisciplinary teams, validating findings locally, and integrating MVC data monitoring into existing QI initiatives. These outcomes demonstrate the program’s goal of helping site coordinators translate data insights into meaningful action.

Participant Feedback and Preliminary Outcomes

Evaluation is embedded throughout the education program to ensure the curriculum continues to meet participants’ needs. While the program is in its first year, initial feedback suggests it is already helping participants build confidence in using MVC resources. Following the completion of Module 1, site coordinators have reported an average confidence rating of 4.5 out of 5 in their ability to “describe MVC’s data resources and engagement opportunities.” These early results indicate that the program is successfully establishing a strong foundation for participants as they progress towards applying claims data to QI initiatives within their organizations.

Additionally, participants have highlighted the program’s impact on building both knowledge and confidence:

"Thank you so much for the time and education! I think this is exactly what I need as a new Quality Manager and Site Coordinator. Looking forward to the next module!"

"It was a great learning experience and I'm looking forward to learning more about how we can use this data for process improvement."

"This was a foundational review. I feel very confident with the foundational principles now. I look forward to becoming more comfortable with the claims data and using this data more confidently to improve our performance."

Looking Ahead

MVC’s education modules were designed to bridge the gap between data availability and practical application by combining several complimentary learning strategies. By equipping site coordinators with the knowledge and tools to not only interpret but also apply MVC data to QI efforts, the program aims to strengthen hospitals’ ability to identify improvement opportunities, support evidence-informed decision-making, and advance value-based care across Michigan.

As the program continues to expand, the MVC Coordinating Center is planning to scale up the program by training additional Coordinating Center team members to lead these sessions. Using participant feedback from post-module and post-program surveys, MVC will also continue to refine the curriculum to best meet the needs of site coordinators.

MVC looks forward to welcoming future cohorts of hospital quality leaders to the education program. If interested in joining the next cohort beginning in October 2026, please complete the registration form here.

Off
View Post
MVC Finalizes Summary Evaluation of PY 24-25 P4P Cycle

MVC Finalizes Summary Evaluation of PY 24-25 P4P Cycle

This year, the Michigan Value Collaborative (MVC) completed scoring and evaluation for Program Year (PY) 2025 of the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This concluded a two-year program cycle encompassing the program methodologies and conditions utilized in PYs 2024 and 2025. MVC recently completed an evaluation of these two program years, which focused on hospital performance on average 30-day risk-adjusted, price-standardized total episode payments for the included conditions as well as utilization rates for the included value metrics across both program years.

The PY 2024-2025 program cycle utilized episode claims from 2021 through 2024. PY 2024 scoring compared performance year data from 2023 against baseline year data from 2021. PY 2025 scoring compared performance year data from 2024 against baseline year data from 2022.

Hospitals chose one episode spending condition from six available options for the PY 2024-2025 program cycle, including chronic obstructive pulmonary disease (COPD), colectomy (non-cancer), congestive heart failure (CHF), coronary artery bypass graft (CABG), joint replacement (hip and knee), and pneumonia. Among these six P4P conditions, joint replacement was the most selected condition (31), and pneumonia was the least frequently selected (6). Colectomy was not selected by any hospital.

Trends in average price-standardized episode payments showed a consistent decrease over the years for joint replacement. Both COPD and CABG showed relatively consistent trend in payments and had the highest payments in 2022 as seen in Figure 1. Both PYs saw an average decrease in payments in both CABG and joint replacement. Joint replacement was the largest contributor to the cost savings in this cycle with a decrease of $3 million dollars in PY 2024 and $1.9 million dollars in PY 2025.

Figure 1. Average Price-Standardized Episode Payment Trends for P4P Conditions (2020-2024)

Line chart showing 30-day total episode payments from 2020 to 2024 for five conditions: CABG, Pneumonia, CHF, COPD, and Joint. CABG payments remain highest around $50,000 with slight fluctuations, while other conditions show gradual increases between $14,000 and $18,000.

MVC further assessed the components contributing to total episode spending, and determined all conditions except COPD showed a decrease in spending in at least one episode component (i.e., index payment, professional services, post-discharge care, readmissions) across both PYs (Figures 2-3). Joint replacement showed decreased spending across all components in PY 2025 and across all components except readmissions in PY 2024. Similarly, all conditions demonstrated a reduction in spending for at least one post-discharge component in both PYs. Home health spending decreased across all conditions while inpatient rehabilitation spending increased for most conditions in both PYs. Emergency department spending also decreased for most conditions across both PYs.

Figure 2. Change in Average Price-Standardized Episode Components, PY 2024

Bar chart comparing 30-day episode component payments across five P4P conditions: CABG, CHF, COPD, Joint Replacement, and Pneumonia. Each condition's total payment is broken down into four color-coded components—Index (dark blue), Professional (orange), Post-Discharge (bright blue), and Readmissions (gray)—highlighting negative payment for CABG and Joint Replacement and positive payments for other conditions.

Figure 3. Change in Average Price-Standardized Episode Components, PY 2025

Bar chart comparing 30-day episode component payments across five P4P conditions: CABG, CHF, COPD, Joint Replacement, and Pneumonia. Payment components include Index (dark blue), Professional (orange), Post-Discharge (bright blue), and Readmissions (gray), showing negative total payments for CABG and Joint Replacement, and highest positive payment for Pneumonia.

In addition to selecting an episode spending condition, hospitals also selected one of seven available value metrics for the PY 2024-2025 program cycle. This included 7-day follow-up after CHF, 7-day follow-up after pneumonia, 14-day follow-up after COPD, 30-day inpatient readmissions after sepsis, 90-day cardiac rehab after CABG, 90-day cardiac rehab after PCI, and preoperative testing before low-risk surgeries (i.e., inguinal hernia repair, cholecystectomy, and lumpectomy). The 7-day follow-up after CHF metric (23) was the most frequently selected value metric followed by 90-day cardiac rehab after PCI (17). In contrast, 90-day cardiac rehab after CABG and 30-day inpatient readmissions after sepsis were the least frequently selected (5) value metrics.

Among the high-value metrics, hospitals that selected 14-day follow-up after COPD and 90-day cardiac rehab after PCI increased their utilization rate by 1.4% and 3.1%, respectively, from 2021 to 2023 (Table 1). In PY 2025, the utilization of 90-day cardiac rehab after CABG increased by 3.6% in 2024 compared to 2022 (Table 2). Among the low-value metrics, sepsis readmission rates decreased by 0.5% in PY 2024 and 7.0% in PY 2025. Preoperative testing rates decreased by 5% from 2022 to 2024 in PY 2025.

Table 1. Average Utilization Changes for P4P Value Metrics in PY 2024

Table displaying P4P value metrics with average utilization percentages for 2021 and 2023, alongside utilization change rates. Metrics include follow-up rates after CHF, pneumonia, COPD, cardiac rehab after CABG and PCI, inpatient readmissions after sepsis, and preoperative testing, with notable increases in 14-day COPD follow-up (1.4%) and 90-day cardiac rehab after PCI (3.1%).

Table 2. Average Utilization Changes for P4P Value Metrics in PY 2025

Table comparing average utilization rates for various healthcare metrics in 2022 and 2024, highlighting percentage changes. Metrics include follow-up periods after conditions like CHF, pneumonia, COPD, cardiac rehab after CABG and PCI, inpatient readmissions after sepsis, and preoperative testing, with notable increases in 90-day cardiac rehab after CABG and decreases in inpatient readmissions and preoperative testing.

Overall, the average total points earned remained relatively stable between PY 2024 (6.6) and PY 2025 (6.7), as shown in Figure 4. Average episode spending points decreased from 2.4 to 2.2, while average value metric points increased from 2.4 to 2.6, and average engagement points increased from 1.7 to 1.8 from PY 24 to PY 25.

Figure 4. Average Points Earned by Scoring Components in PYs 2024-2025

Bar chart comparing scores for PY 24 and PY 25 across four categories: Episode Spending Points, Value Metrics, Engagement Points, and Final Score. PY 25 slightly outperforms PY 24 in Value Metrics, Engagement Points, and Final Score, with both years scoring similarly in Episode Spending Points.

The distribution of total points earned by participating hospitals in PY 2024 and PY 2025 are shown in Figures 5 and 6, respectively. Approximately 15% of hospitals scored the maximum score of 10 points in PY 2024 and this proportion decreased to 10% in PY 2025.

Figure 5. Distribution of Hospital Total Points Scored for PY 2024

Scatter plot showing PY24 final scores of MVC hospitals participating in PY24-25 program, with scores ranging from 0 to 10. Data points are marked in blue, with mean score 6.6 in orange and median score 6.1 in gray, highlighting most hospitals scoring at or above median and mean.

Figure 6. Distribution of Hospital Total Points Scored for PY 2025

Scatter plot showing final PY 25 scores for MVC hospitals participating in PY 24-25 program, with scores ranging from 2 to 10. Plot includes orange line for mean score (6.7), gray line for median score (6.0), and dark blue dots representing individual hospital scores, highlighting most hospitals scoring at or above median.

Additional details are contained in the full report. Please contact the Coordinating Center for more details on the report or for any questions regarding the PY 2024-2025 cycle.

Off
View Post
Share Your Success Story at MVC’s Fall 2026 Collaborative-Wide Meeting

Share Your Success Story at MVC’s Fall 2026 Collaborative-Wide Meeting

The Michigan Value Collaborative (MVC) is now accepting presentation proposals for its fall 2026 collaborative-wide meeting, taking place Fri., Oct. 9, at the VistaTech Center in Livonia, Michigan.

Each collaborative-wide meeting provides an opportunity for members to learn directly from one another by sharing innovative approaches, practical lessons learned, and successful quality improvement strategies. MVC is seeking presentations that highlight quality improvement initiatives informed by MVC offerings, such as push reports, custom reports, registry data, or insights gained through participation in MVC events and peer learning opportunities.

Potential presentation topics include how your organization used MVC offerings to:

  • Benchmark performance against peer hospitals
  • Establish quality improvement goals and target metrics
  • Build leadership support for improvement initiatives
  • Identify variation in care across hospitals or communities
  • Measure the progress or impact of interventions
  • Inform the development of new workflows, programs, or best practices

We also welcome proposals showcasing other ways your organization has leveraged data to support quality improvement planning, implementation, or evaluation.

Partners may submit MVC's online presentation proposal form by Tues., July 28, to share their proposed topic. After proposals are reviewed, the MVC Coordinating Center will contact selected presenters to discuss their topic and provide guidance throughout the presentation development process.

As an added benefit, hospitals participating in the MVC Component of the BCBSM Pay-for-Performance (P4P) Program may earn 0.5 engagement points toward Program Year 2026 for presenting at an MVC event.

We hope you'll consider sharing your team's work and helping inspire improvement efforts across the MVC collaborative.

Presentation proposal deadline: Tues., July 28

Please reach out to the MVC Coordinating Center with any questions.

Off
View Post
PY 2025 Final Scorecards Shared for MVC Component of the BCBSM P4P Program

PY 2025 Final Scorecards Shared for MVC Component of the BCBSM P4P Program

Last month, the Michigan Value Collaborative (MVC) distributed final scorecards for Program Year (PY) 2025 of the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This report provided hospitals with their final scores for PY 2025 as well as detailed breakdowns by scoring components. It also included a preview of measure scoring for the new health outcome variation measure that will be worth one point in PYs 2026-2027.

Each hospital received a final score out of a total of 10 points, including 0 to 4 points for their selected total episode payment metric, 0 to 4 points for their selected value metric, and 0 to 2 points for completed eligible engagement activities. PY 2025 scored each participating hospital’s achievement and improvement for selected episode spending conditions and value metrics using index admissions from 2024 performance year data against 2022 baseline year data. Hospitals were awarded the higher of their achievement or improvement point scores.

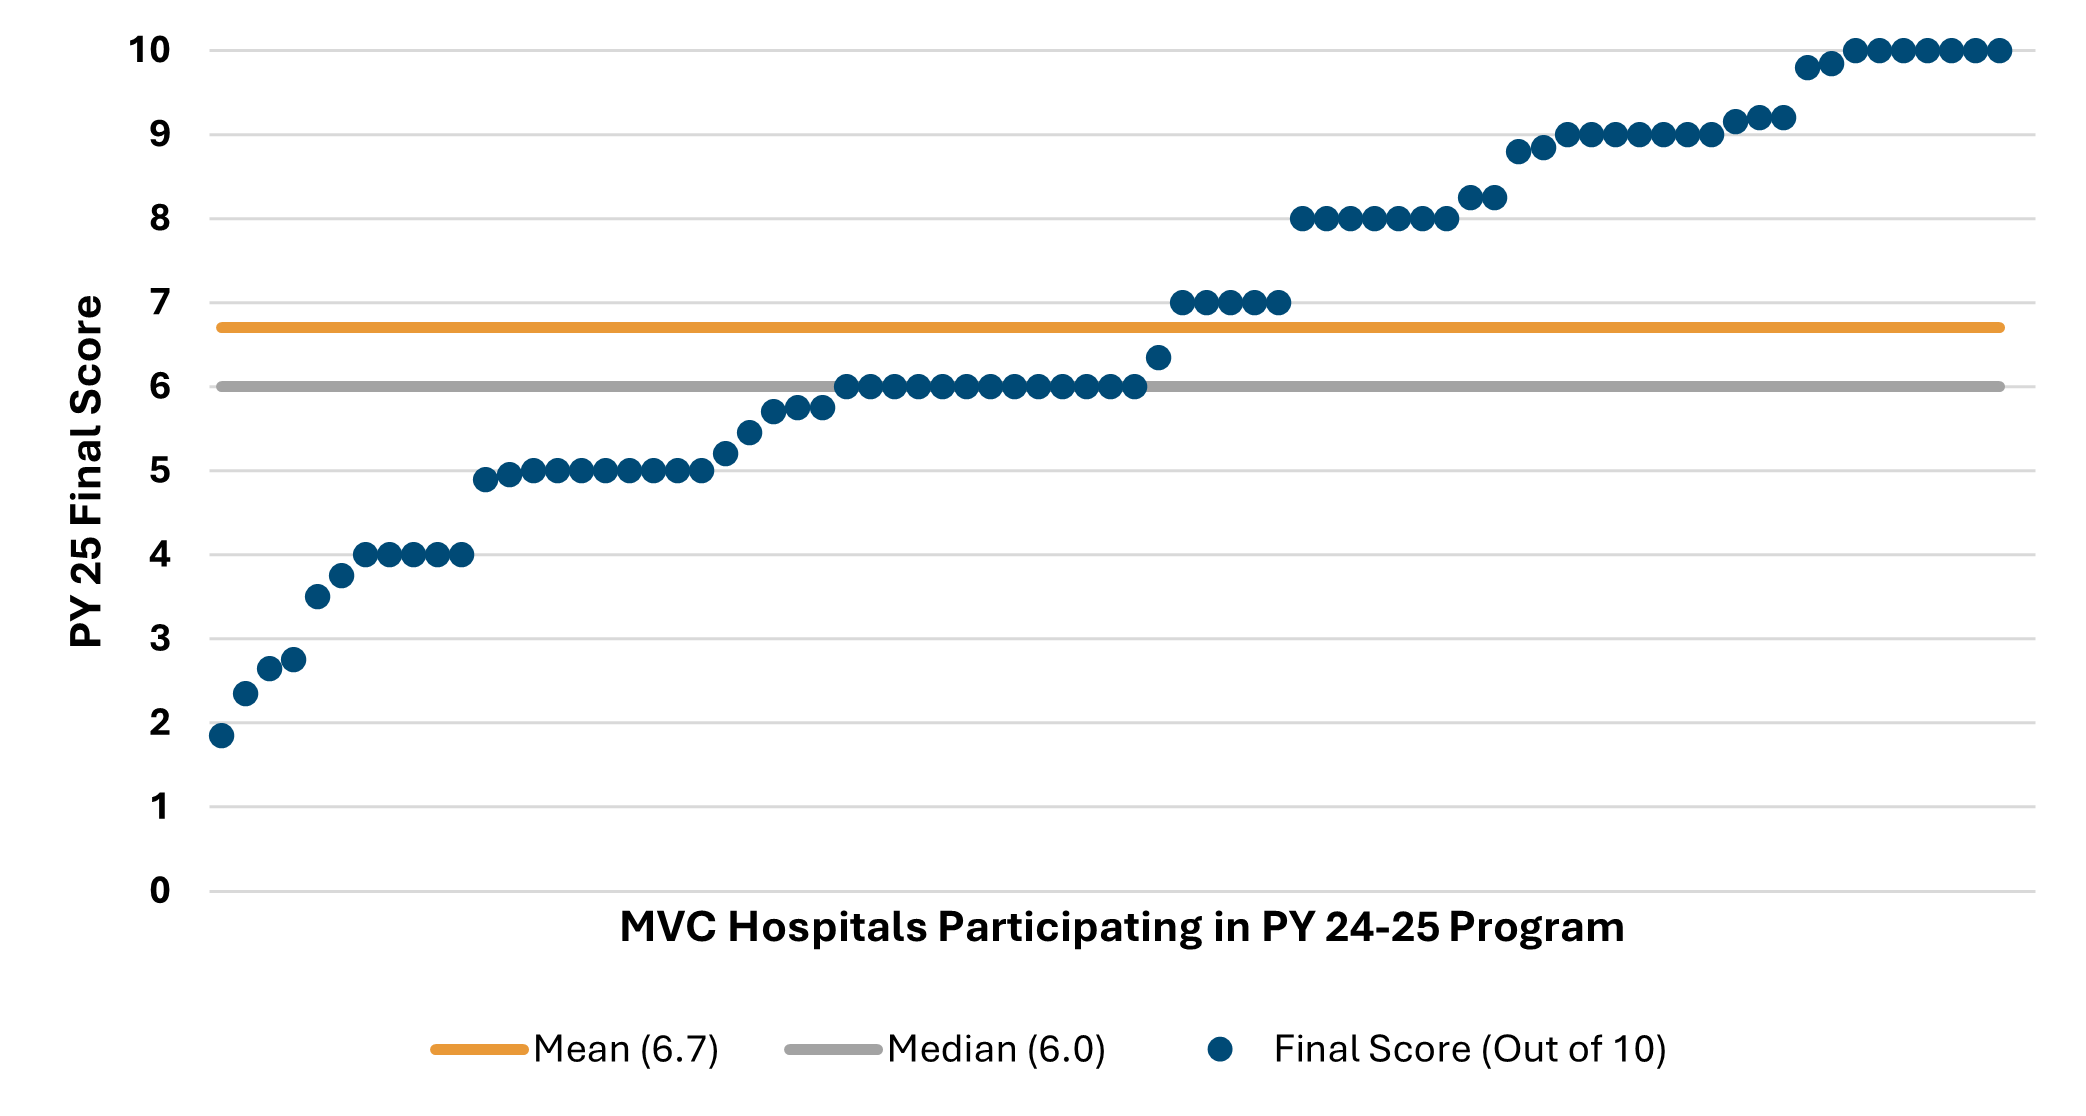
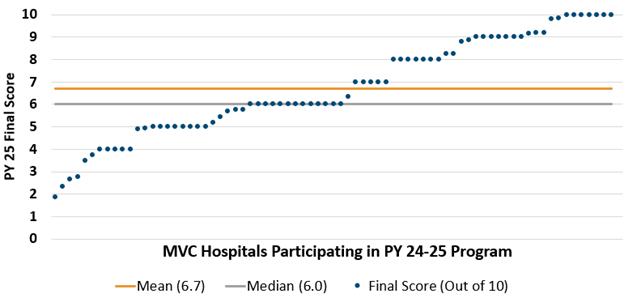
Figure 1 illustrates the distribution of total points out of 10 across the collaborative. The average points scored across the final scorecards was 6.7 out of 10. This average is 0.1 higher than the average points scored at the conclusion of PY 2024.

Figure 1. Distribution of Hospital Total Point Scores for PY 2025

Line chart showing final scores of MVC hospitals participating in PY 24-25 program, with scores ranging from 2 to 10 out of 10. Chart includes orange line for mean score (6.7) and gray line for median score (6.0), highlighting most hospitals scored above median and mean.

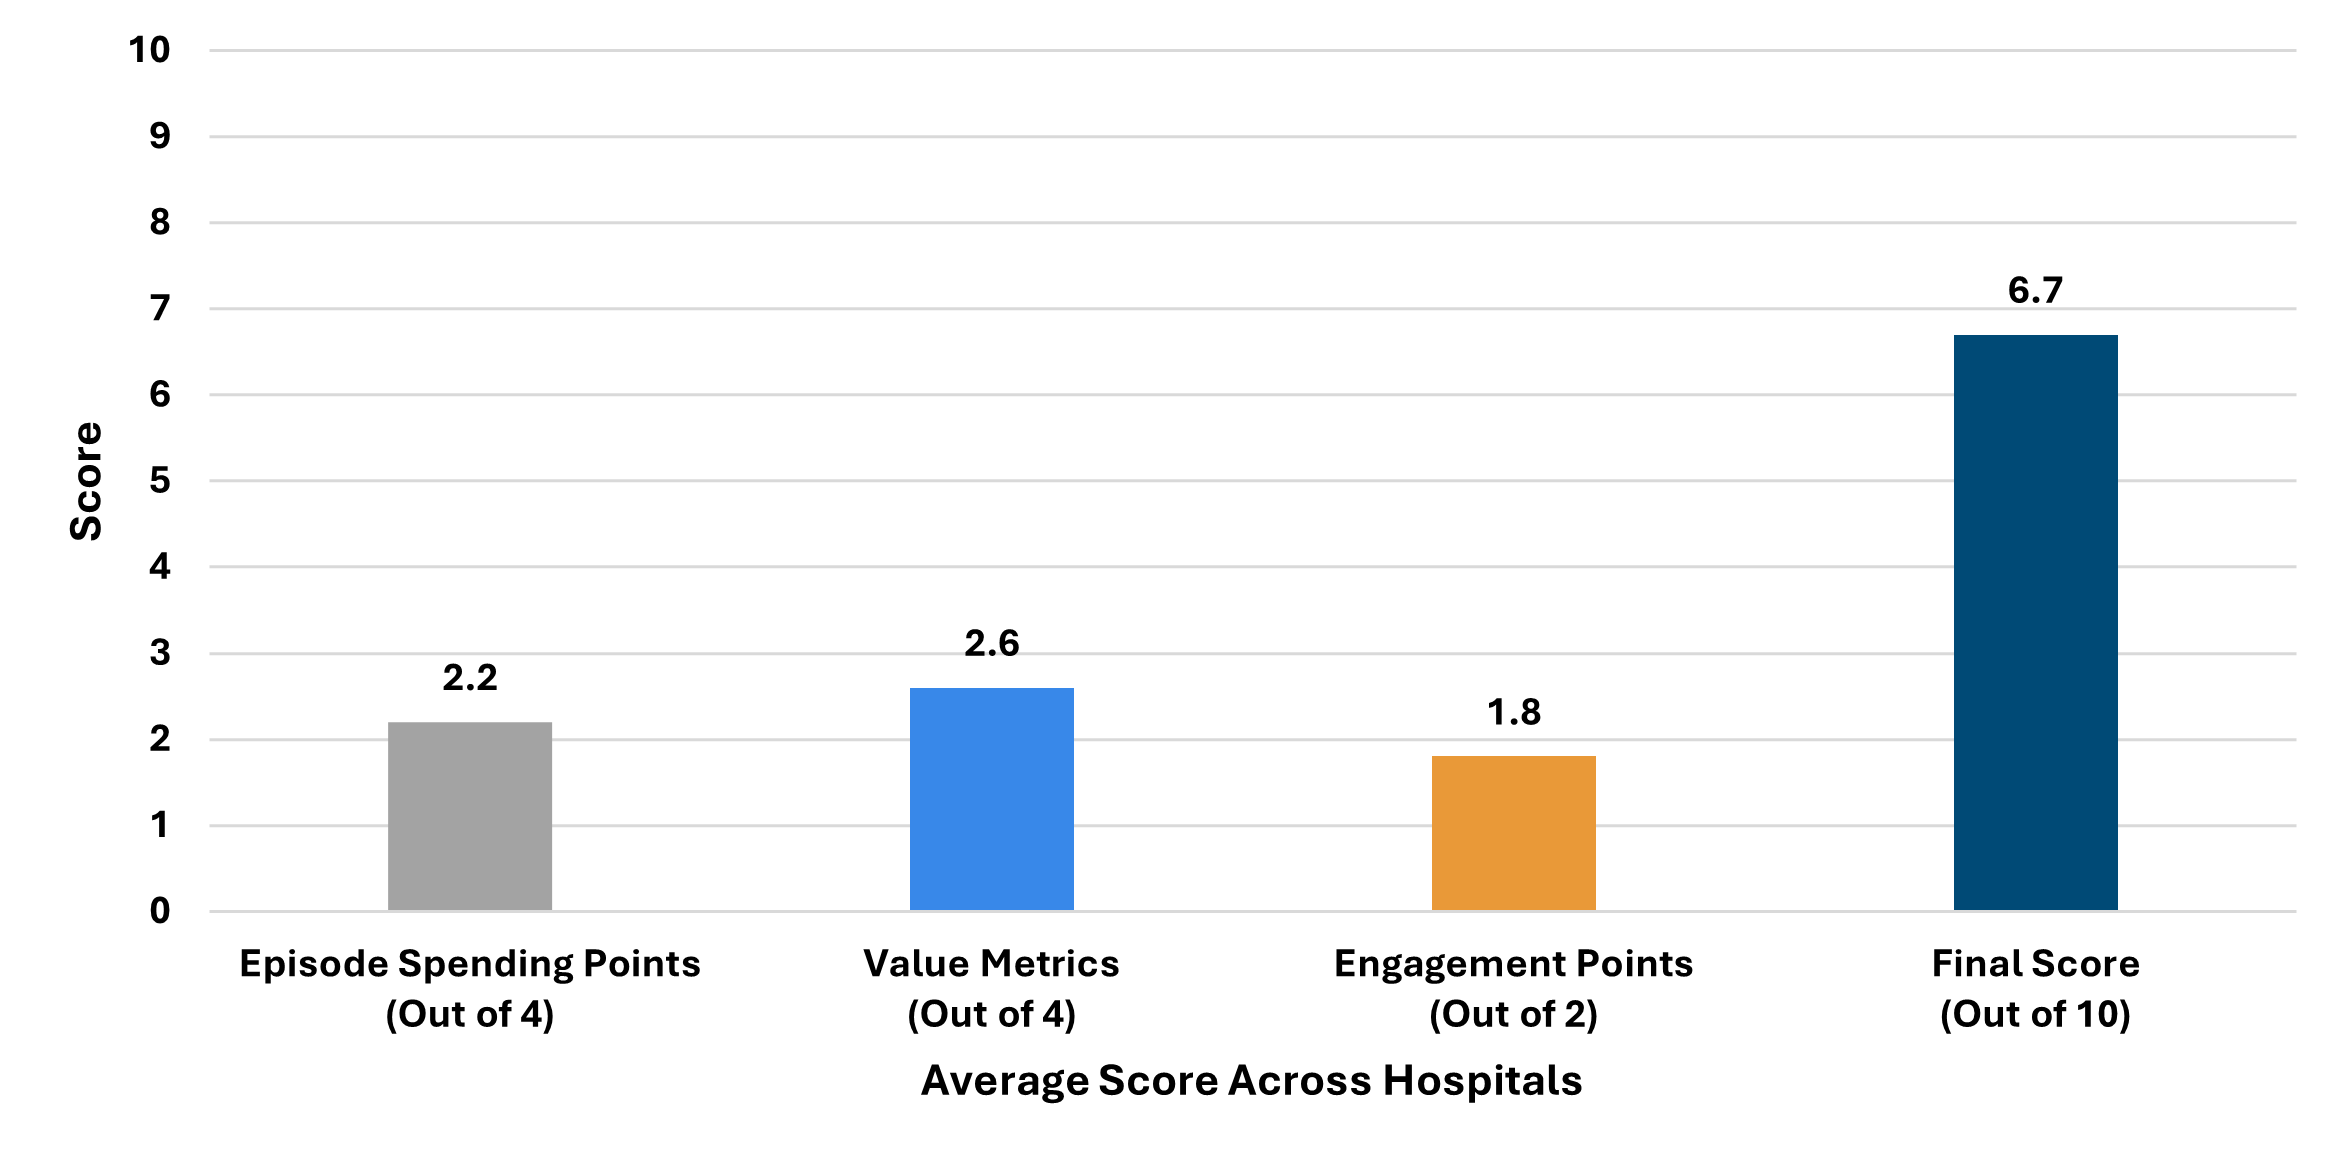
Figure 2 illustrates the breakdown of scoring on average by each program component (i.e., episode spending metric, value metric, engagement points). Hospitals could earn up to four points for their episode spending and value metric selections, and up to two points for engagement activities completed in 2025. Across the collaborative, hospitals scored an average of 2.2 points for episode spending, 2.6 points for value metrics, and 1.8 points for engagement activities.

Figure 2. Average Points Earned in PY 2025 by Scoring Component

Bar chart comparing average scores across hospitals in four categories: Episode Spending Points, Value Metrics, Engagement Points, and Final Score. Bars are color-coded gray, blue, orange, and dark blue respectively, with Final Score notably highest at 6.7 out of 10.

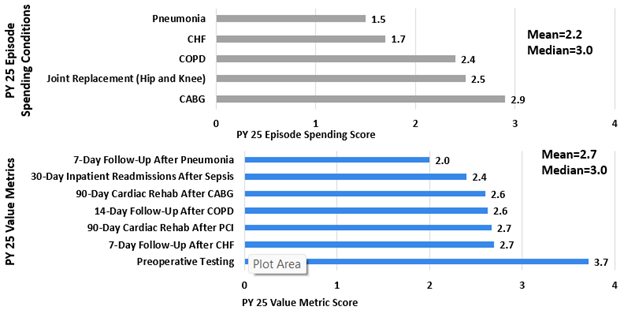
Figure 3 illustrates the breakdown of the average points by episode spending conditions. The highest scoring episode spending condition was coronary artery bypass grafting (CABG) with an average of 2.9 points, and this was followed by joint replacement with 2.5 points. Conditions that hospitals scored less than 2 points on episode spending on average were congestive heart failure and pneumonia with 1.7 and 1.5 points respectively.

Figure 3. Average Points Earned Out of Four in PY 2025 by Episode Spending Condition

Bar chart comparing PY 25 episode spending scores across five medical conditions, with CABG showing the highest score of 2.9 and Pneumonia the lowest at 1.5. Chart includes mean spending score of 2.2 and median of 3.0, with dark blue bars labeled by condition on the x-axis and spending scores on the y-axis.

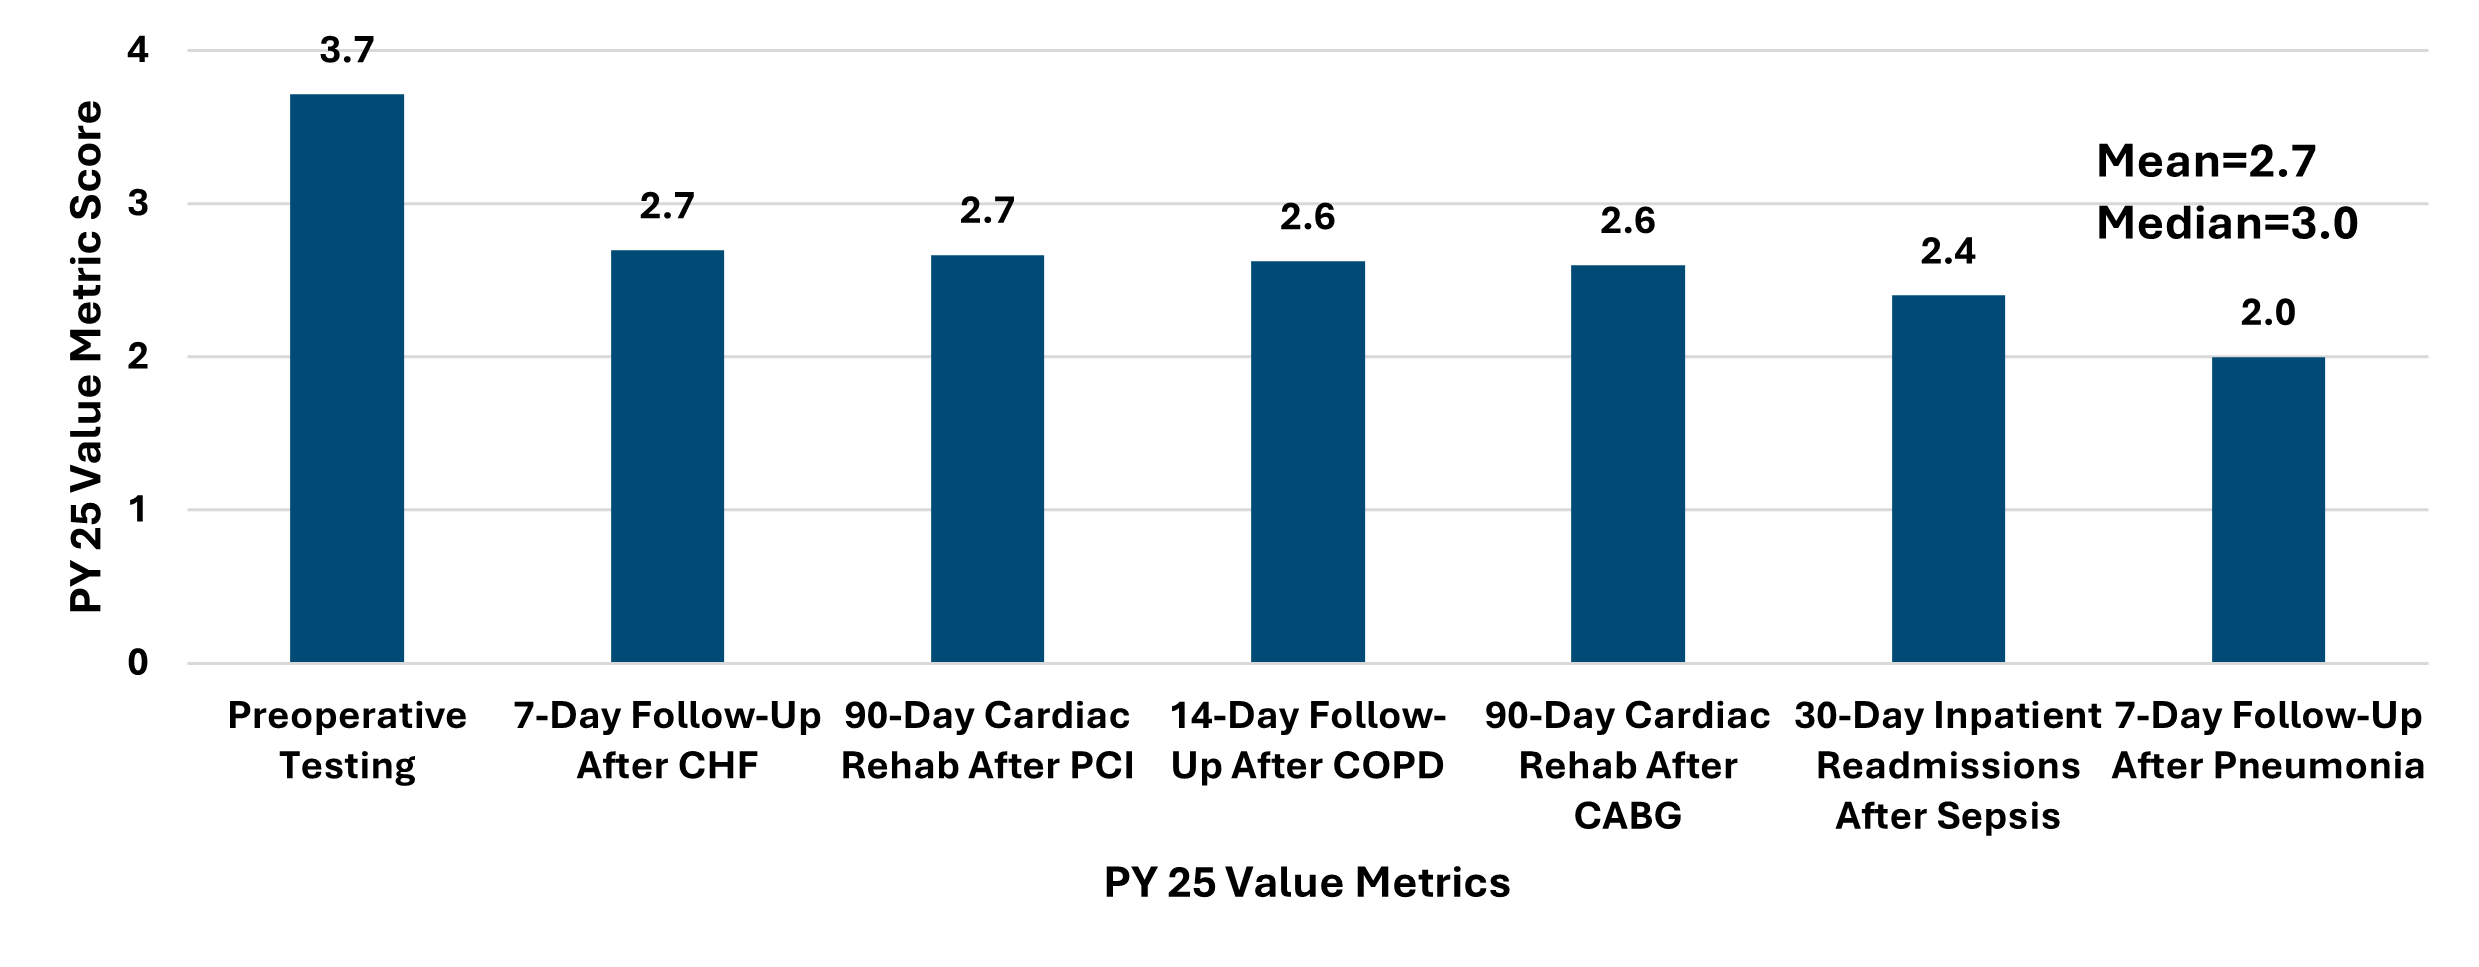
Figure 4 illustrates the breakdown of average points by value metrics. Consistent with PY 2024, the highest scoring value metric was preoperative testing with 3.7 points. This was followed by 90-day cardiac rehab after PCI and 7-day follow up after CHF, both with an average score of 2.7 points. The lowest scoring value metric was 7-day follow up after pneumonia and follows the same trend as that of PY 2024 with 2 points.

Figure 4. Average Points Earned Out of Four in PY 2025 by Value Metric

Bar chart displaying PV 25 value metric scores across various medical follow-up and testing categories, with scores ranging from 2.0 to 3.7. Categories include preoperative testing, cardiac rehab, and inpatient readmissions, with mean score 2.7 and median 3.0 indicated on chart.

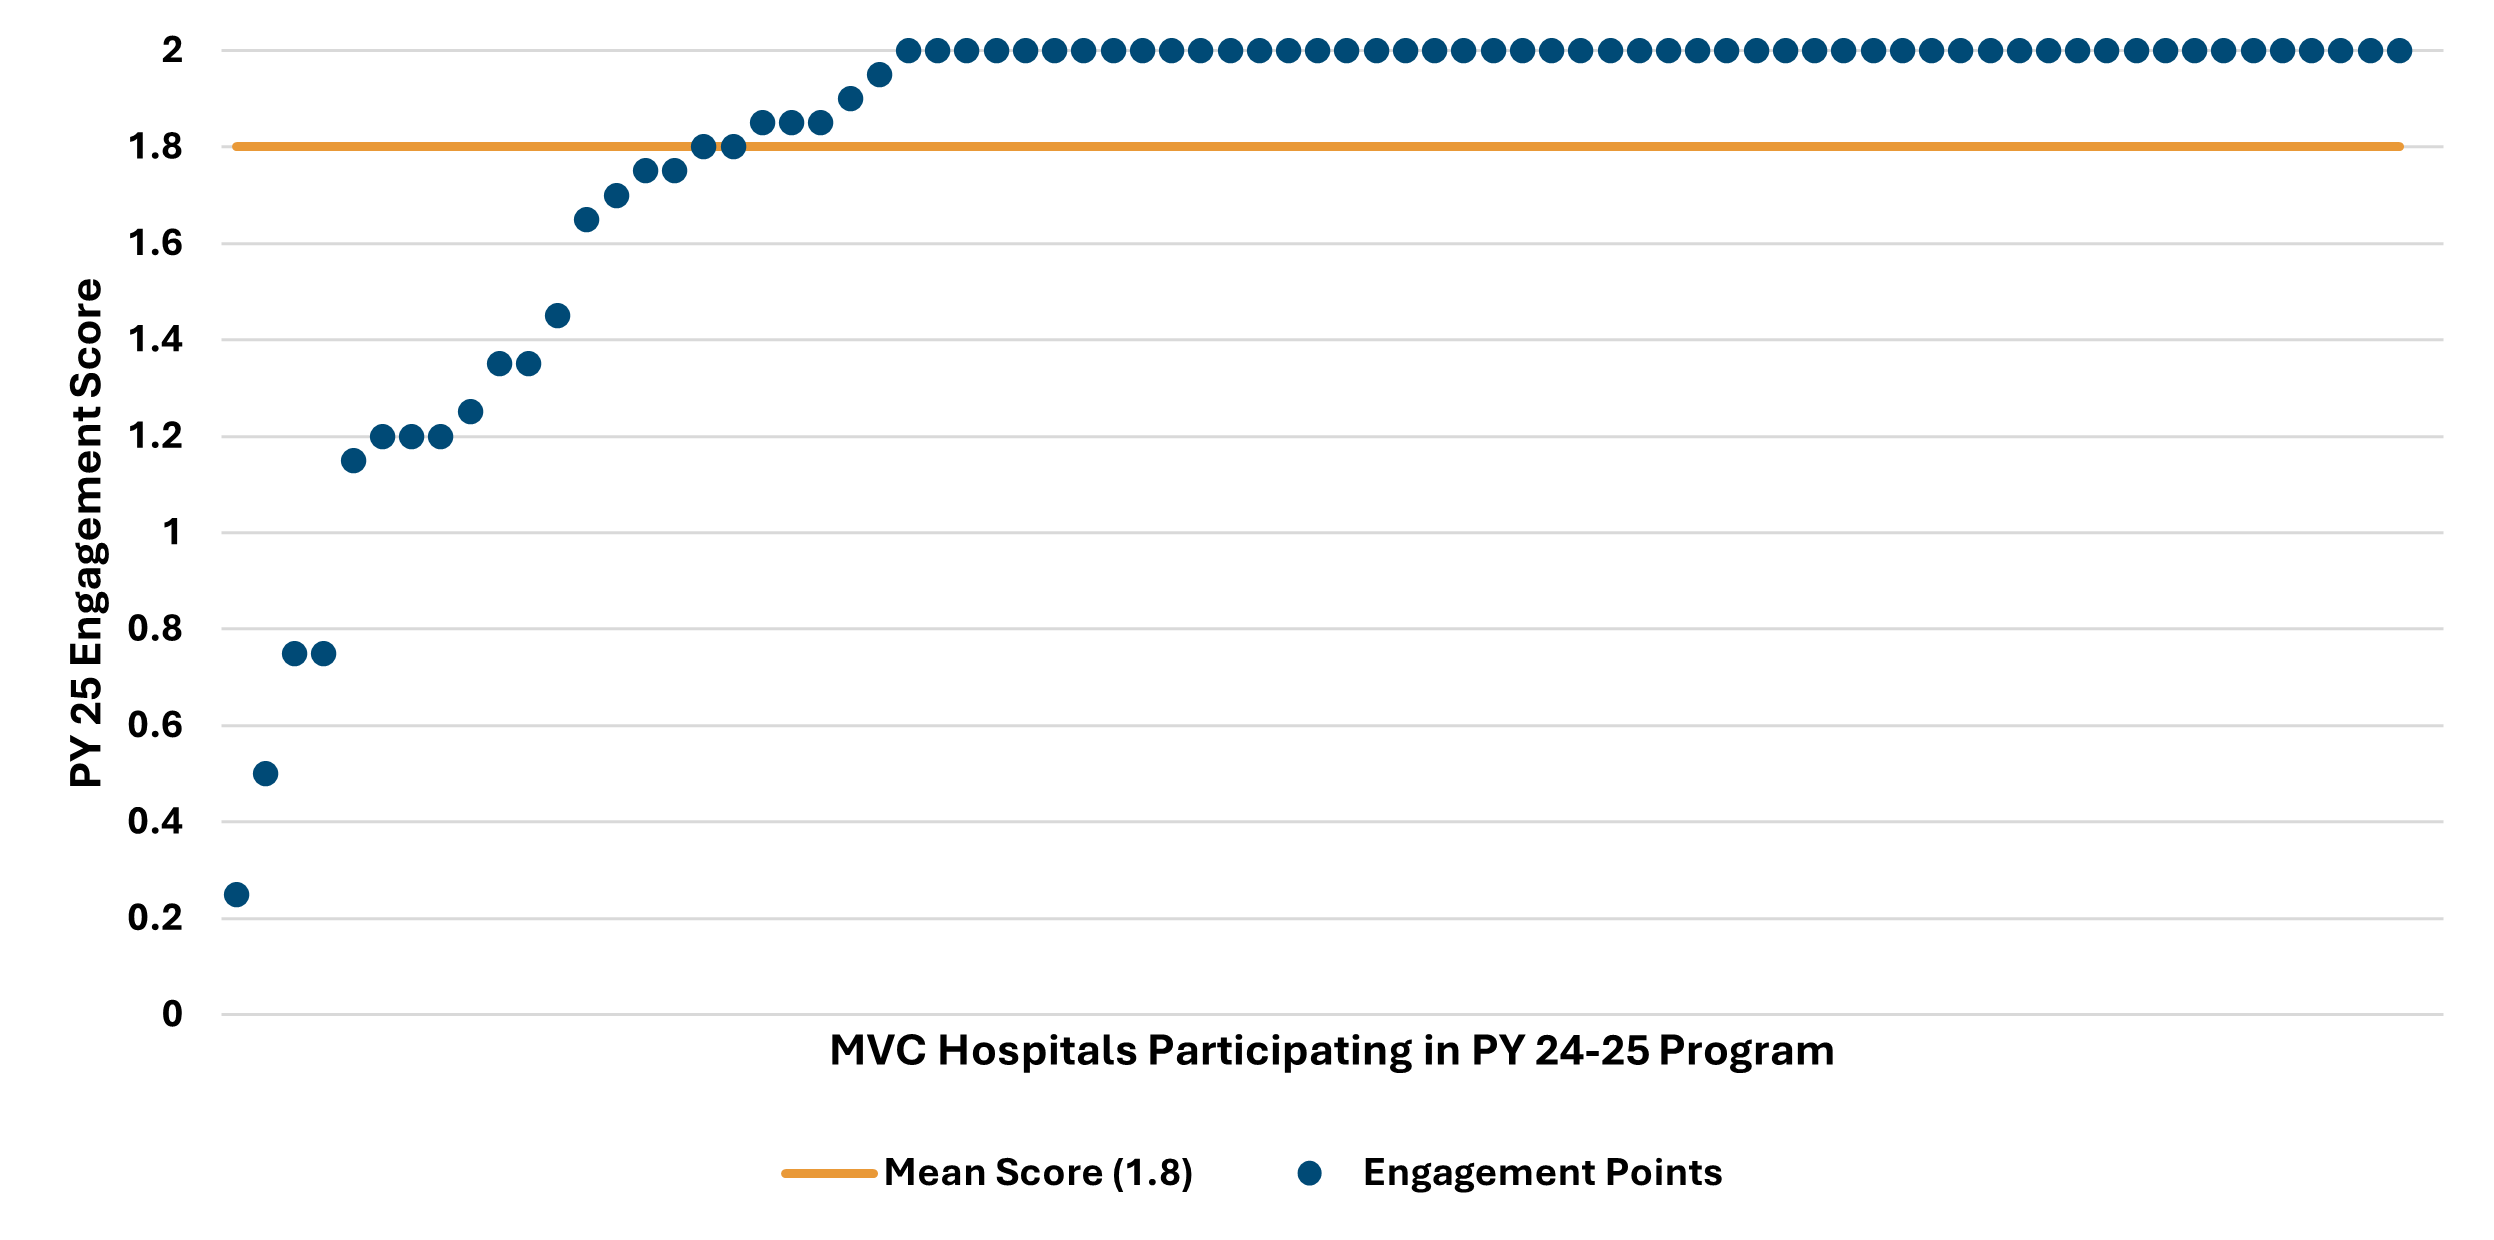
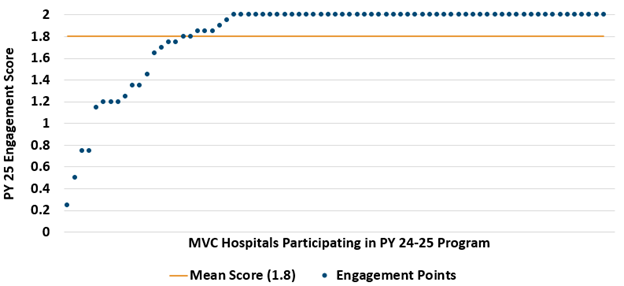
Figure 5 shows the distribution of engagement points earned out of a maximum of 2 across the collaborative. Notably, about 70% of the participating hospitals earned both engagement points in PY 2025.

Figure 5. Distribution of Engagement Points Earned by Hospitals in PY 2025

Scatter plot showing engagement scores of MVC hospitals participating in PY 24-25 program, with individual hospital scores represented by blue dots. An orange horizontal line marks the mean score of 1.8, highlighting that most hospitals meet or exceed this engagement threshold.

This is the second year of a two-year (PY 24-25) P4P cycle. The full methodology for this program cycle can be found in the PY2024-2025 technical document [PDF].

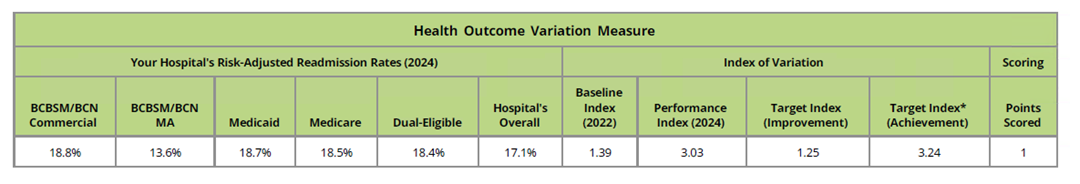
In addition to the PY 2025 final scorecard summary, this report also included a preview of the new health outcome variation measure scoring, which will be worth one point in PY 2026-2027 (Figure 6). The table presents the hospital’s payer-specific risk-adjusted readmission rates in the performance year, the baseline and performance indexes for the hospital, and the target indexes required to score a point via improvement or achievement. This table’s scoring is based on PY 2025 data (i.e., 2024 performance year data and 2022 baseline data). When used in conjunction with other previously shared reports (e.g., the health outcome variation measure push report), hospitals can view performance trends over time on this measure. MVC has also recently prepared custom report requests for members on their HOV performance.

Please note that this table was included to help orient members with the scoring methodology for this new measure and did not impact PY 2025 scores. For detailed information about this measure, hospitals can watch an MVC introductory video to the HOV measure and refer to the PY 2026-2027 P4P technical document.

Figure 6. Sample Scoring of New Health Outcome Variation Measure

Table displaying Health Outcome Variation Measure for hospital readmission rates in 2024 across different insurance types, including BCBSM/BCN Commercial, BCBSM/BCN MA, Medicaid, Medicare, and Dual-Eligible. Key data includes baseline index (1.29), performance overall (3.03), target index for improvement (1.25), target index for achievement (1.24), and a scoring column with points scored (1).

If you have any questions regarding PY 2025 of the MVC Component of the BCBSM P4P Program, please refer to the MVC P4P PY 2024-2025 Technical Document.  You can also contact the MVC Coordinating Center for a walkthrough of your hospital’s PY 2025 final scorecard or P4P registry reports. MVC will evaluate and release mid-year scorecards for PY 2026 in Q3 of 2026.

Off
View Post
MVC 2026 Spring Collaborative-Wide Meeting Summary – From Innovation to Impact: Advancing Care Across Health Networks

MVC 2026 Spring Collaborative-Wide Meeting Summary – From Innovation to Impact: Advancing Care Across Health Networks

The Michigan Value Collaborative (MVC) held its spring 2026 collaborative-wide meeting on Fri., May 8, in Traverse City, Michigan. A total of 84 attendees representing 48 hospitals, 16 multi-hospital systems, and seven physician organizations from throughout the state of Michigan explored strategies for elevating quality across integrated health networks through the lens of system-wide alignment and data-driven improvement.

MVC Director Mark Bradshaw, MSc, began Friday’s meeting with updates on the MVC Coordinating Center and the MVC Component of the BCBSM P4P Program [see slides]. He first introduced attendees to MVC’s newest team members, Senior Faculty Advisor Ryan Howard, MD, MS, and Lead Analyst Megan Heath, PhD. Bradshaw then provided an update on recent MVC reporting since the fall collaborative-wide meeting, including 12 hospital-level custom reports, a push report focused on follow-up utilization, and the P4P Program Year (PY) 2025 final scorecards. It was further announced that MVC’s registry was recently updated with new payer data, including three new months of BCBSM/BCN claims and three new quarters of Medicare FFS claims.

He also provided an update on MVC’s new site coordinator education program. With a total of 31 site coordinators enrolled thus far in 2026, he encouraged those interested in starting in Q4 of 2026 or Q1 of 2027 to join the waitlist for this individualized educational offering [registration link].

Bradshaw next summarized updates on the Michigan Cardiac Rehab network’s (MiCR) efforts to improve cardiac rehabilitation utilization. These include an upcoming MiCR virtual forum featuring a group cardiac rehab demo [registration link], a third round of NewBeat material orders, and Heart-to-Heart patient stories. Additionally, he summarized the status of MiCR’s medication management initiative. If interested in participating in an interview on this topic, please contact MVC via email [email link].

After providing MVC Coordinating Center updates, Bradshaw moved on to provide insights into final scoring of P4P PY 2025 (see Figures 1-3), which included slight increases in average total points scored from PY 2024, some improvements in engagement point scoring, and continued scoring success for value metrics tied to MVC’s value-based initiatives (e.g., cardiac rehab and preoperative testing metrics).

Figure 1. Distribution of MVC’s P4P PY 2025 Total Points

Line chart displays final scores of MVC hospitals participating in PY 24-25 program, with scores plotted as blue dots ranging from 2 to 10. Horizontal lines indicate mean score of 6.7 in orange and median score of 6.0 in gray, highlighting most hospitals scoring above median with several reaching 10 out of 10.

Figure 2. MVC’s P4P PY 2025 Scoring Breakdown by Episode Spending and Value Metric Selections

Horizontal bar chart comparing PY 25 episode spending scores and value metric scores across medical conditions and procedures. Spending scores range from 1.5 for Pneumonia to 2.9 for CABG, while value metric scores range from 2.0 for 7-day follow-up after Pneumonia to 3.7 for Preoperative Testing, with mean and median values indicated for each group.

Figure 3. MVC’s P4P PY 2025 Engagement Point Distribution

Scatter plot showing engagement scores of MVC hospitals participating in PY 24-25 program, with individual hospital scores represented by blue dots and a mean score of 1.8 marked by an orange horizontal line. Most hospitals achieve or exceed the mean score, with several reaching the maximum score of 2.0, indicating high engagement levels across participants.

After reviewing hospital performance in 2025, Bradshaw looked to the PY 2026-2027 cycle, announcing a one-time alternative point opportunity for PY 2026 to earn credit for MVC’s new health outcome variation (HOV) metric. Additional details on submission requirements and timelines will be announced to site coordinators in the coming weeks. Following this, he noted the many opportunities to earn engagement points remaining in calendar year 2026 including virtual workgroups, networking dinners, and MVC’s fall collaborative-wide meeting in Livonia. For a complete schedule of events and registration, please visit MVC’s events webpage. Bradshaw reminded members that PY 2026 mid-year scorecards are expected in Q3 2026, and hospitals will be asked to make metric selections for PYs 2028-2029 in Q4 2026.

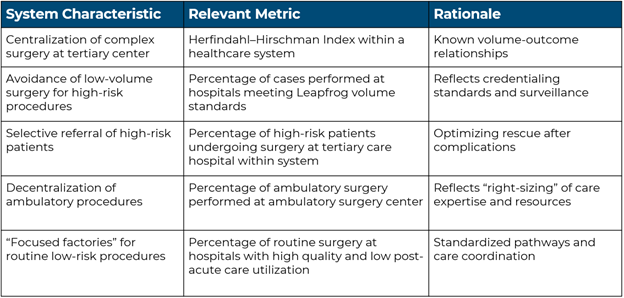
The meeting then featured an MVC data presentation by MVC Medical Director Hari Nathan, MD, PhD, and MVC Analyst Janet Zhang, MPH, on reporting and benchmarking outcomes across Michigan health systems. Dr. Nathan began with a discussion on the gradual, structural shift over the last two decades from independent ownership towards health system affiliation, noting that Michigan has outpaced national averages for system affiliation. He then reviewed the current state of MVC’s system-level reporting and outlined other measures of system variation from the literature not currently utilized in MVC reporting (Figure 4), emphasizing the need for MVC and its membership to co-design a path for measuring system-level quality in the future.

Zhang supplemented the presentation by sharing unblinded data on variation in hospital-level risk-adjusted 30-day readmission rates within hospital systems. She outlined traditional methods of showcasing variation using caterpillar plots and demonstrated how MVC might leverage hospital-level data to calculate a single index value for systems to support tracking variation over time. Zhang and Dr. Nathan both emphasized the importance of considering quality in outcomes and variation in outcomes as they evaluate their system-level performance.

Figure 4. Sample Approaches to Measuring System Variation

Table presenting system characteristics, relevant metrics, and rationales for surgical care quality assessment. It includes metrics like Herfindahl–Hirschman Index for centralization, case volume percentages for surgery avoidance and selective referral, and ambulatory surgery distribution, highlighting standards, care optimization, and resource allocation.

Building on the data presentation, a panel discussion led by Dr. Nathan further explored what “systemness” and system quality of care mean in practice and how stronger integration can improve quality, outcomes, and access across health systems and networks. Panelists included Alex Callaway, MBA, CPHQ, CPPS, Regional Quality Director of Munson Health System; Emily Nerreter, MBA, CPC, CRC, Pay for Performance & Registries Manager of Henry Ford Health System; and Stephanie Pins-Schallip, MSA, CPHQ, Director of Value Analysis & Enhancement of MyMichigan Health. Each panelist brought unique perspectives and experience to the discussion, presenting compelling evidence to support the optimization of system-level resources, data, and cooperation.

Attendees then spent the remainder of the morning in breakout sessions [see breakout session slides] learning from peers, sharing intervention success stories, and brainstorming approaches to measuring quality in both small, stand-alone hospitals and large multi-hospital systems:

  • Catalyst Community for Improvement: Transforming Performance Together (Corewell)
  • Roadmap to Building Strong Post-Acute Care Network (Trinity Health Alliance)
  • Developing a Heart Failure Care Management Program (Trinity Health IHA)
  • Rural & Critical Access Hospital Claims Data Reporting Strategies (MVC)
  • Advancing System-Level Quality Improvement: Exploring Concepts for New MVC Metrics (MVC)

Following a networking lunch and a second session of breakouts, attendees came back together for the presentation of MVC awards by Engagement Manager Jessica Souva, MSN, RN, C-ONQS. The 2025 Engagement Award recipients included:

  • Henry Ford Health – 2025 Most Engaged System
  • Primary Care Partners, Inc. - 2025 Most Engaged Physician Organization
  • Scheurer Health – 2025 Most Engaged Critical Access Hospital
  • University of Michigan Health-West – 2025 Most Engaged General Acute Care Hospital

Souva also announced the winner of the poster contest, which was identified through member voting during the afternoon poster session. University of Michigan Health – Sparrow Carson won “best poster” for their “Rural Sepsis Initiative: Timely Care, Better Outcomes” poster submission. The poster was presented by Sara Hagerman, BSN.

The meeting closed with a reflection of the day’s themes and sessions, and reminders about upcoming meetings and events.

What are attendees saying about the meeting?

“The interactive sessions were great, and so was the location.”

“Today was a really great day, filled with a lot of discussion, networking and interactive activities.”

“This was my first meeting. I appreciate the information shared and opportunity.”

“I liked the panel discussion today. In the past, I also like the different tables of presenters to allow for smaller group discussion. Overall, lots of good discussion on how to work in a system.”

“Always love coming to MVC collaborative wide meetings as they’re so informative and a great way to network with others who have the same or very similar goals and outcomes!”

“The information presented was highly applicable across systems and independents.”

If you have questions about any of the topics discussed at MVC’s spring collaborative-wide meeting or are interested in following up for more details, please email the MVC Coordinating Center. MVC’s next collaborative-wide meeting will be held in person on Fri., Oct. 9, 2026, in Livonia, Michigan.

Off
View Post
Spring Collaborative-Wide Meeting Agenda, Speakers Announced

Spring Collaborative-Wide Meeting Agenda, Speakers Announced

The MVC Coordinating Center is excited to announce the agenda for its spring collaborative-wide meeting on Friday, May 8, 2026, from 10 a.m. – 3 p.m., at the Grand Traverse Resort & Spa in Acme, MI. This meeting’s theme is “From Innovation to Impact: Advancing Care Across Health Networks” and will highlight the various ways in which MVC's members collaborate across health systems and networks to advance the quality of healthcare across Michigan. Those interested in attending MVC's spring 2026 collaborative-wide meeting must register here by Tues., April 21.

MVC Director Mark Bradshaw, MSc, will kick off the day with updates on MVC’s Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This will be followed by an MVC Data in Action presentation by MVC Medical Director, Hari Nathan, MD, PhD, and MVC Data Analyst, Janet Zhang, MPH.

Dr. Nathan will then invite system representatives from Munson Health System, Henry Ford Health System, and MyMichigan Health System to join him on stage for a panel discussion titled “Elevating Quality Across an Integrated Health Network”.  Nathan will lead the panelists and attendees through a discussion on addressing barriers to health care improvements and measuring success across health systems and networks.

Attendees will then transition to their first breakout session before lunch and networking. The second breakout session will occur following lunch and networking. The five breakout topics will cover:

  • Corewell Health’s system-level approach to performance improvement
  • The development of Trinity Health IHA Medical Group’s Heart Failure Care Management Program
  • Trinity Health Alliance of Michigan’s Post-Acute Care Network
  • An exploration of new concepts for MVC metrics to support Advancing System-Level Quality Improvement
  • Rural and Critical Access Hospital Claims Data Reporting Strategies

View a summary of the breakout presentations using this LINK.

MVC’s Engagement Manager, Jessica Souva, MSN, RN, C-ONQS, will close out the day presenting MVC members with MVC’s second annual engagement awards and next steps for MVC’s Component of the BCBSM P4P Program.

The deadline to register for MVC’s spring 2026 collaborative-wide meeting is Tues., April 21. We look forward to seeing you there!

Off
View Post
Reducing Unnecessary Preoperative Testing: Progress on RITE-Size Partnership

Reducing Unnecessary Preoperative Testing: Progress on RITE-Size Partnership

For many patients preparing for surgery, the process begins long before they enter the operating room. Blood tests, lab visits, and diagnostic screenings often become routine steps in preoperative care—even for patients undergoing low-risk procedures. In many cases, these tests add extra appointments and costs without changing how care is delivered.

Research suggests that as many as one in three patients evaluated for low-risk surgery receive tests that are not clinically necessary, and those results rarely influence clinical decisions. Improving the appropriateness of testing is therefore an important opportunity to improve the patient experience while reducing inefficiencies in surgical care.

For the last few years, the Michigan Value Collaborative has engaged its suite of offerings – from dedicated registry pages and push reports to workgroups and performance-based incentives – to support hospitals across the state in aligning their preoperative protocols with evidence-based guidelines.

Progress on the RITE-Size Trial

Another key component in the success of improved preoperative testing appropriateness in Michigan is the Right-Sizing Testing Before Elective Surgery (RITE-Size) trial, supported by the Michigan Program on Value Enhancement (MPrOVE), the Michigan Surgical Quality Collaborative (MSQC), the Anesthesiology Performance Improvement and Reporting Exchange (ASPIRE), and MVC.

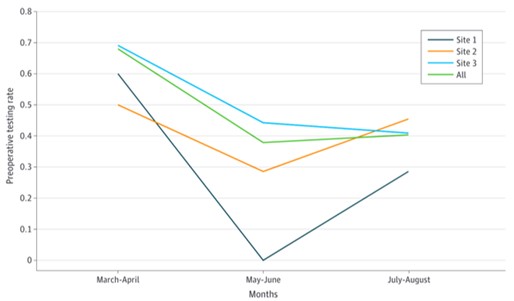
RITE-Size is an Agency for Healthcare Research and Quality (AHRQ)-funded, multi-institutional quality improvement trial. RITE-Size launched a pilot in March 2024 at three hospitals in Michigan. The study aimed to meet criteria in several areas such as feasibility (implementation in the appropriate amount of time), testing rates (reduction), and acceptability and appropriateness (results from interviews). By August 2024, the desired milestones had been achieved, showing a 68% average reduction in unnecessary testing by the three participating sites (Figure 1). All three sites saw significant decreases in their testing rates following implementation of the multi-component intervention.

Figure 1. MVC RITE-Size Pilot Program Testing Rates Over Time Across All Three Sites from March-April 2024 to July-August 2024

line graph depicting reduction in unnecessary preoperative testing at three pilot sites

This was followed by a larger trial in 2025 with six new hospitals. Each site participated in a site visit, personalized coaching, and evaluation of their data in consultation with the RITE-Size team to guide on-site efforts to improve the appropriateness of their preoperative testing. In 2026, the RITE-Size partners are looking to enroll 12-15 hospitals and ambulatory surgery centers (ASCs) across Michigan.

Along the way, some of the successes, tools, and challenges from sites participating in the trial have been featured in MVC’s preoperative testing workgroups, where clinical and quality leaders have come together to learn from one another and share best practices. In one of those recent workgroups, for example, Lake Huron Medical Center shared insights into their experience in the trial and its impact on their preoperative protocols. A collated list of MVC’s preoperative testing workgroups can be found on MVC’s YouTube channel.

The work is also contributing to the broader evidence base on reducing low-value care. Nicole Mott, MD, MSCR, a National Clinician Scholar at the University of Michigan supported by the Veterans Administration and a general surgery resident at the University of Colorado, was the lead author on a recently published paper in JAMA Network Open that described the components and impact of the trial.

Leveraging Partner Operations for Recruitment

Over the past year, the RITE-Size partnership has worked to strengthen alignment between the trial’s activities with those operational activities of the partner organizations.

For instance, participation in the RITE-Size initiative is now tied to MSQC’s BCBSM P4P scorecard for preoperative testing, allowing hospitals to receive credit toward their scorecard by engaging in the initiative. MVC is also leveraging its new ambulatory surgery center (ASC) dataset to identify additional sites beyond the hospital setting that may benefit from participating in the initiative, with recruitment efforts under way with six eligible ASCs. Three new hospitals joined the trial at the start of 2026, and additional sites are engaged in conversations and related information sessions as they consider participating.

Supporting Hospitals in Practice Change

Participating hospitals are approaching preoperative testing improvement from a variety of starting points. For some, the initiative has helped validate practices that were already evolving. For others, it has created an opportunity to revisit long-standing protocols and bring them in line with current evidence.

At Lake Huron Medical Center, participation in the RITE-Size initiative helped uncover an important opportunity for improvement. While staff had already begun reducing unnecessary preoperative testing in practice, the hospital discovered that its formal documentation had not kept pace with these changes. The pre-anesthesia testing protocol used by staff still included outdated materials and handwritten updates accumulated over time.

Through the collaborative work of the RITE-Size initiative, the hospital was able to review and modernize its protocol, ensuring that documentation reflects current practice and provides clear guidance for clinical teams. This type of operational refinement—aligning written protocols, data reporting, and frontline practice—is a common step for organizations working to improve the appropriateness of preoperative testing.

Kelly Lewton, RN, BSN quote

The collaborative structure of the initiative has also proven valuable. Participating hospitals are able to share implementation strategies, learn from peers facing similar challenges, and access guidance from project partners as they refine their approaches.

Looking Ahead

As this work continues, MVC is also using its claims-based data to examine the broader impact of reducing unnecessary testing. The MVC Coordinating Center is currently partnering with MSQC to explore the impact and value of MSQC’s preoperative testing metric since its inclusion in their scorecard. The aims of this analysis are to better understand the statewide improvement in the measure as well as the potential financial and operational benefits associated with improvements.

Insights from this analysis will help the RITE-Size partners better understand the impact of an incentive-based measure on testing outcomes as well as related cost savings that may accompany on-the-ground improvements.

As the RITE-Size trial continues into its next phase, the trial partners remain committed to supporting hospitals through shared data, collaborative learning, and practical implementation resources. Together, these efforts aim to ensure that preoperative testing is used when it adds clinical value.

Hospitals interested in learning more about their preoperative testing rates and opportunities can contact the MVC team.

Off
View Post
Celebrating 2025 Successes and Setting the Stage for 2026

Celebrating 2025 Successes and Setting the Stage for 2026

On behalf of the MVC Coordinating Center, let me first start this end-of-year blog by thanking you all for your partnership and continued support throughout 2025. In case you blinked and its now December – don’t worry, you’re not alone! The last year has flown by with plenty of twists and turns along the way. Before we get caught up in the holidays and planning for 2026, we wanted to step back and celebrate the successes we achieved together over the last 12 months.

In writing my reflection piece last year, I highlighted that both our engagement participation and analytics utilization were far above previous years. While this gave us a hard act to follow, we are delighted to share that this trend continued upwards in 2025. Over the last year, we welcomed two new hospital members to the collaborative, delivered 23 virtual workgroups with an average attendance of 41, facilitated 24 different member presentations, completed 9 site visits, delivered 14 custom analytic requests, and supported 106 new users in gaining access to our online registry. On top of all of this, we held two collaborative wide meetings in Midland and Livonia, with 197 member representatives joining us to share stories, spotlight successes, and support one another in navigating all of the challenges which 2025 decided to bring.

These flagship numbers only tell one part of the story; the true value of each of the activities detailed above comes from the relationships and partnerships developed as a result of the time spent together. We hope you all have taken as much benefit from these collaborations as our group has during this time. Which brings me to another highlight…the MVC Coordinating Center. Let’s take a moment to celebrate the people who not only help make all of the above possible but that make this such a great place to work. Thank you to the entire MVC team for your hard work and commitment to supporting our members throughout 2025. I’m excited for what the next year will hold. Speaking of which, here’s a sneak peek of a few things that will be taking place in 2026.

Collaborative Wide Meetings, Networking Events, and Virtual Workgroups

MVC’s 2026 engagement events calendar is now live. Our spring collaborative wide meeting will take place on Friday, May 8 in Traverse City and we will be returning to Livonia for our fall meeting on Friday, October 9. These forums continue to be supported by virtual and in-person networking activities and dinners throughout the year, and dates for our regular suite of virtual workgroups can also be found on the 2026 calendar. Save the dates - we look forward to seeing you at each of these events!

MVC Site Visits

We visited a number of you in 2025, providing the opportunity to strengthen our understanding of member activities, priorities, and system-level practices. This effort will continue next year, and members can participate in these site visits in either a virtual or in-person capacity, with P4P engagement points on offer for taking part. If you are interested in getting on the calendar for 2026, please don’t hesitate to reach out.

MVC Site Engagement Coordinator Education Program

In response to member feedback, MVC will be launching a new Site Coordinator Education Program in 2026, designed to offer a flexible, individualized, rolling training curriculum to provide members with a stronger understanding of MVC data, share tools to help evaluate metric progress, and facilitate peer collaborations. This program is in high demand with capacity already met for the first round of registration. Additional opportunities to participate in this new education program will open throughout the calendar year – more communications to follow!

New MVC Component of the BCBSM P4P Program PY26/27 Registry Pages & Webinars

As with previous cycles, new P4P pages will be launched at the turn of the year to correspond with the changes implemented for PY26/27. These pages will look and feel similar to those currently available with a few important updates to reflect changes to our episode spending and value metric menu options and the introduction of MVC’s new Health Outcome Variation Measure. The latter reflects a new metric to the MVC Component, and to support members in navigating and utilizing these new registry pages, dedicated explainer webinars will be held in January.

MVC Push Reports and Custom Analytics

As highlighted above, MVC’s push reports and offer of custom analytics were well utilized by members in 2025, and to reflect member feedback, efforts will be spent strengthening this offering for member benefit in 2026. Remember, if you are interested in working with the Coordinating Center on a custom build, reach out to us by email. [LINK]

Thank you again for your continued partnership throughout the last year and we look forward to more successes in 2026. Have a great holiday and a happy new year when it rolls around.