Off
View Post
Reducing Unnecessary Preoperative Testing: Progress on RITE-Size Partnership

Reducing Unnecessary Preoperative Testing: Progress on RITE-Size Partnership

For many patients preparing for surgery, the process begins long before they enter the operating room. Blood tests, lab visits, and diagnostic screenings often become routine steps in preoperative care—even for patients undergoing low-risk procedures. In many cases, these tests add extra appointments and costs without changing how care is delivered.

Research suggests that as many as one in three patients evaluated for low-risk surgery receive tests that are not clinically necessary, and those results rarely influence clinical decisions. Improving the appropriateness of testing is therefore an important opportunity to improve the patient experience while reducing inefficiencies in surgical care.

For the last few years, the Michigan Value Collaborative has engaged its suite of offerings – from dedicated registry pages and push reports to workgroups and performance-based incentives – to support hospitals across the state in aligning their preoperative protocols with evidence-based guidelines.

Progress on the RITE-Size Trial

Another key component in the success of improved preoperative testing appropriateness in Michigan is the Right-Sizing Testing Before Elective Surgery (RITE-Size) trial, supported by the Michigan Program on Value Enhancement (MPrOVE), the Michigan Surgical Quality Collaborative (MSQC), the Anesthesiology Performance Improvement and Reporting Exchange (ASPIRE), and MVC.

RITE-Size is an Agency for Healthcare Research and Quality (AHRQ)-funded, multi-institutional quality improvement trial. RITE-Size launched a pilot in March 2024 at three hospitals in Michigan. The study aimed to meet criteria in several areas such as feasibility (implementation in the appropriate amount of time), testing rates (reduction), and acceptability and appropriateness (results from interviews). By August 2024, the desired milestones had been achieved, showing a 68% average reduction in unnecessary testing by the three participating sites (Figure 1). All three sites saw significant decreases in their testing rates following implementation of the multi-component intervention.

Figure 1. MVC RITE-Size Pilot Program Testing Rates Over Time Across All Three Sites from March-April 2024 to July-August 2024
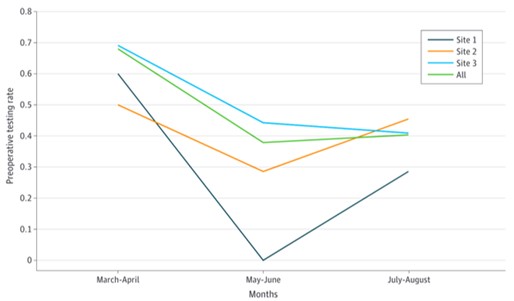
line graph depicting reduction in unnecessary preoperative testing at three pilot sites

This was followed by a larger trial in 2025 with six new hospitals. Each site participated in a site visit, personalized coaching, and evaluation of their data in consultation with the RITE-Size team to guide on-site efforts to improve the appropriateness of their preoperative testing. In 2026, the RITE-Size partners are looking to enroll 12-15 hospitals and ambulatory surgery centers (ASCs) across Michigan.

Along the way, some of the successes, tools, and challenges from sites participating in the trial have been featured in MVC’s preoperative testing workgroups, where clinical and quality leaders have come together to learn from one another and share best practices. In one of those recent workgroups, for example, Lake Huron Medical Center shared insights into their experience in the trial and its impact on their preoperative protocols. A collated list of MVC’s preoperative testing workgroups can be found on MVC’s YouTube channel.

The work is also contributing to the broader evidence base on reducing low-value care. Nicole Mott, MD, MSCR, a National Clinician Scholar at the University of Michigan supported by the Veterans Administration and a general surgery resident at the University of Colorado, was the lead author on a recently published paper in JAMA Network Open that described the components and impact of the trial.

Leveraging Partner Operations for Recruitment

Over the past year, the RITE-Size partnership has worked to strengthen alignment between the trial’s activities with those operational activities of the partner organizations.

For instance, participation in the RITE-Size initiative is now tied to MSQC’s BCBSM P4P scorecard for preoperative testing, allowing hospitals to receive credit toward their scorecard by engaging in the initiative. MVC is also leveraging its new ambulatory surgery center (ASC) dataset to identify additional sites beyond the hospital setting that may benefit from participating in the initiative, with recruitment efforts under way with six eligible ASCs. Three new hospitals joined the trial at the start of 2026, and additional sites are engaged in conversations and related information sessions as they consider participating.

Supporting Hospitals in Practice Change

Participating hospitals are approaching preoperative testing improvement from a variety of starting points. For some, the initiative has helped validate practices that were already evolving. For others, it has created an opportunity to revisit long-standing protocols and bring them in line with current evidence.

At Lake Huron Medical Center, participation in the RITE-Size initiative helped uncover an important opportunity for improvement. While staff had already begun reducing unnecessary preoperative testing in practice, the hospital discovered that its formal documentation had not kept pace with these changes. The pre-anesthesia testing protocol used by staff still included outdated materials and handwritten updates accumulated over time.

Through the collaborative work of the RITE-Size initiative, the hospital was able to review and modernize its protocol, ensuring that documentation reflects current practice and provides clear guidance for clinical teams. This type of operational refinement—aligning written protocols, data reporting, and frontline practice—is a common step for organizations working to improve the appropriateness of preoperative testing.

Kelly Lewton, RN, BSN quote

The collaborative structure of the initiative has also proven valuable. Participating hospitals are able to share implementation strategies, learn from peers facing similar challenges, and access guidance from project partners as they refine their approaches.

Looking Ahead

As this work continues, MVC is also using its claims-based data to examine the broader impact of reducing unnecessary testing. The MVC Coordinating Center is currently partnering with MSQC to explore the impact and value of MSQC’s preoperative testing metric since its inclusion in their scorecard. The aims of this analysis are to better understand the statewide improvement in the measure as well as the potential financial and operational benefits associated with improvements.

Insights from this analysis will help the RITE-Size partners better understand the impact of an incentive-based measure on testing outcomes as well as related cost savings that may accompany on-the-ground improvements.

As the RITE-Size trial continues into its next phase, the trial partners remain committed to supporting hospitals through shared data, collaborative learning, and practical implementation resources. Together, these efforts aim to ensure that preoperative testing is used when it adds clinical value.

Hospitals interested in learning more about their preoperative testing rates and opportunities can contact the MVC team.

Off
View Post
MVC Virtual Networking Event: Relational Coordination in Healthcare Quality Improvement

MVC Virtual Networking Event: Relational Coordination in Healthcare Quality Improvement

In February, MVC hosted its first virtual networking event of 2026 with a special presentation on relational coordination by MVC Project Manager Emily Woltmann, PhD, MSW, and Richard Wylde, MSc, Deputy Director of Improvement at Leeds and York Partnership, National Health Service (NHS) Foundation Trust. With more than 45 attendees, the event introduced members to relational coordination, a framework that can be used to evaluate and strengthen collaboration and teamwork in healthcare settings. Following presentations, participants joined breakout groups to discuss the content and complete a case study activity, followed by a debrief and wrap up discussion. 

Overview of Relational Coordination  

Woltmann kicked off the event with an introduction to relational coordination, which was first introduced by Jody Hoffer Gittell as a mutually reinforcing process of communicating and relating for the purpose of task integration. She introduced participants to the relational coordination framework developed by Braneis University’s Relational Coordination Collaborative (RCC), which showcases how relationships and communication continuously reinforce each other in positive and negative ways. In relational coordination, the main components being considered are whether communication that occurs is happening in a frequent, timely, and accurate manner and is being used with the intention of problem-solving; while relational components reference shared goals and knowledge rooted in mutual respect. 

Relational coordination is a dynamic theory, where many areas influence each other. In addition to communication and relational components, the full framework (Figure 1) describes the types of structural, relational, and work process interventions that may impact communication and relationships to impact downstream outcomes. 

Figure 1. RCC’s Dynamic Theory of Coordination

flow chart

Structural interventions are implemented by leadership roles and include things like shared meetings, huddles, information systems, and boundary spanner roles that cross over multiple departments. Relational interventions focus on directly improving ways people relate to each other, such as cultivating safe spaces for discussion. Finally, work process interventions focus on workflows and sometimes use plan, do, study, act (PDSA) cycles for improvement.

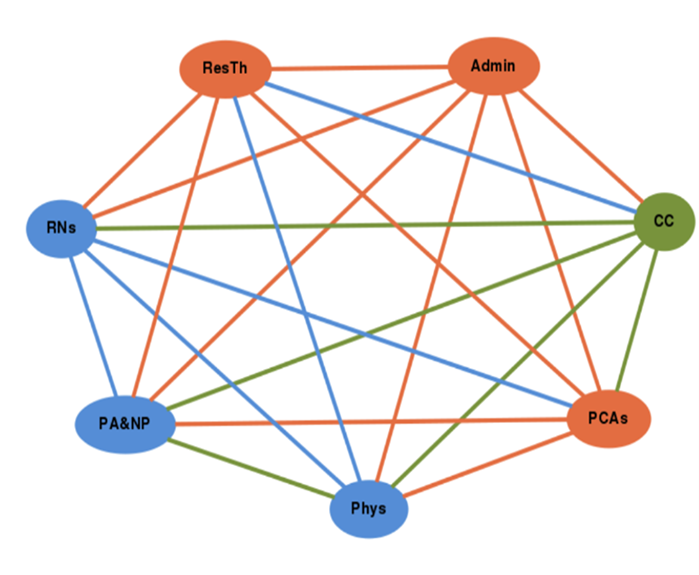
Woltmann highlighted some of the methods available for measuring relational coordination, including a validated quantitative survey to measure role-based coordination between team members. The survey can help evaluate how well relational coordination is working between different roles. Another measurement tool that can be used is relational coordination mapping (Figure 2), which is a visual way to view responses from the relational coordination survey and summarize the strength of relationships between groups. It is designed to encourage deeper engagement and reflection among participants.

Figure 2. Measuring Relational Coordination: Relational Coordination Mapping

Relational Coordination Mapping using a line matrix

Woltmann explained that when relational coordination is working well and is strong, it supports organizations in achieving a wide range of desired performance outcomes such as quality, safety, efficiency, staff well-being, learning, and innovation.

The Maryland and Michigan DECIPHeR Project - Relational Coordination in Community Mental Health Settings

Woltmann also discussed lessons and insights she gleaned about relational coordination from the Maryland and Michigan DECIPHeR Project, which focuses on implementing interventions that decrease cardiovascular disease (CVD) risk factors in people with serious mental illness. Led by Dr. Amy Kilbourne, PhD, MPH, in the Department of Learning Health Sciences at the University of Michigan, and Dr. Gail Daumit, MD, MHS, at Johns Hopkins University, the project focuses on identifying effective interventions shown to address CVD risk factors in persons with a serious mental illness. This broader implementation trial is researching ways to implement a new intervention called IDEAL GOALS in behavioral health homes (BHHs).

While analyzing the qualitative data for this needs assessment phase of the project, Woltmann and colleagues became interested in using relational coordination to understand relational aspects of care coordination in the BHH context. The sample for this study included 14 sites across Michigan and Maryland, with 14 nurses and 32 frontline staff. Sites were given a qualitative designation of “consistently positive” relational coordination, “consistently negative” relational coordination, or “mixed” relational coordination.

Of the 14 sites, Woltmann said five had a consistently positive relational coordination level, six had a consistently negative level, and three had a mixed result. The research team found that sites with consistently positive relational coordination had a variety of structural factors in place to support RC. Boundary spanner roles were seen as particularly important in achieving good relational coordination, as they take on the role that crosses the gap in care for patients – in this instance community mental health staff to primary care providers. Results from the study indicated there were many kinds of strategies that sites used to develop functional RC, and that the most imperative component to building positive relationships was having a strong sense of trust.

Relational Coordination in Mental Health Services – The National Health System

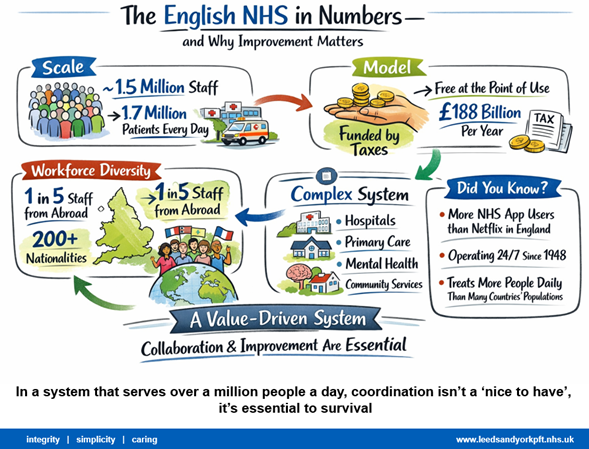
Following Woltmann’s presentation, Richard Wylde, Deputy Director of LYPFT, provided participants with an in-depth look at how relational coordination is being utilized in his work at the National Health System (NHS) of England and emphasized how important coordination is in a large healthcare system. The NHS employs 1.5 million staff to care for roughly 1.7 million patients daily. With a tax funded healthcare model, each patient’s care is financially covered (£188 Billion per year) (Figure 3).

Figure 3. The English NHS in Numbers and Why Improvement Matters

Illustration of why improvement matters in healthcare

The NHS has a complex system of hospitals, primary care clinics, mental health clinics, and community services. Wylde is a part of the Leeds and York Partnership NHS Foundation Trust (LYPFT) which provides specialist mental health and learning disability services to the people in Leeds West Yorkshire, England. They have 48 locations, including 408 beds, see over 25,000 new patients, and have contact with over 270,000 people in the community per year.

Wylde shared that the NHS relationship coordination journey began with senior leadership who had previous experience with relational coordination, introducing the concept and promoting it to other leaders and the board. He recounted that there was slow organizational uptake of relational coordination theory within the system initially. However, as other leadership saw the benefits, they were able to implement strategies at other organizational levels.

Within the community mental health services system, the LYPFT program wanted to look at how young people transition to adult mental health services. They found that it was important to provide a safe space for players in the system to come together to better coordinate this process, and to be mindful of the many different perspectives and power imbalances present. One of the barriers they experienced, Wylde said, was the difficulty in balancing the need for human relationships and trust building timelines versus the systems' need for quick answers.

Wyle highlighted several key lessons learned through implementing relational coordination at multiple levels of a system, including:

  1. Governance at the board level can have limitations on time for developing a relational space
  2. Relational coordination worked best when senior leaders had a collectively shared understanding of what relational coordination was and how they could use it
  3. Relational coordination was more successful when it had clear framing and context to the program/service/team
  4. It was important for all levels to understand how the relational coordination dynamic functions at the smallest level of a system (between people)
  5. Relational coordination is both a relationship and a process
  6. Strong relationships enable strong processes and vice versa

Breakout Session Debrief

During the breakout session portion of the networking event, participants were guided through a patient case study that demonstrated how breakdowns in staff communication and relationships could negatively impact patient outcomes. The breakout groups had engaging conversations that focused on building trust, relational coordination interventions, explaining the “why” to help teams develop shared goals, understanding the impact of staff-to-patient ratios on communication, and other tools and frameworks that have helped teams improve their communication.

MVC was glad to highlight this topic and the expertise of these presenters to support shared learning and continuous improvement within healthcare teams. MVC welcomes presenters to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members, which cultivates a community of peers looking to collaborate in a non-competitive space. Please reach out to MVC by email if you are interested in being a presenter or submit a presentation proposal online.

Off
View Post
February Workgroup Highlights Increasing Cardiac Rehabilitation Utilization with a Member Panel and MVC Data

February Workgroup Highlights Increasing Cardiac Rehabilitation Utilization with a Member Panel and MVC Data

In February, the Michigan Value Collaborative (MVC) hosted a virtual cardiac rehabilitation workgroup presentation featuring a panel of cardiac care specialists. The panel focused on discussing chronic heart failure metrics related to the pay for performance (P4P) program and how cardiac rehabilitation (CR) can play a vital part in the recovery process for congestive heart failure (CHF) patients. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Cardiac Rehabilitation Workgroup – MVC and Member Panel 

For this workgroup MVC was joined by panelists Tyelor Wymer, CEP, BS, Cardiology Supervisor at University of Michigan Health (UMH) Sparrow-Clinton; Laura Meiste, RN, BSN, Manager of Cardiac and Pulmonary Rehabilitation at Holland Hospital; Zach Johnson, BS, ACSM-CEP, Lead Exercise Physiologist for Cardiac and Pulmonary Rehabilitation Programs at Corewell Health; Greg Scharf, BS, CEP, CCRP, Cardiopulmonary Rehabilitation System Manager at MyMichigan Health; and Mike Thompson, PhD, MPH, Associate Professor of Cardiac Surgery at Michigan Medicine

CHF Goals and Metrics

MVC’s Site Engagement Coordinator Emily Bair, MS, MPH, RDN, CSP, began the workgroup by reviewing CHF P4P metrics for program years 2026 – 2027, which is part of MVC’s Cardiac Rehabilitation Value-Based Initiative. These included an episode spending metric focused on CHF episodes of care and a value metric that tracks the 7-day follow up care for CHF episodes of care. In addition to discussing the P4P CHF metrics, Bair reviewed current CR standards that MVC uses for measuring the CR value-based initiative, including Michigan Cardiac Rehabilitation Network (MiCR) standards and the Million Hearts Campaign CR goal for CHF patients (Figure 1).

Figure 1. MVC, MiCR and Million Hearts CR Goals for CHF Patients

Presentation slide titled "Goals & Metrics" outlining cardiac rehabilitation follow-up and start rate targets. It lists MVC P4P Metrics with a 7-day follow-up after CHF, Michigan Cardiac Rehab Network aiming for 10% of CHF patients to start CR within 365 days, and Million Hearts with ACC and AHA targeting 70% of eligible patients to start CR within 365 days.

MVC Registry and Data Reports Resources

Bair highlighted some of MVC’s relevant data reports and how the episodes of care are built within the MVC data registry. Bair noted that MVC episodes of care have a slightly different post-discharge window for CHF patients in CR, 365 days (Figure 2), versus the 30 – 90-day windows for patients with cardiac conditions such as percutaneous coronary intervention (PCI)/coronary artery bypass grafting (CABG). The MVC data registry has several useful cardiac related reports including,

Multi-payer CR reports which evaluate CR utilization and other metrics provided in MVC’s hospital-level reports:

  • CR Utilization Rates
  • CR Utilization Rankings
  • Mean Days to First CR Visit
  • Mean Number of CR Visits

Payer specific reports which allow registry users to investigate utilization, readmissions rates, and cost of care including:

  • Episode Payment Report
  • Episode Utilization Rate Report
  • Readmissions Report
  • CR Report

Figure 2. Example of MVC Registry CR Utilization Rate within 365 Days After Discharge for CHF, Jan. 2024 – Mar. 2025 (MVC All, blinded):

Dotted line graph

The graph above shows that from Jan. 2024 – Mar. 2025, the MVC All average was  6% for CR participation within 365-days post-discharge for CHF patients. With the MiCR goal being a 10% CR utilization for CHF patients and the overall utilization range being 0% to 19%, it is clear there is room for improvement across the MVC member portfolio.

Push reports are another useful resource offered by MVC. The Process Measures Report that MVC shared with members in January 2025 had helpful visuals of site and system 7-day follow up data for CHF episodes of care (Figure 3).

Figure 3. MVC Process Measures Report – 7-day follow up after CHF

example of MVC Process Measures Report for 7-Day Follow-Up After CHF content including vertical bar charts and line graphs

Panel Discussion

The focus for the panel discussion centered around how CR services can be utilized to support rehabilitation of CHF patients who may not be able to participate in rehabilitation as quickly as those that have conditions such as PCI or CABG. Bair began the discussion by leading participants through a common care pathway for CHF patients who utilize CR (Figure 4).

Figure 4. CHF Follow-Up and Cardiac Rehabilitation Typical Patient Pathway

Diagram illustrating the typical CHF patient pathway with five key stages: Admission, Discharge, Follow-Up, Cardiac Rehab, and Readmission. Annotations highlight transitions such as patient diagnosis, care shift from inpatient to outpatient, appointment scheduling, referral placement, and follow-up care including rehab and emergency department utilization.

CHF Barriers to Care and Change Concepts

To help organize a solutions-based approach, Bair went on to introduce the Change Concepts Model, 2nd Ed. (Figure 5) adapted from the Million Hearts Initiative to address some of the common barriers seen in CHF care.

From the Million Hearts Change Package, 2nd Ed., some notable barriers to care for CHF follow-up in CR include:

  • Patient or provider lack of awareness
  • Lack of clear and consistent communication
  • No integration of CHF cardiac rehabilitation needs into cardiovascular services or workflows
  • Limited capacity of CR programs
  • Patient transportation, financial burden, competing responsibilities or cultural/language barriers

Figure 5. Million Hearts Change Concepts

Flowchart illustrating four stages of a process: Systems Change, Referrals, Enrollment and Participation, and Adherence.

Systems Level Change

Bair shared some of the ways systems change could be implemented including establishing a hospital CHF champion, engaging hospital administrators and senior staff, securing and maintaining a multidisciplinary workforce, engaging the cardiac care team in the follow-up care and rehabilitation planning, tracking follow-up/CR referrals, enrollment rates, and patient participation as quality-of-care indicators.

UMH Sparrow-Clinton’s Tyelor Wymer shared that they have had success with appointing CHF champions in their centralized cardiac care team. Team members rotate through four to five different UMH Sparrow hospitals, fostering consistent care practices across the health system. MyMichigan Health System’s Greg Scharf shared that they have a similar system wide collaborative team for heart failure care, and they have had great success as well.

At Holland Hospital, Laura Meiste shared that they have a care transitions team that works in the cardiology department and focuses specifically on patient follow-up within seven days of discharge, while also working on maintaining consistent communication with the administrative staff that schedules patient appointments.

Optimizing Referrals

Another opportunity to reduce barriers to care is by improving the referral process itself. This can be done by using data to drive improvements and incorporating referrals into standardized processes. Some examples include:

  • Adding CHF cardiac rehabilitation language to echo reports for patients with reduced ejection fraction (EF) that meet the appropriate criteria for CR
  • Including a referral to CR in order sets for patients with CHF
  • Adding CR to guideline-directed medical therapy algorithms for patients with CHF

Scharf shared that optimizing referrals is an ongoing challenge in MyMichigan Health’s system where there might be a standardized best practice advisory (BPA) for CHF in general, but there is no built-in trigger for flagging a CHF case as CR appropriate. Working in the Epic electronic health record (EHR) program, they can create custom BPAs for this, but it takes time and education.

Meiste shared that at Holland Hospital, an auto-referral process through an order set triggers a case in the system to be sent to clinical staff for CR eligibility screening. If the case meets eligibility criteria, the staff will set up an in-person visit with the patient. Similarly, workgroup participant Karolina Kaser, BSN, RN, MBA, CIC, Quality, Safety and Experience Director for Corewell Health Dearborn, shared that their site utilizes standardized clinical pathways for their cardiac cases. Included in the pathway is an order set that automatically includes a CR referral even for CHF cases. Some other effective processes have been to utilize the cardiac nurses to ensure CHF patients have CR offered if they meet criteria, as well as training administrative and call center staff on the importance of scheduling these follow-up appointments.

Enrollment and Participation

Increasing enrollment is a key goal in the Million Hearts change concept. This may include methods of optimizing care coordination for patients by promoting enrollment into CR at follow-up appointments and reducing delay from discharge to their first CR appointment. This can be done by using data to drive improvement in follow-up appointments and enrollment numbers, and by developing flexible delivery models such as hybrid CR programs. MiCR tools and resources also help to boost CR enrollment.

Supporting Adherence and Reducing Non-Medical Barriers

The next step in the change concept process is finding ways to reduce inconsistent adherence to a CR program. Some recommendations to address this issue included identifying populations at risk for low engagement, accounting for patient needs such as lack of transportation, incorporating motivational incentives, and utilizing automated communications and reminders.

Zach Johnson from Corewell Health System shared that they have a successful support group established that meets quarterly. The group includes a range of patients who have either completed the CR program or those who are just beginning their journey to recovery. To address some of the common barriers for patients, Corewell has partnered with Michigan Rehabilitation Services to help cover a patient’s copay with a contingency that the patient plans to return to work for a minimum of 20 hours per week in the future.

To address transportation barriers, Corewell has partnered with True North which is funded by a family donation fund. If a patient meets the criteria for being at or below poverty level, they will qualify to receive financial assistance to cover the cost of transportation to and from visits. Holland Hospital’s Meiste shared they have utilized a mini grant awarded from the MiCR initiative to fund their heart failure orientation and to offer copay assistance to patients in need.

Opportunities for Further Improvement

Bair rounded out the panel discussion by asking panelists to describe unique challenges they identified when trying to incorporate CHF patients into CR programs. In response to Scharf’s inquiry about strategies to connect with patients who have CHF but have not yet met the 35% EF criteria, MVC Faculty Advisor, Mike Thompson shared that cardiac clinicians at Michigan Medicine are having CR conversations with CHF patients earlier in the disease process.

Additionally, lack of a standardized approach to discussing cardiac rehab for patients at 40% - 35% EF range is a common concern. Wymer shared that UMH Sparrow-Clinton addressed this by encouraging clinicians to urge patients who fall within the 35 – 40% EF range to begin participating in CR before their condition deteriorates further. MVC members can raise awareness by following and reposting BMC2 and MVC on LinkedIn.

MVC Cardiac Rehabilitation Workgroup: Feb. 10, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please email us if you are interested in being a workgroup presenter or submit a presentation proposal online.

Off
View Post
Cardiac Rehabilitation Awareness Week Spotlighted Resources and Tools Improving Cardiac Rehab Enrollment

Cardiac Rehabilitation Awareness Week Spotlighted Resources and Tools Improving Cardiac Rehab Enrollment

MVC and BMC2 took to LinkedIn recently to celebrate Cardiac Rehab Awareness Week, spotlighting the importance of cardiac rehabilitation for patients recovering from cardiovascular events. MVC and BMC2 collaborate to lead the Michigan Cardiac Rehab network (MiCR) and its related offerings. Across multiple posts, both teams highlighted stories, tools, collaborations, and insights designed to support providers, patients, and programs working to improve cardiac rehab outcomes in Michigan.

One of the central themes of the week was the voice of the patient. MiCR shared the first completed patient story from a new storytelling initiative called Heart-to-Heart, developed with the Healthy Behavior Optimization for Michigan (HBOM) team. This initiative amplifies real patient experiences, bringing to light why cardiac rehab matters — not just clinically, but personally — for those considering participation. Cardiac rehab week marked the launch of the first available patient story about a patient named Margaret from Covenant Healthcare.

Cardiac Rehab Week also offered opportunities for networking and knowledge exchange. MVC hosted a virtual cardiac rehab workgroup [view video] focused on optimizing congestive heart failure (CHF) follow-up and increasing rehab enrollment in this especially vulnerable patient population. Featuring panelists from Corewell Health, Holland Hospital, Michigan Medicine, MyMichigan Health, and University of Michigan Health-Sparrow, this session highlighted real-world strategies and insights for improving care transitions and referral practices.

Throughout the week, both organizations also shared posts featuring practical tools to strengthen cardiac rehab engagement, such as:

  • NewBeat Resources: BMC2 highlighted NewBeat materials — engaging, evidence-based education and referral tools designed to help care teams talk with patients about the benefits of cardiac rehab and support meaningful discussions that lead to enrollment (Figure 1). A new round of no-cost printing for MiCR sites was announced, offering flexible, ready-to-use materials that programs can request.
  • Cardiac Rehab Center Finder: Knowing “where to go” is a crucial earliest step. MVC and BMC2 reinforced the MichiganCR.org searchable directory that allows patients and providers to locate nearby rehab programs. This simple tool reduces a key barrier to engagement by connecting patients with access points across Michigan.
  • Resource Library Spotlight: The MiCR Resource Library was featured as a one-stop hub for tools — from evidence-based products to collaborative resources developed with partners throughout the state — supporting both providers and patients as they plan, refer, and participate in cardiac rehab sessions.

Figure 1. Cardiac Rehab Resource Materials

decorative

Recognizing the evolving landscape of cardiac rehabilitation delivery, MiCR also took the opportunity to highlight its newest strategic efforts throughout cardiac rehab week, including its explorations into the role of telehealth in cardiac rehab as well as medication management opportunities. Updates on these efforts and more were summarized and linked in a summary blog to the MiCR website. To learn more, read the MiCR summary.

As the week wrapped, the MiCR teams thanked everyone for their role in advancing cardiac rehab throughout Michigan, and invited their active participation going forward—either by trying a MiCR tool in their daily work or sharing their experiences and stories. As MiCR continues its work, the momentum from this week sets the stage for meaningful improvement in patient outcomes and program engagement statewide.

Off
View Post
MVC and MSSIC Impact Assessment Quantifies $73M in Cost Savings from Reduced Surgical Complications

MVC and MSSIC Impact Assessment Quantifies $73M in Cost Savings from Reduced Surgical Complications

Over the past several years, the Michigan Value Collaborative (MVC) has partnered with clinical quality collaboratives across the state to better understand how improvements in care delivery translate into value—for patients, providers, and payers alike. By pairing robust clinical data with claims-based cost and utilization data, these partnerships allow us to move beyond reporting improvement to quantifying its real-world impact.

The MVC Coordinating Center is excited to announce the completion of two new impact and value assessments conducted in partnership with the Michigan Spine Surgery Improvement Collaborative (MSSIC). These analyses examined statewide improvements in postoperative urinary retention (POUR) complications and surgical site infections (SSI) following spine surgery.

Although focused on different complications, both assessments followed a shared framework: pairing MSSIC’s clinically abstracted registry data with MVC’s claims-based episode data to quantify the impact of declining complication rates on episode-level spending and utilization.

Background and Approach

MSSIC has led statewide efforts to reduce preventable surgical complications following spine surgery through surgeon engagement, performance feedback, alignment of incentive-based measures, and implementation of evidence-informed practice changes. Over time, MSSIC-participating hospitals demonstrated measurable declines in both urinary retention and surgical site infections.

To assess the value implications of these improvements, MSSIC provided MVC with a dataset of lumbar and cervical spine patients that included the presence or absence of complications as abstracted from medical records. Spine patients were matched to MVC’s analytic tables and spine cohort for Medicare Fee-For-Service (FFS), Medicaid, Blue Cross Blue Shield of Michigan (BCBSM) Commercial, BCBSM Medicare Advantage (MA), Blue Care Network (BCN) Commercial, and BCN MA claims. MVC then evaluated the matched population for readmission status and price-standardized facility payments associated with POUR and SSI. MVC and MSSIC used the rates of adverse events pre- and post-QI to estimate the number of events averted. MVC payment data was then used to calculate cost savings from averted events.

Postoperative Urinary Retention (POUR)

While postoperative urinary retention may not always be perceived as a high-cost complication, the analysis demonstrated that it is associated with meaningful differences in episode spending and utilization. Episodes involving POUR were linked to higher total payments and greater downstream healthcare use compared to episodes without urinary retention.

The analysis conducted revealed that there were statistically significant reductions in the rates of POUR and readmissions between 2016-2024 from which to estimate cost savings. Specific to POUR, MVC and MSSIC estimated there were 5,197 POUR events averted. Using the MVC-based estimate of 21.7% of POUR events also involving readmission, MVC and MSSIC estimated there were 1,128 readmissions averted.

To estimate cost savings from averted POUR events, MVC completed a comparative analysis of diagnosis-related group (DRG) and post-discharge payments among lumbar and cervical spine patients with no POUR compared to those with POUR events. The results of the analysis of higher inpatient DRG payments (Figure 1) show that the weighted average DRG payments for patients without POUR were $25,743.40; the weighted average payments for those with POUR was $27,603.20, a difference of $1,859.80 per patient. Looking at post-discharge payments (Figure 2), MVC found that the average payment for a patient without POUR was $1,691. The weighted average payment for those with POUR (21.7% with readmission and 78.3% without readmission) was $12,684.65, a difference of $10,993.65 between patients with and without POUR.

Figure 1. Calculation of Additional Inpatient Diagnosis-Related Group (DRG) Payments Based on Complications and Comorbidities (CC) by POUR Status

Table outlining the differences in inpatient average episode payments for patient with and without urinary incontinence complications

Figure 2. Calculation of Post-Discharge Price-Standardized Payments Associated with POUR

Table outlining differences in outpatient costs between patients with and without urinary incontinence

This amounted to an estimated total direct cost savings to payors of $66,799,380 from POUR rate reductions. On this finding, Senior MSSIC QI Lead Kari Jarabek, BSN, RN, said, “The analyses here show how decreasing rates of what some may consider to be a ‘minor complication’ of surgery can have profound consequences in terms of cost savings for patients, employers, and other payers.”

View the complete summary of the December 2025 MSSIC urinary retention assessment on MVC’s CQI collaboration page.

Surgical Site Infections (SSI)

The association between surgical site infections and higher costs is well established, and the MVC–MSSIC assessment reinforces this relationship within Michigan hospitals. Episodes complicated by SSI were associated with significantly higher total episode payments and increased post-discharge utilization.

The analysis revealed statistically significant reductions in the rates of SSI and readmissions from the 2019 baseline year to the 2020-2024 post-intervention period. MVC and MSSIC estimated 301 SSI events were averted. Using the MVC-based estimate of 62.6% of SSI events also involving readmission, MVC and MSSIC estimated that 188 readmissions were averted.

To estimate cost savings from averted SSI events, MVC completed a comparative analysis of diagnosis-related group (DRG) and post-discharge payments among patients with no SSI compared to those with SSI events. The results of the analysis of higher inpatient DRG payments (Figure 3) showed that weighted average DRG payments for patients without SSI were $25,823; the weighted average payments for those with SSI was $26,483, a difference of $660 per patient. Looking at post-discharge payments (Figure 4), MVC found that the average payment for a patient without SSI was $1,801. The weighted average payment for those with SSI (62.6% with readmission and 37.4% without readmission) was $23,274, a difference of $21,473 between patients with SSI and those without. This amounted to an estimated total direct cost savings to payors of $6,662,033 from SSI rate reductions.

Figure 3. Calculation of Additional Inpatient Diagnosis-Related Group (DRG) Payments Based on Complications and Comorbidities (CC) by SSI Status

Table outlining differences in inpatient episode costs for patients with and without SSI

Figure 4. Calculation of Post-Discharge Outpatient Payments Associated with SSI

Table outlining the differences in post-discharge payments for patients with and without SSI.

View the complete summary of the December 2025 MSSIC SSI assessment on MVC’s CQI collaboration page.

Advancing Value Through Collaboration

Taken together, these two assessments demonstrated that MSSIC efforts delivered significant net savings for its BCBSM sponsor and healthcare providers in Michigan, and that targeted practice changes—such as early ambulation and updates to existing protocols to reflect best practices—not only improved patient recovery but also contributed to improved value at the episode level.

These two assessments also demonstrated a consistent pattern: fewer complications were associated with lower episode spending and reduced downstream utilization. By linking clinical registry data with claims-based cost analysis, MVC and MSSIC were able to move beyond reporting improvements in complications to quantifying its broader impact.

As MVC continues its partnerships with the BCBSM Value Partnership CQIs, this work provides a replicable model for understanding how collaborative clinical improvement translates into measurable value for patients and the healthcare system.

Off
View Post
January Workgroups Highlight Using Claims Data to Drive Sepsis QI and Reducing SSIs Through Multidisciplinary Collaboration

January Workgroups Highlight Using Claims Data to Drive Sepsis QI and Reducing SSIs Through Multidisciplinary Collaboration

In January, Michigan Value Collaborative (MVC) kicked off the 2026 workgroup calendar with a sepsis workgroup focused on helping members better understand how to use claims-based data to support sepsis quality improvement (QI) efforts. The session featured an overview of sepsis-related reporting available on the MVC registry followed by an example of how custom analytic reports can be used to dig deeper into areas of clinical interest. The second workgroup of the month, a health in action presentation, featured Corewell Health Farmington Hills Hospital’s multi-year QI initiative aimed at reducing surgical site infections (SSIs) in colorectal surgery. The MVC Coordinating Center hosts one to two workgroup presentations per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Sepsis Workgroup – MVC Coordinating Center

The workgroup opened with a presentation by MVC’s Site Engagement Coordinator Rachel Folk, MHA, who walked participants through the types of sepsis related data available in the MVC registry and how members can use these reports to support local QI initiatives. The presentation emphasized that MVC’s claims-based data registry allows members to examine sepsis episodes of care across multiple payers and care settings, providing a broader view of healthcare utilization and outcomes than many internal data sources alone.

Participants were introduced to several registry reports that are particularly relevant to sepsis analysis, including:

  • Episode Payments Report, which shows total, price-standardized payments for 30- or 90-day episodes and can be used as a proxy for assessments of utilization across inpatient, professional, post-acute, and readmission services.
  • Episode Utilization Rates Report, which breaks down where patients receive care during and after an episode, such as skilled nursing facilities, home health, inpatient rehabilitation, or emergency department visits.
  • Readmissions Report, which allows members to explore readmission rates for patients by time interval and whether patients return to the index hospital or are readmitted elsewhere.
  • Comorbidities Report, which highlights common coexisting conditions among patients and supports a deeper understanding of patient complexity.
  • Payment by Condition Report, which compares case volume and utilization across conditions and helps contextualize sepsis relative to other medical episodes.

The presentation also included a review of sepsis-related Pay for Performance (P4P) reports available in the MVC registry including a Value Metric Summary Report and Value Metric Trends Report, which allow users to assess their current performance, improvement and achievement baselines and trends over time (Figures 1 and 2). Folk explained how these reports can help teams visualize progress relative to peer hospitals and MVC-wide averages.

Figure 1. MVC Data Registry Value Metric Summary – Blinded Report

MVC Data Registry Value Metric Summary table – Blinded Report

Figure 2. MVC Data Registry Value Metric Trends – Blinded Report

MVC Data Registry Value Metric Trends line graph – Blinded Report

Throughout the presentation, Folk additionally highlighted key registry features such as filtering by hospital type, payer, episode length, patient demographics, and episode time frame. She also reviewed case suppression thresholds and reminded participants that MVC’s data are risk adjusted, allowing for fairer comparisons across hospitals with differing patient populations.

Using Claims Data to Support Improvement

A recurring theme of the discussion was the importance of approaching the registry with curiosity. Participants were encouraged to consider the “five W’s” when reviewing their data and to use the available benchmarking opportunities to compare their hospital’s performance against similar hospitals to help identify realistic opportunities for improvement.

Polling during the session revealed that many participants had limited or no prior experience with an MVC registry review. Registry reviews are a dedicated opportunity for MVC staff to walk members through their site-specific data, focusing on the reports and metrics most relevant to their individual goals. These reviews can help teams move beyond high-level trends to more actionable questions about variation, utilization, and outcomes.

If you’re interested in setting up a time to complete a registry review, please email MVC.

Applying Custom Analytics to Sepsis Care

The workgroup concluded with a second presentation by MVC Analyst Janet Zhang, MPH, highlighting how custom analytic reports can be used to explore specific questions not fully addressed by standard registry reports. Using a recent example focused on sepsis patients and the impact of palliative care, Zang demonstrated how tailored analyses can provide deeper insight into care patterns, outcomes, and opportunities for improvement.

MVC encourages members interested in deeper analyses via custom report to submit a request through the Coordinating Center [Link].

MVC Sepsis Workgroup: Jan. 13, 2026

Health in Action Workgroup – Corewell Health Farmington Hills Hospital

MVC’s second workgroup of January featured Jennifer Hengy, BSN, RN, Internal Quality Improvement Specialist, Dr. Eugene Laveroni, Chief of Surgery, and Leslie Smith, RPh, JD, BCPS, BCIDP, Clinical Pharmacist Specialist from Corewell Health Farmington Hills. Together they showcased how a multidisciplinary team used data, evidence-based guidelines, and workflow redesign to drive meaningful improvements in patients’ safety by reducing SSIs in colorectal surgery.

SSIs remain a significant source of patient harm and financial penalty for hospitals nationwide. Despite advances in sterile technique and surgical technology, data from the Centers for Disease Control and Prevention (CDC) continue to show SSIs occur at alarming rates. As Hengy explained, their local data mirrored this challenge with an SSI rate of 9.6% in colorectal surgeries in 2023. This signaled an urgent need for targeted improvement. For Farmington Hills, this started with building the right team.

Building a Team

The initial improvement committee included surgical leadership, quality improvement specialists, pharmacy, nursing education, and anesthesia, with additional stakeholders added as new insights emerged. This diverse group ensured that clinical expertise, frontline workers, and data review were all represented throughout the project. Another key principle of the initiative was fostering a non-punitive culture. Chart reviews and peer discussion focused on learning and system improvement rather than individual blame, helping to sustain engagement across disciplines.

The Discovery Phase: Identifying Key Gaps

The discovery phase proved to be the most challenging but ultimately the most impactful, Hengy shared. The team conducted detailed chart reviews of SSI cases to better understand contributing factors, examining elements including:

  • Use of clean closing gloves, gowns, and closing packs
  • Skin preparation and closure techniques
  • Antibiotic selection, timing, and infusion duration
  • Documentation of infections present at the time of surgery (or PATOS)

Early interventions focused on education about documentation, standardized closing packs, and surgical techniques. While these steps led to modest improvements, they did not produce the level of change the team was seeking so they turned to the experts in antibiotics.

Optimizing Antibiotic Selection and Timing

A deeper dive into perioperative antibiotic practices at Farmington Hills revealed variability in both the antibiotics chosen and their infusion timing. The team identified frequent use of second-line antibiotics in patients with reported penicillin allergies, as well as inconsistencies ensuring antibiotics were fully infused prior to surgical incision.

Smith, a clinical pharmacist specializing in antimicrobial stewardship and a member of Corewell Health Farmington Hills’ SSI workgroup explained that cefazolin remains the preferred first-line prophylactic antibiotic for colorectal surgery and can be safely administered to most patients with reported penicillin allergies. Pharmacy-led education highlighted Cefazolin’s uniquely low risk of cross-reactivity and proven lower SSI rates compared to non-beta-lactam alternatives. Education was delivered through multiple channels, including surgical quality meetings, residents and provider training, newsletters, and real-time feedback to reinforce adherence to standardized protocols.

In addition, the team redesigned workflows to address infusion timing. New processes ensured that antibiotics requiring longer infusion times were started earlier in the preoperative phase. The use of visual job aids, memory tools, and Omnicell alerts reinforced these changes at the point of care (Figures 3 and 4).

Figure 3. Timing of Preoperative Antibiotic Infusion Flyer

Timing of Preoperative Antibiotic Infusion Flyer

Figure 4. Recommended Antibiotic Re-Dosing Interval Guideline Table for Patients Currently Receiving Antibiotics

Recommended Antibiotic Re-Dosing Interval Guideline Table for Patients Currently Receiving Antibiotics

Outcomes and Impact

Following implementation of these antibiotic-focused interventions and revised workflows, Corewell Health Farmington Hills observed a substantial reduction in colorectal SSIs with an infection ratio (SIR) of 0% between February 2024 and August 2024. In conclusion, the presenters emphasized that while zero harm is an aspirational goal, the consistency of guideline adherence and the sustainability of improved practices represented their major successes.

MVC Health in Action Workgroup: Jan. 29, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us via email or by submitting a presentation proposal using this form if you are interested in sharing your work.

Off
View Post
MVC Thanks Presenters from the Second Half of 2025

MVC Thanks Presenters from the Second Half of 2025

The MVC Coordinating Center wishes to express our deep appreciation for the 31 dedicated healthcare professionals who volunteered to present at MVC’s third and fourth quarter 2025 virtual workgroups, fall collaborative-wide meeting, and the Michigan Cardiac Rehabilitation network (MiCR) fall meeting. We know that MVC’s members and partners have many demands on their time from within their own organizations and beyond. Nonetheless, these 31 guest speakers shared their data, innovative approaches, best practices, and lessons learned with MVC members to support our shared goals of peer learning and high-value care delivery for all Michigan patients. We celebrate you for contributing in this important way, some at multiple events. You DO make a difference!

Join us in giving these folks a well-deserved round of applause:

Health in Action Workgroup

  • Amanda Escalera-Torres, RD, Program Director for Hurley Medical Center Food FARMacy Program
  • Leah Julian, BA, Innovation in Behavioral Health (IBH) Specialist, Michigan Department of Health and Human Services (MDHHS)
  • Lindsey Naeyaert, MPH, Service Delivery Transformation Section Manager, MDHHS

Post-Discharge Follow-Up Workgroup

  • Sara Hagerman, BSN, RN, Quality/Performance Improvement Specialist, University of Michigan Health - Sparrow Carson
  • Noa Kim, MSI, Informatics Design Lead, Healthy Behavior Optimization of Michigan (HBOM)
  • Larrea Young, MDes, Human-Centered Design Project Manager, HBOM

Preoperative Testing Workgroup

  • Amy Poindexter, BSN, RN, Performance Improvement Analyst, Holland Hospital
  • Kelly Lewton, RN, BSN, Performance Improvement Coordinator, Lake Huron Medical Center
  • Nicole Mott, MD, MSCR, Resident Physician and Post-Doctoral Fellow, University of Colorado & University of Michigan

Rural Health Workgroup

  • Lindsey Crouch, RN, Program Director, Hillsdale Community Health Center Mobile Health Clinic
  • Victoria Durr, BSN, RN, Infection Prevention Coordinator, Scheurer Health

Sepsis Workgroup

  • Errin Couck, RN, BSN, HMS Sepsis Abstractor, Henry Ford Health Macomb
  • Brandie DeVos, RN, MSN, Sepsis Coordinator, Henry Ford Health Macomb

Fall Collaborative-Wide Meeting Keynote Speaker

  • Gloria Rey, PA-C, MPH, Director of Post-Acute Care, Populance Henry Ford Health

Fall Collaborative-Wide Meeting Podium and Breakout Session Speakers

  • Brad Iott, PhD, MPH, Content Expert in Health Informatics and Social Care Integration, MSHIELD
  • Julia Weinert, MPH, Program Manager, MSHIELD
  • Amanda Biskner, RN, Paramedic, CP-C, Community Paramedicine Coordinator, Tri-Hospital EMS
  • Kelly Clark, MD, Faculty, Munson Family Medicine Residency Program and Clinical Assistant Professor, Department of Family Medicine at Michigan State University
  • Belinda Dokic, CPhT, BA, MBA, Clinically Integrated Network Program Manager, Trinity Health Livonia
  • Michael Gatt, MD, Gynecologist, Trinity Health Livonia
  • Holly Gould, MSN, CNM, RN, Director of Quality Improvement and Organizational Excellence, McLaren Port Huron
  • Nicole Luczak, President and CEO, United Way Bay County
  • Greg Scharf, BS, ACSM-CEP, AACVPR-CCRP, Cardiopulmonary Rehab System Manager, MyMichigan Medical Center - Midland

MiCR Fall In-Person Meeting Keynote Speaker

  • Stacey Greenway, MPH, MS, President of the American Association of Cardiovascular and Pulmonary Rehabilitation (AACVPR)

MiCR Fall In-Person Meeting Podium Speakers

  • Barry Franklin, PhD, Director (Emeritus), Preventive Cardiology and Cardiac Rehabilitation, Corewell Health East, William Beaumont University Hospital
  • Megan Gross, MPH, CHES, ACSMCEP, EIM, Clinical Exercise Physiologist, Holland Hospital
  • Cindy Haskin-Popp, MS, CEP Manager, Cardiology, Corewell Health East
  • Amy Poindexter, BS, CEP, Performance Improvement Analyst, Trinity Ann Arbor
  • Brett Reynolds, MPH, ACSM-CEP, Supervisor of Cardiology, Corewell Health East
  • David Running, BS, CEP, Supervisor-Cardiac Rehab, University of Michigan Health West
  • Amber Steele, ACSM-CEP, Cardiac Rehab Lead, McLaren Bay Region
  • Larrea Young, MDes, Human-Centered Design Project Manager, HBOM
thank you graphic

The MVC members and partners who attend MVC events appreciated these presenters, too. Here are just a few of the many glowing survey responses MVC received about presenters and their content in 2025.

presentation attendee testimonials

As a reminder, past workgroups and virtual networking event recordings can be viewed on MVC’s YouTube channel, and presentation slides and materials from MVC’s fall collaborative-wide meeting can be viewed here.

Do you have valuable information to share?

Whether you are new to presenting or a seasoned pro, the MVC Coordinating Center is here to support you every step of the way. From exploring topic ideas to preparing information and managing event logistics, our team makes the experience of presenting easy and comfortable. The P4P points you can earn as a presenter are a great benefit to your organization, too. For more information about presenting, contact the MVC Coordinating Center or submit a proposal here.

Off
View Post
CQI Spotlight: Obstetrics Initiative

CQI Spotlight: Obstetrics Initiative

In 2018, Michigan was facing a concerning reality: nearly one in three births in the state occurred by cesarean delivery, a rate that exceeded the national average and signaled opportunities to improve the safety, experience, and value of childbirth care. Behind every data point were real families navigating some of the most important moments of their lives and clinicians striving to deliver the best possible care within a complex maternity landscape. The need for change was personal, urgent, and increasingly difficult to ignore.

As such, patients, clinicians, and employers began voicing concerns about rising cesarean rates affecting patients’ recoveries, long-term health, and trust in the healthcare system. Recognizing the scope of the problem and the opportunity to address it, Blue Cross Blue Shield of Michigan (BCBSM) turned to clinician leaders at University of Michigan to help design a statewide response, which leveraged Michigan Value Collaborative (MVC) claims data on childbirth episodes. In 2018, this collaboration laid the groundwork for what would become a dedicated effort to transform maternity care in Michigan.

Formally launched in 2019, the Obstetrics Initiative (OBI) emerged as one of BCBSM’s 21 Collaborative Quality Initiatives (CQIs). At that time more than 70 hospitals joined together under OBI’s vision to support safer deliveries, reduce unnecessary cesarean deliveries, use resources more wisely, and improve the overall culture of care. Today, OBI continues to build on that foundation by ensuring that every birth in Michigan is supported by the best evidence, the best practices, and a shared commitment to healthier beginnings.

Services and Benefits for OBI Members

To support its members in successfully implementing quality improvement (QI) initiatives, OBI supports its members using four primary offerings (Figure 1). One of those offerings is OBI’s robust, real-time benchmarking data that enables actionable insights. OBI’s registry is a best-in-class source of clinically credible data and compelling data stories that inspire change. A second core offering is direct support and expertise on specific QI interventions, including the development of best practice protocols and resources that advance evidence-based care. A third core offering is the transformational learning that occurs at OBI’s collaborative-wide meetings and other activities that are key to networking, partnership building, and collective learning across maternity units in Michigan. Finally, a fourth core offering is the intentional collection and incorporation of patient stories and experiences in all ongoing activities.

Figure 1: OBI Member Service Offerings

OBI service offerings: data and analytics, learning, QI evaluation, collaboration with patients

OBI Program Director Michelle Moniz, MD, MSc, recognizes how OBI’s tailored approach to QI support helps sites achieve a shared purpose of high-quality perinatal care that improves the lives of current and future generations. In her words:

“Every large-scale QI initiative faces a vexing unsolved problem: how best to support hospitals and clinicians who aren’t responding. Our routine QI support approaches—group meetings, webinars, online toolkits, performance incentives—can fall short for sub-optimally responding sites/clinicians, and leave patients vulnerable to low-quality, low-value healthcare. OBI imagines a future where CQIs deliver the right support, to the right hospital/clinician, at the right time, to achieve highest-quality care across all CQI members. This vision—which we call Precision QI—leverages scarce resources most efficiently to achieve evidence-based healthcare at scale for all patients.” 

OBI’s "precision QI” offers personalized QI support for each hospital. Just as precision medicine accounts for individual patient differences in developing a treatment plan, OBI’s precision QI support model (Figure 2) is adaptive, diagnosing and responding to the unique needs of each OBI member and may include:

  • Performance Measurement: Offering observed, risk-adjusted, and peer-comparative data
  • Performance Feedback: Incorporating individualized goal setting and data for hospitals and individual providers
  • Outreach: Offering augmented support when performance deteriorates or is stably poor
  • Engagement: Offering a suite of resources for key target audiences, including hospital leadership, QI leader, bedside clinicians, and patients

Figure 2. Mechanisms for OBI’s Precision QI Support Model

performance measurement, performance feedback, outreach, engagement

OBI’s Key Initiatives and Achievements

OBI is now a unique asset for quality improvement in Michigan and beyond. Having built a vibrant community of multidisciplinary teams at currently 65+ hospitals across Michigan, OBI generates the evidence base needed for more effective, transformational quality improvement in obstetrics.

Putting that framework into action, OBI achieved noteworthy successes over the years. Since OBI’s inception, their flagship initiative, Safely Averting Cesarean Births, has focused on safely lowering the primary cesarean rate in Michigan. In 2023, OBI launched Patient Voices, a statewide survey to assess childbirth experiences and patient-reported outcomes related to birth. OBI then launched another statewide initiative, Bringing Our Patients COMFORT, in 2024, to promote best practices for managing pain after childbirth.

To reduce first-birth term cesareans – also known as nulliparous term singleton vertex (NTSV) cesareans, OBI’s Safely Averting NTSV Cesarian Births initiative successfully reduced the statewide cesarean rate from a historic high of 28.9% in 2023 to 26.9% as of September 2025. This improvement reflects years of effort to increase compliance with national diagnostic criteria for labor arrest disorders (which increased from 37.9% in 2020 to 77.1% in 2025). Increased compliance was aided using an algorithm to guide fetal management in labor, resulting in significant improvement from 47.3% compliance in 2022 to 93.2% in 2025.

Pain management is another area where OBI has made meaningful progress. Successful promotion of the use of scheduled nonopioid prescribing after cesarean births through OBI’s Bringing Our Patients COMFORT quality initiative boosted a compliance rate of 86.1% in 2024 to 96.8% compliance in 2025. Analyses are ongoing to evaluate corresponding reductions in opioid prescribing rates and amounts.

OBI’s third quality initiative Better Births for All aims to ensure that every OBI member has the tools and support to consistently implement evidence-based obstetric practices while fostering psychological safety and respectful, person-centered care for all during labor and birth. The path to accomplish that is threefold. First, OBI partners with a Patient and Community Action Board (PCAB) to center patient and community experiences in its QI initiatives. The OBI PCAB reviews patient-facing materials and has decision-making power over OBI’s selection of QI initiatives and operationalization of initiative measures in OBI’s incentive packages. OBI further centers patients’ perspectives in its work by measuring and improving collection of patient-reported outcomes and experience data to ensure that patients’ voices are embedded in daily QI work. OBI also educates and trains clinicians on patient-centered approaches and practices they can bring to their own daily work.

"Relationships are at the heart of what we do. We have a shared belief that our goals will be better met when we advance toward them together." Helen Costis, MSHA, Program Manager, OBI

What’s Next for OBI?

In 2026, OBI will launch a new Induction of Labor initiative to promote evidence-based management of induction of labor (IOL), the procedure to start labor before it begins on its own. This procedure occurs in more than 30% of all births, and yet the use of evidence-based techniques occurs in less than 10% of all inductions with wide variation across sites in Michigan (Figures 3 and 4).

Figure 3. Pathways for Evidence-Based Induction of Labor

Induction of labor pathways: Dual-Agent Ripening; Early Amniotomy
Rate of use graph of evidence-based induction of labor techniques. Patients who get both recommended techniques is 7.1%.

OBI is incredibly proud to be a part of the 25+ year history of the Value Partnership portfolio in Michigan, including its long-standing partnership with MVC. OBI and MVC are currently collaborating on several analyses to drive quality improvement, such as evaluating statewide variation in complications and expenditures for different patient groups and modes of delivery, improving the timeliness and quality of prenatal care, evaluating the association between social vulnerability and surgical management of early pregnancy loss. MVC is also working with OBI to estimate the impact and associated cost savings of OBI’s efforts to safely reduce cesarean birth rates in Michigan as well as the impact of OBI’s opioid management work on prescribing rates and costs in Michigan.

The BCBSM-funded CQIs play a crucial role in driving healthcare quality improvement in Michigan. MVC is excited to continue highlighting the innovative contributions of individual CQIs and the ways in which MVC’s data are supporting high-value care initiatives across the portfolio. Please reach out to MVC by email if you are interested in learning more.

Off
View Post
MVC Welcomes Faculty Advisor and Physician Ryan Howard

MVC Welcomes Faculty Advisor and Physician Ryan Howard

I am so excited to be joining the Michigan Value Collaborative as a Senior Faculty Advisor. I’ve worked closely with the Collaborative Quality Initiatives for the last decade and am thrilled to continue that work in this new role!

By way of introduction, I am a surgeon and healthcare researcher at the University of Michigan. I am Maize and Blue through and through, having completed my undergrad, medical school, residency, and fellowship at the University of Michigan. My clinical practice focuses on bariatric and hernia surgery, and I also specialize in comprehensive obesity treatment with medications and other non-surgical options. What I love most about my practice is partnering with patients to help them accomplish their goals and live their life to the fullest.

My research focuses on studying the quality and safety of surgical care. My passion is taking what we discover through research and turning it into real-world improvements for our patients. To that end, I conduct studies that identify opportunities to improve care, then I use those findings to inform quality improvement efforts to make those changes a reality. My research has explored post-operative opioid prescribing, abdominal wall hernia repair, and long-term health changes after bariatric surgery. I’ve also written a lot about the Collaborative Quality Initiatives, which really demonstrate what you can accomplish through statewide collaboration and partnership.

The Michigan Value Collaborative is such a critical engine for translating our research into real-world improvements for patient care, and I could not be happier to join such a talented and dedicated team. In my role at MVC, I’ll be engaged in studying the quality of surgical care in Michigan, collaborating on quality improvement initiatives, and helping identify new ways to enhance the care we deliver to patients.

I’m truly looking forward to the work ahead and to contributing to MVC’s mission of driving high-value, patient-centered care across the state.

Off
View Post
December Workgroups Highlight RITE-Size Preoperative Testing and MVC Year End Reflections and Goals

December Workgroups Highlight RITE-Size Preoperative Testing and MVC Year End Reflections and Goals

In December, Michigan Value Collaborative’s (MVC) preoperative testing workgroup featured a co-presentation by Kelly Lewton, RN, BSN, Performance Improvement Coordinator for Lake Huron Medical Center, and Nicole Mott, MD, MSCR, a National Clinician Scholar at the University of Michigan supported by the Veterans Administration and a general surgery resident at the University of Colorado. The presentation focused on the Right-Sizing Testing Before Elective Surgery (RITE-Size) trial; Dr. Mott was the lead author on a recently published paper in JAMA Network Open that described the components and impact of the trial, and Lewton shared her first-hand experience as the lead during Lake Huron Medical Center’s participation in the trial. RITE-Size works with hospitals to identify and right-size testing before elective surgery procedures. The second workgroup, health in action, featured MVC Site Engagement Coordinator Emily Bair, MS, MPH, RDN, CSP, and the Engagement team and focused on a year in review of quality initiatives across MVC members. The MVC Coordinating Center hosts one to two workgroup presentations per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Preoperative Testing Workgroup - RITE-Size & Lake Huron Medical Center

The RITE-Size trial is a partnership among quality improvement teams in Michigan including the Michigan Program on Value Enhancement (MPrOVE), the MVC Coordinating Center, the Michigan Surgical Quality Collaborative (MSQC), and the Anesthesiology Performance Improvement and Reporting Exchange (ASPIRE). Dr. Mott shared that the goal for RITE-Size participants is to lower unnecessary preoperative testing before elective outpatient cholecystectomy, inguinal hernia repair, and lumpectomy. Routine preoperative testing before these low-risk surgeries has shown no clinical benefit to the patient but has led to multiple downstream consequences such as increased spending, care cascades, and treatment delays (Dossett & Wilkinson, 2022).

Dr. Mott described that RITE-Size launched a pilot feasibility study in March 2024 at three hospitals in Michigan. The study aimed to meet criteria in several areas such as feasibility (implementation in the appropriate amount of time), testing rates (reduction), and acceptability and appropriateness (results from interviews). By August 2024, the desired milestones had been achieved, showing a 68% reduction in unnecessary testing at all participating sites (Figure 1).

Figure 1. MVC RITE-Size Pilot Program Testing Rates Over Time Across All Three Sites from March-April 2024 to July-August 2024

line graph depicting reduction in unnecessary preoperative testing at three pilot sites

Some barriers that impacted the study included lack of clarity about guidelines, a need for ongoing education due to the automated nature of testing processes, and coordination across a large healthcare system and/or within the limitations of institutional rules. Elements that led to success included strong leadership through key collaborators, incorporation of the initiative into policy, self-monitoring throughout, and team cohesiveness and communication. The pilot's success allowed RITE-Size to expand to other sites across Michigan.

Lewton from Lake Huron Medical Center (LHMC) followed the RITE-size presentation sharing first-hand experience of participating with the initiative in 2025. She described the site onboarding process, which included a RITE-Size site visit in July 2025 where her team worked with Dana Greene, Jr., Project Manager at MPrOVE, to discuss LHMC interventions and progress over the duration of the program and to schedule ongoing coaching sessions (Figure 2).  After investigating preoperative testing rates, LHMC found that their biggest outlier was electrocardiograms (EKGs) ordered by a particular surgeon.

After the site visit, the lead anesthesiologist met with the surgeon, and they discovered he had been given outdated testing guidelines when he onboarded. With this discovery, their team was able to review their testing guidelines and begin the process of updating and educating team members. By November 2025, LHMC saw a notable decrease in preoperative testing for low-risk surgeries and began development for an updated version of their pre-admission testing (PAT) guidelines.

Figure 2. LHMC Timeline of RITE-Size Pilot Work

Lake Huron Medical Center timeline of RITE-Size pilot work

Lewton rounded out the presentation sharing that the RITE-Size project helped LHMC to update their care guidelines, improve patient care, and reduce unnecessary testing. RITE-Size also provided many resources for staff to help with new process implementation and coached staff to use evidence-based research to guide everyday practice.

MVC Preoperative Testing Workgroup: Dec. 2, 2025

Health in Action Workgroup - MVC Coordinating Center

This month’s health in action workgroup was led by MVC Site Engagement Coordinator Emily Bair, MS, MPH, RDN, CSP, with support from other staff at the MVC Coordinating Center. The workgroup encapsulated a year in review for member QI work in 2025 as well as a look ahead at 2026.

Bair shared result highlights from the MVC QI survey that many MVC members completed in June 2025, noting several common QI efforts across the state (Figure 3). The top areas of focus were sepsis, readmissions, transitions of care, population health management, and emergency department care. Of the 88 survey responses, there were a total of 65 hospitals, 8 physician organizations, and 15 hospital systems represented.

Figure 3. Statewide QI Initiatives in 2025

Statewide QI Initiatives in 2025 depicting sepsis, readmissions, transitions of care, population health management, and emergency department care

Some of the common barriers identified by member sites in the survey included insufficient resources and funds, staff burnout, high turnover, and staff shortages.

The MVC QI survey also sought to consider the needs of its members and asked participants to provide suggestions for how MVC can best support them in the upcoming year (Figure 4). The top requests included data and report-specific training, recordings and summaries of workgroups for those unable to attend events, user-friendly reports, smaller and more frequent breakout sessions during virtual events, and data and QI topics that are helpful for all types of hospital sites.

Figure 4. MVC Member Suggestions for Future Offerings

Graphic Summary of MVC Member Suggestions for Future Offerings

Bair reminded participants that MVC uploads virtual workgroup recordings to MVC’s YouTube channel and shares the link with members in a post-workgroup summary email along with slides and resources from presentations. To support members in accessing additional training opportunities, MVC has launched its new new site coordinator education program in January 2026. The four-module training is designed to provide a more individualized approach to building knowledge as an MVC site coordinator. The MVC QI survey was also a helpful resource for presenter recruitment, developing 2025 workgroup content, and planning 2026 offerings.

Following the 2025 review, participants engaged in an interactive polling activity about QI progress from the past year (Figure 5), areas of focus, and their key accomplishments. Some of the successes shared included improving compliance with the sepsis bundle, maintaining a low readmission rate, increased senior/executive leadership engagement, and a department-led change to improve utilization.

Figure 5. MVC Participants QI Progress Word Cloud

MVC Participants QI Progress Word Cloud

Workgroup participants were asked to share some of their QI priorities for 2026, including ways that their sites are trying to align with other services or programs and how MVC can best support them. Several shared they will focus on the following priorities in 2026:

  1. Sepsis compliance improvement
  2. Streamlining order sets to reduce sepsis fallouts
  3. Reducing readmissions
  4. Building connections with primary care clinics
  5. Reducing length of stay
  6. Reducing unnecessary preoperative testing by participating in the RITE-Size trial
  7. Reducing hospital acquired infections
  8. Interviewing readmissions patients

Participants also shared different ways they are working to align with Collaborative Quality Initiatives (CQI) and Centers for Medicare & Medicaid Services (CMS) measures. Several sites noted that they are shifting to align their sepsis metrics with the Michigan Hospital Medicine Safety Consortium (HMS) sepsis initiative and the CMS Hospital Sepsis Program Core Elements.

Members expressed interest in learning more about local quality leaders, developing effective committee structures within their sites, and acquiring new resources that might be available. Additionally, there was great interest in MVC’s new site coordinator education program that kicked off this January with modules that support site coordinators via one-on-one tailored training. Registration for the education program is closed for Q1 – Q2, and a waitlist has been started for Q3 – Q4. If you are a site coordinator interested in participating, you can submit an interest form. [LINK]

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to us by email or by submitting a presentation proposal here if you are interested in sharing your work in a presentation.

MVC Health in Action Workgroup: Dec. 18, 2025