
4
View Post
MVC, BMC2 Launch Michigan Cardiac Rehab Network & Toolkit

MVC, BMC2 Launch Michigan Cardiac Rehab Network & Toolkit

This year in the United States, cardiovascular disease will be responsible for one in every four deaths. Despite its prevalence, few cardiac patients eligible for cardiac rehabilitation utilize this life-changing program. In response, the Michigan Value Collaborative (MVC) and the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2) recently established the new Michigan Cardiac Rehab Network (MiCR) to collaborate on efforts that heighten awareness of these programs and support meaningful improvement in Michigan.

Cardiac rehabilitation (CR) is a comprehensive program encompassing supervised exercise, nutrition education, smoking cessation, mental health resources, skills training for heart-healthy lifestyles, and peer support from others who are experiencing a similar life event. It has a Class IA indication for recent cardiac-related events or procedures, meaning there is high-quality evidence that it is beneficial to patients. In fact, individuals who complete the full program of 36 sessions have a 47% lower risk of death and a 31% lower risk of heart attack than those who attend only one session. The evidence is clear that CR extends life and improves quality of life for patients with a recent cardiac-related event or procedure. Unfortunately, only one in three eligible Michiganders participates—a rate well below the Million Hearts nationwide goal of 70% participation.

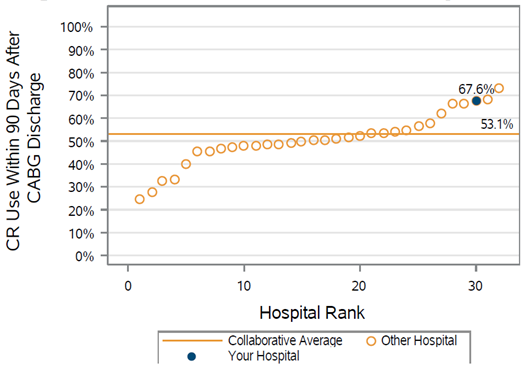
Using claims data, MVC can assess both initiation and adherence – whether and when someone starts CR, and how long they keep going. There is wide variability in CR rates between MVC’s member hospitals (see Figure 1 for a sample plot from a recent blinded report). The site with the highest rate of cardiac rehab after coronary artery bypass graft surgery (CABG), for example, succeeds at sending 75% of their CABG patients to CR, while another only sends 28% of their CABG patients. This variation shows that it is possible to reach high CR rates, and hospitals can learn from each other to make improvements that save lives and reduce costs.

Figure 1. Collaborative-Wide CR Use Following CABG Discharge
MiCR was developed for this reason and will work to equitably increase CR participation for all eligible individuals in Michigan. Serving as Co-Directors of MiCR are Mike Thompson, Co-Director of MVC, and Dr. Devraj Sukul, Associate Director of BMC2 PCI. MiCR will distribute regular CR utilization summaries to relevant providers, convene regular meetings with its stakeholder and advisory groups, create resources that help hospitals and CR facilities optimize CR utilization, and continue to leverage the expertise of both CQIs.

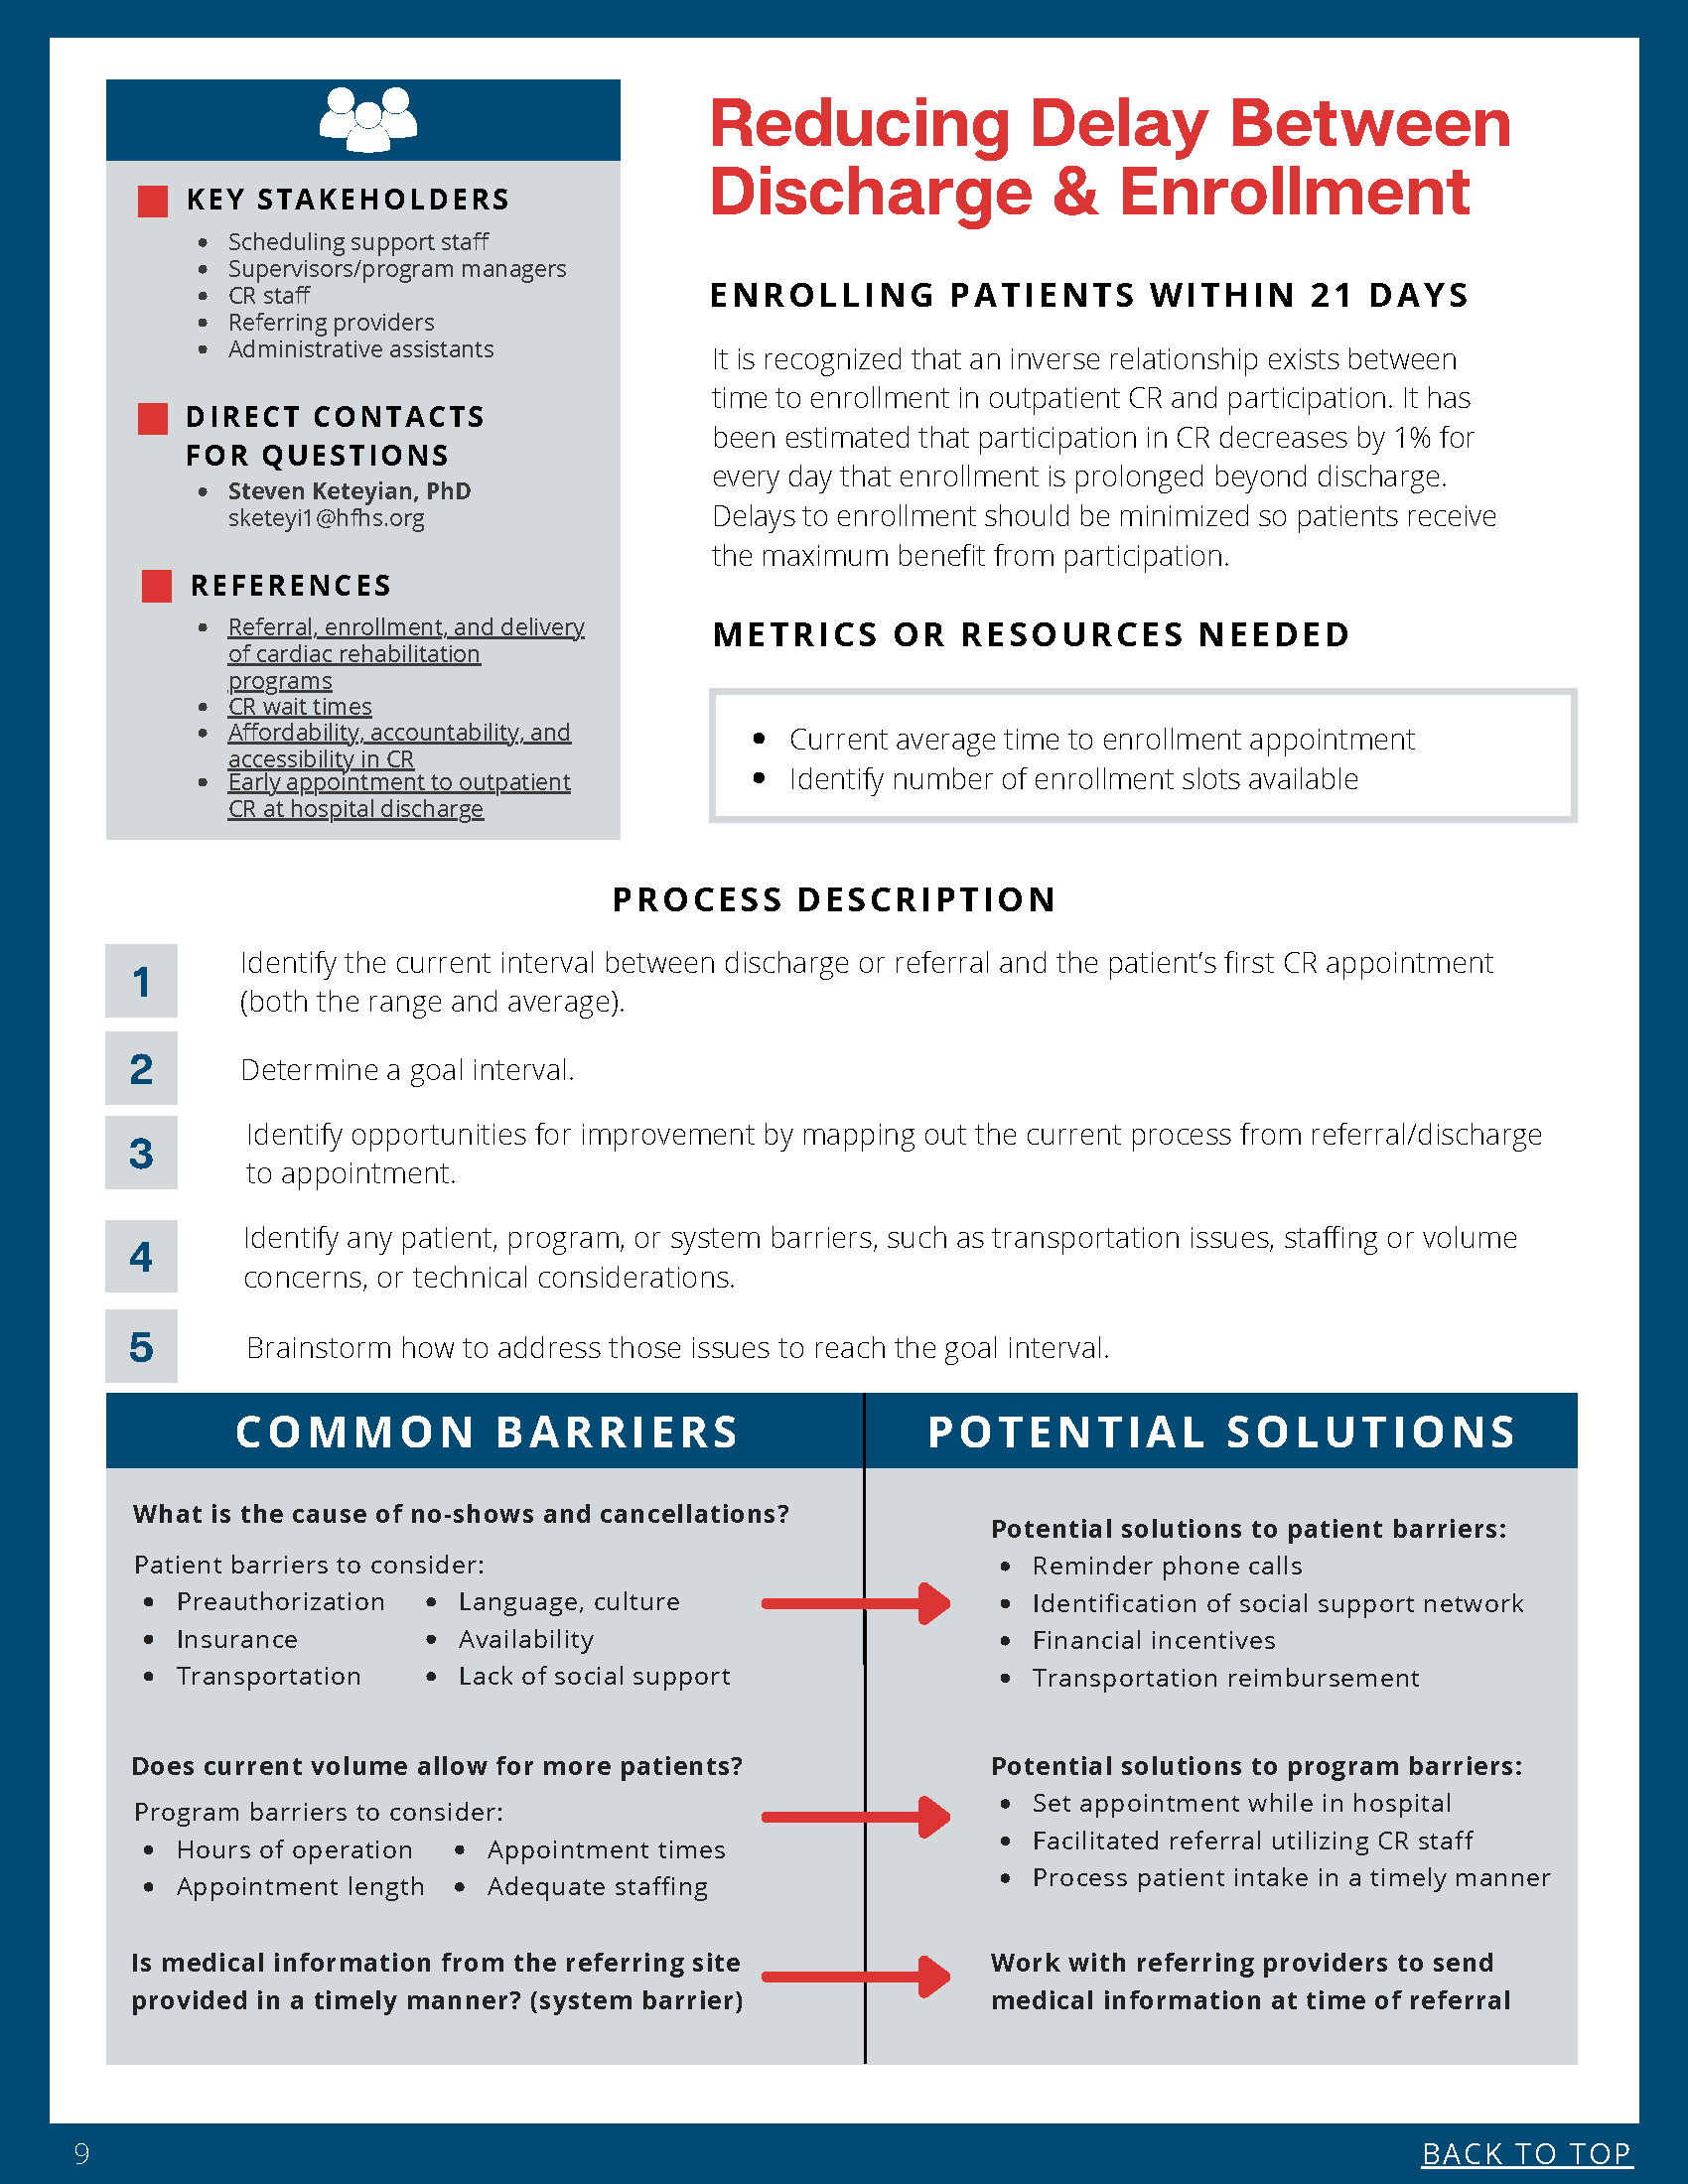
In one of its first coordinated efforts, MiCR worked with CR providers and content experts to create a Cardiac Rehab Best Practices Toolkit, which was launched in April. It outlines initiation, maintenance, and innovation strategies for increasing the utilization of CR (see Figure 2 for a sample page). MVC encourages members to turn to this tool as they work to encourage the enrollment of more patients.

Figure 2. Sample Page from MiCR Best Practices Toolkit
The partner CQIs behind MiCR also released new statewide goals for improved CR utilization. Currently, 30% of patients utilize CR following transcatheter aortic valve replacement (TAVR), surgical aortic valve replacement (SAVR), coronary artery bypass graft surgery (CABG), percutaneous coronary intervention (PCI), and acute myocardial infarction (AMI). The first goal is to reach 40% CR utilization for TAVR, SAVR, CABG, PCI, and AMI patients. In addition, only about 3% of congestive heart failure (CHF) patients currently utilize CR. The second statewide goal is a collaborative-wide utilization rate of 10% for CHF patients. Progress on these goals will be shared by MVC in its CR reports sent every six months.

The two CQIs will also continue with their respective activities in the CR space. MVC supports CR participation in two primary ways. One is providing opportunities for MVC members to collaborate, and the second is the preparation of reports using its unique multi-payer data sources. The MVC team supports collaboration through stakeholder meetings and workgroups, which allow sites and clinicians to share solutions for common challenges. The reports MVC prepares analyze member claims data with time-specific hospital-level information on CR enrollment and completed visits within one year of discharge. This allows hospitals to benchmark their performance against peers and identify areas for improvement. MVC will also share unblinded data on CR rates with members at its May semi-annual meeting in one week, which is meant to drive conversation and encourage best practice sharing across the collaborative. The MVC team hopes that its outreach and resources help members to save lives by providing strong endorsements for CR and addressing barriers that may limit patient participation.

For more information on MVC’s CR efforts, visit MVC’s Value Coalition Campaign webpage. For more information about CR, view this MVC video or visit the Million Hearts website. If you have questions about any of the above activities or resources, reach out to the Coordinating Center at michiganvaluecollaborative@gmail.com.

4
View Post
MVC Draws Attention to Cardiac Rehab in Promotional Week

MVC Draws Attention to Cardiac Rehab in Promotional Week

Every February while the nation honors American Heart Month, a subset of heart health advocates spend one week paying tribute to the lifesaving value of cardiac rehabilitation. Last week the Michigan Value Collaborative (MVC) Coordinating Center joined in on Cardiac Rehabilitation Week by helping to increase awareness and promote MVC’s efforts to improve utilization. Over the course of the week, MVC distributed press releases, published a daily cadence of social media content on Twitter and LinkedIn, and launched a video about the importance of cardiac rehab – all in service of inspiring collaboration in this area.

Cardiac rehabilitation (CR) has a Class IA indication for recent cardiac-related events or procedures, meaning there is high-quality evidence that it is beneficial to patients. In fact, individuals who complete the full program of 36 sessions have a 25% lower risk of death and a 30% lower risk of heart attack than those who attend only one session. It also reduces hospital readmissions and saves thousands of dollars per patient per year of life saved. Nevertheless, CR is widely underutilized, with national utilization rates of only 25-50%. It is for this reason that MVC wishes to equitably increase CR participation for all eligible individuals in Michigan. Throughout CR week, therefore, MVC endeavored to define the value of CR, what it entails, and how the actions of MVC members impact CR participation.

MVC’s role in the CR space is two-fold. One is the preparation of reports using its unique multi-payer data sources, and the second is providing opportunities for MVC members to collaborate. The reports that MVC prepares for members analyze claims data with time-specific hospital-level information on CR enrollment and completed visits within one year of discharge. This allows hospitals to benchmark their performance against peers and identify areas for improvement. There’s a huge amount of variation in CR rates across many dimensions – hospitals, qualifying events, and payers. For example, the hospital with the highest rate of CR after coronary artery bypass graft surgery (CABG) succeeds at sending 75% of their CABG patients to CR, while another only sends 28% of their CABG patients. This variation shows that it is possible to reach high CR rates, and hospitals can learn from each other to make systemic improvements that get more patients into this life-changing (and cost-saving) program.

To support collaboration among its member base of 100 hospitals and 40 physician organizations, MVC hosted a special, one-time workgroup on CR last week as part of its newly launched “Health in Action” workgroup series. This series is meant to drive discussion and collaboration on special topics that rotate throughout the year. Last week’s session featured the expertise of two special voices in the world of CR: Steven Keteyian, Ph.D., Director of Cardiac Rehabilitation/Preventive Cardiology at Henry Ford Medical Group, and Greg Merritt, Ph.D., patient advocate and founder of Patient is Partner. The workgroup was well attended with over 100 guests, who benefitted from informative and inspiring presentations from both speakers.

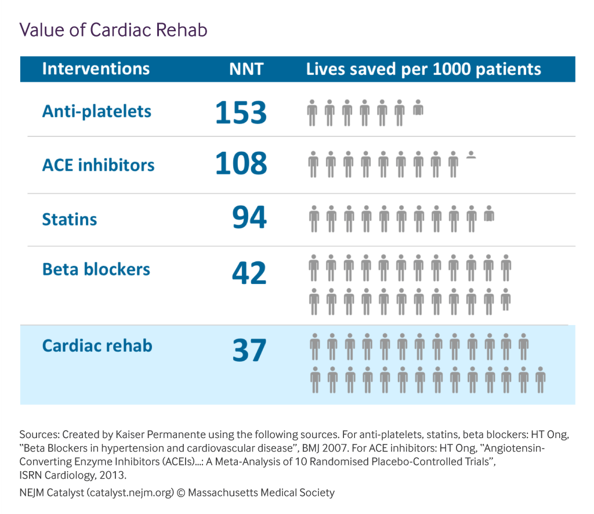
Dr. Keteyian presented updates on the clinical effectiveness of CR as well as some of the key barriers facing the field. There is high-quality evidence that CR is beneficial to patients on a variety of physiological measures, including improved exercise tolerance, decreased risk of future hospitalization, and decreased cardiovascular mortality. He also reiterated the value of cardiac rehab relative to other recommended cardiac interventions, with CR demonstrating more lives saved per 1000 patients than ACE inhibitors, statins, and other common medications (see Figure 1).

Figure 1. Calculating the Value of Cardiac Rehab

The current quality measures for CR suggest a patient’s time to enrollment should occur within 21 days of discharge, and that the patient should attend at least 36 sessions to receive the greatest benefit. The current goal for CR participation set by the Million Hearts initiative is 70%. However, Dr. Keteyian found that of the CR-eligible beneficiaries, only 28.6% participated and only 27.6% of those participants completed all 36 sessions. This represents a significant utilization gap. While discussing related challenges, Dr. Keteyian suggested that hospitals implement EMR-driven automatic referrals, overt provider endorsements, and an inpatient liaison to bridge the gap between referral and enrollment. He also recommended the use of hybrid CR programs that leverage telehealth to offer remote options.

Dr. Merritt’s presentation included his own personal story of surviving a cardiac event and his ensuing participation in a CR program. Following his experience, he became a “patient questionologist” dedicated to finding opportunities for patient and provider collaboration. His story ultimately led to the founding of an organization called Patient is Partner, which is dedicated to the principles of patient-partnered care. Inspired by the writings of behavioral scientists as well as Why We Revolt by Victor Montori, Dr. Merritt outlined a vision for healthcare innovation that invites patients and their unique perspectives to help solve healthcare’s greatest challenges. He encouraged attendees to join the movement and invite more patient voices to contribute to their respective committees and teams.

At the conclusion of the week, the MVC team had helped its audiences connect to educational materials, data, specialists, former patients, and successful peers in this space. The Coordinating Center is eager to continue this momentum from CR Week in pursuit of a variety of goals for 2022 and beyond. If your hospital or physician organization is interested in improving CR utilization rates, you can learn more about how MVC supports members to increase CR enrollment or reach out directly at michiganvaluecollaborative@gmail.com. You can also view a recording of the full CR workgroup here.
3

Reports Identify Opportunity to Reduce Preoperative Testing

MVC distributed its final push report of 2021 this week when the Coordinating Center distributed preoperative testing reports to members. It provided recipients with refreshed data using only Blue Cross Blue Shield of Michigan claims in order to provide the most up-to-date and granular preoperative testing information available.

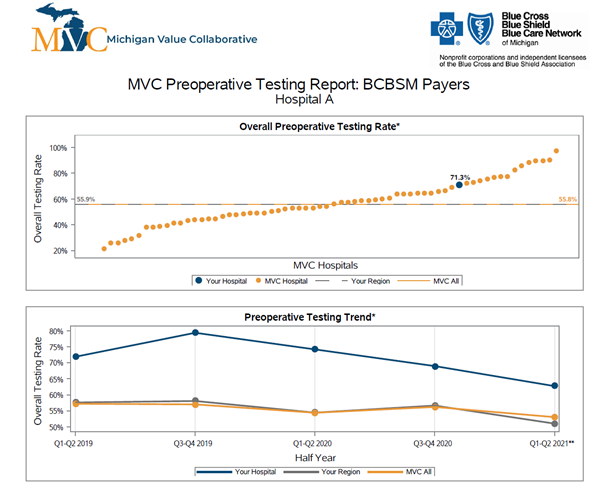
In general, the report demonstrated significant variation in testing rates between members, with preoperative testing rates ranging from 20% to over 90%. The average overall testing rate was 56% when looking at only the BCBSM payers, whereas the rate was 62% when looking at all payers in the earlier version of the report from February of 2021. The report included overall testing rate (Figure 1), preoperative testing rate trends over time (Figure 1), and rates for specific tests and procedures.

Figure 1. Blinded Preoperative Testing Push Report Graphs

Due to the amount of variation, MVC suspects that preoperative testing is overused at the state level such that even hospitals that are average or below average may still have significant opportunities to safely reduce preoperative testing.

Preoperative testing, especially in low-risk surgical procedures, often provides no clinical benefits to patients. Despite this, these services continue to be ordered regularly at hospitals across Michigan. Eliminating unnecessary and, in some cases, potentially harmful preoperative testing represents a clear opportunity to improve value in surgery. The MVC Coordinating Center uses administrative claims data and engagement with MVC members to try and reduce the use of unnecessary preoperative testing for surgical procedures to improve quality, reduce cost, and improve equity of care delivery throughout Michigan. The MVC Coordinating Center’s work on this issue is supported by a stakeholder working group to advise ongoing activity and provide insights on the best approaches to improve member awareness and practices.

This latest preoperative testing report also marked the conclusion of one year’s worth of activity in support of MVC’s Preoperative Testing Value Coalition Campaign. As part of MVC’s commitment to improve the health of Michigan through sustainable, high-value healthcare, the Coordinating Center developed specific focus areas to drive improvement. These are termed ‘Value Coalition Campaigns’ (VCCs).

In an effort to communicate progress on its Preoperative Testing VCC, the Coordinating Center recently compiled a 2021 Preoperative Testing Progress Report (see Figure 2) and included it as an attachment with the most recent report communications. Accomplishments included the development of educational flyers and resources, a published manuscript, partnerships with fellow Collaborative Quality Initiatives (CQIs), and custom analytics prepared for members. In addition, the Coordinating Center set several goals for 2022, such as developing provider-level reporting and hosting a dedicated symposium or workgroup, among others.

Figure 2. MVC 2021 Preoperative Testing VCC Progress Report

The Michigan Value Collaborative is eager to reduce unnecessary preoperative testing. If you are interested in a more customized report on preoperative testing practices at your hospital or physician organization or you want to learn more about the stakeholder working group, please contact the MVC Coordinating Center at michiganvaluecollaborative@gmail.com.
