Off
View Post
March Workgroups Highlight Rural Remote Patient Monitoring and Post-Discharge Follow-Up Innovations

March Workgroups Highlight Rural Remote Patient Monitoring and Post-Discharge Follow-Up Innovations

In March, the Michigan Value Collaborative (MVC) hosted two workgroups highlighting innovative strategies to improve care transitions and expand access to care across Michigan. A rural health workgroup explored how McKenzie Health System implemented remote patient monitoring to support patients with chronic conditions. MVC’s post-discharge follow-up workgroup featured a presentation from MyMichigan Health on the development of a continuing care clinic designed to improve post-discharge follow-up and reduce hospital readmissions.

Together, these presentations demonstrated how healthcare organizations can leverage care coordination, technology, and new care delivery models to improve patient outcomes across the continuum of care. The MVC Coordinating Center hosts one to two workgroup presentations per month covering a variety of topics including post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action.

Rural Health Workgroup – McKenzie Remote Patient Monitoring

The first workgroup of the month featured a presentation led by Heather Baumeister, BSN, RN, CRHCP, Director of Healthcare Practices at McKenzie Health System, who shared how her organization implemented a remote patient monitoring (RPM) program to better support patients living in rural communities.

McKenzie Health System includes a 25-bed critical access hospital (CAH) located in Sandusky, Michigan. The organization also operates six primary care clinics across multiple communities throughout the Thumb region offering several specialty services such as gastroenterology, orthopedic care, general surgery, and behavioral health. Like many rural health systems, McKenzie serves a geographically dispersed patient population where travel distance and limited healthcare resources can make frequent in-person visits difficult. To help bridge these gaps, Baumeister said, the organization relies heavily on care coordination.

McKenzie currently employs three full-time and one part-time registered nurse care coordinators who support primary care clinics across the system. Baumeister described how these coordinators conduct daily follow-ups with patients seen in the emergency department and help connect patients without an established primary care provider to appropriate outpatient care. Care coordinators also participate in monthly readmission review meetings to identify patients who may benefit from additional care management services and reduce avoidable hospitalizations.

Launching a Remote Patient Monitoring Program

To expand its ability to monitor patients between visits, McKenzie Health System participated in an 18-month pilot program focused on RPM for rural health systems. After completing the pilot, McKenzie established a long-term partnership with an RPM vendor to manage several operational aspects of McKenzie’s RPM program, including device shipping, monitoring, nurse outreach for readings outside clinical thresholds, uploading data into the electronic health record (EHR), and billing services. Baumeister said this helped clinicians at McKenzie to integrate RPM into their care model without needing to manage the technical infrastructure internally.

Providers refer patients to the program through the organization’s EHR. After receiving a referral, the RPM vendor enrolls the patient and distributes the appropriate monitoring devices. Patients enrolled in the program receive connected monitoring devices that automatically transmit readings directly to the monitoring platform after patients begin taking measurements. Devices currently used include blood pressure cuffs, weight scales, blood glucose monitors, and pulse oximeters. If readings fall outside predetermined ranges, a monitoring nurse contacts the patient to assess symptoms and determine whether clinical intervention is needed. If necessary, the nurse escalates the case to the patient’s provider according to established care protocols.

Implementing the program in a rural context presented several challenges. Baumeister described how unreliable internet near Michigan’s lakeshore, difficulty reaching patients by phone, and excessive measurement were challenges in delivering the program.

Benefits of RPM Program

Baumeister said the RPM program is particularly beneficial for patients managing chronic conditions like congestive heart failure, diabetes, hypertension, chronic obstructive pulmonary disease, and obesity. This is because remote monitoring enables care teams to detect early warning signs of health deterioration that might otherwise go unnoticed between routine visits so providers can intervene proactively. Baumeister gave examples such as adjusting medications, scheduling follow-up appointments, or providing additional education before conditions worsen.

She also noted that many patients became more engaged in their own care through the program, as regular monitoring helped them better understand how lifestyle choices affect their health. View the complete workgroup recording using the video below.

MVC Rural Health Workgroup: March 3, 2026

Post-Discharge Follow-Up Workgroup – MyMichigan Health Continuing Care Clinic

MVC’s second March workgroup featured a presentation by Steven Frazier, MHA, BA, RN, ACM-RN, Director of Quality and Patient Safety for Post-Acute Services at MyMichigan Health, and Dr. John Hagan, DO, Family Medicine Physician and Medical Director of the Continuing Care Clinic at MyMichigan Health. Their presentation highlighted the MyMichigan Health Continuing Care Clinic (CCC), a program designed to ensure patients receive timely follow-up care after hospitalization and to reduce hospital readmissions. Frazier previously presented about the establishment of the CCC program at MVC’s May 2024 collaborative-wide meeting, and this month provided a number of updates on progress in the program to date.

MyMichigan Health serves more than one million Michigan residents across a 26-county region, with multiple medical centers and roughly 1,100 hospital beds. Despite this extensive network, MyMichigan recognized that many patients faced barriers to obtaining timely follow-up care after leaving the hospital, citing limited appointment availability with primary care providers as well as patients without established providers struggling to navigate the healthcare system.

Frazier and Hagan said internal MyMichigan data revealed hospital readmissions were often occurring 12-13 days after discharge, highlighting a critical window when follow-up care could potentially prevent complications. Research also suggested that follow-up with a physician within seven days of discharge could significantly reduce both readmission and mortality risk for patients hospitalized with conditions such as heart failure, myocardial infarction, and COPD.

Launching and Evolving the Continuing Care Clinic

To address these gaps in care, MyMichigan Health opened the CCC in Midland, Michigan in August 2023. The clinic now operates with two locations (Midland and Alma) and three providers, supported by a multidisciplinary care team. The clinic was designed to function as a transitional care bridge, ensuring patients receive follow-up care within seven days after discharge while they wait to reconnect with their primary care providers. Services currently range from follow-up visits and assistance with establishing a primary care provider to behavioral health support and advance care planning.

Since its launch, the clinic’s role has expanded beyond its original focus on hospital discharge visits to support patients who are transitioning between primary care providers, are new to the community’s providers, need additional support navigating the healthcare system, or are seeking follow-up after emergency or urgent care visits. This evolution has allowed the clinic to function as a comprehensive transitions-of-care hub within the MyMichigan Health system.

Early Results and Impact

According to Frazier and Hagan, the CCC has already demonstrated encouraging results, saying that the program helped the health system achieve lower readmission rates compared to peers and maintain short scheduling lead times for follow-up appointments. Additionally, MyMichigan has seen an improvement in operational efficiency and budget performance with the expansion of services to additional geographic regions within the system. The program has also helped bring new patients to the MyMichigan Health network by connecting individuals without primary care providers with internal ongoing care relationships.

Patient feedback has been an important indicator of the clinic’s success, the presenters noted. Patient testimonials were shared during the presentation that emphasized how the clinic helped patients better understand their diagnoses, feel supported during recovery, and access care more easily after discharge. Patients described the clinic as a valuable resource that provided compassionate care and guidance during a vulnerable time in their healthcare journey. View the complete workgroup recording using the video below.

MVC Post-Discharge Follow-Up Workgroup: Mar. 19, 2026

Key Takeaways for MVC Members

The March workgroups highlighted two practical approaches to improving patient outcomes across the care continuum, with several key themes emerging. For one, remote patient monitoring is expanding access to care by helping teams identify early warning signs and better manage chronic conditions—especially in rural communities. At the same time, dedicated transition clinics are strengthening post-discharge care by ensuring timely follow-up and support after hospitalization.

Across both models, strong care coordination remains essential, supported by multidisciplinary teams, clear communication, and sometimes newer technologies. Just as important, patient engagement continues to drive better outcomes by empowering individuals to take a more active role in their care.

Through these shared examples, MVC workgroups continued to support collaboration and help organizations across Michigan identify actionable strategies to improve quality, outcomes, and value. If you are interested in pursuing a healthcare quality improvement project, MVC has data specialists available to help you navigate our data resources and create custom analytics reports to support your efforts. Please reach out to us by email [LINK] if you would like to learn more about MVC data, engagement offerings, or would like to present at a future MVC workgroup.

 

Off
View Post
MVC Virtual Networking Event: Leveraging Claims Data for Rural & Critical Access Hospital Quality Initiatives

MVC Virtual Networking Event: Leveraging Claims Data for Rural & Critical Access Hospital Quality Initiatives

On August 21, 2025, MVC Coordinating Center hosted a virtual networking event providing members from rural, critical access, and acute care hospitals with an opportunity to make professional connections and discuss strategies for leveraging claims data. Twenty-three MVC members from twenty different hospitals and eight health systems participated in the ninety-minute event.

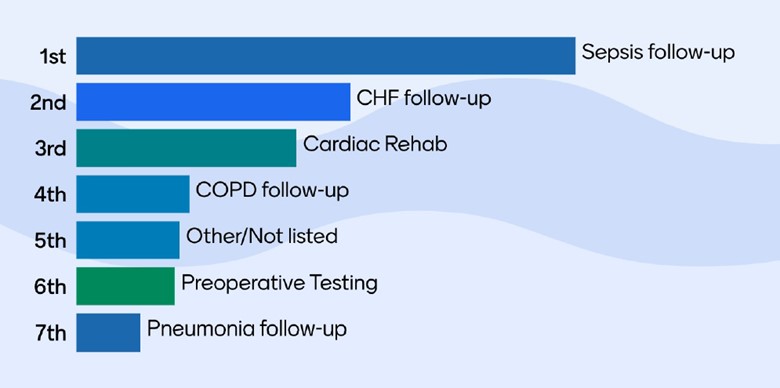
The event began with an ice breaker activity and a brief interactive quiz reviewing the number of and CMS requirements for rural and critical access hospitals (CAHs). This portion of the event concluded with a survey of MVC value metrics most relevant to quality improvement (QI) at rural and CAHs revealing most sites are focused on sepsis follow-up (Figure 1).

Figure 1. Most relevant MVC value metrics to QI at your site

The networking event continued with a presentation by MVC’s Engagement Manager Jessica Souva, MSN, RN, C-ONQS highlighting MVC’s history with critical access and rural hospitals and the addition of ED-based episodes. Starting in 2016, CAHs began joining MVC membership and today twenty-four different CAH sites are active MVC members.

Souva emphasized the need to better serve this group by understanding their unique challenges. She then shared unblinded data on hospital-level index emergency department (ED) visits with behavioral health ICD-10 code rates for 30-day ED-based episodes from January 1, 2021 to November 30, 2024. Prior to sharing the data, members were asked where they thought their hospital’s rate would fall compared to the MVC All average, most felt their rates would be higher than the average. After sharing the data, most members found their rates to be lower than expected.

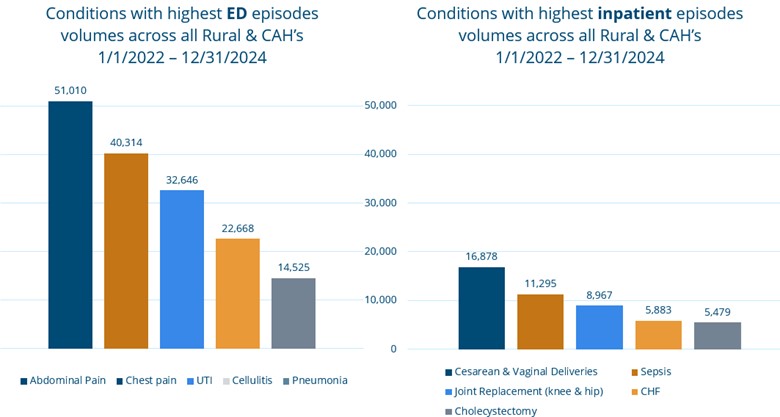
Aggregate data for conditions with the highest ED episode and inpatient episode volumes across all rural and CAHs from January 1, 2022 to December 31, 2024 were also shared (Figure 2). Souva encouraged members to discuss opportunities for benchmarking and custom analytics during the breakout session with this data in mind.

Figure 2. Conditions with the highest ED and inpatient episode volumes

vertical bar graphs of conditions with the highest ED and inpatient episode volumes

The breakout discussions were structured to engage attendees in conversations about the challenges and strategies to address leveraging claims data for rural and CAHs. After breaking into two smaller groups, attendees were provided with three primary discussion prompts to reflect upon:

  1. Data Possibilities: What data sources and metrics are frequently utilized to determine outcomes and impact of process improvements in the inpatient or ED setting?

MVC members reported that various internal data platforms and benchmarking tools such as Vizient, Premiere, and Q-Centrix are used by critical access and rural health sites. They also noted frequently using metrics provided by various collaborative quality initiatives (CQIs) (e.g., HMS, MEDIC, etc.) and Medicare Beneficiary Quality Improvement Project (MBQIP) Core Measure sets to evaluate process improvements. When asked how MVC can optimize benchmarking for rural and CAHs, attendees explored options for comparing data with similar-sized sites and increased alignment between CQI pay-for-performance (P4P) metrics.

  1. Data Sharing: Which stakeholders are commonly engaged in determining strategies and indicators of successful QI initiative implementation?

The discussions in both breakout rooms highlighted the importance of involving clinical leads, physician champions, and quality improvement oversight boards for the success of QIs. One hospital noted that they additionally include an executive sponsor for each QI which they find helps to drive QI forward. Others noted a shift in culture towards encouraging ownership of QI implementation to front line staff. They noted that with adjustments to quality departments’ scope and capacity, quality leadership can focus more on the “why” versus the “how” of QI.

  1. Conditions & Follow-Up Care: Are there specific conditions currently focused on reducing ED return visits and/or inpatient readmissions?

Key conditions of focus identified by MVC members include readmissions, chronic obstructive pulmonary disease (COPD), congestive heart failure (CHF), pneumonia, sepsis and diabetes. When asked if the data shared today inspired interest in new conditions or processes to investigate in the future, members noted interest in continuing to explore the utilization of behavioral health in ED-based episodes.

Feedback from members on MVC’s August Virtual Networking Event included:

  • “I enjoyed participating and sharing during this event.”
  • “This was very helpful. I would love more meetings like this specific to critical access hospitals and small rural hospitals.”
  • “These networking events are always great and provide great insight into what is happening across the state. It allows us to share ideas but there is also a validation component that we are all experiencing a lot of the same challenges and barriers.”
  • “This was a great networking event. As a member of an organization going through multiple ‘changes’, it was awesome to see how larger acute or rural hospitals tend to their QI projects.”
  • “There was a lot of great dialogs about changing culture and how we approach quality improvement.”

MVC looks forward to hosting additional networking events in the future to increase collaboration and connection with MVC’s members. The next networking opportunity will be an in-person networking dinner on October 9, 2025, the evening before MVC’s Fall Collaborative-Wide meeting. If you are interested in attending, please register for this event here. Please note that space is limited.

Off
View Post
September MVC Workgroups Highlight Initiatives for COPD Readmissions, High-Value Care for All

September MVC Workgroups Highlight Initiatives for COPD Readmissions, High-Value Care for All

Since its founding, a core component of MVC’s strategy has been organizing opportunities to collaborate with and learn from peers, leading to the ongoing facilitation of MVC workgroups. MVC has hosted workgroup presentations twice per month in recent years, and this year’s workgroups are focused on six topic areas: post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and health in action. Going forward, MVC will publish a monthly blog to highlight key takeaways and shared resources from the prior month’s presentations. In doing so, all MVC members and partners may utilize and benefit from the content regardless of their live participation.

September Post-Discharge Follow-Up Workgroup

MVC hosted a post-discharge follow-up workgroup on Sept. 10 featuring a presentation by Brian Leideker, RRT, COPD Navigator for Trinity Health Oakland Hospital. Leideker’s presentation summarized Trinity Heath Oakland Hospital’s progress since initiating an A3 COPD readmission committee in June 2021, including the key interventions their team has implemented to date.

One initial intervention was the hiring of a COPD navigator. Leideker described how his unique role as a respiratory therapist involved in case management has allowed him to be “a middleman between respiratory physicians and other entities trying to deliver and support services” for COPD patients.

Following several root cause analyses, the COPD committee identified that nearly 90% of patients readmitted for COPD at Trinity Health Oakland Hospital had an interruption in intended continuation of pharmacotherapy and/or non-pharmacotherapy treatments. This finding encouraged Leideker’s team to work to improve the education of patients, providers, and the greater healthcare community on ambulatory treatment for COPD as well as reviewing the testing and documentation needed to ensure coverage of durable medical equipment (DME) post-discharge.

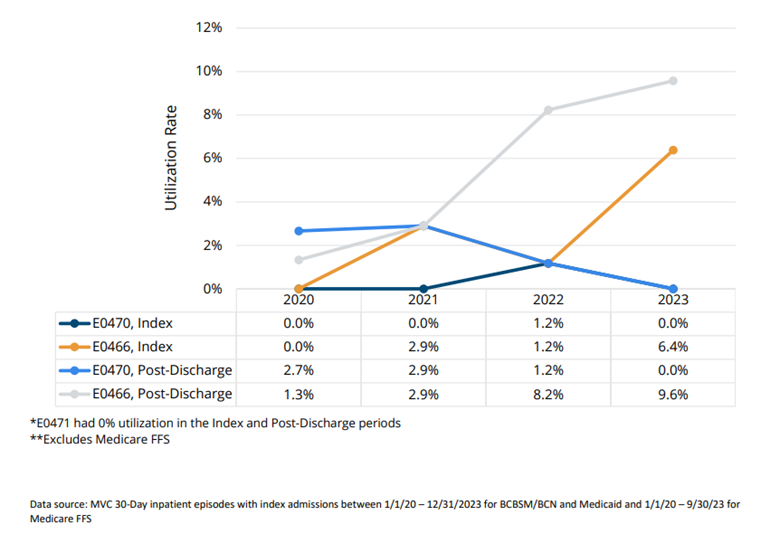
With the help of an MVC custom analytic report, Leideker was able to trend DME utilization rates for patients hospitalized with COPD since the initiation of these interventions, as seen in Figure 1.

Figure 1. Annual Select* DME Utilization Rates During the Index and 30-Day Post-Discharge Period Among Patients Hospitalized for COPD at Trinity Health Oakland (2020-2023)**

Generally, the utilization rate of post-discharge non-bi-level home ventilators (E0466) was found to increase over time, while bi-level home ventilator (E0470) utilization has decreased. Leideker noted that this was somewhat expected since patients routinely report difficulty with the utilization of bi-level home ventilators (BiPAP) and often move on to non-bi-level home ventilators (CPAP). Additionally, based on Trinity Health Oakland’s internal analyses as of May 2024, their COPD three-day readmission rates have been reduced to <18% for all payers.

Sept. 10 Post-Discharge Follow-Up Workgroup

September Rural Health Workgroup

MVC hosted a rural health workgroup on Sept. 26 featuring a presentation by Brent Mikkola, MBA, PMP, Manager of Community Health at MyMichigan Health. Mikkola’s presentation summarized MyMichigan Health’s strategic approach to ensuring high-value care for all and an overview of some specific community programs currently in place. MyMichigan Health’s strategic approach is currently focused on evaluating opportunities to overcome non-medical drivers of health in an “assess, analyze, and address” model.

Some unique community partnerships that resulted from this process include:

  • Gratiot County Public Transit voucher program
  • Rx 4 Health – partnership with Michigan State Extension and specific grocery suppliers including SpartanNash, SaveALot, and Meijer
  • Food Pharmacies & Weekend Kits - partnership with the Greater Lansing Food Bank and the Food Bank of Eastern Michigan
  • Bridge to Belonging - virtual series on loneliness and social connection
  • Continuing Care Clinic Pilot with Community Health Workers (CHWs)
  • Intervention for Nicotine Dependence: Education, Prevention, Tobacco and Health (INDEPTH) Suspension Diversion Program

In addition, Mikkola described how MyMichigan Health delved into the data collection, analysis, and quality improvement work surrounding gaps in healthcare outcomes. For example, after initially integrating CHWs into community practices and inpatient services, MyMichigan Health further integrated CHWs following the WHO’s CHW Lifecycle Approach. CHWs have become instrumental to MyMichigan’s assessment of non-medical drivers of health as required by CMS and JCAHO mandates; they have done so by filling gaps in system workflows and in the expansion of the Continuing Care Clinic Pilot. To date, nearly 500 well visit appointments have been completed by CHWs at MyMichigan. Of those patients, 34% were identified as experiencing gaps in care and 50% of those positive screens have now reportedly been met through connections to community support services.

To learn more about the efforts showcased by Trinity Health Oakland and MyMichigan Health, or to view past workgroup presentations, visit MVC’s YouTube channel here.

October’s workgroups will include a health in action presentation on Oct. 8 about the University of Michigan’s Hospital Care at Home program, as well as a sepsis presentation on Oct. 17 by Garden City Hospital. You can view the complete 2024 calendar of events and register for workgroups here. To learn more about MVC workgroups or other presentation opportunities, contact the MVC Coordinating Center by emailing us here.

Off
View Post
MVC Celebrates National Rural Health Day with MyMichigan Workgroup Presentation

MVC Celebrates National Rural Health Day with MyMichigan Workgroup Presentation

Today is National Rural Health Day. Since 2010, the National Organization of State Offices of Rural Health set aside the third Thursday of every November to highlight the unique healthcare challenges facing residents within rural communities and celebrate providers who deliver innovative, affordable, and coordinated rural healthcare. MVC’s current membership includes 44 hospitals based in rural communities, 22 of which are designated as Critical Access Hospitals (CAHs). In tribute to National Rural Health Day and the needs of its growing rural membership, MVC hosted a special rural health workgroup yesterday.

The workgroup featured a guest presentation by Stephanie Pins, MSA, CPHQ. Pins is the Director of Quality, Risk, and Compliance for MyMichigan Medical Center Sault, formerly War Memorial Hospital, and is co-leading the Health Equity Council for MyMichigan Health. She led the creation of a transportation program for War Memorial Hospital by working with local transportation companies and applying for grants to cover the cost of the program.

This guest presentation focused on how MyMichigan is supporting rural communities through their Non-Emergency Medical Transportation (NEMT) Project, and the steps their team took to develop this program. Beginning in 2024, CMS will require that hospitals screen admitted patients for five social determinants of health (SDOH) domains. One of those five required domains is transportation needs since access to transportation and distance to care have a significant impact on healthcare outcomes.

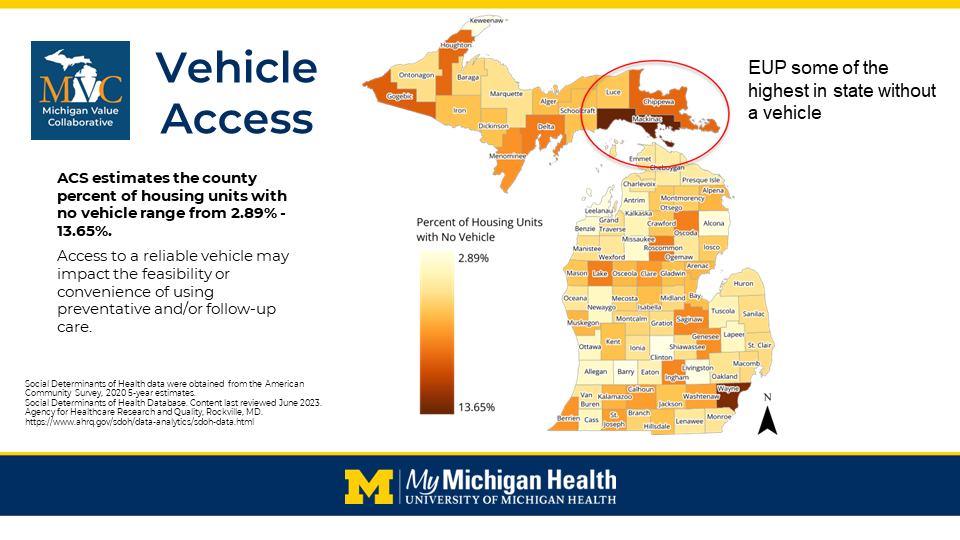
MyMichigan Medical Center Sault primarily services the very rural communities of Chippewa, Luce, and Mackinac counties, located in the eastern Upper Peninsula of Michigan. A resident of Drummond Island—part of Chippewa County—may have to drive as many as 70 miles each way to get to an appointment at MyMichigan Medical Center Sault. Limited vehicle access in this part of the state was highlighted recently at MVC’s fall collaborative-wide meeting; the eastern Upper Peninsula had some of the highest rates in the state for housing units with no vehicle (Figure 1).

Figure 1.

While presenting, Pins emphasized that once MyMichigan identifies a need through screening, the next step is to find a way to connect those patients with the assistance they need to access medical care. One transportation solution utilized by MyMichigan Medical Center Sault is the Road-to-Recovery program, offered in partnership with McLaren Northern Michigan in Petoskey. The MyMichigan Medical Center Sault location offers some oncology cancer treatment services, but not radiation, so patients may need to travel to Petoskey—a distance of over 90 miles—to receive radiation therapy as part of their cancer treatment. The fully funded Road-to-Recovery program is available five days a week free of charge to anyone in the eastern Upper Peninsula. A hospital-owned van is driven by a volunteer driver from the MyMichigan Medical Center Sault location to scheduled pick-up locations along the I-75 corridor to Petoskey. Service times are coordinated with McLaren Northern Michigan’s oncology group so all the patients using this service have aligned appointment times. Pins shared that one noteworthy ancillary benefit of this program has been the peer support and relationship building that resulted from patients traveling together for extended periods while going through a similar treatment experience.

A second transportation solution utilized by MyMichigan Medical Center Sault is the Rides-to-Wellness Program, a partnership effort with local transportation companies and Connect UP. Patients can use this service to travel to other appointments or patient care services and serves as a critical stopgap in ensuring patients have somewhere to turn for time-sensitive transportation needs. Pins shared that the patient testimonials from those utilizing the service are helpful evidence of its value to the eastern Upper Peninsula (Figure 2).

Figure 2.

MyMichigan Medical Center Sault identified several lessons learned from delivering its Rides-to-Recovery Program over the last 10 years and applied many of those lessons to the development of its more recent Rides-to-Wellness Program. Pins also shared several tips for starting similar hospital-based transportation support programs at other locations throughout the state (Figure 3).

Figure 3.

Those who missed the workgroup and would like to learn more about these two programs, how they are managed, and how they were developed can review the full recording here. MVC is excited to offer a new rural health workgroup series quarterly in 2024. Contact MVC if you are interested in receiving invitations to those workgroups.