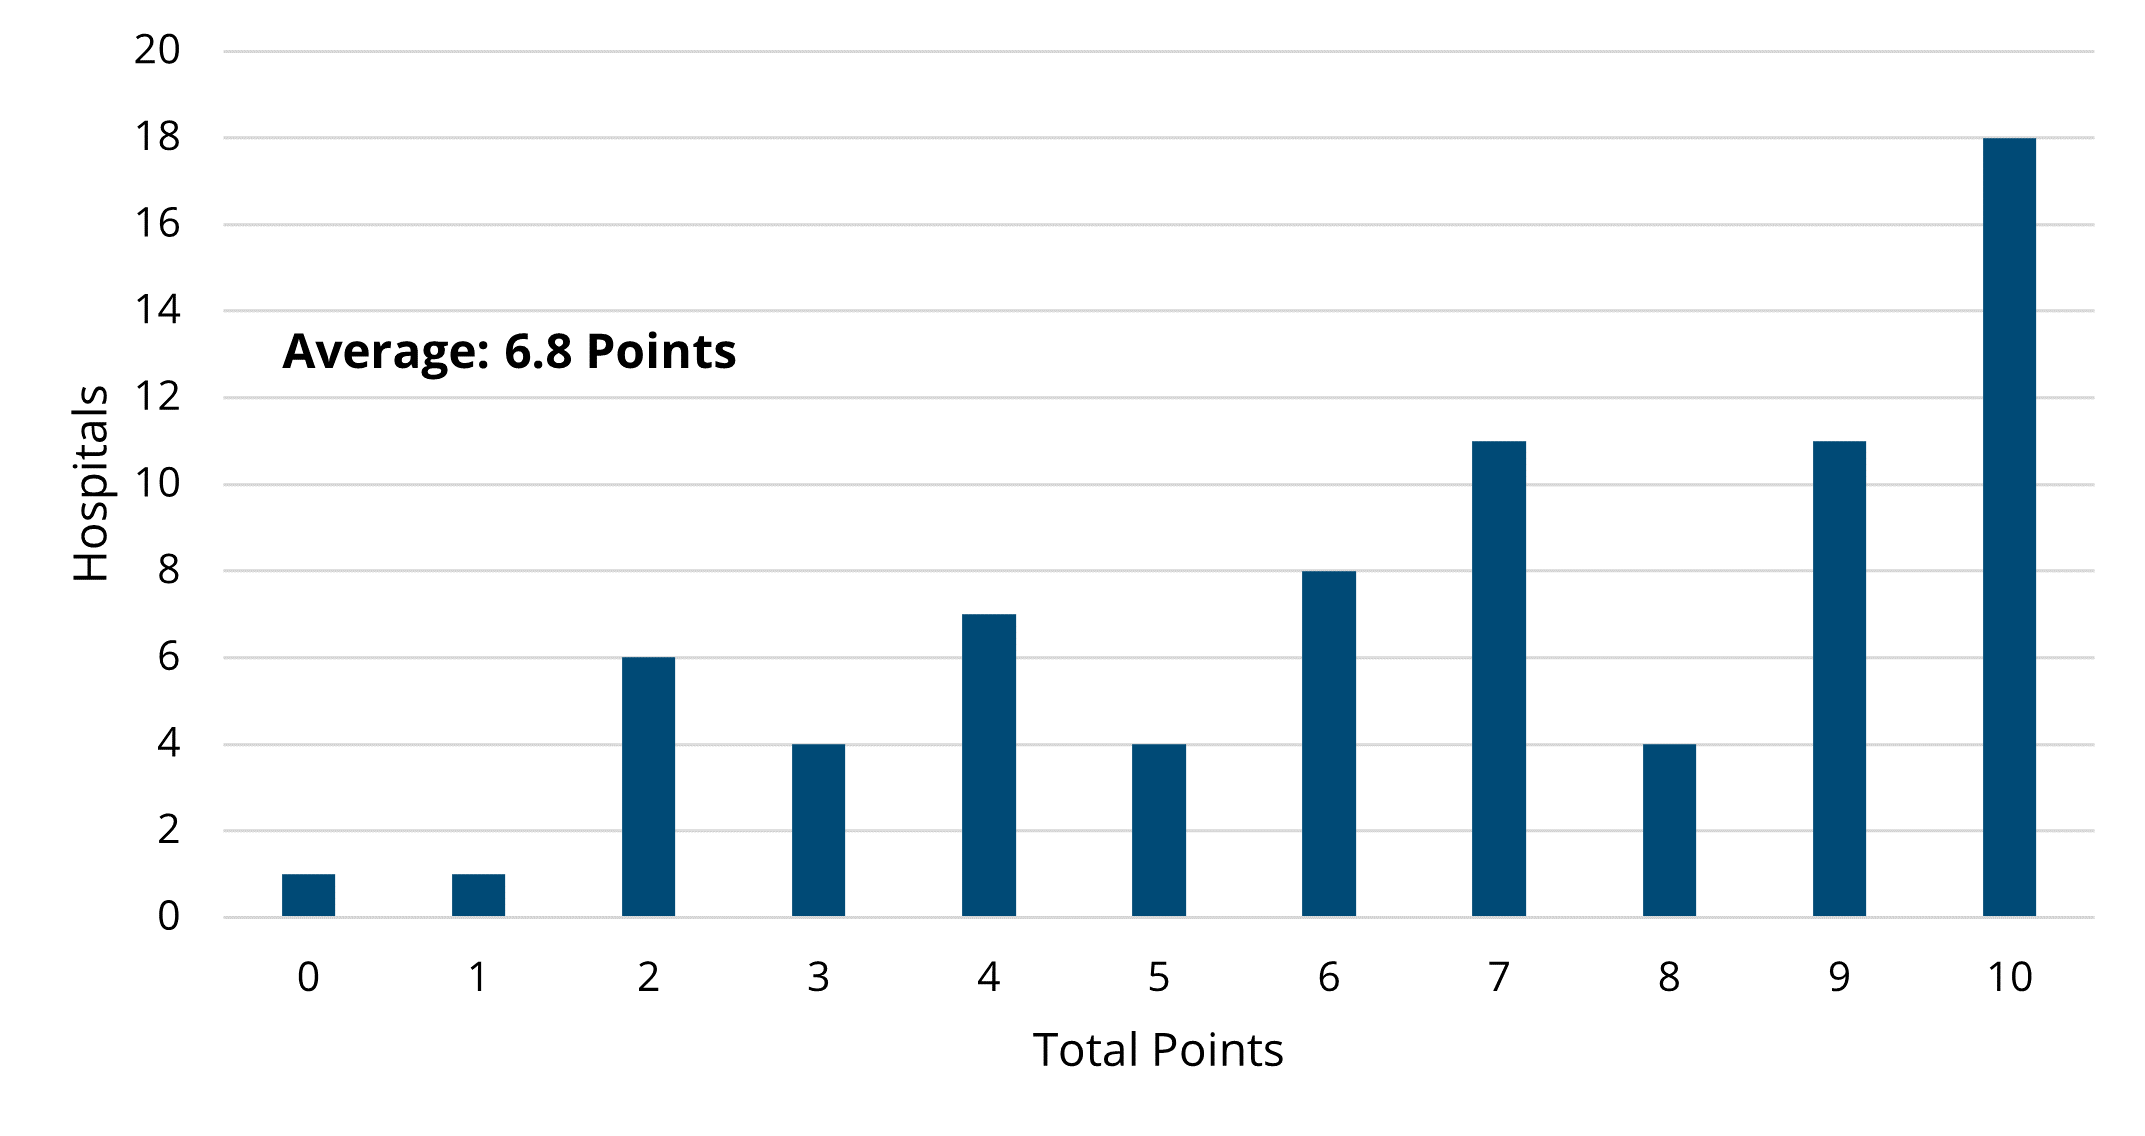2
View Post
Latest MVC Preop Testing Report Features New Figures and Data

Latest MVC Preop Testing Report Features New Figures and Data

This week MVC distributed its second preoperative testing push report of 2022, providing members with another opportunity to benchmark their testing practices. MVC first introduced its preoperative testing push reports in 2021 to help members reduce the use of unnecessary testing for surgical procedures. Preoperative testing, especially for low-risk surgeries, often provides no clinical benefits to patients but is ordered regularly at hospitals across Michigan.

The report distributed this week had many similarities to the version distributed earlier this year in April, namely that members continued to see their rates across a variety of tests for three elective, low-risk procedures performed in outpatient settings: laparoscopic cholecystectomy, laparoscopic inguinal hernia repair, and lumpectomy. Claims were evaluated for the index event as well as 30 days prior to the procedures for the following common tests: electrocardiogram (ECGs), echocardiogram, cardiac stress test, complete blood count, basic metabolic panel, coagulation studies, urinalysis, chest x-ray, and pulmonary function.

The latest report has a few key differences from the spring version, the most significant of which is that it utilizes claims from Blue Cross Blue Shield of Michigan (BCBSM) and Blue Care Network (BCN) plans exclusively. This allows members to see MVC’s most up-to-date data; the report includes index admissions from 1/1/2019 through 12/31/2021. In addition, since the report contains BCBSM/BCN data only, there is no case count suppression, whereas members would only see their data in the spring version if they had at least 11 cases in each year of data for the three combined conditions.

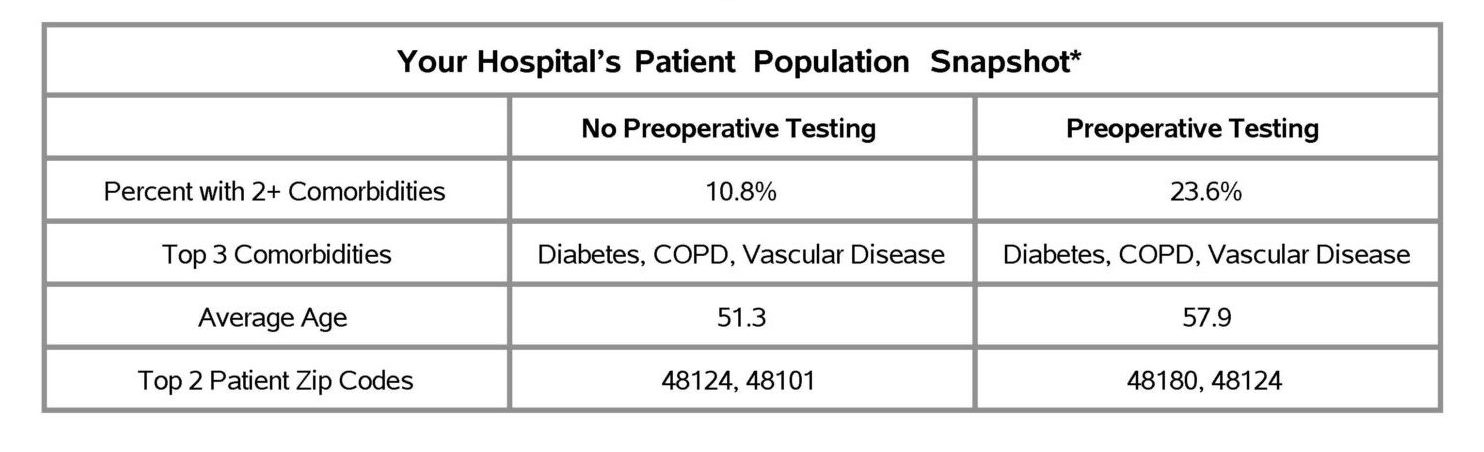
The reports received by members this week included several new figures. Similar to other MVC push reports, members will now see a patient snapshot table that provides additional information about the report’s patient population. For this, MVC chose to include patient characteristics such as age, zip code, and comorbidities. Generally speaking, there were more comorbidities among patients who underwent preoperative testing compared to patients with one or no comorbidities (see Figure 1). However, the majority of patients who complete a preoperative test do not have multiple comorbidities. There were also observed differences in testing rates by age. In general, patients who had preoperative testing were older on average than patients who had no preoperative testing.

Figure 1.
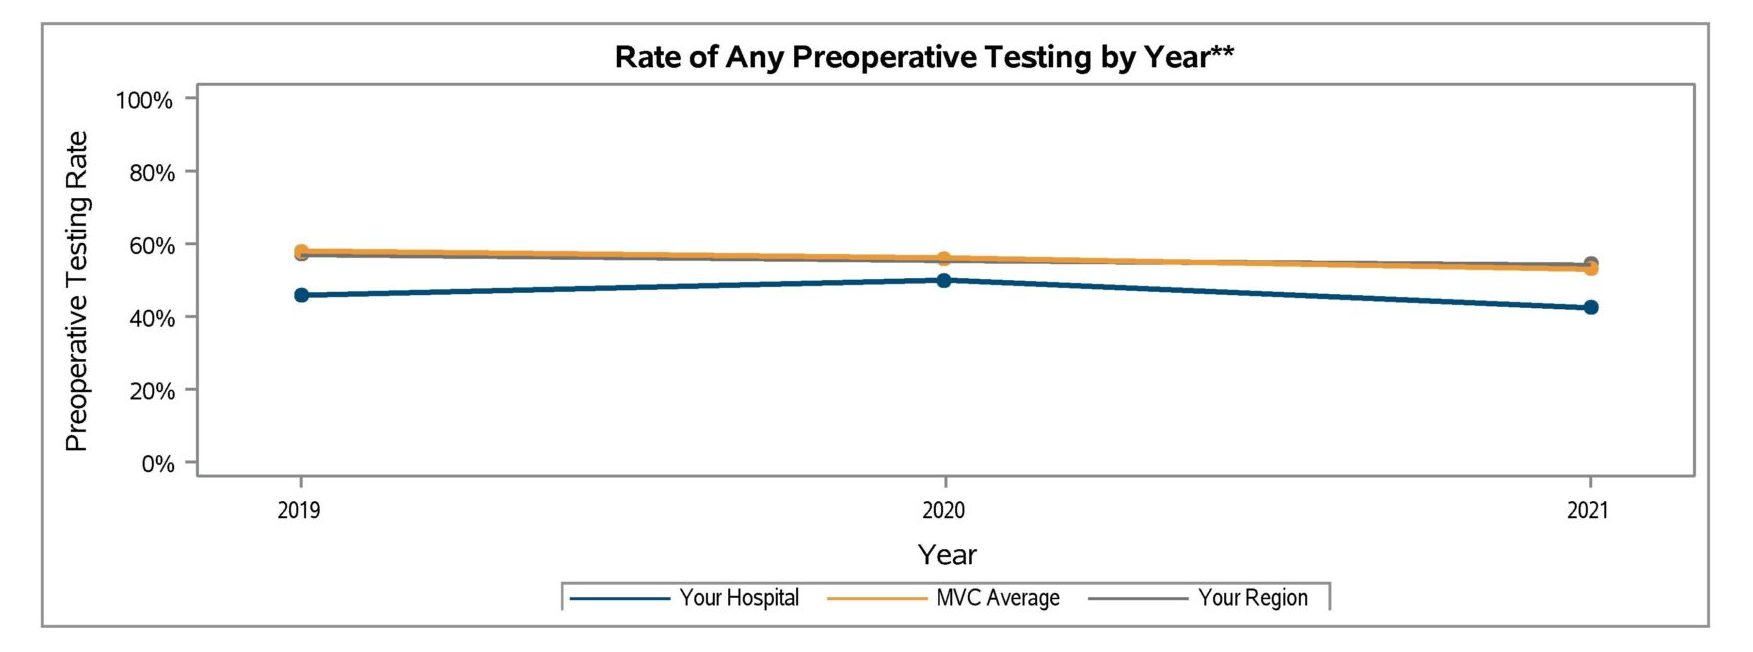
Another new figure showcased the overall preoperative testing rates by year. This trend graph showed members how their overall rate for any preoperative testing compared in 2019, 2020, and 2021, and it included data points for the MVC average and regional comparison groups (see Figure 2). The key finding for this figure was that there has been very little change in testing rates over time when looking at overall preoperative testing practices. This means that, in general, the prevalence of low-value preoperative testing has remained consistently high overall across the collaborative for three years and likely longer.

Figure 2.
The latest report also included a new figure for absolute change in any preoperative testing from 2019 to 2021. For each hospital, this appears as a caterpillar plot of absolute change percentages for their highest-volume procedure among the three low-risk surgeries in the report. Members can see the percentage change—positive or negative—in their testing rate for that surgical condition, as well as how their absolute change compares to the rest of the collaborative. For example, hospitals that perform more cholecystectomies than hernia repairs or lumpectomies saw a wide range of both increases and decreases in preoperative testing rates from 2019 to 2021 (see Figure 3).

Figure 3.
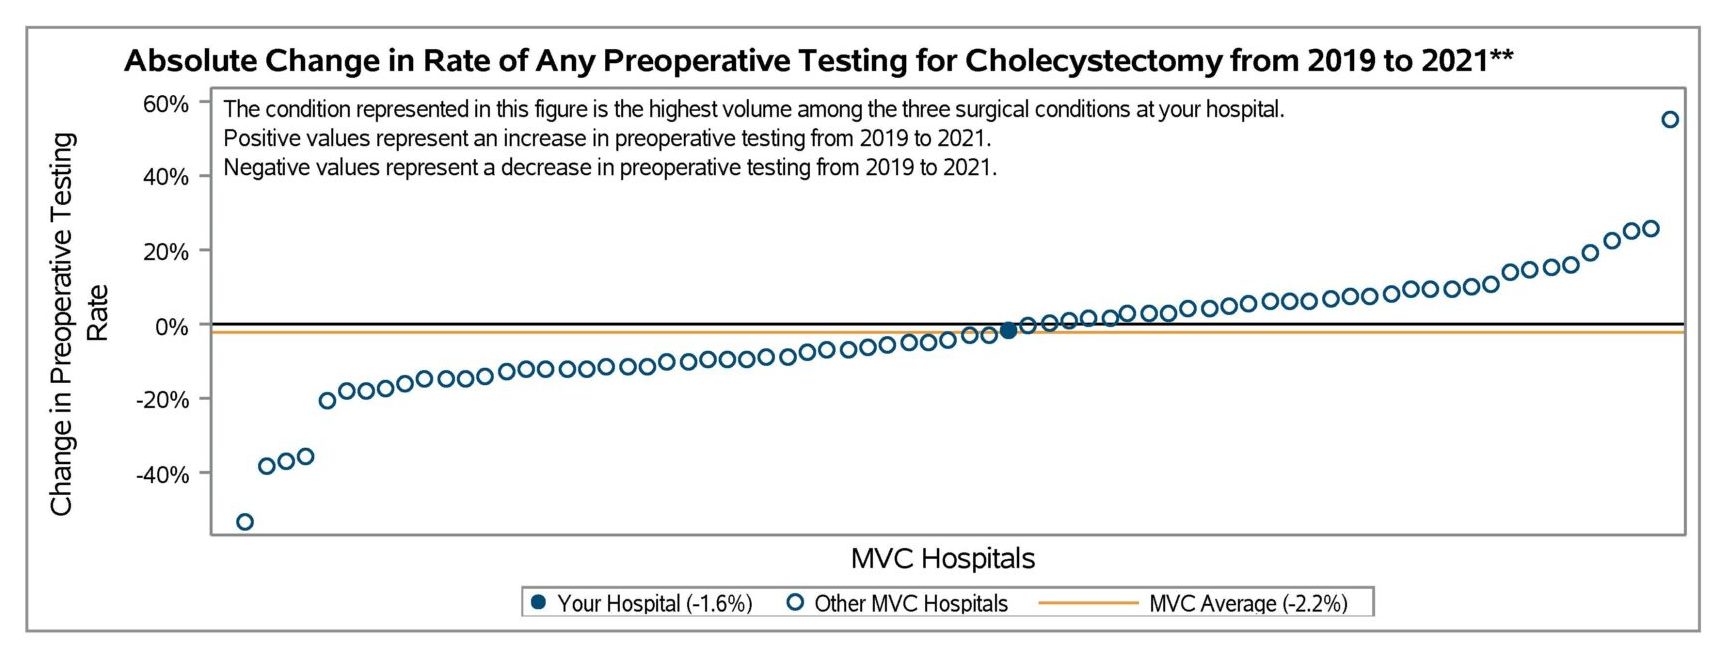
The blinded hospital in this example observed very little change in its testing rate for cholecystectomy (-1.6%), and the MVC average was similar (-2.2%). This showcases that although the collaborative is not seeing much change to overall rates for any testing over time, individual members might see greater variability over time for specific tests or procedures, especially in instances of low case counts.

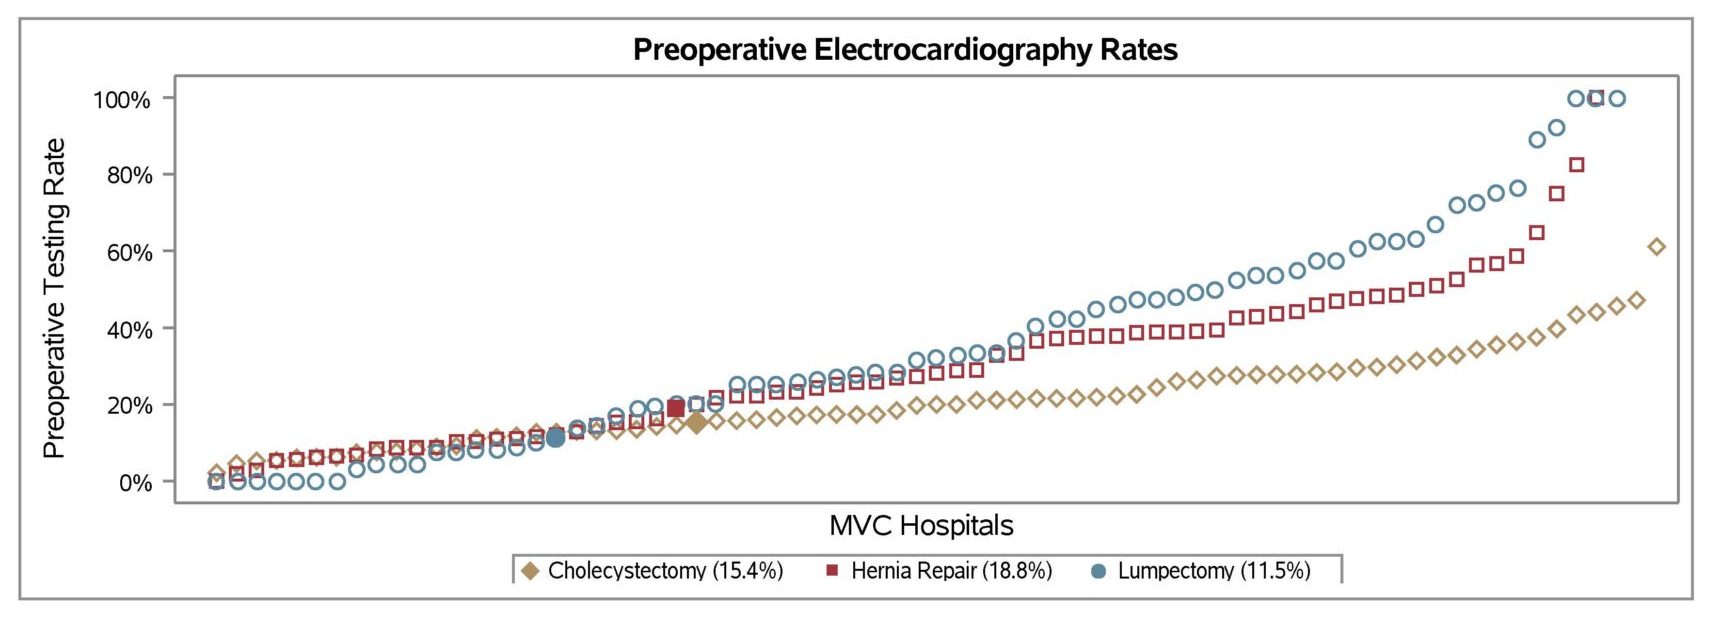
Members will be able to take those deeper dives into their rates for specific tests in the figures that make up the remaining pages of the report. Viewing one’s preoperative testing rates for each specific test can help members understand if any specific tests are driving their overall testing rate. One area of opportunity, for example, could be to reduce one's rate of cardiac testing, specifically ECGs; the rate of ECGs is very variable across the collaborative (see Figure 4) and could lead to a cascade of care.

Figure 4.
MVC is eager to drive improvement in this area. For more information on how MVC is working to reduce unnecessary preoperative testing, visit its Value Coalition Campaign webpage here. If you are interested in a more customized report or would like information about MVC’s preop testing stakeholder working group, please contact the MVC Coordinating Center at michiganvaluecollaborative@gmail.com.

1

Reflecting on MVC’s Accomplishments: January-June 2022

As we start the second half of 2022, the MVC Coordinating Center is taking a moment to pause and reflect on the tremendous work that has been accomplished over the past six months. Here is a look back at some of the highlights.

JANUARY

MVC Workgroups consist of a diverse group of representatives from Michigan hospitals and POs that meet virtually to collaborate and share ideas related to various topics. January kicked off with the launch of MVC’s new Health Equity Workgroup! The inaugural meeting featured speakers from the Michigan Social Health Interventions to Eliminate Disparities (MSHIELD) Collaborative. The Health Equity Workgroup has two more meetings in 2022 and we’d love to see you there! Visit the MVC 2022 Events Calendar to register and check the calendar for additional Workgroup offerings focused on Chronic Disease Management, Diabetes, Health in Action, Joint Replacement, and Sepsis.

FEBRUARY

MVC launched two new push reports in February, with the release of the new Physician Organization (PO) Colectomy Report, shared with 35 of MVC’s PO members, and the first-ever Pneumonia Push Report, distributed to 89 MVC hospital members[1]. To meet the needs of MVC’s growing hospital members, a subset of the Pneumonia Push Reports was tailored to meet the specific data needs of our Critical Access Hospital members.

MARCH

After completing 58 hospital site visits in 2021, MVC announced the creation of a robust quality improvement (QI) initiatives database, developed to track QI initiatives across the collaborative. The database, searchable by QI focus area and project status, allows MVC to understand common themes and challenges among all its members as well as within subgroups such as hospital size or region. In 2022, the MVC team is hosting site visits with our PO members and will be gathering QI initiatives to add to the QI initiatives database. The database is being used as a resource for custom analytic requests and a library of practice standards for members. If you are an MVC PO interested in participating in a virtual site visit, please contact the MVC Coordinating Center to schedule.

APRIL

In April, MVC distributed a refreshed Sepsis Push Report, developed in collaboration with the Michigan Hospital Medicine Safety Consortium. These customized reports provide hospitals with new insight on demographics for their sepsis patients, including the percentage of COVID-positive patients to illustrate how COVID has impacted their sepsis data, along with race, top comorbidities, and most common zip codes, stratified by payer.

MAY

MVC held its first collaborative-wide meeting of 2022 in May, with a focus on “Turning Data into Action.” Held virtually, a total of 158 leaders representing 68 different hospitals and 15 physician organizations (POs) from across the state of Michigan participated in the event. Save the Date for our next in-person collaborative-wide meeting, scheduled for Friday, October 28th at the Radisson Hotel Lansing!

JUNE

In June, the MVC Coordinating Center hosted its first in-person event since 2019, with a Regional Networking Dinner for our Eastern Michigan sites (Region 3). The dinner provided an opportunity for MVC hospital and PO members to come together to network, share ideas and discuss key priorities, including health equity initiatives. MVC’s next Regional Networking Event for Southeast Michigan (Region 4) is scheduled for Tuesday, September 27th. For identification of your MVC designated region, please see the MVC Regions Map here.

AND COMING SOON…

Along the way, the MVC team has been hard at work preparing for two new exciting developments:

  • MVC’s first Northern Summer Meeting (RSVP here) is scheduled for Thursday, August 18th at Traverse City’s Great Wolf Lodge. The agenda is tailored to highlight unique opportunities and challenges facing the Northern Michigan healthcare community. Interested MVC members serving Northern Michigan, the Upper Peninsula, and small/rural communities are encouraged to The University of Michigan Medical School designates this live activity for a maximum of 3.75 AMA PRA Category 1 Credit(s)™.  This meeting will feature presentations from:
    • Michigan Center for Rural Health
    • MyMichigan Medical Center – Sault
    • Munson Healthcare Grayling Hospital
    • Region 9 Area Agency on Aging

To learn more about these initiatives and other MVC happenings, visit the MVC blog!

Footnote

[1] Hospitals and POs not meeting case count thresholds did not receive a report.

2
View Post
MVC Coordinating Center Team Volunteers at Member Hospital

MVC Coordinating Center Team Volunteers at Member Hospital

As employers and managers endeavor to invest in their company’s culture, there is one often overlooked activity that can positively impact job satisfaction: volunteering. According to a study from Deloitte, cultivating a culture that encourages volunteerism can boost employee morale, workplace atmosphere, and brand perception. It found that 89% of employees believe companies with sponsored volunteer activities offer a better overall work environment and that 70% felt volunteering was a stronger boost to morale than company-sponsored happy hours. Since team culture and the retention of skilled employees have become increasingly important in the current job market, there has never been a better time to help staff feel connected to their community and teammates.

The Michigan Value Collaborative (MVC) experienced some of these benefits recently when the Coordinating Center team spent several hours volunteering together at a local MVC member hospital. This was the first time MVC had organized an official service day for its team. It took place at the Farm at Trinity Health, located at the Trinity Health St. Joseph Mercy Ann Arbor Hospital in Ypsilanti, MI. The MVC team spent several hours weeding, planting, and harvesting vegetables. After harvesting, the MVC team helped wash and pack fresh greens, salad mix, kale, and radishes for the Farm’s community-supported agriculture (CSA) program and patient produce boxes.

Selecting the Farm at Trinity Health as MVC’s service day location was an exciting opportunity due to its many connections to MVC’s priorities. The produce boxes distributed by the Farm help feed members of the community who experience food insecurity or hunger, as well as hospital patients who participate in programs like cardiac rehabilitation (CR). MVC has identified health equity as a strategic priority for 2022 and beyond, and also currently has a Value Coalition Campaign that encourages members to increase patient utilization of CR programs. The MVC team was excited to learn about this direct connection to CR patients and the program’s overall impact on community health. In addition, the Farm at Trinity Health is a participating site in the Washtenaw County Health Department’s Prescription for Health Program, which was a featured topic at MVC’s health equity workgroup earlier this year.

This service day also coincided with an overall shift in how MVC staff members interact. As MVC grew over the past two years, multiple new employees had only ever interacted with coworkers virtually because of the pandemic’s impact on in-person activities. That changed this past spring with MVC’s part-time return to in-person work and some in-person team-building events. The service day was intended to bring teammates together after many months apart to get to know one another, connect, and give back to the wider community.

If you have a story about an impactful program that could be shared with the Collaborative or wish to connect your team with local community volunteering, contact the MVC Coordinating Center for assistance at michiganvaluecollaborative@gmail.com. Learn more about the Farm at Trinity Health (formerly the Farm at St. Joe’s) here.

0
View Post
MVC Registry to Soon Include Patient-Level Medicare Data

MVC Registry to Soon Include Patient-Level Medicare Data

In the coming weeks, MVC registry users will receive communications outlining several required steps related to implementing the Coordinating Center’s new data use agreement (DUA) as a qualified entity (QE) with the Centers for Medicare and Medicaid Services (CMS). The QE DUA permits MVC to display Medicare Fee-For-Service (FFS) claims data with fewer data suppression limitations than its research DUA within its online registry. As a result, authorized users of the MVC registry may gain access to identifiable Medicare beneficiary data.

These changes are the result of years of work by the MVC team to earn its QE status through the Qualified Entity Certification Program (QECP), which is also known as the Medicare Data Sharing for Performance Measurement Program. The QE application includes multiple phases before an entity is permitted to show patient-level data. The MVC Coordinating Center has been working through the final phase (see Figure 1) of the application, which involves developing and documenting measures for public reporting.

Figure 1.

The QE Medicare data will be contained in a separate tab on the MVC registry. Authorized users will have access to both the existing Medicare FFS reports as well as the QE reports. The QE data will be available for the most recent 18 months of index admissions only and will not have any case count suppression, allowing users to see the more granular data that is censored in the Medicare FFS reports.

The QE reports also have additional patient population filters to view the data by patient comorbidities, patient age, and more granular date options. These reports also feature trend graphs that can be viewed monthly, quarterly, or annually. In addition to uncensored data, the QE data will allow for patient-level drill-down as is currently available in the Blue Cross Blue Shield of Michigan data. The drill-down includes detailed information on the patient’s comorbidities, price standardized episode payments, and claim level walk-through. Although patient drill-down is available, the provider identifiers have been removed in conjunction with the QECP regulations. Additionally, the skilled nursing facility report is not available in the QE reports to avoid identifying providers.

For those with access, the QE reports should be used when evaluating the most recent years of data. The Medicare FFS reports can still be useful for historical trends and the Coordinating Center may be able to provide custom reports to fill in information that isn’t available through the registry. The patient-level drill-down can be used in conjunction with a hospital’s clinical information to understand what led to high-cost patients. The QE data should make Medicare data more useful to hospital members. However, QE data is only to be used for quality improvement rather than for marketing purposes. Additionally, authorized users are prohibited from disclosing or redistributing data provided in these reports outside of their institution.

Next week MVC member hospitals will receive a new QE DUA to be reviewed and signed by an authorized representative from their institution. This signed DUA is a prerequisite for receiving access to the new QE pages once they are available. MVC’s current CMS research DUA will remain in effect on non-QE registry pages and will continue to utilize data suppression for fewer than 11 episodes to protect patient identities. The MVC registry will also implement multifactor authentication (MFA) upon login for all registry users regardless of QE access in order to comply with the new DUA's security and data privacy requirements.

In the coming weeks, MVC members and registry users are encouraged to be attentive to any communications containing additional details or requests. In the meantime, please contact the MVC Coordinating Center with any immediate questions at michiganvaluecollaborative@gmail.com.

2
View Post
MVC Welcomes Associate Program Manager Erin Conklin

MVC Welcomes Associate Program Manager Erin Conklin

Inspired by the Michigan Value Collaborative’s (MVC) vision and mission, I am thrilled to join the team as Associate Program Manager. In this newly created role, I will be responsible for supporting the management, performance, and daily operations of the MVC Coordinating Center.

After receiving my Master of Public Administration degree from the University of Michigan-Flint, I began my first role in the healthcare space at the Greater Flint Health Coalition (GFHC), a collaborative, cross-sector organization dedicated to improving the health status of Genesee County residents. This experience provided me with a unique opportunity to learn about a wide range of public health issues, such as the impact of social influencers, the complexity of care navigation for patients with mental health and substance use disorders, and the role of systemic racism and racial disparities in care. I gained valuable skills in project management, strategic planning, sustainable implementation, and partnership development.

Following my tenure with the GFHC, my career focused on managing quality and operational improvement initiatives that aimed to improve health outcomes through patient-centered, value-based care at leading institutions, including Michigan Medicine and Massachusetts General Hospital. This work included implementing new payment and service delivery models, such as the Pioneer ACO Model initiative and the Innovation Advisors Program, in partnership with the CMS Innovation Center. I also had the opportunity to support provider engagement and the expansion of evidence-based care delivery models across Michigan with the Centering Healthcare Institute and Michigan Opioid Partnership.

I am excited to serve as MVC’s new Associate Program Manager. I look forward to learning and collaborating with members, key stakeholders, and partner organizations to advance the mission, vision, and values of MVC. If you have any questions or wish to get in touch, please feel free to email me.

Off
View Post
Semi-Annual Summary: Turning Data & Collaboration into Action

Semi-Annual Summary: Turning Data & Collaboration into Action

The Michigan Value Collaborative (MVC) held its first semi-annual meeting of 2022 last Friday. A total of 158 leaders joined the MVC Coordinating Center’s virtual meeting, representing 68 different hospitals and 15 physician organizations (POs) from across the state of Michigan. “Turning Data and Collaboration into Action” was the theme of this year’s first semi-annual, putting the spotlight on quality initiatives that successfully leveraged data or collaboration to bring about improvements in healthcare.

MVC’s Director, Dr. Hari Nathan, kicked off Friday’s meeting with an update from the MVC Coordinating Center. He welcomed two new collaborative members, McLaren Caro Region and UP Health System - Bell, as well as MVC’s newest team member, Engagement Associate Chelsea Andrews. Dr. Nathan also highlighted the successes delivered by the Coordinating Center during the first six months of 2022. This included the incorporation of Medicaid data into MVC’s suite of push reports to provide a more complete view of the collaborative’s patient population, the launch of three new push reports (colectomy, pneumonia, and P4P), and the incorporation of additional demographic data into MVC's reporting.

MVC’s recent Qualified Entity accreditation was also highlighted, representing a breakthrough for the collaborative that will allow the relaxation of certain data use agreement regulations and improve the granularity of data available to members. As part of extending this improved access, the Coordinating Center will reach out to site coordinators to have authorized representatives at each institution complete a new data use form. To align with the security requirements of the Qualified Entity program, the MVC registry will also begin requiring multi-factor authentication for users upon login. More information on each of these elements will be shared with the collaborative in the coming weeks. Chelsea Abshire Pizzo, MVC’s Manager of Analytics, rounded off the meeting welcome by sharing some highlights from Program Year 2021 of the MVC Component of the Blue Cross Blue Shield of Michigan Pay-for-Performance (P4P) Program.

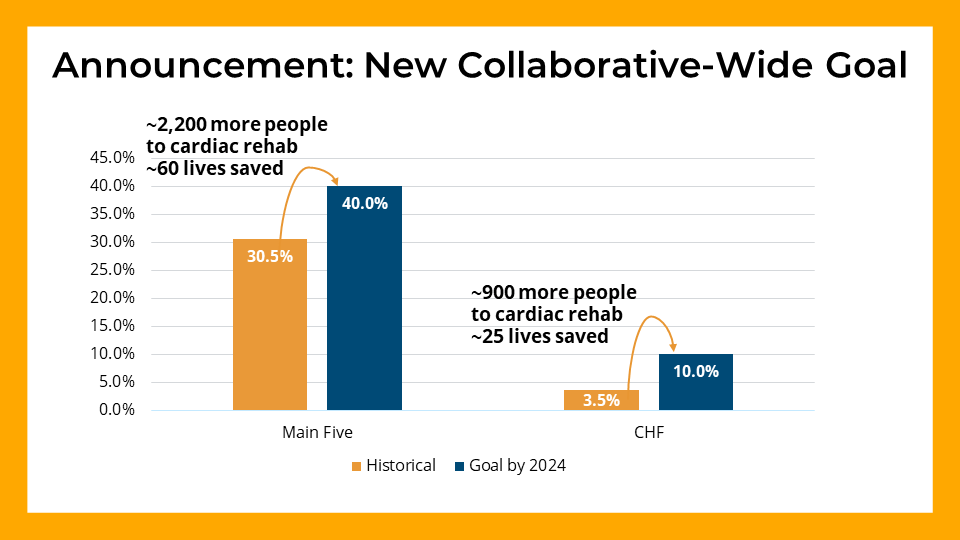
Showcasing opportunities where MVC data can drive change was a focal point for the meeting. Utilizing unblinded data from the collaborative, MVC Analyst Jessica Yaser led attendees through a data session focused on MVC’s two Value Coalition Campaigns (VCCs): Preoperative Testing and Cardiac Rehab. This allowed attendees to see their preoperative testing and cardiac rehab utilization rates compared to their peers. Hospitals performing well were invited to offer insights as to how this was achieved and what mechanisms other hospitals could adopt to improve performance levels. Jessica also announced new collaborative-wide goals around cardiac rehab utilization rates (see Figure 1), which will continue to be promoted and highlighted in the months ahead.

Figure 1.

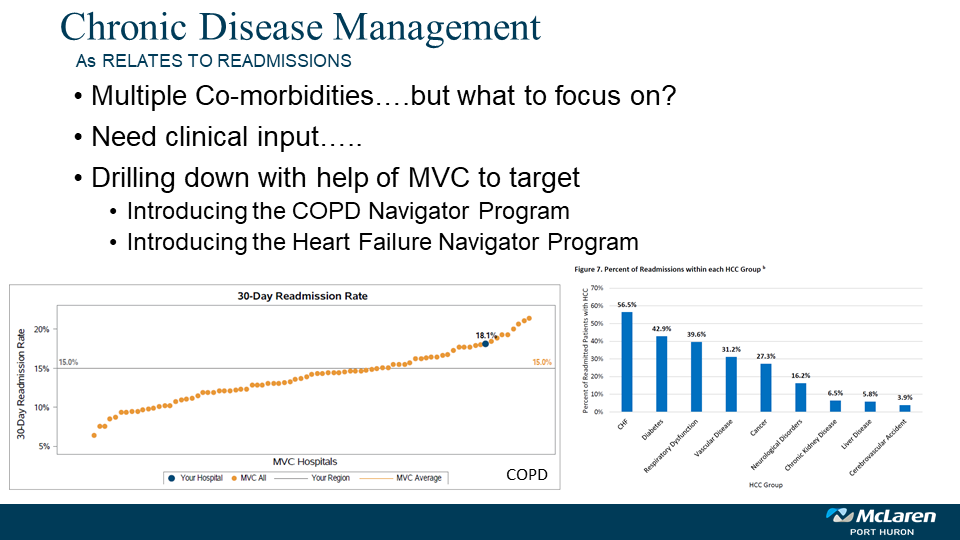
With the scene set, MVC welcomed guest speakers Mary Pool and Holly Gould from McLaren Port Huron hospital. Mary and Holly provided attendees with an overview of how they have used MVC data to help tackle high readmission rates for the congestive heart failure (CHF) and chronic obstructive pulmonary disease (COPD) patient populations at McLaren Port Huron. Specifically, data provided by the Coordinating Center helped confirm the suspicion that although follow-up rates were high across the institution, this wasn’t being translated into a reduction in readmissions. Stratifying these data further helped McLaren Port Huron introduce tailored initiatives in the form of their COPD and Heart Failure Navigator Programs, aimed at driving the effectiveness of follow-up visits (see Figure 2).

Figure 2.

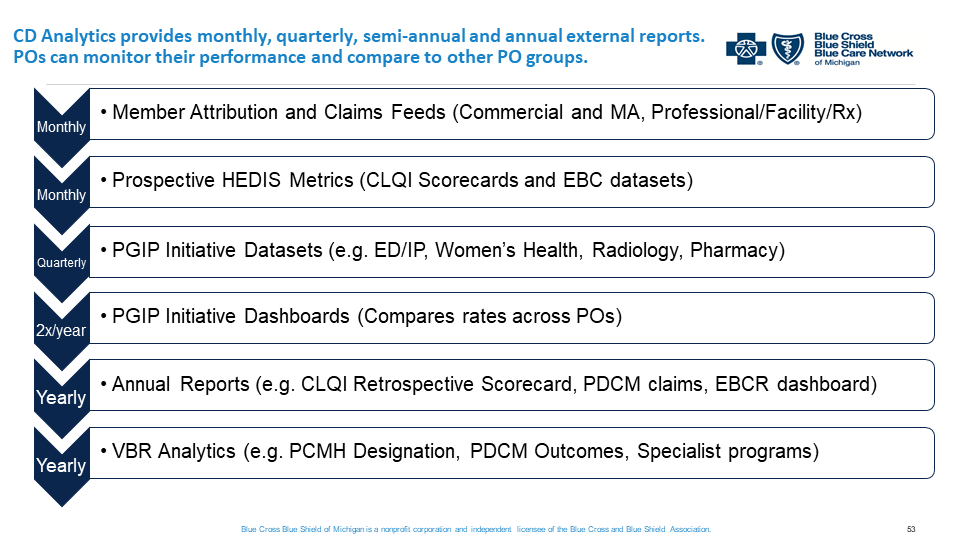
After hearing from McLaren Port Huron, Michelle Marchese from BCBSM provided an overview of how their Physician Group Incentive Program (PGIP) platform supports value-based care. As part of this, Michelle provided a walk-through of the current state of BCBSM data and report sharing, outlining how these all fit together to provide valuable healthcare insights for physician organizations (POs) (see Figure 3). MVC’s ongoing partnership with BCBSM to identify PO-level opportunities for improvement was also highlighted – a collaboration that will continue moving forward to enhance the level of support available to POs across the state. Michelle then passed the baton to Dr. Shannon Martin from MyMichigan Health who shared how MyMichigan has used its internal data to develop, implement, and assess its “Health Aging Program.” This initiative is aimed at decreasing the use of high-risk medications in the elderly population, saving many seniors from the harm of adverse drug effects.

Figure 3.

The meeting concluded with a summary of the day and key upcoming activities, led by MVC Engagement Associate Chelsea Andrews. The recording from Friday’s meeting is available here. If you have questions about any of the topics discussed at the semi-annual or are interested in finding out more about MVC, please reach out to the Coordinating Center. MVC’s next semi-annual meeting will be in person on Friday, October 28 at the Radisson in Lansing – we look forward to seeing you all then!

4
View Post
MVC, BMC2 Launch Michigan Cardiac Rehab Network & Toolkit

MVC, BMC2 Launch Michigan Cardiac Rehab Network & Toolkit

This year in the United States, cardiovascular disease will be responsible for one in every four deaths. Despite its prevalence, few cardiac patients eligible for cardiac rehabilitation utilize this life-changing program. In response, the Michigan Value Collaborative (MVC) and the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2) recently established the new Michigan Cardiac Rehab Network (MiCR) to collaborate on efforts that heighten awareness of these programs and support meaningful improvement in Michigan.

Cardiac rehabilitation (CR) is a comprehensive program encompassing supervised exercise, nutrition education, smoking cessation, mental health resources, skills training for heart-healthy lifestyles, and peer support from others who are experiencing a similar life event. It has a Class IA indication for recent cardiac-related events or procedures, meaning there is high-quality evidence that it is beneficial to patients. In fact, individuals who complete the full program of 36 sessions have a 47% lower risk of death and a 31% lower risk of heart attack than those who attend only one session. The evidence is clear that CR extends life and improves quality of life for patients with a recent cardiac-related event or procedure. Unfortunately, only one in three eligible Michiganders participates—a rate well below the Million Hearts nationwide goal of 70% participation.

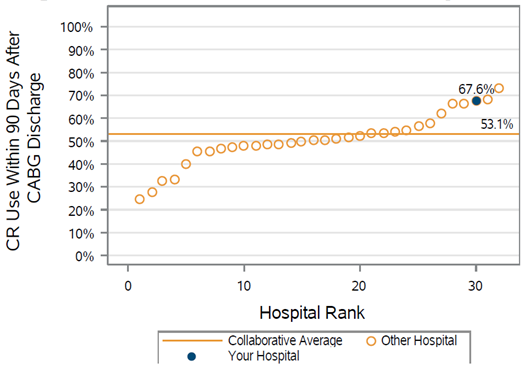
Using claims data, MVC can assess both initiation and adherence – whether and when someone starts CR, and how long they keep going. There is wide variability in CR rates between MVC’s member hospitals (see Figure 1 for a sample plot from a recent blinded report). The site with the highest rate of cardiac rehab after coronary artery bypass graft surgery (CABG), for example, succeeds at sending 75% of their CABG patients to CR, while another only sends 28% of their CABG patients. This variation shows that it is possible to reach high CR rates, and hospitals can learn from each other to make improvements that save lives and reduce costs.

Figure 1. Collaborative-Wide CR Use Following CABG Discharge

MiCR was developed for this reason and will work to equitably increase CR participation for all eligible individuals in Michigan. Serving as Co-Directors of MiCR are Mike Thompson, Co-Director of MVC, and Dr. Devraj Sukul, Associate Director of BMC2 PCI. MiCR will distribute regular CR utilization summaries to relevant providers, convene regular meetings with its stakeholder and advisory groups, create resources that help hospitals and CR facilities optimize CR utilization, and continue to leverage the expertise of both CQIs.

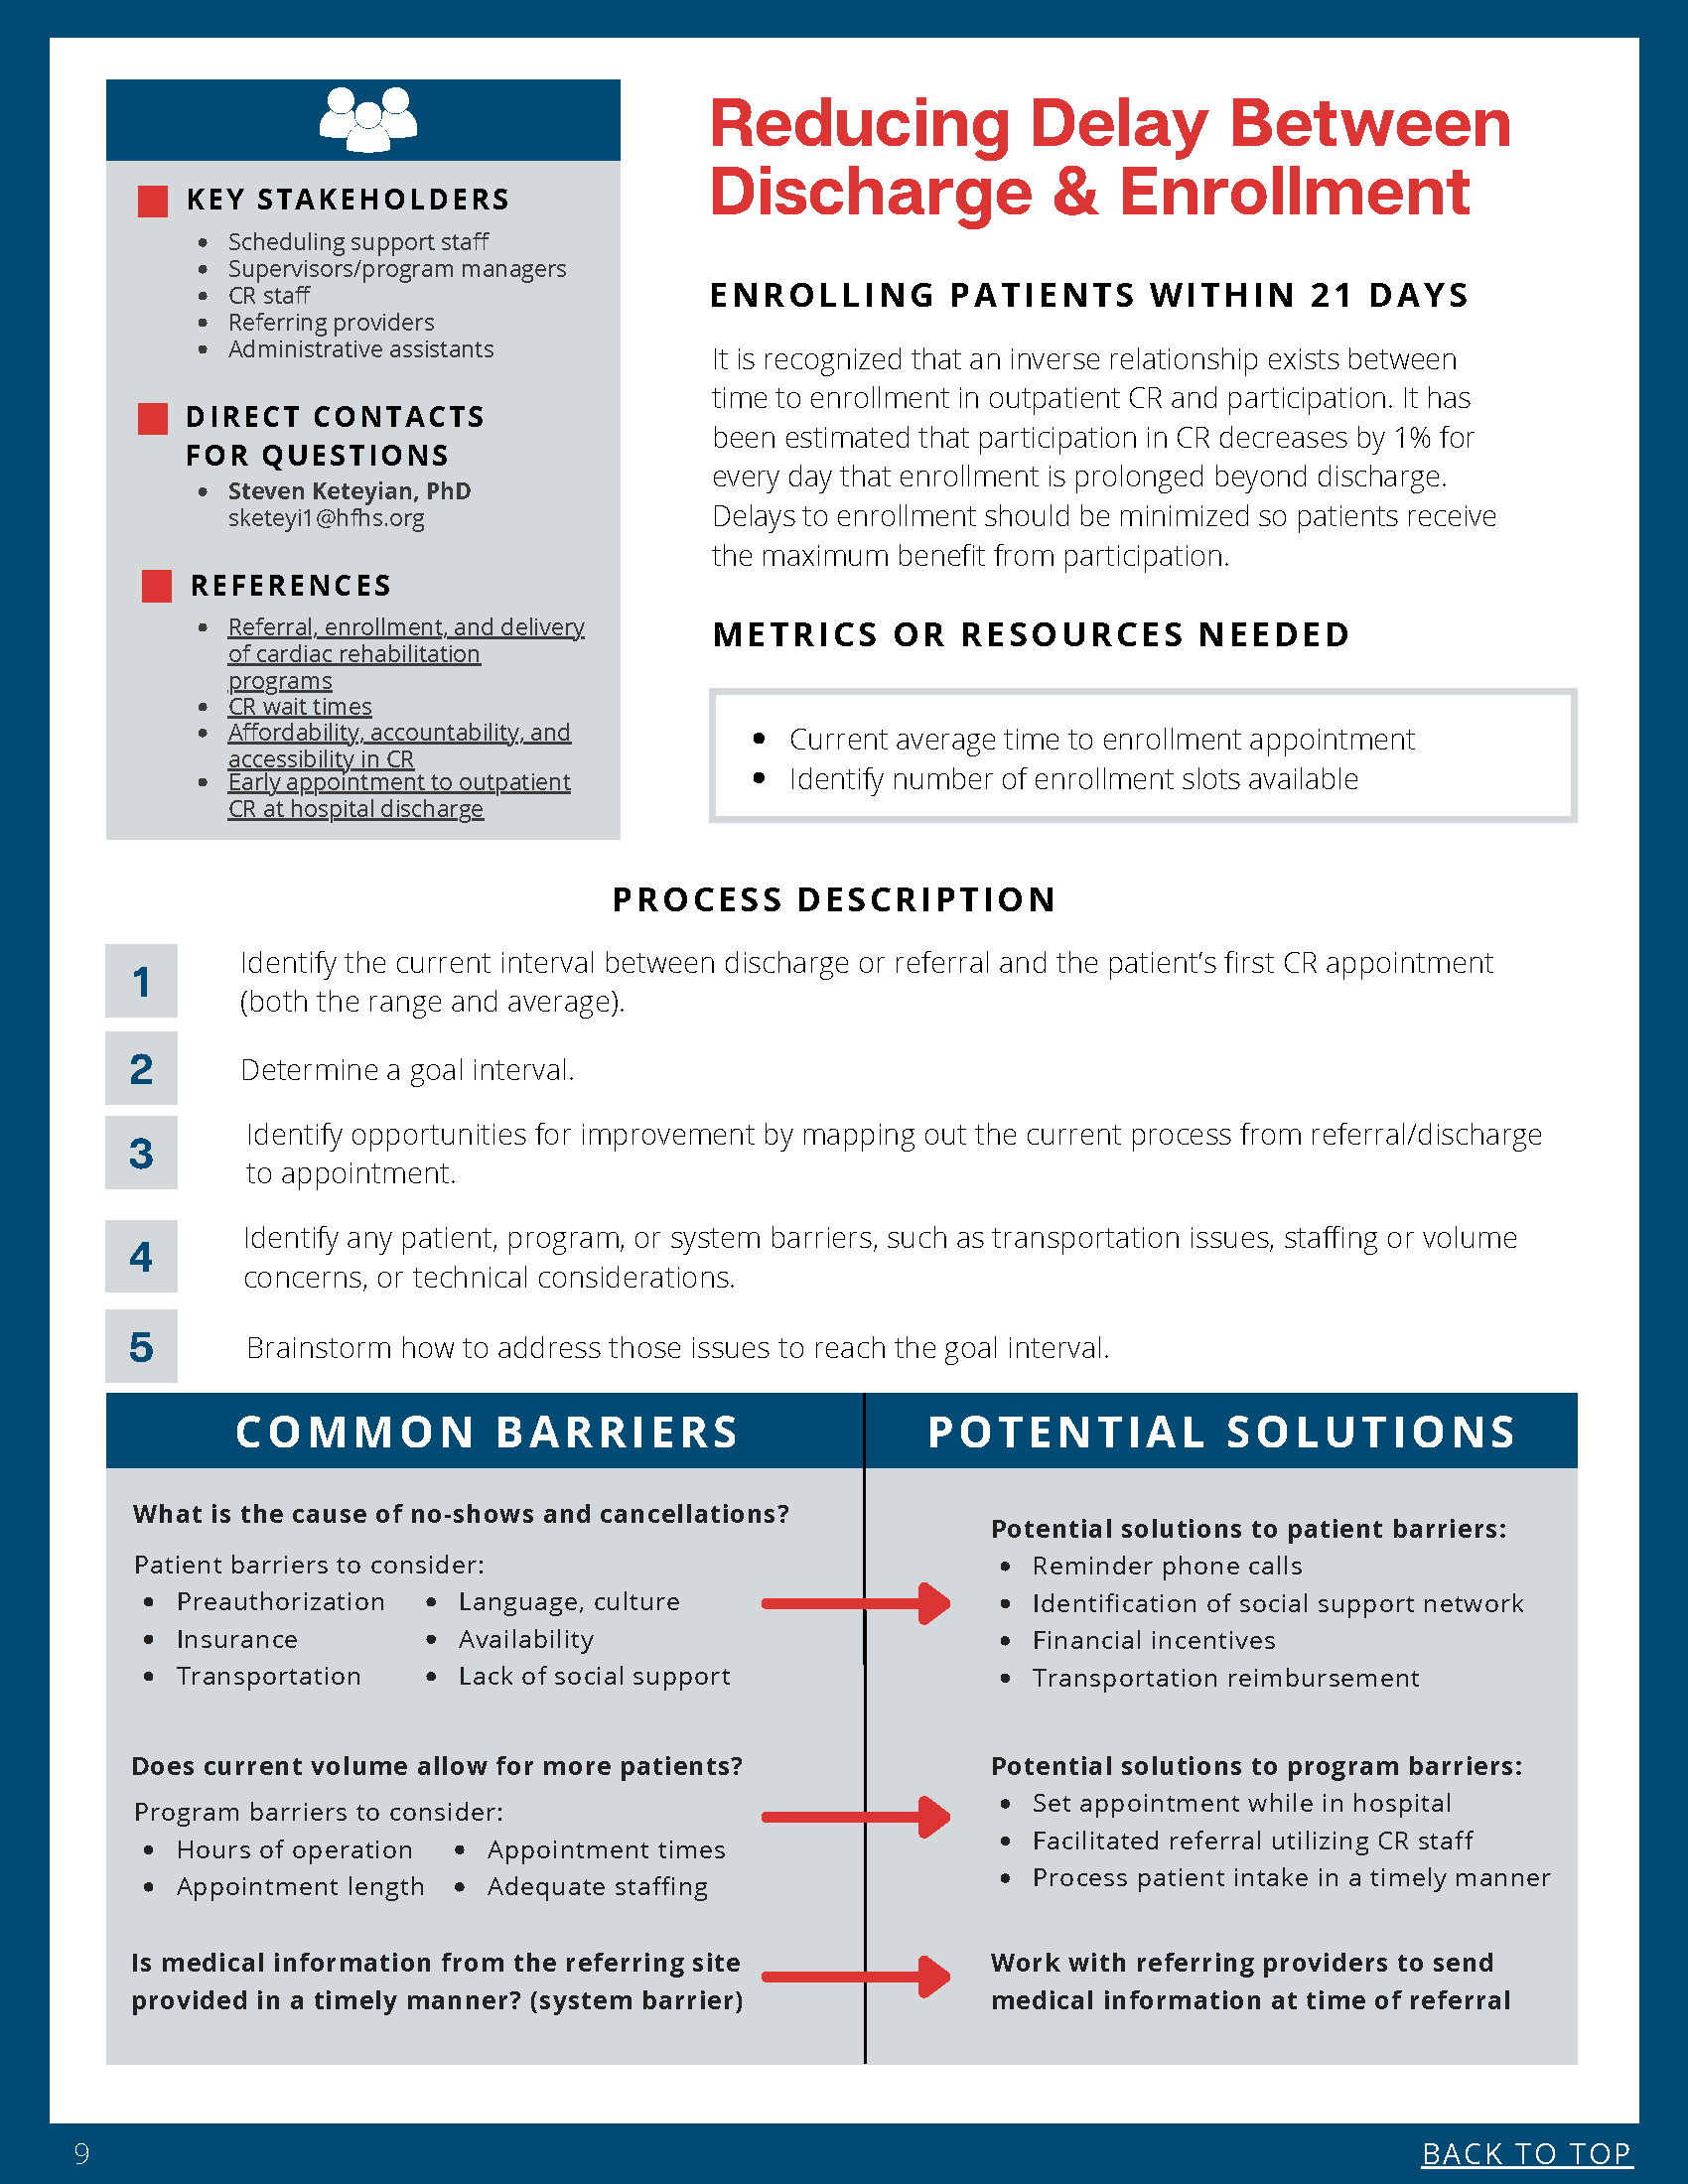
In one of its first coordinated efforts, MiCR worked with CR providers and content experts to create a Cardiac Rehab Best Practices Toolkit, which was launched in April. It outlines initiation, maintenance, and innovation strategies for increasing the utilization of CR (see Figure 2 for a sample page). MVC encourages members to turn to this tool as they work to encourage the enrollment of more patients.

Figure 2. Sample Page from MiCR Best Practices Toolkit

The partner CQIs behind MiCR also released new statewide goals for improved CR utilization. Currently, 30% of patients utilize CR following transcatheter aortic valve replacement (TAVR), surgical aortic valve replacement (SAVR), coronary artery bypass graft surgery (CABG), percutaneous coronary intervention (PCI), and acute myocardial infarction (AMI). The first goal is to reach 40% CR utilization for TAVR, SAVR, CABG, PCI, and AMI patients. In addition, only about 3% of congestive heart failure (CHF) patients currently utilize CR. The second statewide goal is a collaborative-wide utilization rate of 10% for CHF patients. Progress on these goals will be shared by MVC in its CR reports sent every six months.

The two CQIs will also continue with their respective activities in the CR space. MVC supports CR participation in two primary ways. One is providing opportunities for MVC members to collaborate, and the second is the preparation of reports using its unique multi-payer data sources. The MVC team supports collaboration through stakeholder meetings and workgroups, which allow sites and clinicians to share solutions for common challenges. The reports MVC prepares analyze member claims data with time-specific hospital-level information on CR enrollment and completed visits within one year of discharge. This allows hospitals to benchmark their performance against peers and identify areas for improvement. MVC will also share unblinded data on CR rates with members at its May semi-annual meeting in one week, which is meant to drive conversation and encourage best practice sharing across the collaborative. The MVC team hopes that its outreach and resources help members to save lives by providing strong endorsements for CR and addressing barriers that may limit patient participation.

For more information on MVC’s CR efforts, visit MVC’s Value Coalition Campaign webpage. For more information about CR, view this MVC video or visit the Million Hearts website. If you have questions about any of the above activities or resources, reach out to the Coordinating Center at michiganvaluecollaborative@gmail.com.

3
View Post
MVC Releases Agenda, Speakers for May Semi-Annual Meeting

MVC Releases Agenda, Speakers for May Semi-Annual Meeting

The MVC Coordinating Center recently released the full agenda for its forthcoming spring Semi-Annual Meeting on Friday, May 13, 2022, from 10-11:30 a.m. The MVC Coordinating Center holds collaborative-wide meetings twice each year to bring together quality leaders and clinicians from across the state. This meeting’s theme of “turning data and collaboration into action” reflects how members often balance multiple internal and external data sets in addition to a broad portfolio of resources from MVC and other CQIs.

Speakers at semi-annual events are often members who share their successes, challenges, barriers, and solutions in pursuing a higher value and quality of care. The speakers outlined on May’s meeting agenda will share examples of quality initiatives that successfully leveraged data or collaboration to bring about improvements in healthcare. The speakers also represent a variety of stakeholder groups, including hospitals, physician organizations (POs), payers, and of course MVC Coordinating Center leadership.

The first guest presentation will be from hospital leaders at McLaren Port Huron’s Quality Improvement and Organizational Excellence team. Regional Director Mary Pool and Manager Holly Gould will discuss partnering for clinical efficiency and effectiveness. This presentation will be followed by Michelle Marchese, Director of Care Delivery Analytics at Blue Cross Blue Shield of Michigan (BCBSM), who will present about how BCBSM’s Physician Group Incentive Program (PGIP) supports value-based care. The final guest presentation of the day will feature PO members and comes from leaders at the MyMichigan Collaborative Care Organization. Dr. Shannon Martin, Primary Care Council of MyMichigan Medical Group, will present on affecting medication overload in seniors.

Attendees can also expect to hear from MVC Coordinating Center leadership and staff about the MVC Component of the BCBSM Pay-for-Performance (P4P) Program, as well as insights on how performance in the areas of preoperative testing and cardiac rehabilitation utilization compares across the collaborative.

At the conclusion of the meeting, attendees will be able to identify the value of a variety of data sources and collaboration opportunities to assist with implementing and evaluating quality improvement projects. The full agenda can be accessed online here.

These presentations would be informative and applicable for any of the following stakeholders who are welcome to attend:

  • MVC Hospital Site Coordinators
  • MVC Physician Organization Site Coordinators
  • Quality Leadership
  • Clinicians
  • Healthcare abstractors, analysts, and statisticians
  • CQI staff

Those interested in attending this informative and collaborative meeting should register here. The MVC Coordinating Center looks forward to a fantastic meeting. See you there!

3
View Post
Unique Food Assistance Program Bridges Medical and Food Sectors

Unique Food Assistance Program Bridges Medical and Food Sectors

MVC hosted another successful session of its new health equity workgroup last week with a guest presentation by Ariane Donnelly, MPH, RD, Health Promotion Coordinator at the Washtenaw County Health Department. The new health equity workgroup was established in response to a greater strategic focus on health equity within the MVC Coordinating Center as well as widespread interest in this topic within the healthcare field.

The March 16 workgroup focused on the Prescription for Health program, which takes a unique approach to chronic disease management by connecting the medical system with the food sector. It operates by having participating healthcare providers assign “prescriptions” to their patients to eat more fruits and vegetables. These prescriptions can then be “filled” at local participating farmers markets, where patients receive $100 in tokens to spend on fresh fruits and vegetables as well as nutrition education and support. Participants also work with Community Health Workers to set health goals. The program leverages the fact that Michigan is the second most agriculturally diverse state in the country, and its abundant farmers markets can be an asset in supporting healthy lifestyles for patients.

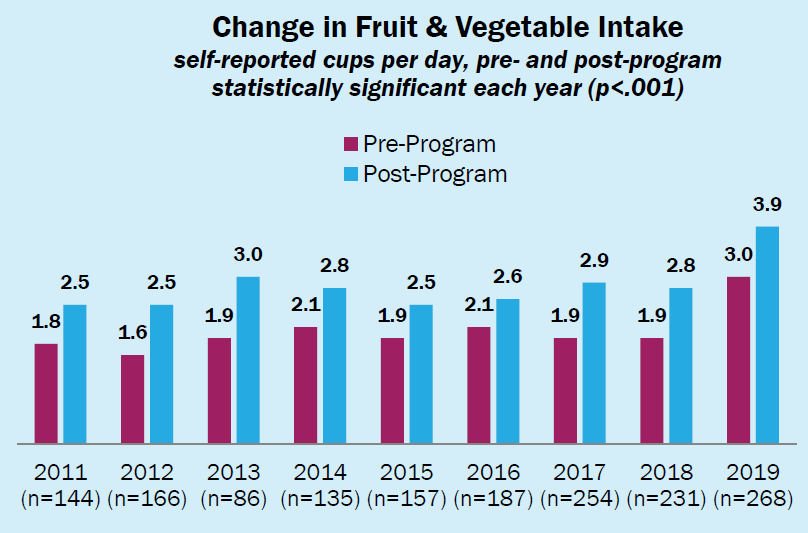
Evaluation of the program’s effectiveness has been fruitful. For every year of the program, the health department found a statistically significant increase in self-reported fruit and vegetable intake, often by one cup or serving per day (see Figure 1).

Figure 1.

The program was first created in 2008 in response to high levels of food insecurity within communities in Washtenaw County combined with generally low consumption of fruits and vegetables, both of which are associated with an increased risk of chronic disease. Ms. Donnelly pointed out that while many clinics provide nutrition advice, patients face multiple barriers to equitably accessing healthy foods and need additional support. Since its first pilot, the program has continued to grow in total enrollees and economic impact, and it maintained its participation levels throughout the pandemic with a modified version of the program.

Similar programs are in operation in other parts of the state and country as well, such as Food Rx in Chicago and Fresh Prescription in Detroit. Washtenaw County’s Prescription for Health program launched an implementation toolkit in 2016 to help others with starting a similar program in their area.

To learn more about the Prescription for Health program’s operations, impact, and lessons learned, watch the full recording of the workgroup here: https://bit.ly/3IyIsnS. You can also visit the program website for more information: www.washtenaw.org/prescriptionforhealth.

MVC will continue to invite guest speakers with valuable insights on a more equitable health system. The next MVC health equity workgroup will take place on Tuesday, May 10, from 1-2 p.m. If you would like to suggest a topic or speaker for a future workgroup, please contact the MVC Coordinating Center at michiganvaluecollaborative@gmail.com.
Prescription for Health is funded by Saint Joseph Mercy Health System with additional financial support from multiple partners.

2
View Post
MVC Component of the BCBSM P4P Program: PY21 in Review

MVC Component of the BCBSM P4P Program: PY21 in Review

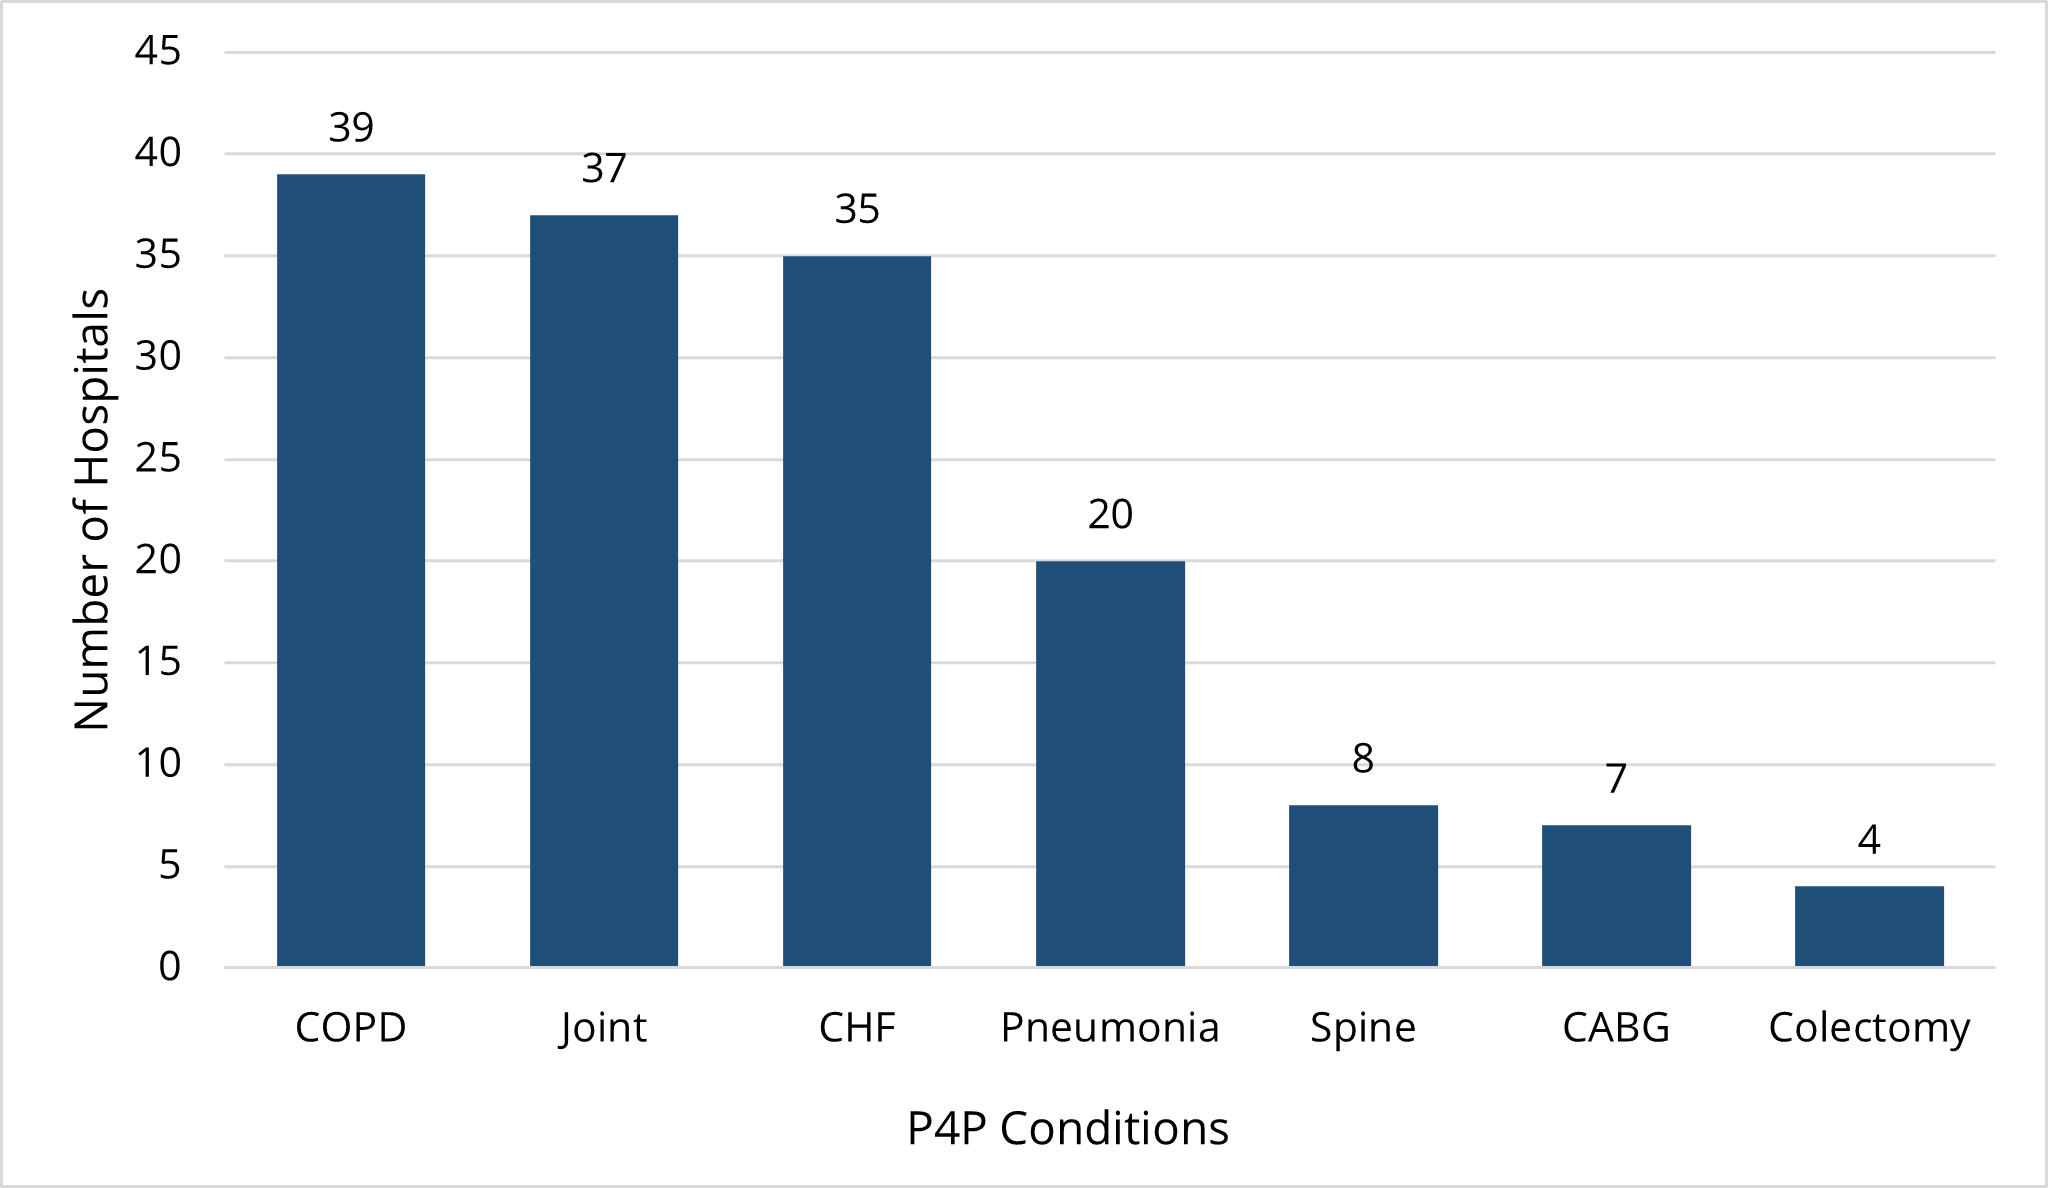
Last month the Michigan Value Collaborative (MVC) Coordinating Center distributed the final scorecards for the 2021 program year of the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. The 2021 program year was the second year of a two-year cycle for which hospitals were evaluated using MVC data. Hospitals were scored on two conditions that they selected from seven options: chronic obstructive pulmonary disease (COPD), colectomy, congestive heart failure (CHF), coronary artery bypass graft (CABG), joint replacement, pneumonia, and spine surgery. Figure one shows the frequency of hospital condition selections for the two-year program cycle.

Figure 1. Distribution of Hospital Condition Selections for PY21

The MVC Component of the BCBSM P4P Program evaluates each participating hospital’s risk-adjusted, price-standardized, average 30-day episode payments for their two selected conditions through two methods. One way that hospitals earn points is by reducing their payments from the baseline period (which included index admissions in 2018) to the performance period (which included index admissions in 2020). These are termed “improvement points.” Alternatively, hospitals can earn points by being less expensive than the other hospitals in their cohort. These are referred to as “achievement points.” The MVC cohorts are groups of hospitals determined to be peers using bed size, case mix index, and teaching status.

While participants are scored on both improvement and achievement, members receive the higher of the two scores for each condition. Hospitals are also eligible to earn a bonus point for each condition provided all hospitals in their respective cohort who selected the same condition reduced spending by five percent. For the 2021 program year, the Coordinating Center added two additional bonus points that could have been earned by attending both semiannual meetings (one point) and by completing a site visit with MVC in 2021 (one point). A maximum of 10 points were awarded for participating members. Figure 2 shows the distribution of total points earned by hospitals for the 2021 program year.

Figure 2. Distribution of Total P4P Scores for PY21

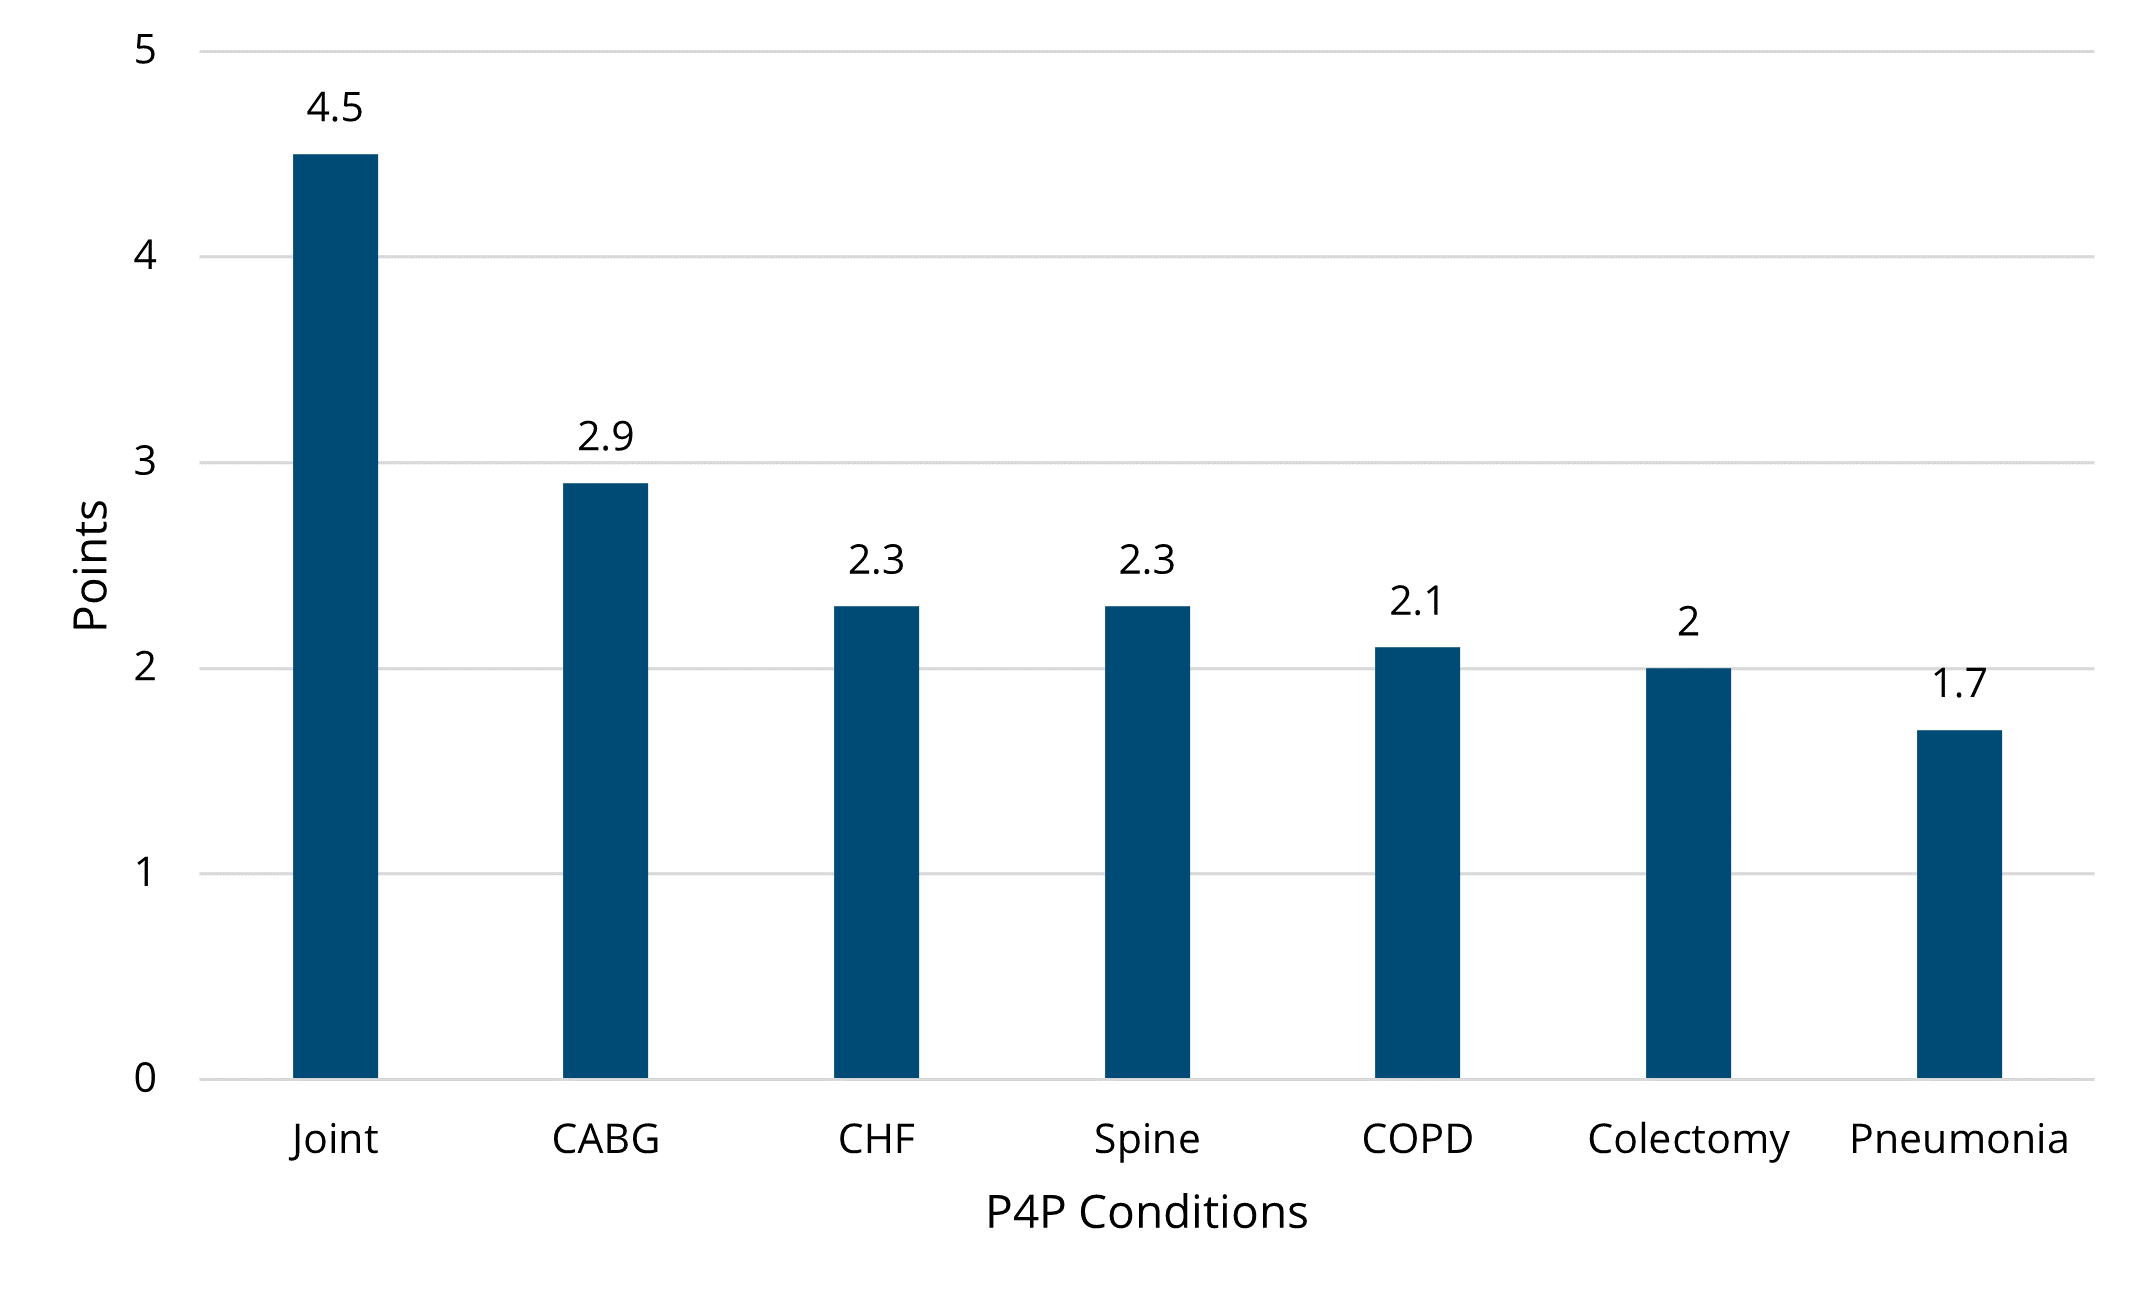
On average, hospitals earned 6.8 points total, an increase of 1.3 points from the 2020 program year average of 5.5 points. A majority (88%) of hospitals earned at least one of the two possible participation bonus points. In addition, 31 cohort bonus points were distributed within COPD, CHF, and joint replacement. Consistent with previous years, the condition with the highest average point total was joint replacement at 4.5 points with CABG coming in second at 2.9 points (Figure 3).

Figure 3. Average Points by Service Line

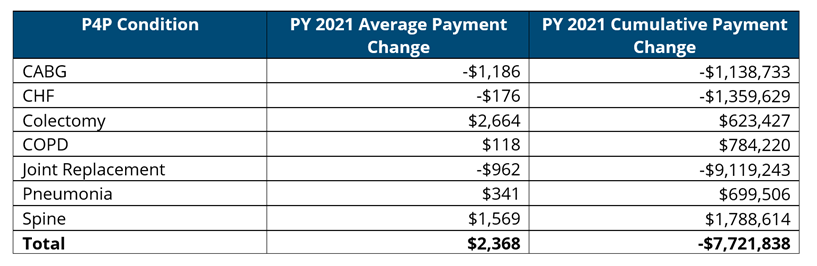
When looking at the episode payments behind the point totals, MVC found that hospitals that selected CABG, CHF, and joint replacement saw a decrease in payments from 2018 to 2020 (see Figure 4). Taking into account case counts for all conditions in the baseline year, MVC also found that payments decreased overall for the selected P4P conditions by $7.7 million dollars in program year 2021.

Figure 4. Payment Change by P4P Condition

If you have any questions regarding the MVC Component of the BCBSM P4P Program, please reference the P4P Technical Document for Program Years 2020 and 2021 and the MVC P4P FAQ PY 2020-2021. If you would like to set up a meeting to review your hospital’s performance, please contact the Coordinating Center at michiganvaluecollaborative@gmail.com. The Coordinating Center will be evaluating and releasing a report on the 2020 and 2021 program year cycle later in 2022.