Off
View Post
MVC Celebrates Q4 Updates and Successes to Close Out 2023

MVC Celebrates Q4 Updates and Successes to Close Out 2023

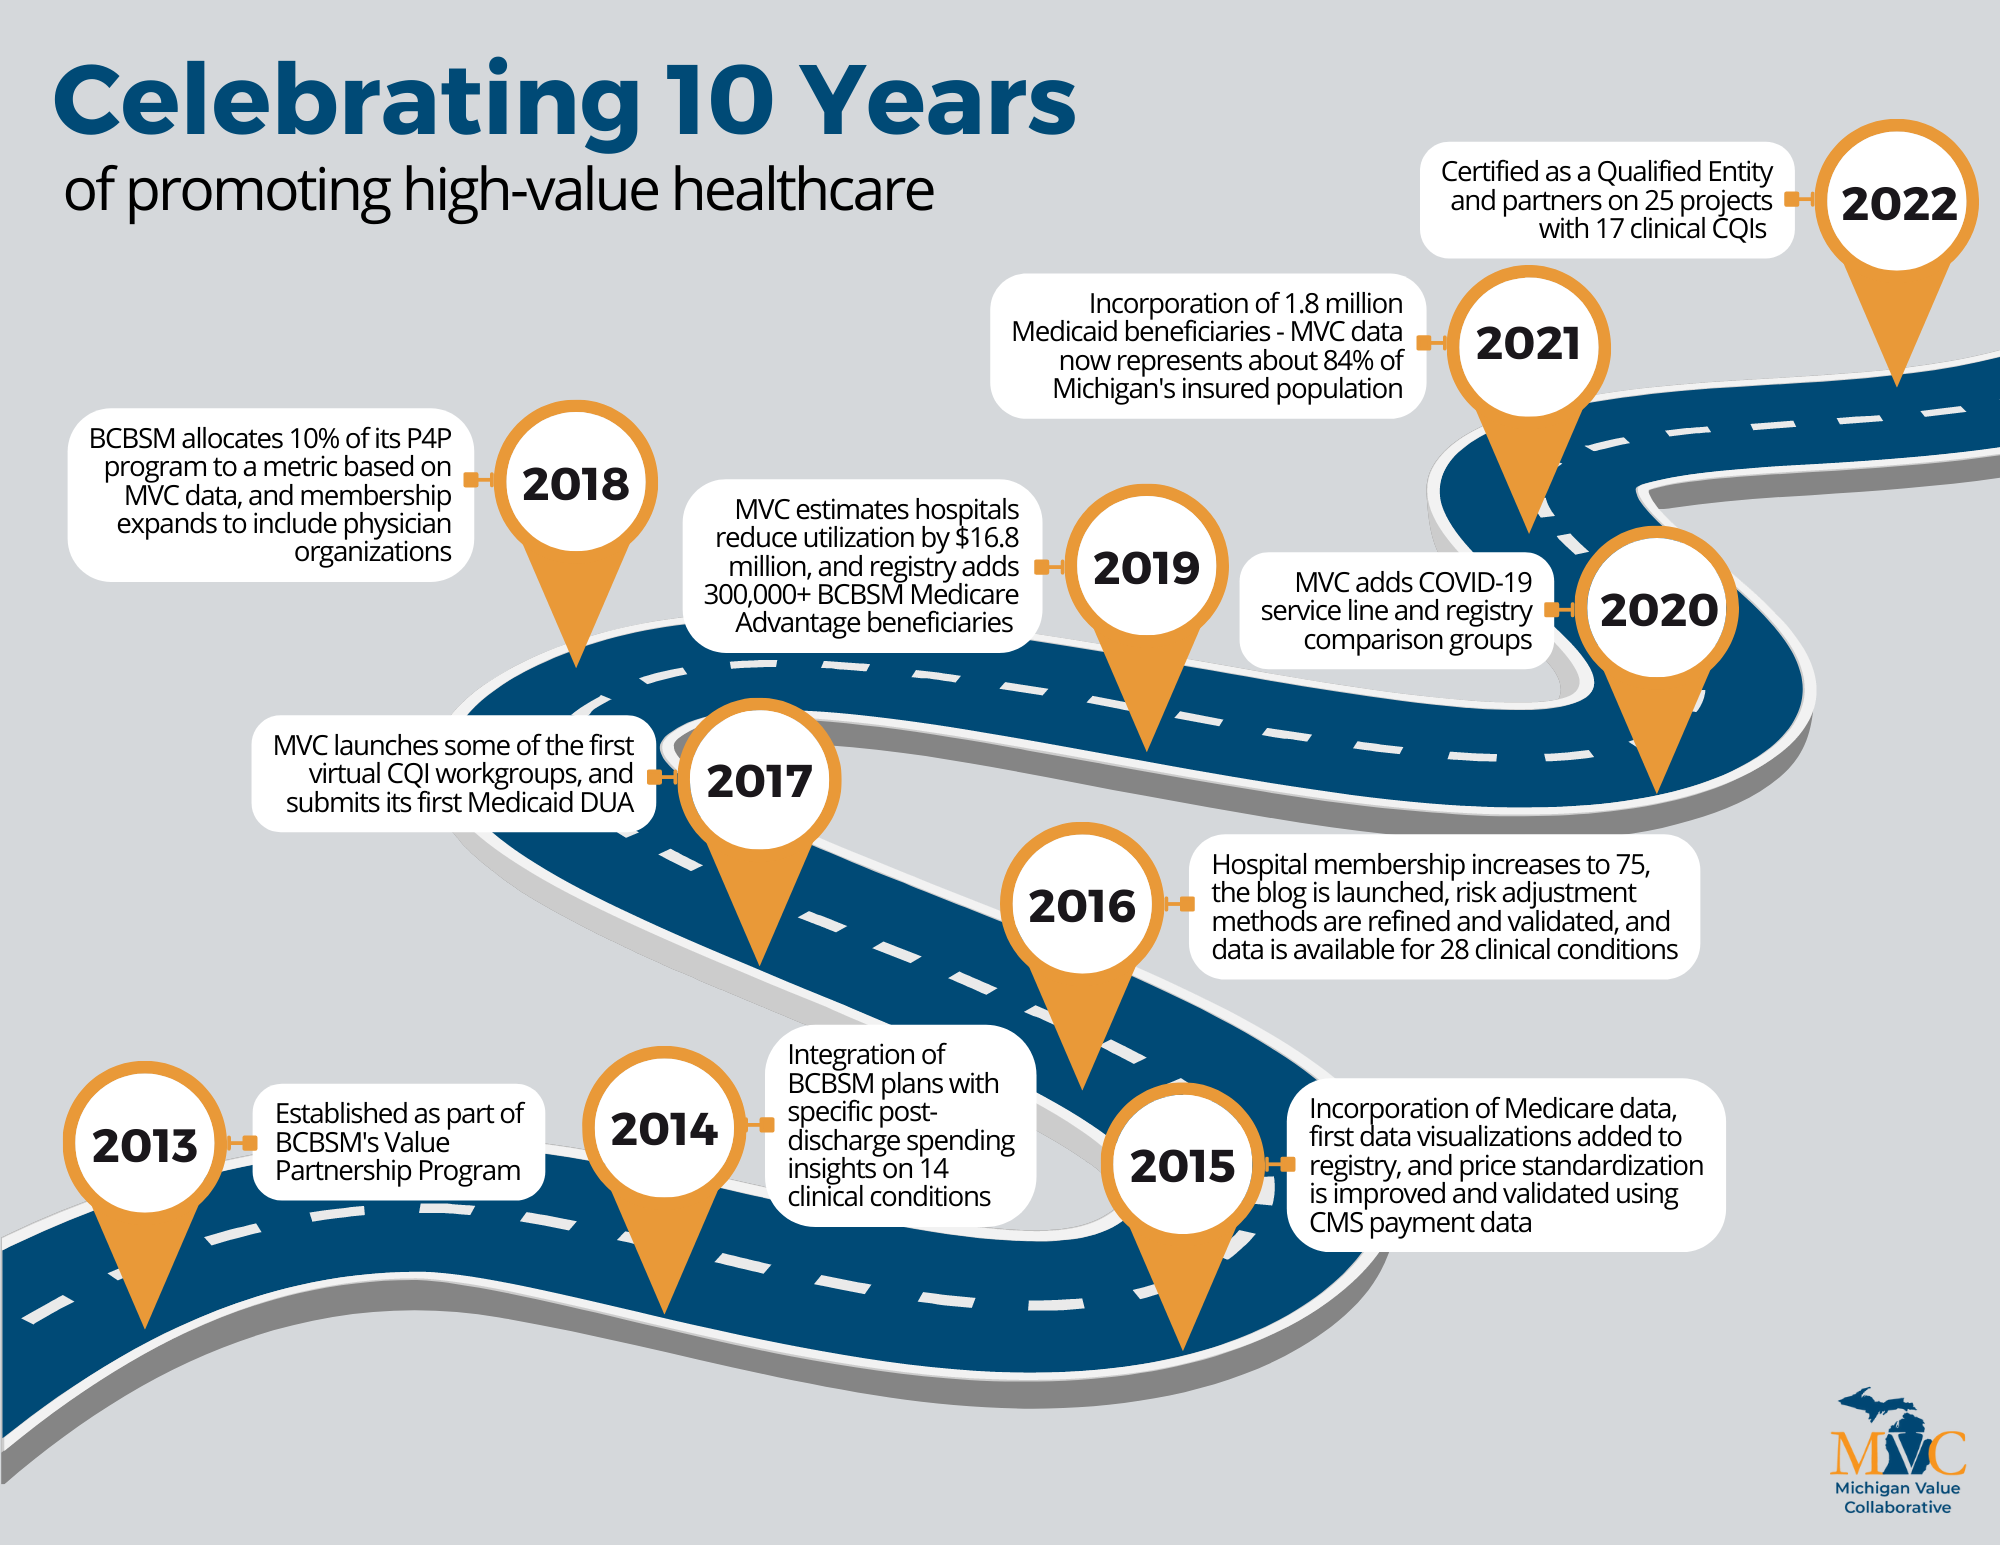
The Michigan Value Collaborative distributes a quarterly newsletter to highlight recent MVC events, reporting, partnerships, and member activity. The final newsletter of 2023 was emailed to subscribers this week and summarizes activities and accomplishments from Q4. First and foremost, the Coordinating Center is grateful to its members for their partnership throughout 2023 - MVC's 10th year in operation as a value-based Collaborative Quality Initiative. This was a special year for the MVC team as we celebrated key successes from the last decade (Figure 1). MVC also celebrated a new addition to the Coordinating Center team in Q4, with MVC Engagement Manager Jessica Souva joining in October (Figure 2).

Figure 1.

Figure 2.

The Q4 newsletter included summary highlights from MVC's fall collaborative-wide meeting, which was held Oct. 20 in Lansing with the theme of "high-value care for all." This newsletter edition also highlighted important updates to MVC's strategy, which were informed by member insights and strategic planning activities over the past year. The resulting revised strategic framework will shape MVC's priorities and activities in 2024 and beyond.

Another key focus of the Q4 newsletter was the release of MVC's Program Year 2024 Engagement Point Menu, available here. Hospitals may earn up to two MVC P4P engagement points toward their PY24 scorecard by mixing and matching the included offerings. MVC hosted an Engagement Point Menu Webinar to introduce this menu and answer questions in November 2023. The webinar recording can be accessed here. In addition, MVC developed a Frequently Asked Questions guide available here.

The Q4 newsletter highlighted a large portfolio of reports and activities completed by MVC staff from October through December. MVC prepared several refreshed hospital-level push reports that were then shared with hospital and physician organization members via their unique Dropbox folders, including refreshed versions of MVC's preoperating testing, sepsis, common condition, and chronic disease management reports. Additionally, MVC and MUSIC worked together on a pair of value-based improvement exercises to assess the impact of MUSIC initiatives on opioid prescription use. One of these exercises focused on the impact of MUSIC's ROCKs initiative on opioid spending following kidney stone surgery, and a second focused on the impact of MUSIC's Michigan Pain-control Optimization Pathway (MPOP) initiative on opioid spending following prostate surgery. MVC also partnered with BMC2, HBOM, and Trinity Health Ann Arbor to co-host the Michigan Cardiac Rehab Network Fall 2023 Stakeholder Meeting in November, during which the new MiCR website and other cardiac rehab resources were announced. 

In January, BCBSM will be conducting its 2024 CQI Coordinating Center Survey, which provides an opportunity for members to evaluate the MVC Coordinating Center staff. We value your feedback and thank you in advance for your participation. The MVC Coordinating Center looks forward to continuing its work in 2024 and wishes everyone a happy holiday season and new year!

Off
View Post
MVC Looks to the Future in Launch of Refreshed Strategy

MVC Looks to the Future in Launch of Refreshed Strategy

You may have noticed MVC celebrating something special this year. If you haven’t guessed from our celebratory blogs, collaborative-wide meeting spotlights, and rather subtle email signatures, MVC is now 10 years old. It’s something as a Coordinating Center that we are incredibly proud of, and we thank each of you for your partnership in helping to grow the collaborative over the years.

MVC’s evolution as a collaborative has been informed by continued member insights and driven by dedicated strategic planning and considered implementation. As we look ahead to the next 10 years of operation and ensure MVC’s support offering continues to align with the future of value-driven healthcare, this practice of leveraging member feedback to shape development will continue to take center stage.

Over the last six months, we engaged with our members and other stakeholders to gather input on what is working well and needs to be protected, as well as taking time to identify where there are opportunities to introduce new service offerings. If we haven’t engaged with you directly and you have ideas, we’d love to hear them. The insights we received to date helped inform our collective vision as to what value-driven healthcare truly looks like and ultimately where MVC fits into this puzzle. I’m excited to share some of this thinking and highlight a number of new related developments we will tackle in the coming years.

As we see it, the pursuit of value in healthcare requires recognizing and embracing three key imperatives. First, although fee-for-service reimbursement will persist for the foreseeable future, population health management will continue to be the chief lever used by policymakers, payers, and providers to manage risk and cost. As payment arrangements further embrace two-sided risk, healthcare providers will need to refine internal processes to strengthen their understanding of their patient population, appreciate its heterogeneity, and respond nimbly to anticipate and optimize resource utilization. Understanding the entirety of the patient’s care pathway across providers and facilities is critical to identifying opportunities to optimize health, coordinate care, and mitigate utilization for acute illness, especially for patients with chronic conditions.

Inpatient care will continue to be a major driver of expenditures, and benchmarking of hospital-based services will continue to be a valuable tool to improve quality and control costs. However, there is an opportunity to conceptualize care delivery more broadly. Developing a more holistic approach to understanding utilization will not only allow for a more complete assessment of where expenditures occur but will also help better identify opportunities for savings. Sites of care exist along a continuum that includes large referral hospitals on one end but stretches as far as the patient’s home on the other. There are multiple options on this continuum—including community hospitals, physician offices, community health centers, ambulatory surgery centers (ASCs), hospital outpatient departments (HOPDs), pharmacies, skilled nursing facilities (SNFs), hospital-at-home, telehealth, and even wearable technology. All must be considered as options to rationalize sites and providers of care and right-size resources to the needs of the patient.

Finally, morbidity and mortality will continue to be important quality metrics, but our definition of quality needs to expand to include patient-centeredness and equity. We need to avoid adverse outcomes and promote positive behaviors, attitudes, and interactions with the healthcare system. Inadequate attention to the social and physical context in which patients live and work will diminish the effectiveness of health interventions and lead to waste. More importantly, understanding and accounting for social influencers of health is a critical element in the shift from treating illness to promoting health.

These three elements will be used to help shape our activity moving forward, both in terms of strengthening existing analytic and engagement platforms and delivering new innovative offerings to help drive member quality improvement efforts. Here’s a sneak peek of some of MVC’s future development areas:

Incorporating Pharmacy Claims

To better understand utilization, pinpoint where expenditures occur, and identify where savings can be made, we will look to consider all sites and providers of care that exist along the continuum. This includes pharmacies and related prescription drug spending. MVC now possesses pharmacy-level data for all sources, and efforts will be directed toward successfully integrating these claims across our existing infrastructure and future planned activity.

Integrating Michigan Medicaid and ED Episode Data

To help strengthen member understanding of their respective patient populations, MVC will leverage the recent receipt of Medicaid data to develop new value-add data offerings in the areas of health equity, women’s health, and pediatric care. Similarly, the creation of new episodes initiated by emergency department (ED) visits will be built upon to provide actionable information on care transitions and the trajectory of care for patients visiting the ED.

Broadening Beyond Inpatient Episodes

The various avenues a patient may take as part of their care pathway highlight the challenges of delivering and understanding coordinated care delivery. An episode-based approach helps to navigate these problems but only takes us so far, with some patients (e.g., those with ambulatory care-based events) still being overlooked. To reflect the importance of population health management, sites and providers of care, patient-centeredness, and equity in all MVC work, efforts will be directed to creatively broaden our data offering beyond inpatient episodes.

Incorporating Ambulatory Surgical Centers

To achieve our aim of considering all sites that exist along the care pathway, our efforts will first be directed towards incorporating ASCs into the collaborative. Many questions regarding the cost and quality of care provided at ASCs remain unanswered. This effort will aim to leverage MVC’s existing infrastructure and explore the introduction of innovative activities to answer such questions and encourage ASC participation.

Reflecting System Level Activity

In recent years, there has been a notable rise in hospital consolidation across Michigan. These developments have placed increased emphasis on the need for MVC to explore, develop, and implement new approaches aimed at supporting quality improvement efforts at the system level. This will look to build on our existing system reporting and engagement activity to better understand how these entities approach care delivery, what the related patient pathway looks like, and how this impacts other pieces of operation, including related incentive programs.

Emphasizing Equity in Healthcare

MVC has successfully integrated health equity and social risk measures into its existing reporting infrastructure. Moving forward, the Coordinating Center will look to discuss these different offerings and their perceived value with members to better understand their priorities and gaps in knowledge. From our discussions with members to date, it has been evident that many are still in an information-gathering phase and desire consensus around best practices. MVC will seek to identify differing approaches to health equity across the collaborative. Through enriching its understanding of member initiatives in the health equity space, MVC can identify common ground and communicate those findings through existing engagement platforms.

As always, we want each of these new developments to be reflective of member needs and feedback. If you have a particular interest in any of these areas or have ideas on what would be most helpful to your daily activities, please get in touch (Michigan-Value-Collaborative@med.umich.edu). We look forward to hearing from you and continuing to work together to improve the health of Michigan through sustainable, high-value healthcare.

Off
View Post
MVC Welcomes Its New Engagement Manager, Jessica Souva, MSN, RN, C-ONQS

MVC Welcomes Its New Engagement Manager, Jessica Souva, MSN, RN, C-ONQS

I feel fortunate to have the opportunity to become a part of the impactful work that MVC began a decade ago. Joining a team that is so committed to improving healthcare quality across Michigan has renewed my passion for driving change to achieve equity in healthcare.

I began my career in healthcare as a nurse over 21 years ago. I have worked as a clinical nurse in the adult and pediatric emergency departments, labor and delivery, and ambulatory care.  In 2018, I earned my Master of Science in Nursing (MSN) from the University of Michigan before transitioning into the quality improvement realm of healthcare in 2019 as a site engagement coordinator for the Obstetrics Initiative (OBI). During my time with OBI, I supported hospital quality improvement teams by applying data analytics to support the implementation and sustainability of health equity initiatives. I believe that healthcare cannot achieve optimal quality without equity in service delivery.

In my time between OBI and MVC, I worked within the care management department at Michigan Medicine, developing workflow processes to launch the University of Michigan Physician Advisor Program, and provided strategic planning support to the nursing and medical directors.

When I am not working, I enjoy cheering on my youngest daughter’s softball team, kayaking, and traveling to new places as much as possible. Please don’t hesitate to reach out to me at jlbishop@med.umich.edu if you have any questions.

Off
View Post
MVC Implements a Variety of Data Updates to Episode Methodology

MVC Implements a Variety of Data Updates to Episode Methodology

Throughout the past few months, the MVC team has made several methodological updates to its claims-based episodes of care data underlying the metrics shared via MVC’s online registry and push reports. Some of these updates were part of regular claims data maintenance, whereas others were improvements identified and implemented by the MVC team.

Long-Term Acute Care Hospital Utilization Added as Post-Acute Care Category

A new category of post-acute care utilization was generated within MVC episodes of care: long-term acute care hospital (LTACH) stays. Previously, facility claims were grouped into seven major categories: inpatient, inpatient rehab, outpatient rehab, emergency department, skilled nursing facility, home health, and outpatient/other. An area of opportunity was identified by the MVC Coordinating Center and MVC members to add LTACH to this list. Formerly in MVC data, claims for stays at LTACH facilities were grouped in with inpatient claims and thus counted towards “inpatient readmissions” in the context of an MVC episode of care. LTACH is now its own category of care within MVC episodes and is assessed separately from inpatient stays at general acute care hospitals and Critical Access Hospitals. To count towards post-index LTACH care in an MVC episode, a facility claim must contain bill type 011X and the billing facility NPI for the claim must be primarily affiliated with taxonomy code 282E00000X. LTACH claims will continue to be price standardized in the same manner as other inpatient claims.

As a result of LTACH being added as a separate category of care in MVC episodes, MVC members can now also look at their patients’ use of LTACHs on the MVC registry. By index condition, members can view their attributed episodes’ rate of post-index LTACH utilization as well as their average LTACH payment per episode within the Payment by Condition reports for all payers. To do so, users must navigate to the Payment by Condition report, scroll down to the “Payment Measure” filter on the left side of the registry, and select “LTACH ($)” or “LTACH (%)” to look at average payments or utilization rates, respectively.

Updates to Hierarchical Condition Category (HCC) Identification

Another update made to MVC data this year was the application of components from the most recent specifications around hierarchical condition categories (HCC) from the Centers for Medicare & Medicaid Services (CMS). HCCs are patient comorbidities that both CMS and MVC use as part of risk-adjustment processes. When creating episodes of care, MVC uses each patient’s claims data in the 180 days prior to a given index event to retrospectively assess the comorbidities diagnosed for that patient prior to their MVC episode of care. Formerly, diagnoses indicated as “present on admission” on a patient’s index claim were also used to ascertain a patient’s HCCs, but MVC has updated its methodology such that no diagnoses from the index claim will be used in the assessment of patient HCCs going forward. MVC continues to create 79 HCCs according to HCC V22, with new diagnosis codes added each year.

Furthermore, we note that the category hierarchies created by CMS have been applied to the HCC comorbidities that MVC assesses and displays on the registry. The “hierarchical” aspect of the condition categories is applied to groups of similar diagnoses with a goal that patient comorbidities are not over-counted. For example, a patient diagnosed with diabetes may have multiple similar diagnoses reported on claims over a six-month period, such as diabetes without complications, diabetes with chronic complications, and diabetes with acute complications. Rather than describing that patient as having all three diagnoses, a hierarchy is applied so this patient will simply be described as having the most severe of the group of diagnoses (i.e., diabetes with acute complications). To look at the prevalence of HCC comorbidities among your patient population for one of MVC’s 40+ inpatient or surgical episodes of care, members can navigate to the “Comorbidities” report on the registry.

New Medicare Severity Diagnosis-Related Group (MS-DRG) Version

As part of annual maintenance to accommodate newly introduced billing codes, MVC recently updated the version of Medicare Severity Diagnosis Related Codes (MS-DRGs) being used to re-group inpatient claims into categories of similar inpatient stays. MS-DRG v40.1 is now being used by MVC to categorize all inpatient claims containing ICD-10-CM diagnosis codes and ICD-10-PCS procedure codes.

Inpatient Claim Outlier Length of Stay Methodology

MVC updated the method by which inpatient claims with a particularly long length of stay are identified and price standardized. MVC price standardizes each inpatient claim by adding up three components: a standard DRG-based payment, an inpatient transfer payment (if applicable), and a length of stay-based outlier payment (if applicable). An outlier payment is added to the total price-standardized payment amount for a given inpatient claim if the covered patient remained in the hospital significantly longer than an average patient with the same DRG. In the past, MVC identified these “outlier” long length of stay inpatient hospitalizations using publicly available national long length of stay thresholds for every DRG from TRICARE, the uniformed services healthcare program. MVC’s updated outlier methodology uses Medicare Fee-for-Service (FFS) claims to identify the 99th percentile in length of stay (days) among inpatient claims for each MS-DRG. The hospitalization length of stay on each inpatient claim is then compared against the newly identified 99th percentile threshold for the corresponding DRG. Claims with stays exceeding that length threshold are considered outliers. The outlier payment added to that claim’s price-standardized payment amount is then calculated with an unchanged formula as follows: Outlier Payment = (Number of Days Over DRG-Specific Length of Stay Threshold) * $2,500.

All-Cause Readmissions Assessed for All MVC Conditions

New this year, all-cause inpatient readmissions following index hospitalizations will be assessed for all MVC conditions whenever readmission metrics are shown. Specifications around the identification of readmissions will not vary by index condition.

Episodes Containing COVID-19 Care Now Identified by Primary Diagnosis Codes Only

Finally, MVC has modified the identification of episodes containing care for COVID-19. Episodes are now flagged as containing significant COVID-19 care if they meet the following criteria: at any point during the 30- or 90-day episode, a COVID-19 diagnosis (U07.1) was found in the primary diagnosis code position on a facility claim categorized as inpatient, inpatient rehab, skilled nursing facility, or LTACH. These episodes are often excluded from metrics displayed in MVC push reports. To exclude episodes containing COVID-19 care from metrics shown on the registry, members can use the registry filter called “COVID Cases.” Users should select “Exclude 30-Day COVID” to exclude episodes in which COVID-19 was found within the index event or 30 days post-index. Selecting “Exclude 90-Day COVID” will exclude episodes where a primary COVID-19 diagnosis was found within the index event or 90 days post-index.

For more information on MVC episodes of care data, please refer to MVC’s data guide. MVC members with questions not covered within the data guide are welcome to reach out to the Coordinating Center at Michigan-Value-Collaborative@med.umich.edu.

Off
View Post
MVC Publishes its 2023 QECP Public Report as a Qualified Entity

MVC Publishes its 2023 QECP Public Report as a Qualified Entity

Today the MVC Coordinating Center published its annual Qualified Entity Certification Program (QECP) public report for 2023. One of the requirements of being a qualified entity (QE) with the Centers for Medicare & Medicaid Services (CMS) through the QECP is the annual dissemination of a public report created using claims data. MVC shared its first public report last year, making the 2023 report the second iteration.

As with last year, the 2023 MVC QECP Public Report provides unidentified aggregated data on Michigan hospitals for two measures: rates of 30-day rehospitalizations following start of home health care, and rates of outpatient follow-up received after hospitalization for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD). Both measures were created using data from episodes of care initialized by inpatient hospitalizations or surgeries between 1/1/2018 and 12/31/2021.

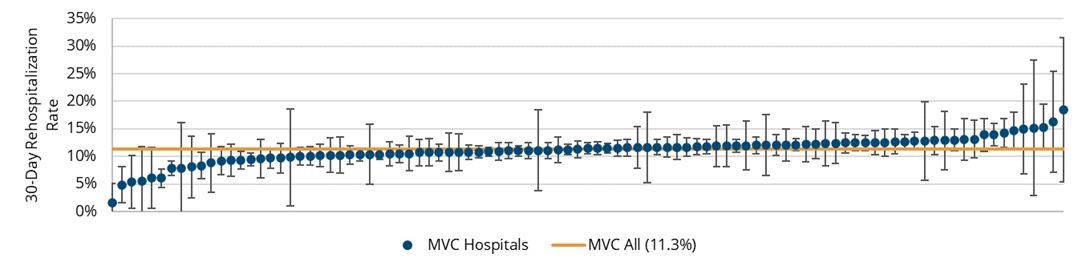
For 2018-2021, the overall rate of 30-day unplanned rehospitalizations from home health among MVC member hospitals in Michigan was 11.3%. Risk-adjusted rates by index hospital ranged from 1.6% to 18.5% (Figure 1). By home health provider, risk-adjusted rates ranged from 2.0% to 23.6%. Patients whose episode of care began with an index event for endocarditis, COPD, CHF, or percutaneous coronary intervention (PCI) were more likely than patients with other index conditions to experience an unplanned rehospitalization in the 30 days after they started home health care.

Figure 1. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by MVC Hospital

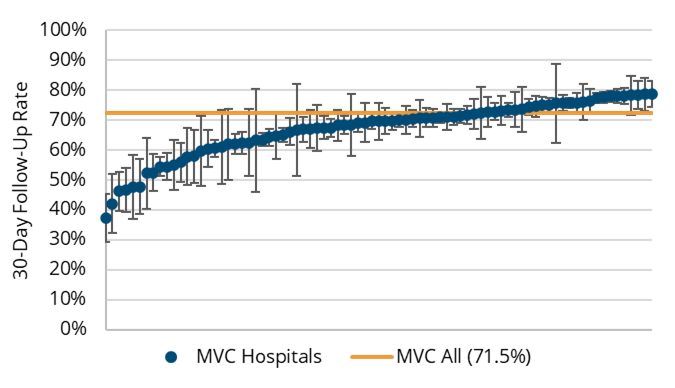
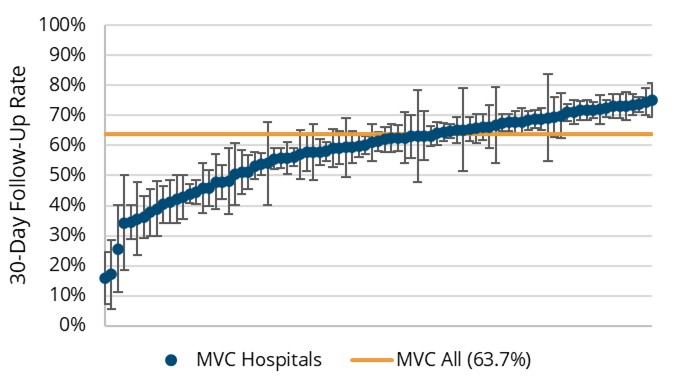
Across the 102 MVC hospitals with attributed episodes of care data underlying this report, the unadjusted rates of patients receiving outpatient follow-up were higher following index hospitalizations for CHF than for COPD (Figures 2 and 3). This was the case whether follow-up occurred three days (16% vs. 13%), seven days (45% vs. 37%), 14 days (63% vs. 54%), or 30 days (72% vs. 64%) after discharge.

Figure 2. 30-Day Follow-Up After CHF by MVC Hospital

Figure 3. 30-Day Follow-Up After COPD by MVC Hospital

For more information and the entire set of findings, we invite you to read the full report, which is available online to any member of the public on the MVC Resources page or directly here.

QE certification status allows MVC to provide hospital members with additional data from Medicare Fee-for-Service (FFS) claims at a level of granularity not otherwise available under standard CMS data use agreements. Reports located under the “QE Data” icon on the MVC registry allow hospital registry users to see unsuppressed data that include case counts <11 as well as utilization rates and average payments based on case counts <11. In addition, on any QE Data registry report, members can click on specific data points to load a list of all episodes underlying that data point. From that episode list, it is possible to view drill-down information on any individual listed episode to learn more about the claims and price-standardized payments comprising that episode.

MVC members representing one or more MVC-participating hospitals can send an email to Michigan-Value-Collaborative@med.umich.edu to learn more about data available through MVC’s QECP reports and to receive the forms necessary to gain access to those registry reports.

0
View Post
MVC Develops PO Post-Discharge and ED-Based Episode Reports

MVC Develops PO Post-Discharge and ED-Based Episode Reports

The Michigan Value Collaborative (MVC) recently completed the development of two new push reports tailored to physician organizations (POs). Both reports mirrored hospital-level push reports distributed earlier this summer and reflect MVC’s ongoing approach to refining and tailoring its analytic offerings to the patient populations and needs of its diverse membership. The first new PO report of 2023 was released in July and focused on post-discharge care, and the second is set to be released next week using new emergency department (ED)-based episodes.

PO ED-Based Episodes Report

The forthcoming PO ED-based episode report features MVC’s new ED-based episode data for five high-volume ED conditions: chest pain, abdominal pain, chronic obstructive pulmonary disease (COPD), congestive heart failure (CHF), and cellulitis. A hospital-level version was distributed in June.

ED-based episodes are a new episode of care structure developed by MVC in collaboration with the Michigan Emergency Department Improvement Collaborative (MEDIC). These episodes are initialized by a patient’s visit to the ED and include all claims-documented care received in the 30 days following a patient’s index ED visit.

For each of the five index conditions included in this forthcoming report, POs will receive information on risk-adjusted and price-standardized 30-day total episode payments, same-day inpatient admission rates over time, utilization of healthcare services across an attributed patient’s 30-day episode of care, and the hospitals where a PO’s attributed patients most frequently presented to the ED for a given index condition. Patient claims data were included for adult patients aged 18 and older who had an ED visit between 1/1/21 and 8/31/22 and were insured by Blue Cross Blue Shield of Michigan (BCBSM) PPO Commercial, BCBSM Medicare Advantage (MA), or Medicare Fee-for-Service (FFS).

Among POs receiving a report, average risk-adjusted, price-standardized 30-day total episode payments for the five reported conditions were highest for CHF ED-based episodes ($16,936) followed by COPD ED-based episodes ($10,286), and lowest for unspecified chest pain ($3,714). Within each condition, MVC 30-day total episode payments were consistently higher for episodes in which the attributed patient had a same-day inpatient admission compared to episodes in which the attributed patient did not have an inpatient stay begin on the date of their ED visit.

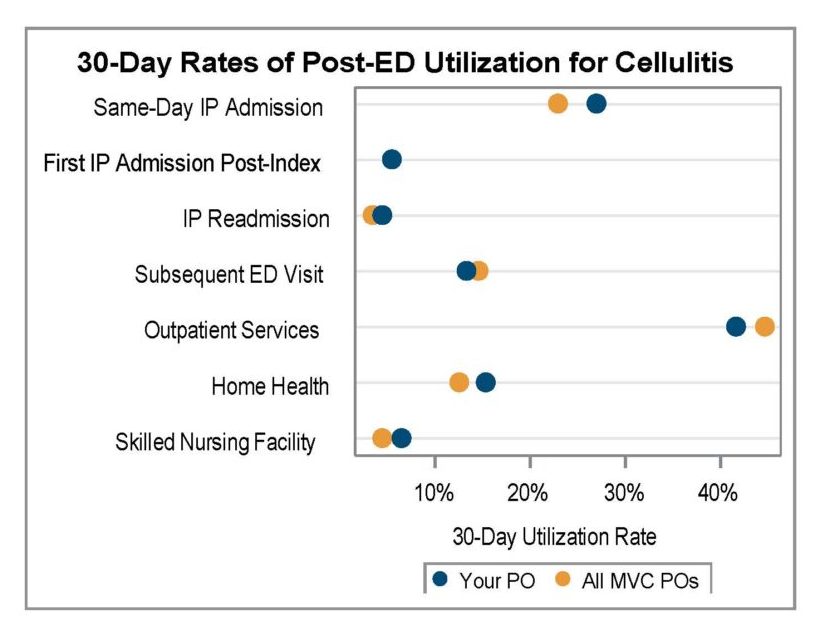
A key goal for these ED-based episode reports was to provide insight into healthcare utilization following index ED visits. Therefore, reports included a dot plot (Figure 1) comparing each PO’s post-ED utilization for their attributed patients compared to the average across all 40 MVC member POs.

Figure 1.

PO Skilled Nursing Facility & Home Health Report

In July, MVC distributed PO-level reports on post-discharge care that included metrics on skilled nursing facility and home health utilization. A hospital-level version was distributed in June. The purpose of this report was to support understanding of care coordination opportunities and benchmark post-discharge care utilization.

This report highlighted various SNF and home health utilization metrics using 30-day claims-based episodes for MVC’s medical conditions: acute myocardial infarction (AMI), atrial fibrillation, COPD, CHF, endocarditis, pneumonia, sepsis, small bowel obstruction, and stroke. A PO’s attributed patient episodes were included if they had an inpatient admission between 1/1/2021 and 6/30/2022 and were insured by BCBSM PPO Commercial, BCBSM MA, or Medicare FFS.

As with other PO-level push reports, MVC included several comparison groups to aid individual POs in benchmarking their performance for select report metrics. Each PO can compare their data to the average for POs of a similar size, the average for POs located within the same geographic region of Michigan according to MVC’s region designations, and the collaborative-wide average for all MVC member POs. Only POs with 20 or more episodes in 2021 and 11 or more in 2022 received a report and were included in comparison group calculations.

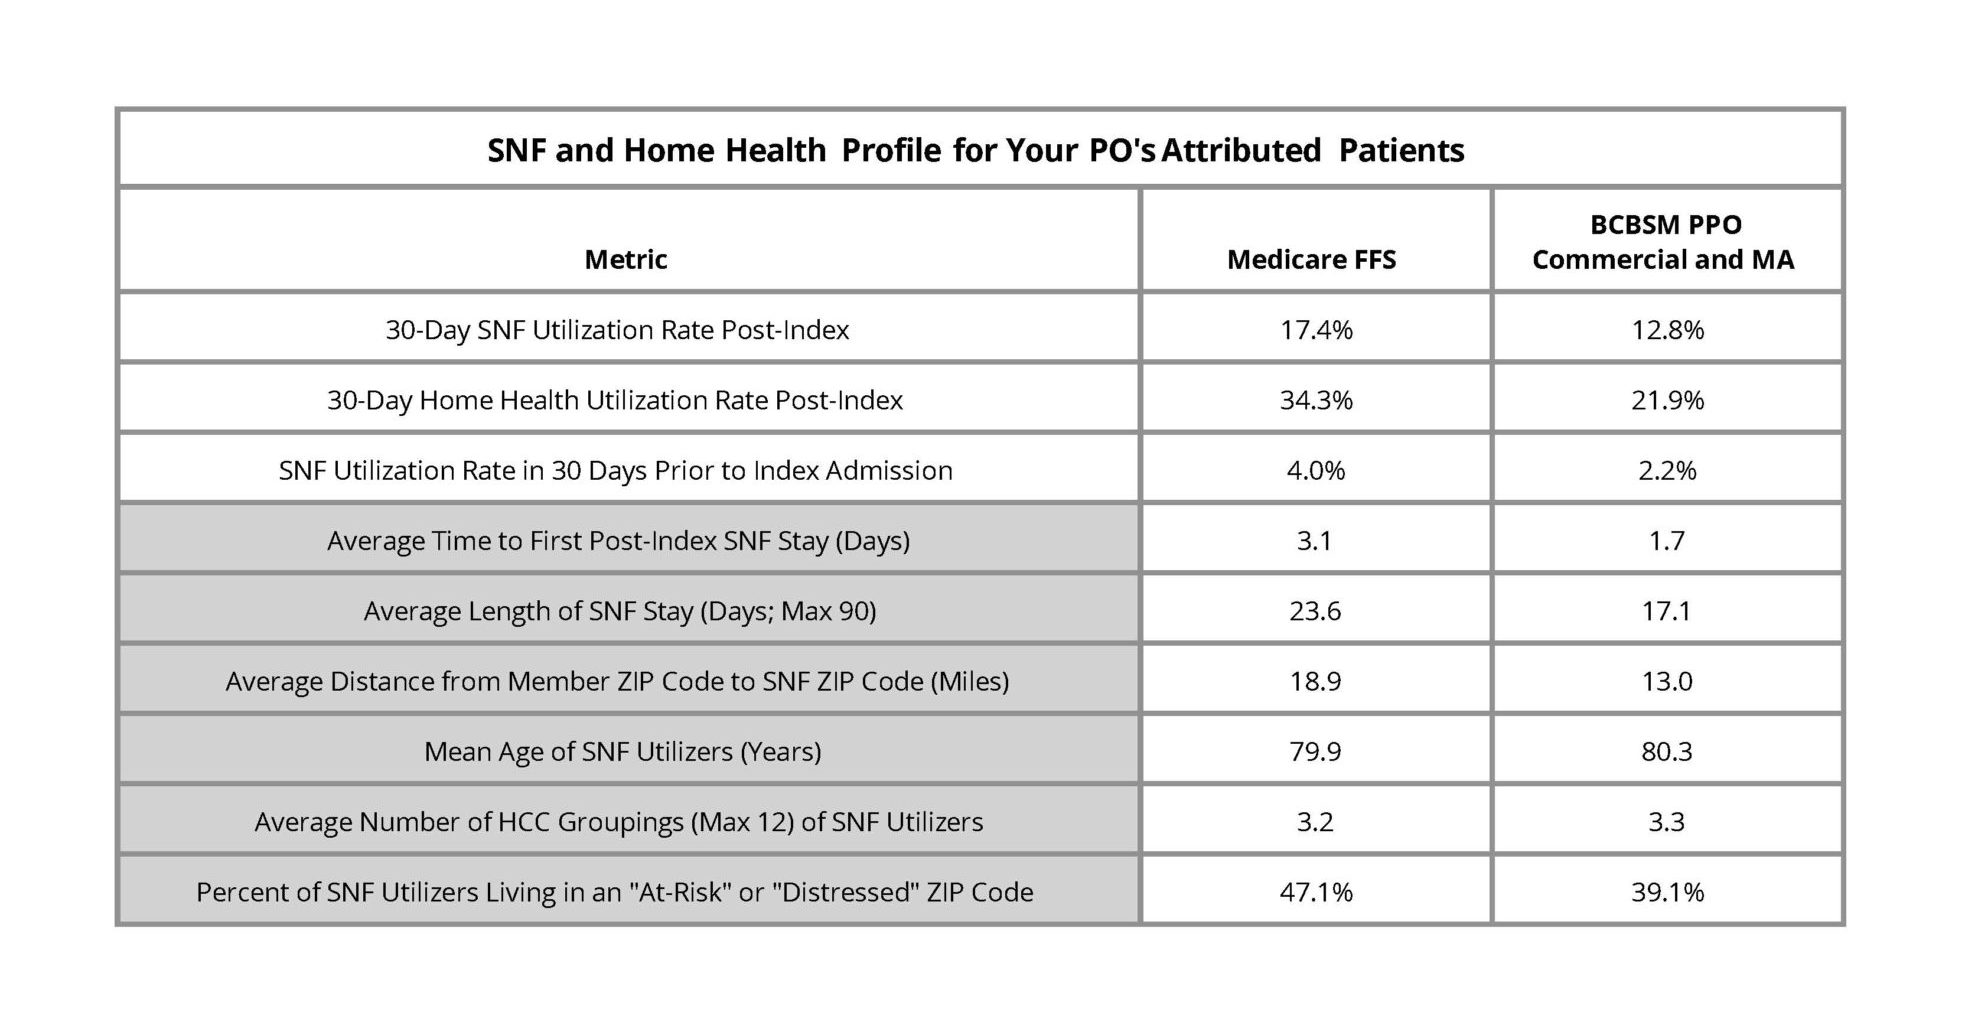
Similar to the hospital-level version, the first page of the report contained a SNF and home health profile table (Figure 2), which provided an overall look at post-discharge utilization patterns by payer as well as information about a given PO's patient population. The first three metrics reflected all attributed patients treated for medical conditions in this time period for the included payers and the metrics in gray were comprised only of attributed patients who utilized SNF in the 30 days post-discharge from their episode's index hospitalization. Overall, MVC found that Medicare FFS patients utilized SNF and home health services more often.

Figure 2.

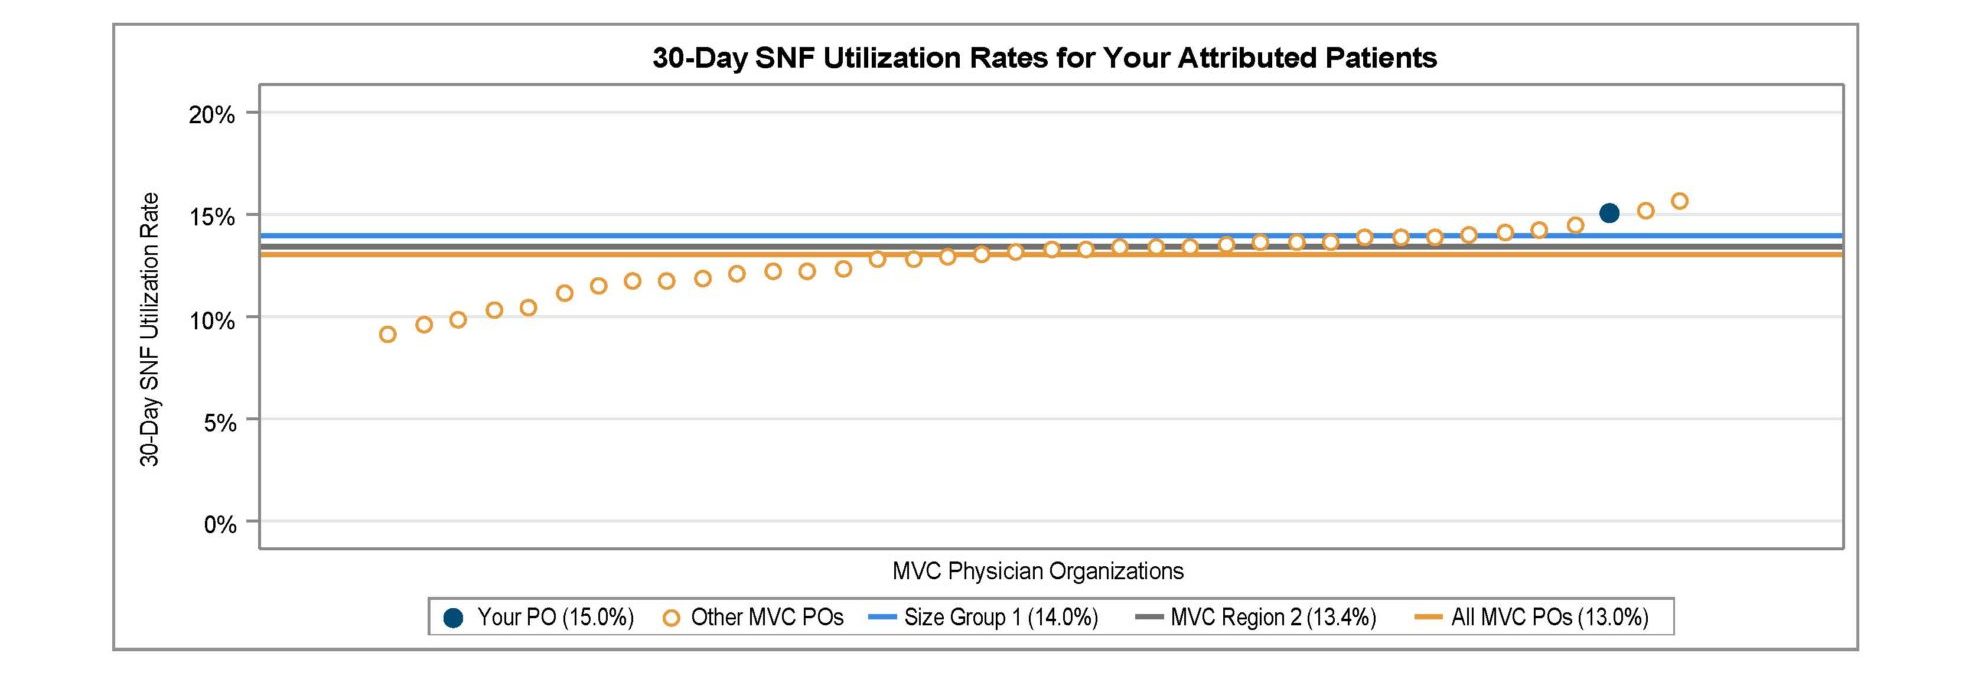
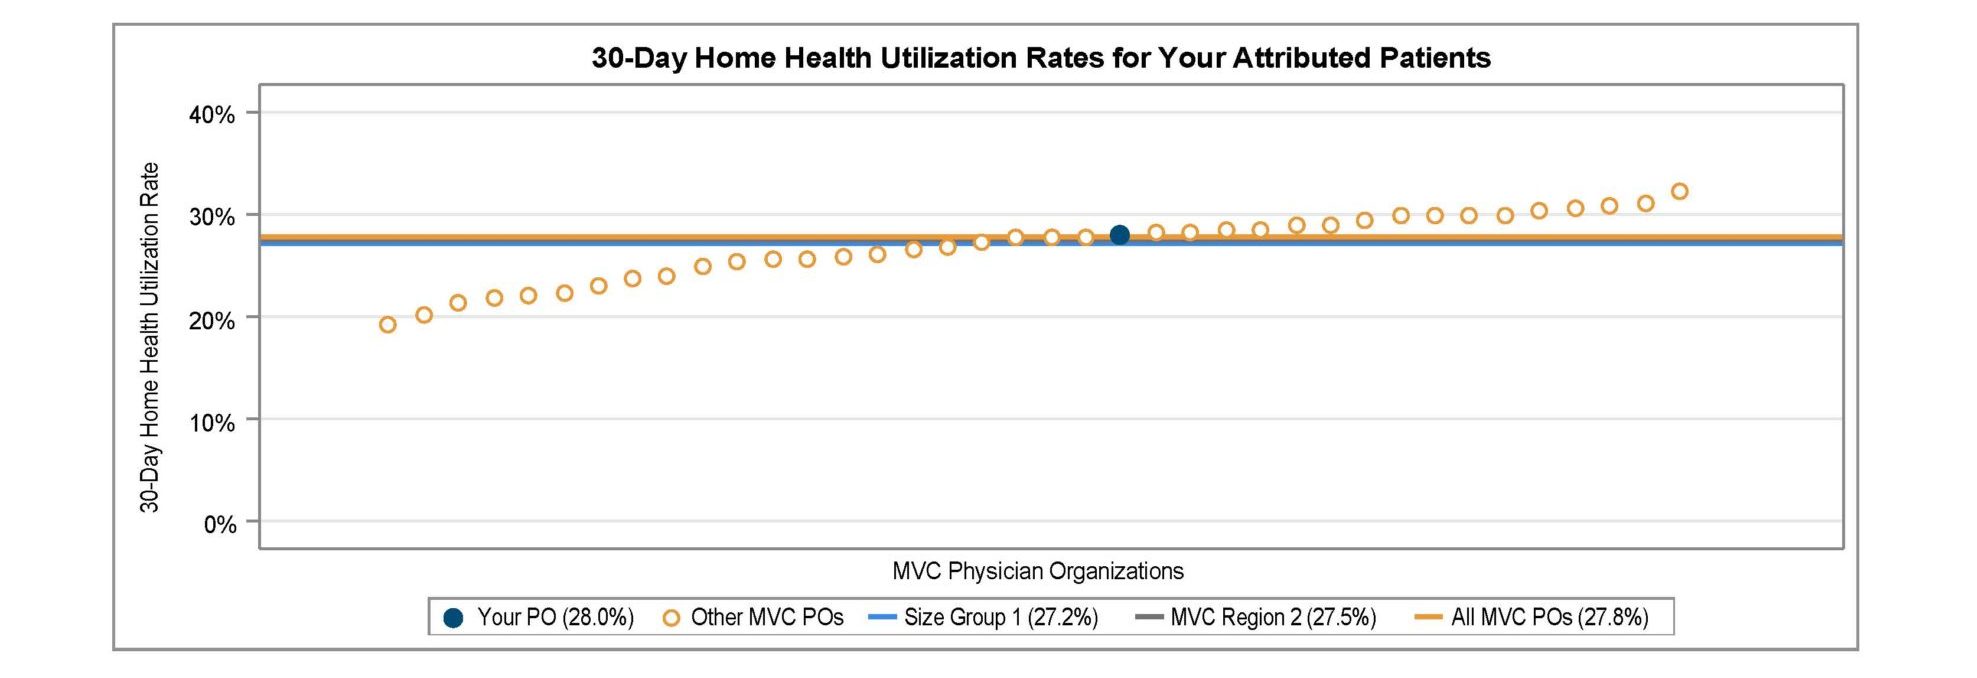
Measures in this report include SNF and home health utilization rates overall and by condition, SNF and home health utilization rates among patients discharged to their home, inpatient readmission rates for SNF and home health utilizers, and a list of the most frequently utilized SNFs and home health providers to help POs understand where their attributed patients are going when receiving SNF or home health care after discharge. MVC presented 30-day overall SNF and home health utilization rates in a caterpillar plot format to showcase variation across POs. These rates varied between roughly 9% and 16% for SNF utilization (Figure 3) and between 19% and 32% for home health utilization (Figure 4).

Figure 3.

Figure 4.

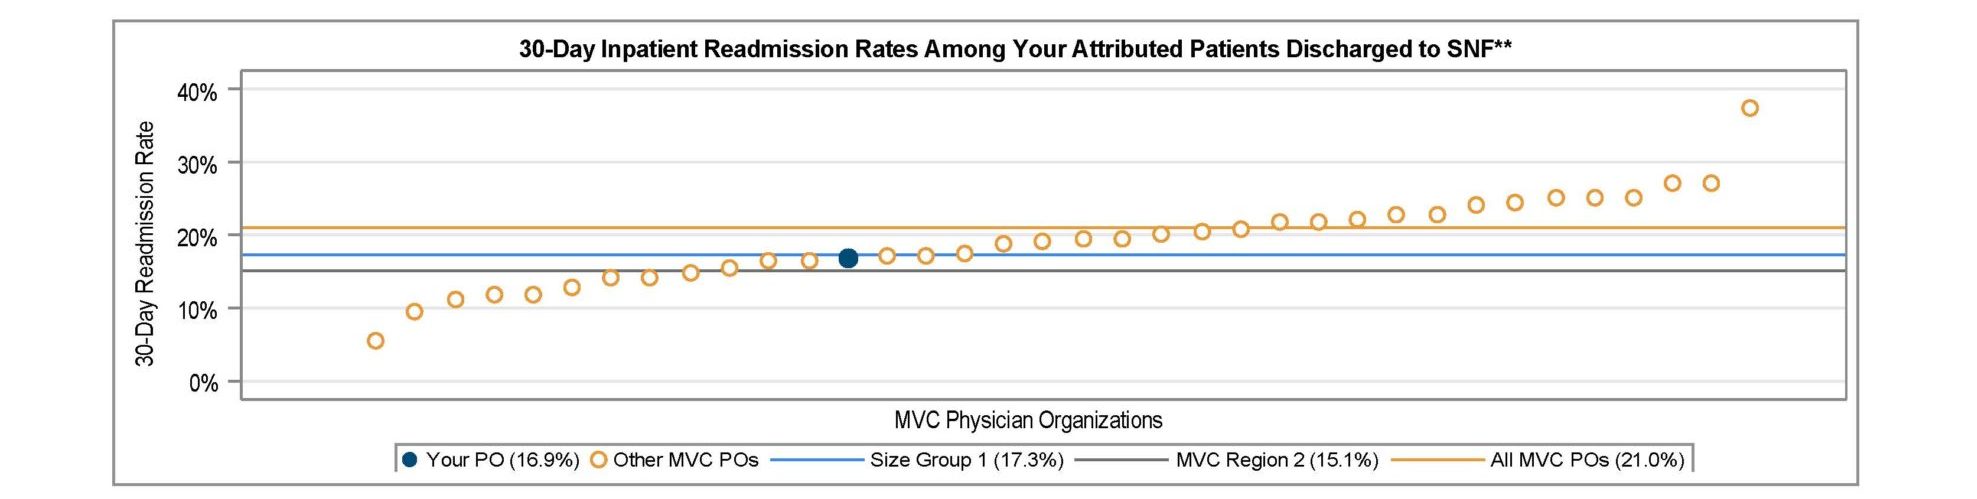
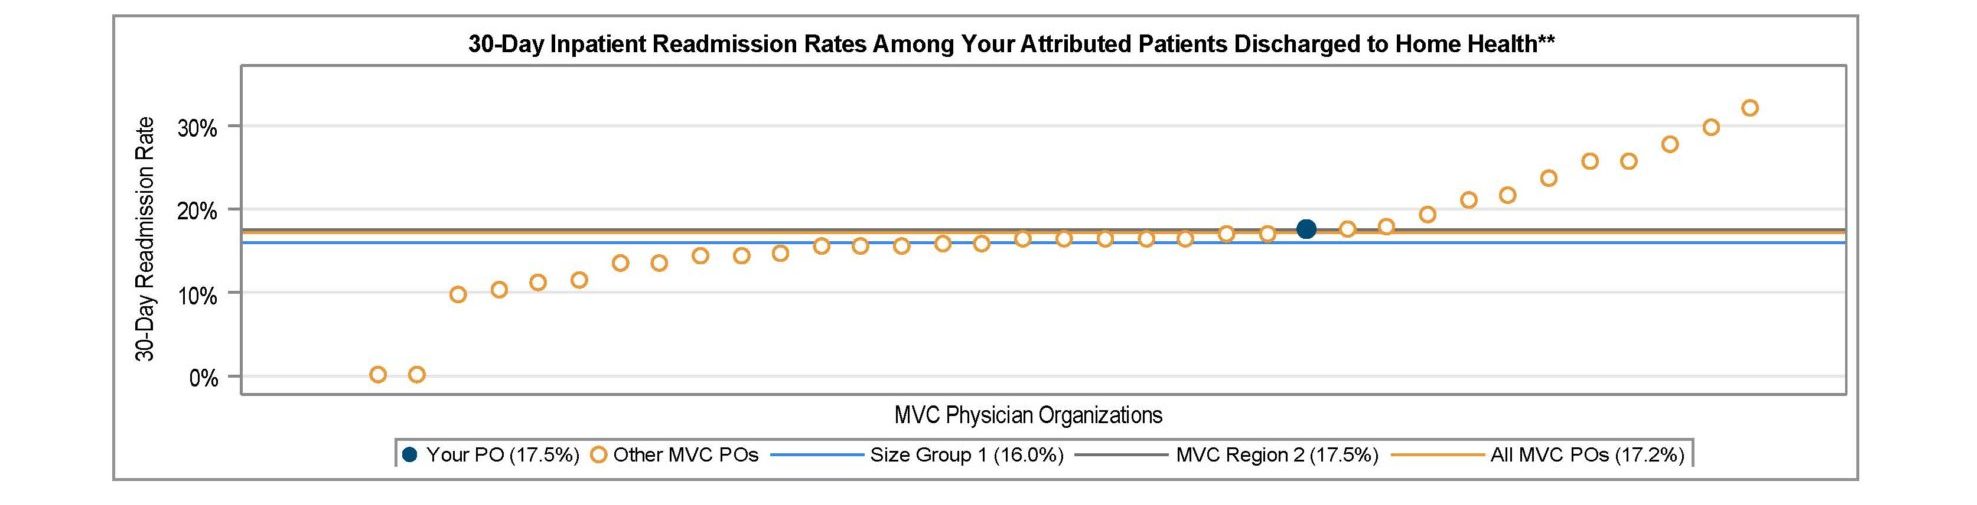
MVC observed average 30-day inpatient readmission rates of 21% among attributed PO patients discharged to SNF (Figure 5) and 17.2% among attributed patients discharged to home health (Figure 6).

Figure 5.

Figure 6.

New Report Distribution Process

MVC piloted a new method for distributing its push reports when sending out the PO SNF/HH reports and is continuing that method for the distribution of its PO ED-based episode reports. Over the summer, PO site coordinators received an email from Dropbox as well as from MVC with a link to their PO’s designated Dropbox folder. Since then, MVC has been working to confirm that contacts are able to successfully access their designated folder and reports.

This new report distribution process will allow MVC’S contacts to access all available MVC reports in a single, secure location, and address some of the email firewall issues experienced by some members. Going forward, members may access and download their individualized reports using Dropbox rather than receiving reports through email. When a new report is made available to members, MVC will still notify all recipients via email with the details of the report. MVC plans to launch this new report distribution process with its hospital partners in the coming months, beginning with Program Year 2023 mid-year scorecards for the MVC Component of the BCBSM Pay-for-Performance (P4P) Program.

If you have any follow-up questions about your site’s latest push reports or the new report distribution process, please contact the MVC Coordinating Center at Michigan-Value-Collaborative@med.umich.edu.

0
View Post
MVC Welcomes New Analyst, Kim Fox, MPH

MVC Welcomes New Analyst, Kim Fox, MPH

It is a privilege to be welcomed to the Michigan Value Collaborative (MVC) team as a Senior Data Analyst! As a new member of the MVC team, I am excited to learn from and work alongside a talented team of MVC coordinators, administrators, and analysts to help improve the health of Michigan through creating sustainable, high-value healthcare.

My public health journey began after discovering the field of Medical Anthropology. Medical anthropologists show us that medical practices are shaped not only by scientific knowledge, but also by sociocultural, environmental, and economic factors. These factors lead to substantial variation in healthcare practices both globally and in our own neighborhoods. It is this principle that underlies my work in public health and keeps me inspired. My goal is to help find compassionate, creative, and robust healthcare approaches that consider and balance these factors to help improve the health and well-being of communities and populations.

Prior to joining MVC, I served in roles that have ranged from research operations and disease surveillance to global healthcare consulting. I received my Master of Public Health (MPH) degree in Epidemiology from the University of Michigan (U-M) School of Public Health and a Bachelor of Arts in Psychology with a minor in Medical Anthropology from U-M.

I am looking forward to working with MVC and its members to identify best practices and opportunities for continuous improvement through the analysis of clinical and claims data. If you have any questions or wish to get in touch, please feel free to email me.

0
View Post
MVC Calls Attention to Research, Resources During Week-Long Preoperative Testing Campaign

MVC Calls Attention to Research, Resources During Week-Long Preoperative Testing Campaign

Prior to surgery, most Michigan patients will undergo a series of tests, such as blood draws, urinalysis, chest x-rays, or electrocardiograms (ECGs/EKGs). Many of these tests are unnecessary for healthy patients undergoing low-risk procedures such as groin hernia repair. Routine preoperative testing is widely considered a low-value service, and yet a majority of hospitals continue to order these tests. In an effort to drive improvement in this area, MVC hosted its second annual preoperative testing awareness campaign this week.

“For a patient, it is key they get the right amount of preoperative assessment,” said Dr. Michael Englesbe, professor of surgery at the University of Michigan, director of the Blue Cross Blue Shield of Michigan-funded Collaborative Quality Initiatives, director of the Michigan Surgical Quality Collaborative (MSQC), and co-director of the Michigan Opioid Prescribing and Engagement Network (Michigan OPEN). “Too little testing and important risks may be missed, too much and patients may be exposed to critical risks of unnecessary testing and delays in care.”

MVC’s Coordinating Center supports preoperative testing de-implementation in several ways. One is providing opportunities for MVC’s members to collaborate and learn from one another. This year MVC launched a workgroup series focused on preoperative testing, the first of which took place in March. As part of its campaign this week, MVC promoted the next session in this workgroup series, set to take place Tues., Aug. 1, from 1-2 p.m. featuring guest speaker Nick Berlin, MD, MPH, MS. Those interested in this topic should register to attend here.

Another key strategy MVC uses to support preoperative testing de-implementation is through data analysis and reporting. MVC analysts utilize administrative claims data to calculate testing rates in the preoperative period, and then share these results with members as reports or as unblinded data at collaborative-wide meetings. More recently, MVC partnered with MSQC to distribute these reports more widely to support cross-collaboration between clinical and quality personnel at a given site.

These reports are an invaluable resource in benchmarking the extent of the issue statewide, says Dr. Hari Nathan, MVC’s director and the chief of hepato-pancreato-biliary surgery at Michigan Medicine. “MVC data can be used by hospitals and providers to understand how their rates of preoperative testing compare to those of other hospitals in Michigan,” he said. “By focusing on a homogeneous cohort of healthy patients undergoing common, low-risk surgical procedures, MVC benchmarks can help all hospitals understand where they have an opportunity to improve, regardless of facility size, resources, or patient population.”

Across the collaborative, MVC sees wide variation in preoperative testing for low-risk elective surgeries like hernia repairs and lumpectomies, with testing rates among young, healthy patients ranging from 10% to 97% across MVC hospitals. This level of interhospital variation is evidence that many hospitals in Michigan are safely performing low-risk surgeries without widespread preoperative testing and that even those hospitals with average rates likely have room to safely reduce their testing further.

MVC also sees quite a bit of intrahospital variation, with certain surgeries driving the overall preoperative testing rate at a given site. Based on the findings of its latest report, one potential area of focus for sites may be reducing the rate of cardiac testing; the rate of ECGs is quite variable across the collaborative and could lead to a cascade of care.

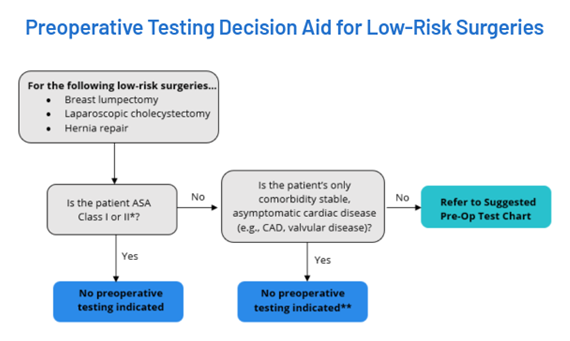
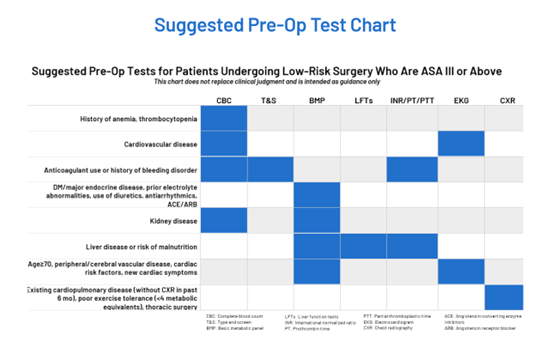
MVC shared its refreshed preoperative testing push report with members in April and also held a report review webinar in June to review the measures included. This webinar also included advice from Dr. Nathan about how to take action using this data. Dr. Nathan promoted several new resources developed in partnership by MSQC, the Michigan Program on Value Enhancement (MPrOVE), and MVC. These include a customizable decision aid (Figure 1), which sites can download to add their branding or modify. It is accompanied by a similarly customizable preoperative testing reference chart (Figure 2).

Figure 1.

Figure 2.

Both of these resources are currently housed on a new Waive the Workup de-implementation resource website managed by MPrOVE, MSQC, and MVC. In addition to pages for the decision aid and chart, the site also offers talking points for debunking common myths about preoperative testing. For instance, one common counterargument to reducing preoperative testing prior to low-risk surgery is a perception that there’s no harm in ordering them, either because they are relatively inexpensive or because they are not invasive tests.

On the contrary, research has established substantial financial costs and risks to patient harm because of preoperative testing, which can and should be safely reduced. Mihir Surapaneni, BBA, a medical student at the University of Michigan Medical School, has been conducting research with MVC on preoperative testing and its impact. “One of the major theories for why there’s so much variability—and indeed just a high utilization rate—for preoperative testing is that there’s no perceived downside,” Surapaneni said. “Many of these tests are relatively cheap compared to the total cost of healthcare and indeed most of them cost no more to the patient than a stick of blood, but we really have to consider that there are costs. Preoperative testing costs billions of dollars in the United States healthcare system annually, and when you consider how strained the healthcare system is and how much of an onus there is on payers and the government to decrease costs, this really adds up. And secondly, we have to consider the possibility of testing cascades—which has been well-documented—in that a patient comes in having an abnormal lab value or test that actually had nothing to do with their intended surgery, and this leads to more and more tests which are expensive and potentially invasive. And finally, we have to consider that there’s established literature showing that even when an abnormality is found in a routine preoperative test, these abnormalities: 1) rarely impact the clinical course of the patient, and 2) rarely lead to actual substantive change in that patient’s care. And I think that we really have to consider these when we’re deciding whether or not we want to test our patients routinely.”

In addition to registering for the Aug. 1 workgroup, MVC has a third preoperative testing workgroup session scheduled for Oct. 26, 11 a.m. - 12 p.m. The Oct. session will be a forum for sharing current successes or initiatives underway across the collaborative. If your hospital has a current initiative underway on preoperative testing de-implementation or has a low average testing rate, MVC would love to learn from you. Please reach out to the MVC team if you’d be interested in sharing your site’s story on Oct. 26.

0
View Post
MVC Reflects on 2023 Mid-Year Progress and Successes

MVC Reflects on 2023 Mid-Year Progress and Successes

As the Michigan Value Collaborative continues its activity in the second half of 2023, the MVC team is taking a moment to pause and reflect on the tremendous work accomplished over the past six months. Here is a look back at some of the highlights.

NEW ED-BASED EPISODE DATA

MVC spent significant time and effort in Q4 of 2022 and Q1 of 2023 developing a new episode-of-care data structure initialized by index visits to the emergency department (ED). This work was done in collaboration with MEDIC—the ED-focused CQI—and the data science portion was completed by ArborMetrix. ED-based episodes were created for 15 high-volume, ED-relevant conditions from January 2017 through the present using all BCBSM, BCN, and Medicare plans for which MVC has claims data. Episodes were created for index events at all qualifying hospitals in Michigan. Over two million ED-based episodes have been created thus far, with plans to update and add additional claims data on a regular cadence. These data were used in the creation of a new ED-based episodes push report and are also available for use in custom reports for members.

ANALYTICS & REPORTING

Since Jan. 1, the MVC team has completed a total of 11 custom requests as well as six push reports, three of which were new:

  • ED-based episodes report (hospital version) - new
  • Skilled nursing facility (SNF) and home health report (hospital and PO versions) - new
  • P4P final scorecards for PY 2022
  • Preoperative testing report refresh
  • Cardiac rehabilitation report refresh

MVC COMPONENT OF THE BCBSM P4P PROGRAM

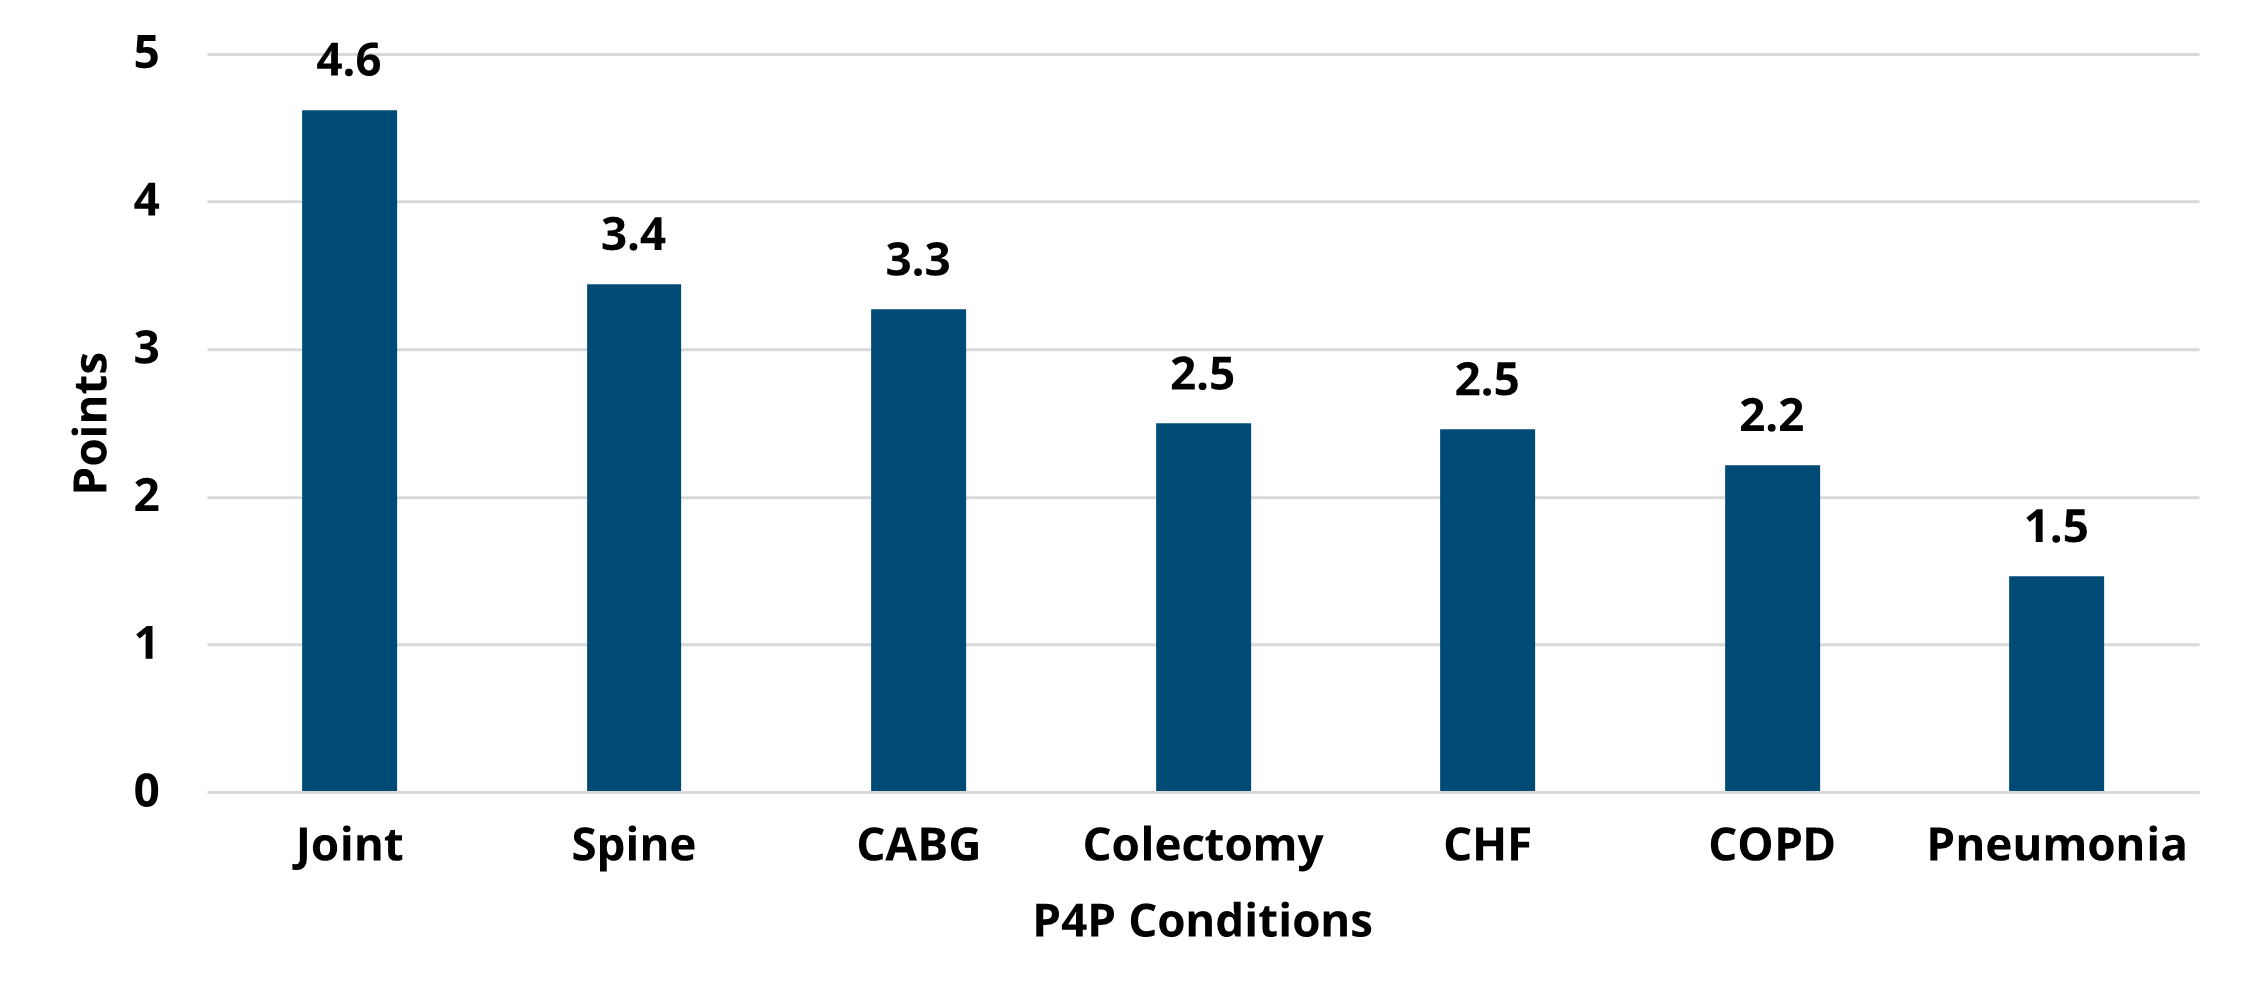
So far in 2023, MVC has been busy implementing and adjudicating the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. In March, MVC finalized and evaluated PY 2022, sending final scorecards to participating hospitals. PY 2022 was the first year of a two-year cycle for which MVC data was used to evaluate hospitals on two of seven selected episode spending conditions, including chronic obstructive pulmonary disease (COPD), colectomy, congestive heart failure (CHF), coronary artery bypass graft (CABG), joint replacement, pneumonia, and spine surgery. The average total points scored was 6/10 before including bonus points, one point higher than the previous PY average. Consistent with previous years, joint replacement was the highest-scoring condition with an average of 4.6 points earned, while pneumonia was the lowest-scoring condition with hospitals earning 1.5 points on average (Figure 1).

After finalizing the methodology for the PY 2024-2025 cycle, MVC collected selections from all hospitals in early Feb. for one of five episode spending conditions and one of seven value metric options. MVC hosted two explainer webinars and five one-on-one meetings to support sites with their episode spending metric and value metric selections. The most common episode spending selection was for joint replacement and the most common value metric selection was seven-day follow-up after CHF.

Figure 1.

QUALIFIED ENTITY PUBLIC REPORT

MVC was approved as a qualified entity (QE) in 2022 under the Qualified Entity Certification Program (QECP) and continues to fulfill requirements to maintain QE status. In the first half of 2023, MVC continued to provide authorized hospital users with registry access to QE Medicare data that met program requirements. In Jan., MVC also published its 2022 Annual Public QECP Report. MVC’s first public report as a QE provides information on hospital performance for two sets of measures: rehospitalization following post-discharge home health use, and outpatient follow-up receipt following CHF/COPD inpatient hospitalization. The public report was published on the MVC website and shared with MVC contacts via email. MVC will refresh and publish its next annual public report this fall, adding two new years of data.

MAY COLLABORATIVE-WIDE MEETING

MVC held its spring collaborative-wide meeting on May 19. A total of 86 leaders from a variety of healthcare disciplines attended representing 50 different hospitals and 13 POs from across the state of Michigan. “Connecting the Dots: Celebrating 10 years of value-based care” was the theme, putting the spotlight on care transitions, care coordination, and MVC’s 10 years of supporting data-driven quality improvement. MVC was joined by guest speakers from Trinity Health IHA Medical Group and the new lung health CQI, INHALE. MVC also offered a poster session highlighting the work of several members and partner CQIs. MVC staff prepared a variety of unblinded data presentations, including a first look at its new ED-based episode data as well as unblinded breakout session presentations on its new P4P value metrics. Save the date for MVC’s fall collaborative-wide meeting, scheduled for Friday, October 20 at the Radisson Hotel Lansing.

WORKGROUPS

Over the last six months, MVC delivered a total of 14 workgroups, which were designed to provide a highly accessible online platform for hospital and PO leaders to come together, collaborate, and learn from peers. MVC offers workgroups on six topics this year: cardiac rehabilitation, chronic disease management, diabetes, health equity, health in action, and preoperative testing. Visit the MVC 2023 Events Calendar to check upcoming dates and topics and to register.

In addition, MVC launched a new Lunch and Learn series dedicated to MVC-focused activities and topics. The kickoff session in March included an overview of MVC and its offerings for new site coordinators or partners. The next session in June featured an introduction to MVC’s data sources, its episode structure and methodology, and an analyst-led walkthrough of one of MVC’s most recent push reports. MVC plans to host two more Lunch and Learn sessions later this year on other topics.

NEW COORDINATING CENTER STAFF

In June, MVC welcomed two new data analysts to the Coordinating Center: Kushbu Narender Singh, MPH, and Jiaying (“Janet”) Zhang, MPH. MVC published welcome blogs about Kushbu and Janet last month and looks forward to introducing them to members and partners in the coming months.

AND COMING SOON…

The MVC team is hard at work preparing for its first Rural Health Meeting, scheduled for Wednesday, August 9, from 10 a.m. to 12 p.m. via Zoom. The purpose of the meeting is to provide presentations and MVC data tailored to its rural or Critical Access Hospital members. This meeting will feature presentations by leaders from MVC, Scheurer Health, and the Michigan Critical Access Hospital Quality Consortium. RSVP here.

0
View Post
Study Shows Lasting Impact of a Modifier 22 Initiative on Opioid Use Among Vasectomy Patients

Study Shows Lasting Impact of a Modifier 22 Initiative on Opioid Use Among Vasectomy Patients

The opioid epidemic continues to harm individuals and communities worldwide; over-prescribing, overuse, and related overdose deaths persist in the United States and abroad. Without proper intervention, the proliferation of opioid use disorder and its negative impact on population health will continue. Healthcare professionals and stakeholders eager to stem this crisis are investing in the development and iteration of interventions that improve control of opioid distribution. As part of this effort, one team of healthcare researchers recently published a paper in Urology investigating the impact of an insurance payer’s novel opioid reduction intervention on the adoption of opioid-sparing pathways.

The authors of this publication, including lead author Dr. Catherine S. Nam, M.D., and her colleagues from Michigan Medicine, sought to compare the percentage of patients who filled peri-procedural opioid prescriptions before and after Blue Cross Blue Shield of Michigan (BCBSM) launched a modifier 22 incentive for opioid-sparing vasectomies in Michigan. This program incentivized the utilization of an opioid-sparing post-operative pathway developed by the Michigan Opioid Prescribing Engagement Network (OPEN) by allowing the use of the modifier 22 reimbursement code for vasectomies performed with minimal or no post-operative opioids. Previous literature has demonstrated success in this approach for other medical procedures. The use of modifier 22 as an opioid reduction intervention was first launched by BCBSM in 2018 for select procedures and was expanded to include vasectomies in 2019. Typically, modifier 22 can be applied to select insurance claims with the primary procedure code when the work attributed to that procedure or medical intervention exceeds the typical amount of required labor. When approved, insurance companies may provide additional reimbursements of up to 35%.

The expanded eligibility for the modifier 22 into vasectomy presented substantial quality improvement potential given both how commonly this procedure is performed—approximately half a million times annually across the US—and the fact that a 2019 survey indicated more than half of urologists prescribed opioids for patients receiving a vasectomy, even though the procedure can be completed without them. For a vasectomy procedure to qualify for the modifier 22 program, a surgeon must intend to follow an opioid-free peri-procedural course as well as provide additional counseling to patients about post-procedural pain expectations, proper opioid disposal, and non-opioid pain management strategies.

Given the novel quality incentive for opioid-sparing pathway application to vasectomy with implications for payers, providers, patients, and policymakers, Dr. Nam and her colleagues were interested in evaluating the impact this policy change had within the state of Michigan.

To perform this analysis, Dr. Nam and colleagues leveraged Michigan Value Collaborative (MVC) administration claims data from beneficiaries in BCBSM’s preferred provider organization (PPO) plan. The data provided by MVC included men ages 20 to 64 who participated in urologic procedures between Feb. 1, 2018, and Nov. 16, 2020.

Between these dates, Dr. Nam and colleagues identified 4,559 men who underwent office-based vasectomies and 4,679 men in the control group, which consisted of men who underwent cystourethroscopies, prostate biopsies, circumcision, and transurethral destruction of prostate tissue. These procedures are all office-based and not eligible for opioid-sparing modifier 22, thus providing a point of comparison.

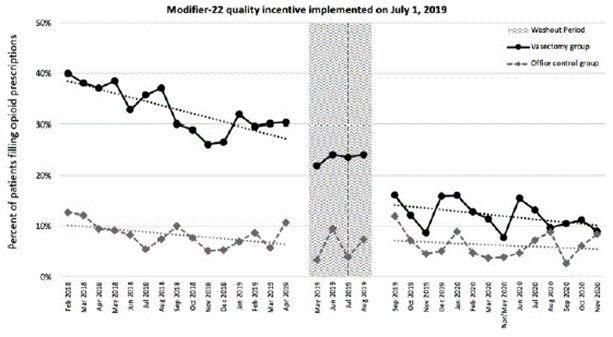
The results of the analysis demonstrated a strong association between the implementation of modifier 22 for vasectomies and filled opioid prescriptions. Before July 1, 2019—prior to the implementation of the expanded modifier 22 policy—32.5% of men filled an opioid prescription after receiving a vasectomy, whereas after implementation only 12.6% of men filled an opioid prescription post-procedure (see Figure 1). As highlighted in the figure below, Dr. Nam and colleagues found a 19.9% absolute reduction and 61% relative reduction in the percentage of vasectomy patients who filled peri-procedural opioid prescriptions.

Figure 1. Percent of Patients Filling Opioid Prescriptions Before and After Implementation of Modifier 22

Among the vasectomy patients in the analysis, for every three opioid prescriptions filled before the implementation of modifier 22, only one was filled after the initiative was implemented. They did not find a significant decrease in the percentage of patients who filled peri-procedural opioid prescriptions in the control group.

In addition to the decreased frequency of men filling peri-procedural opioid prescriptions for vasectomies, Dr. Nam and colleagues also found a significant decrease in the prescribed amount. After the implementation of modifier 22 for vasectomies, the oral morphine equivalents (OME) of peri-procedural opioid prescriptions fills dropped from 89.7 OME per prescription to 27.1 OME per prescription. Dr. Nam and colleagues estimated that this decrease in prescription size led to the distribution of approximately 8,473 fewer oxycodone 5mg pills in Michigan.

When asked about the significance of these findings, Dr. Nam explained, “This estimate helped us grasp the impact of the Modifier 22 policy change for patients as well as the community. If this was the impact in a bit over a year for a single procedure in one state, how large could this impact be annually? What could the impact be when quality incentive is expanded to additional procedures? What if the quality incentive could be expanded to other states?”

These findings suggest that the modifier 22 incentive does decrease the percentage of patients who fill peri-procedural prescriptions after a vasectomy and its implementation correlates with a reduction in the number of opioids circulating within the community. In addition to reducing the unnecessary presence of opioids in communities, this initiative also emphasizes a shift to refocus healthcare interactions on the patient. The required additional education about pain management and proper use of pain management medications implemented as part of the modifier 22 initiative provides patients with a better understanding of their care and encourages physicians to consistently deliver high-value care.

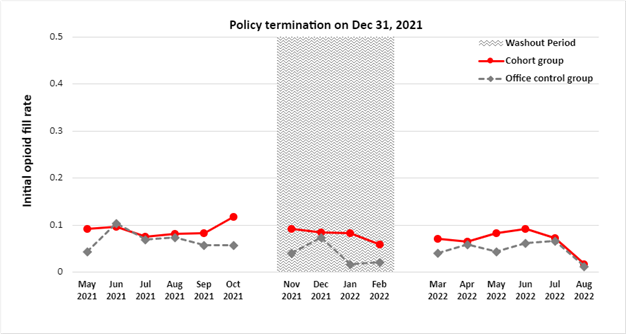
Despite the significant findings of this study, a question remained. If these practice changes were initiated by incentivized modifier 22 interventions, what would happen if BCBSM terminated the incentive? Since the publication of Dr. Nam and colleagues’ original study, BCBSM terminated the financial incentive using modifier 22 for opioid-sparing vasectomies on Dec. 31, 2021. This termination provided the group with an opportunity to observe the long-term impact modifier 22 had on physician prescribing patterns and patient opioid use after the incentive was no longer in place.

Dr. Nam and colleagues performed another interrupted time series analysis before and after the termination of modifier 22 using the same vasectomy and control groups. After analyzing the data provided by MVC, they observed no significant changes in the opioid fill rate compared to the rate observed when the modifier 22 program was in effect. This was true for both the vasectomy group and the control group (see Figure 2). The persistence of reduced opioid prescription sizes was also observed following termination of modifier 22. Prior to incentive termination, the mean opioid prescription amount was 59 OME, and after termination the mean further reduced to 36 OME.

Figure 2. Percent of Patients Filling Opioid Prescriptions Before and After Termination of Modifier 22

These critical findings demonstrate that physician opioid prescribing behavior remained constant after the removal of financial incentives. More research still needs to be done on the long-term impact of programs such as modifier 22; however, Dr. Nam and colleagues suggest that other payers could implement incentive programs like BCBSM’s modifier 22 initiative in order to spur similar changes in prescribing patterns and are hopeful that short-term financial incentives are part of the solution to creating lasting practice changes.

“This is the first example of a novel quality incentive targeting physicians to provide high-value care by incentivizing opioid-sparing pain pathway,” she said. “However, this incentive can be adapted to incentivize other high-value care – could we recognize physicians that are providing guideline-based care? How about ensuring that appropriate lab and imaging tests are ordered for patients as part of their care plan? And if so, could it be possible for there to be an investment made from the insurance companies to champion high-value care for a short period of time to have lasting effects?”

MVC is committed to using data to improve the health of Michigan through sustainable, high-value healthcare. Therefore, one of MVC’s core strategic priorities is intentional partnerships with fellow Collaborative Quality Initiatives (CQIs) and quality improvement collaborators. In partnering with clinical, administrative, and CQI experts to leverage MVC data for analyses, MVC aims to identify best practices and innovative interventions that help all members improve the quality and cost of care.

Publication Authors

Catherine S. Nam, MD; Yen-Ling Lai, MSPH, MS; Hsou Mei Hu, PhD, MBA, MHS; Arvin K. George, MD; Susan Linsell, MHSA; Stephanie Ferrante; Chad M. Brummett, MD; Jennifer F. Waljee, MD; James M. Dupree, MD, MPH

Full Citation

Nam, C. S., Lai, Y.-L., Hu, H. M., George, A. K., Linsell, S., Ferrante, S., Brummett, C. M., Waljee, J. F., & Dupree, J. M. (2022). Less is more: Fulfillment of opioid prescriptions before and after implementation of a modifier 22 based quality incentive for opioid-free vasectomies. Urology, 171, 103–108. https://doi.org/10.1016/j.urology.2022.09.023.