Off
View Post
MVC Welcomes Manager of Data Analytics Ian Raxter, MPH

MVC Welcomes Manager of Data Analytics Ian Raxter, MPH

I am excited to be joining the Michigan Value Collaborative (MVC) team as Manager of Data Analytics! I look forward to working more closely with this great team to improve the quality of care across the state of Michigan.

Since receiving my Master of Public Health in general epidemiology from the University of Michigan in 2012, I have spent my career in the healthcare data world, working in particular with claims data and the CQIs. After graduate school I worked at Blue Cross Blue Shield of Michigan in the Department of Clinical Epidemiology and Biostatistics, working with Value Partnerships to support the Physician Group Incentive Program. After five years there I joined ArborMetrix where I worked as a Data Scientist with several of the CQIs, specifically the Michigan Emergency Department Improvement Collaborative (MEDIC), Michigan Surgical Quality Collaborative (MSQC), Obstetrics Initiative (OBI), and MVC. Following ArborMetrix, I joined Mathematica Policy Research where I worked on a variety of healthcare research projects for federal, state, and other clients.

It was always a pleasure to work with the MVC team during my time at ArborMetrix, and I’m happy to now join the other side of the table to help lead MVC’s analytic team! Please feel free to connect with me at iraxter@med.umich.edu.

Off
View Post
MVC 2025 Spring Collaborative-Wide Meeting Summary

MVC 2025 Spring Collaborative-Wide Meeting Summary

Collaboration in Action: Shaping the Future of Healthcare Across Michigan

The Michigan Value Collaborative (MVC) held its spring 2025 collaborative-wide meeting on Friday, May 9, in Midland. A total of 106 attendees representing 62 hospitals, 6 physician organizations, 6 Collaborative Quality Initiatives (CQIs), and 11 healthcare systems from across the state of Michigan came together to build partnerships and collaborate on approaches to healthcare delivery that will have a long-lasting impact.

MVC Director Dr. Hari Nathan kicked off Friday’s meeting with updates on the MVC Coordinating Center [. He introduced MVC’s newest team members, senior analysts Steven Ellinger and Tanima Basu, and Program Assistant Dinah Pollard. Dr. Nathan also announced the promotion of Jana Stewart to Associate Program Manager and welcomed Dr. Jessica Golbus as the new Co-Director of the Michigan Cardiac Rehab network (MiCR). He provided an update on recruitment progress for Phase II of the RITE-Size pilot and encouraged sites interested in participating to reach out to the MVC Coordinating Center. Dr. Nathan concluded the welcome presentation by highlighting MVC reporting updates. These included new multi-payer preoperative testing dashboard reports added to MVC’s data registry in Q4 of 2024, and five hospital-level push reports with data reflecting P4P Program Year (PY) 2026-2027 selections, statewide health equity, process measures, P4P PY 2024 final scorecards, and ED-based episodes.

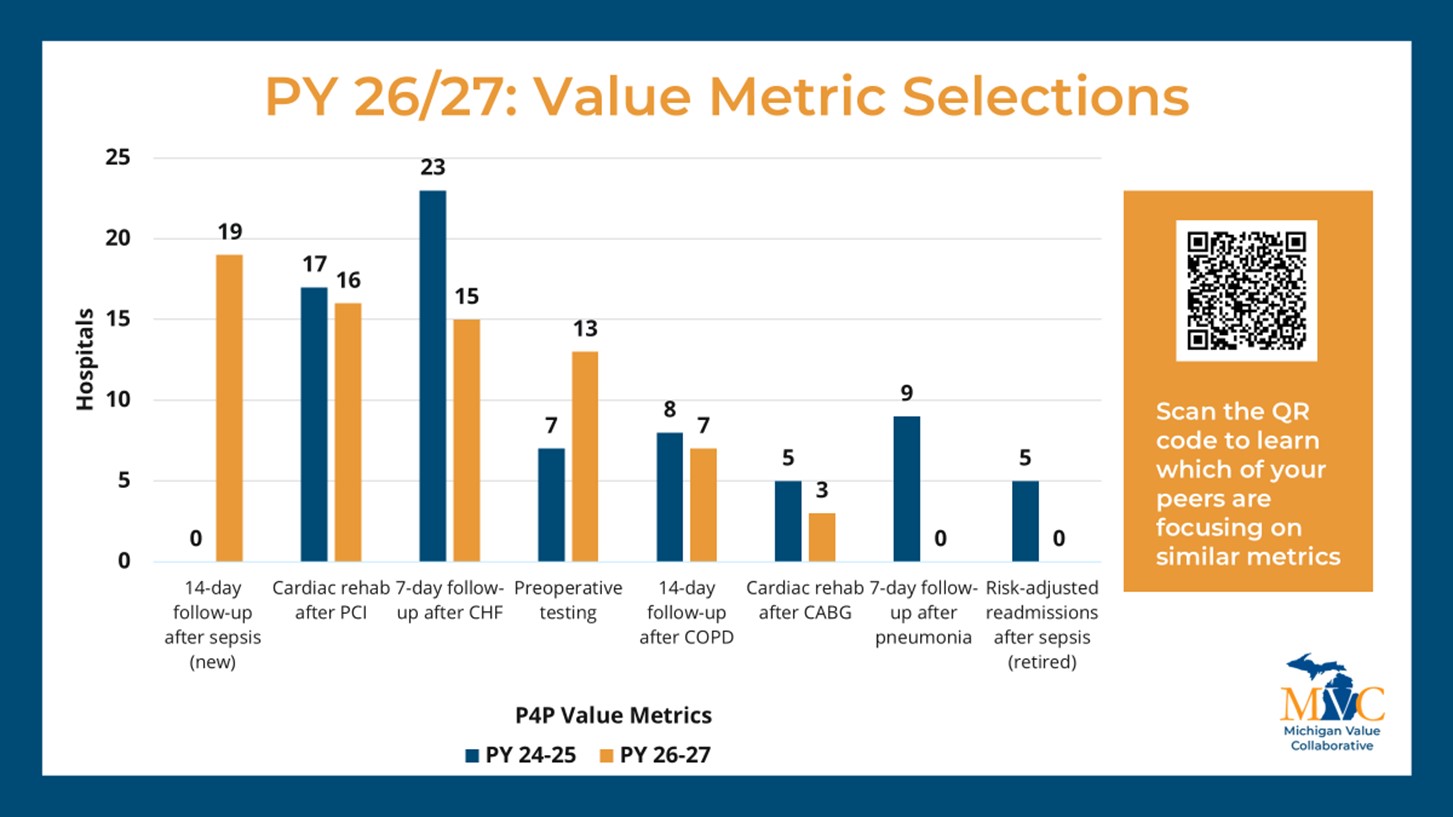
Managing Director Mark Bradshaw, MSc, presented a summary of PY 2024 scoring and PY 2026-2027 selections for the MVC Component of the BCBSM P4P Program [SEE SLIDES]. In his summary of PY 2024 scoring, Bradshaw highlighted opportunities for members to leverage MVC resources to optimize P4P scores via MVC’s engagement point menu options and highlighted some of the value metrics that have seen success after their first year of scoring.

The overview of MVC members’ P4P selections included a comparison of the value metric selections that were made for the PY 2024-2025 vs. the PY 2026-2027 program cycles (Figure 1). Bradshaw also reviewed MVC’s new health equity measure and index of disparity before closing with a reminder about upcoming dates relevant to participating P4P hospitals (Figure 2).

Figure 1. PY 26/27 Value Metric Selections

vertical bar chart: PY 26/27 Value Metric Selections

Figure 2. Upcoming P4P Dates

Upcoming P4P Dates

The meeting then featured MVC’s first Engagement Awards, presented by MVC Engagement Manager Jessica Souva, MSN, RN, C-ONQS. MVC presented the awards to members who went above and beyond in their engagement with MVC to the benefit of the entire MVC membership. Scheurer Health received the award for the most engaged peer group 5 hospital, MyMichigan Collaborative Care organization for the most engaged physician organization (PO), Chelsea Hospital for the most engaged hospital, and Corewell Health for the most engaged health system.

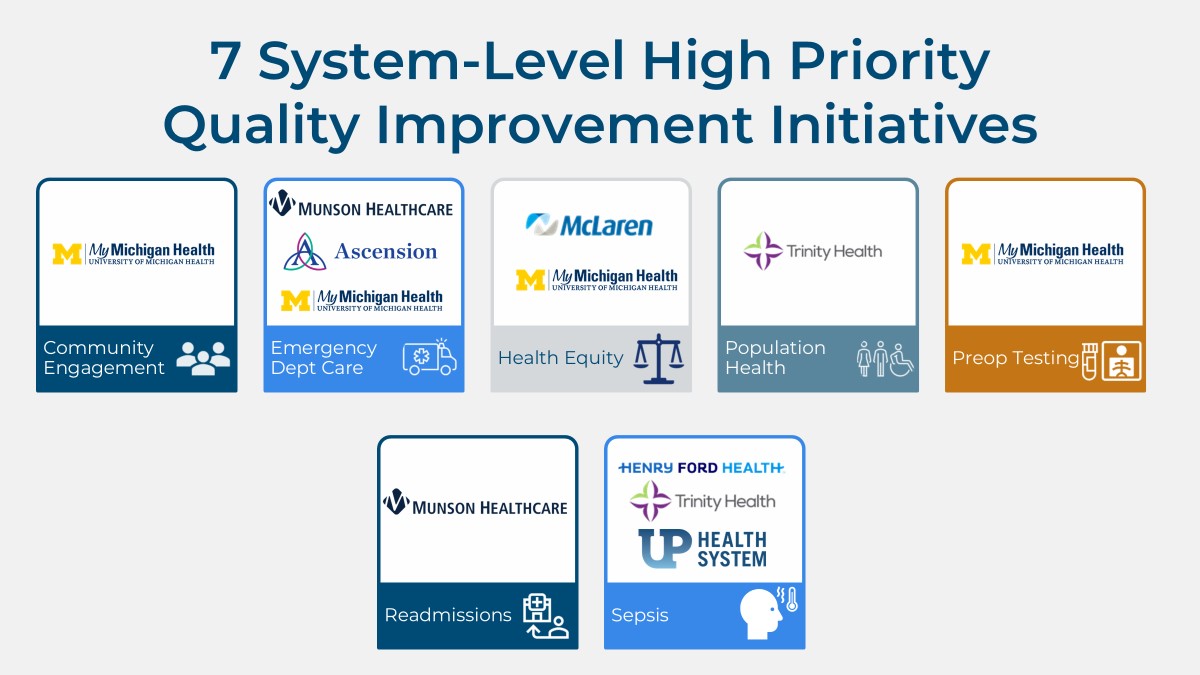
Souva remained at the podium for a presentation on MVC’s 2024 Quality Improvement (QI) survey, sharing details about the survey’s purpose, completion rate, results, and applications [SEE SLIDES]. The four most widely reported QI initiatives included sepsis, health outcome variation, readmissions, and emergency department care, and also aligned with the initiatives reported as highest priority for some of the largest health systems in Michigan (Figure 3). Souva provided specific examples of MVC engagement activities that were developed to specifically support the initiatives reported in the QI survey and address common barriers members reported facing. She urged MVC’s PO members to participate in the 2025 QI survey so that MVC will be better equipped to provide support for PO QI initiatives in the future.

Figure 3. Seven System-Level High Priority Quality Improvement Initiatives

Seven System-Level High Priority Quality Improvement Initiatives

Before sending meeting attendees to participate in the poster session, Souva shared the responses from the opening virtual ice-breaker question: “What keeps you motivated to continue working in healthcare?” Members credited their teams and making a difference in the lives of patients and families as their motivation to persevere during challenging times. Posters were then presented by partner CQIs such as MEDIC, MOQC, MSHIELD, and MI Mind. Electronic copies of the posters are available on the spring meeting website [LINK]. The MVC Coordinating Center would like to thank all poster presenters for sharing their work.

After the poster session, MVC Associate Program Manager Jana Stewart, MPH, provided a presentation highlighting the ways in which MVC collaboratives with other CQIs to help drive local quality improvement efforts in hospitals across Michigan. This included two case studies and unblinded data presentations for MVC’s two value-based initiatives: cardiac rehabilitation utilization and preoperative testing de-implementation. She also presented a use case for a new area MVC is exploring within its ED-based episodes of care focused on behavioral health care and outcomes, also with aggregate and hospital-level unblinded data.

Since the launch of MVC's cardiac rehabilitation initiative in 2020, the work has been incorporated into all aspects of MVC’s portfolio, from dedicated workgroup topics to reporting and related P4P metrics, and it also led to the 2022 launch of MiCR in partnership with BMC2 and the NewBeat program in partnership with HBOM. Cardiac rehabilitation enrollment for patients discharged from a “Main 5” condition (e.g., AMI, CABG, PCI, SAVR, and TAVR), has increased across the collaborative from 24% in 2020 to 34% in 2023, amounting to an estimated 145 lives saved and 243 readmissions avoided. Stewart also shared that the mean days to a patient’s first cardiac rehabilitation visit has decreased from 59 days in 2020 to 46 days in 2024.

Highlights from MVC’s preoperative testing efforts included updates on the RITE-Size pilot—a collaboration largely between MVC, MPrOVE, and MSQC—that supported three MVC member hospitals in reducing their low-value preoperative testing rates in 2024 through a variety of strategies. Stewart called out that members interested in participating in Phase II of the pilot in 2025 or 2026 will be well positioned to both reduce their testing rates significantly and also achieve the full two engagement points for 2025. She encouraged anyone interested to reach out to the MVC Coordinating Center for additional information.

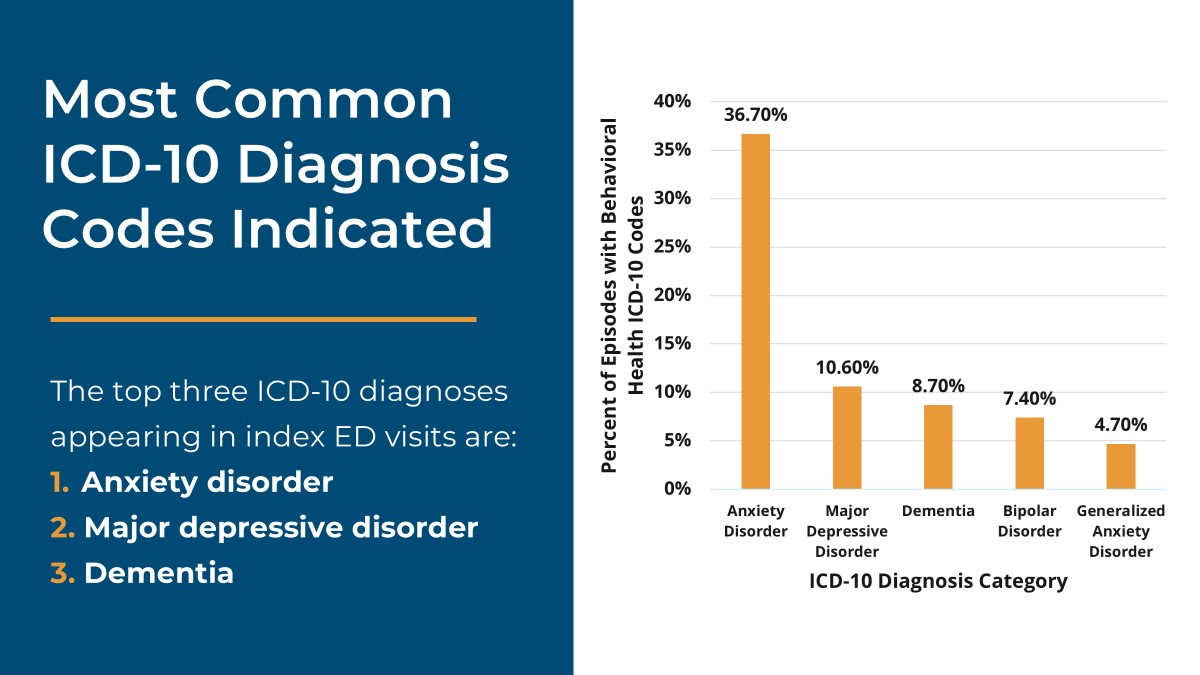
Stewart concluded by sharing aggregate and unblinded data on the prevalence of behavioral health as a co-diagnosis in MVC ED-based episodes, where behavioral health ICD-10 codes such as anxiety disorder, major depressive disorder, and dementia appear as co-diagnoses (Figure 4) in approximately 13% of index ED events. She also shared how those behavioral health rates differ by payer as well as condition and noted that 1 in 3 of ED patients who have a resulting inpatient admission have a behavioral health code noted as a comorbidity.

Figure 4. Most Common ICD-10 Diagnosis Codes Indicated

vertical bar graph: Most Common ICD-10 Diagnosis Codes Indicated - 1. anxiety 2. major depressive disorder 3. dementia 4. bipolar disorder 5. generalized anxiety disorder

After a networking lunch, attendees spent the afternoon participating in roundtable discussions and small group activities on two to three topics [SEE ROUNDTABLE MATERIALS]. During the session, attendees could either join three roundtable discussions or join one roundtable and one small group activity on system approaches to QI. At each table attendees learned about the work of the roundtable facilitator, asked questions, and discussed similar initiatives at their own organizations. In the system activity, MVC members were asked a series of questions about measuring system-level QI, and their responses will help inform MVC’s future work to support health systems across Michigan.

The meeting closed with a reflection of the day spent together, reminders about upcoming meetings, and opportunities for best practice sharing with other MVC members.

If you have questions about any of the topics discussed at MVC’s spring collaborative-wide meeting or are interested in following up for more details, contact the MVC Coordinating Center. MVC’s next collaborative-wide meeting will be in person on Fri., Oct. 10, 2025, in Livonia.


Off
View Post
MVC Announces Agenda, Speakers for Spring Collaborative-Wide Meeting

MVC Announces Agenda, Speakers for Spring Collaborative-Wide Meeting

The MVC Coordinating Center is excited to announce the agenda for its spring collaborative-wide meeting on Fri., May 9, 2025, from 10 a.m. – 3 p.m., at the H Hotel in Midland, MI. This meeting’s theme of “collaboration in action” reflects a focus on partnerships, collaborating to overcome barriers, and leveraging data to shape improvement projects. Those interested in attending MVC's spring collaborative-wide meeting can learn more and register here.

MVC Director Hari Nathan, MD, PhD, and Managing Director Mark Bradshaw, MSc, will kick off the day with Coordinating Center updates as well as announcements about the MVC Component of the Blue Cross Blue Shield of Michigan (BCBSM) Pay-for-Performance (P4P) Program. This will be followed by a new engagement awards ceremony and a presentation about statewide trends in quality improvement efforts, both presented by MVC Engagement Manager Jessica Souva, MSN, RN, C-ONQS.

The meeting includes a mid-morning poster session with 11 presenters highlighting success stories and research across the broader CQI portfolio. This is one of several opportunities to network with peers.

MVC Associate Program Manager Jana Stewart, MS, MPH, will present on recent MVC partnerships with other CQIs that drove site-level quality improvement initiatives. In addition to providing updates on these partnerships and their respective progress, Stewart will also share new priorities related to cardiac rehabilitation, preoperative testing, and ED-based episodes of care. This presentation will include unblinded data on key measures for all three topics, including new data on mental health comorbidities among patients treated in the emergency department. Attendees will be able to benchmark their site’s performance on a variety of metrics and come away with ideas for site-level interventions to implement.

After lunch and open networking, the afternoon features 10 concurrent interactive roundtables covering a wide variety of topics. From collaboration across academic and system units, behavioral health, and data reporting topics to a variety of patient-centered initiatives and more, the roundtables offer something for everyone. Attendees will join between two and three 15-minute discussions as they rotate to different roundtable speaker presentations. One of these options includes a longer 30-minute fireside chat with Hari Nathan, MD, PhD, on system-level approaches to quality improvement.

New this year is an innovation station that will be available throughout the day. It will feature a variety of stations where attendees can interact, leave suggestions, and connect with peers. The day will conclude with closing remarks and next steps with Jana Stewart, MS, MPH.

The deadline to register for MVC’s spring collaborative-wide meeting is April 28. We look forward to seeing you there!


 

Off
View Post
Overcoming Non-Medical Drivers of Health: A Success Story at Marshfield Medical Center-Dickinson

Overcoming Non-Medical Drivers of Health: A Success Story at Marshfield Medical Center-Dickinson

In recent years, the pursuit of high-quality healthcare has pushed an increasing number of organizations to consider how tailored approaches can reduce variation in health outcomes, increase the value of care, and enhance patient experiences with the healthcare system. Reflecting this growing recognition, the Michigan Value Collaborative (MVC) surveyed its members in 2024 to better understand how members were identifying gaps in care and responding to non-medical drivers of health. With questions focused on data collection, strategic planning, and programming, MVC gleaned a wealth of impactful and innovative solutions already under way in hospitals across the state.

For the majority of the surveyed hospitals, the most common focus areas for programming were enhancing provider availabilitiy (i.e., telehealth, mobile units, and nontraditional clinic hours), improving access to reliable transportation, offering financial support, and providing translated materials. Although it is common for hospitals to have strategies in place in these areas, the specific approaches are often as varied as the communities they serve.

At Marshfield Medical Center-Dickinson, for example, one way they approach gaps in preventative care within the community is through dental care programming. Recent studies have established a clear link between oral health and overall health, underscoring the importance of proper dental hygiene as a preventive measure against serious health complications. According to the Mayo Clinic, poor oral health can lead to significant conditions such as endocarditis, cardiovascular disease, pregnancy complications, and pneumonia. Consequently, effective dental hygiene education and preventive care can provide substantial health benefits that extend well beyond oral health alone.

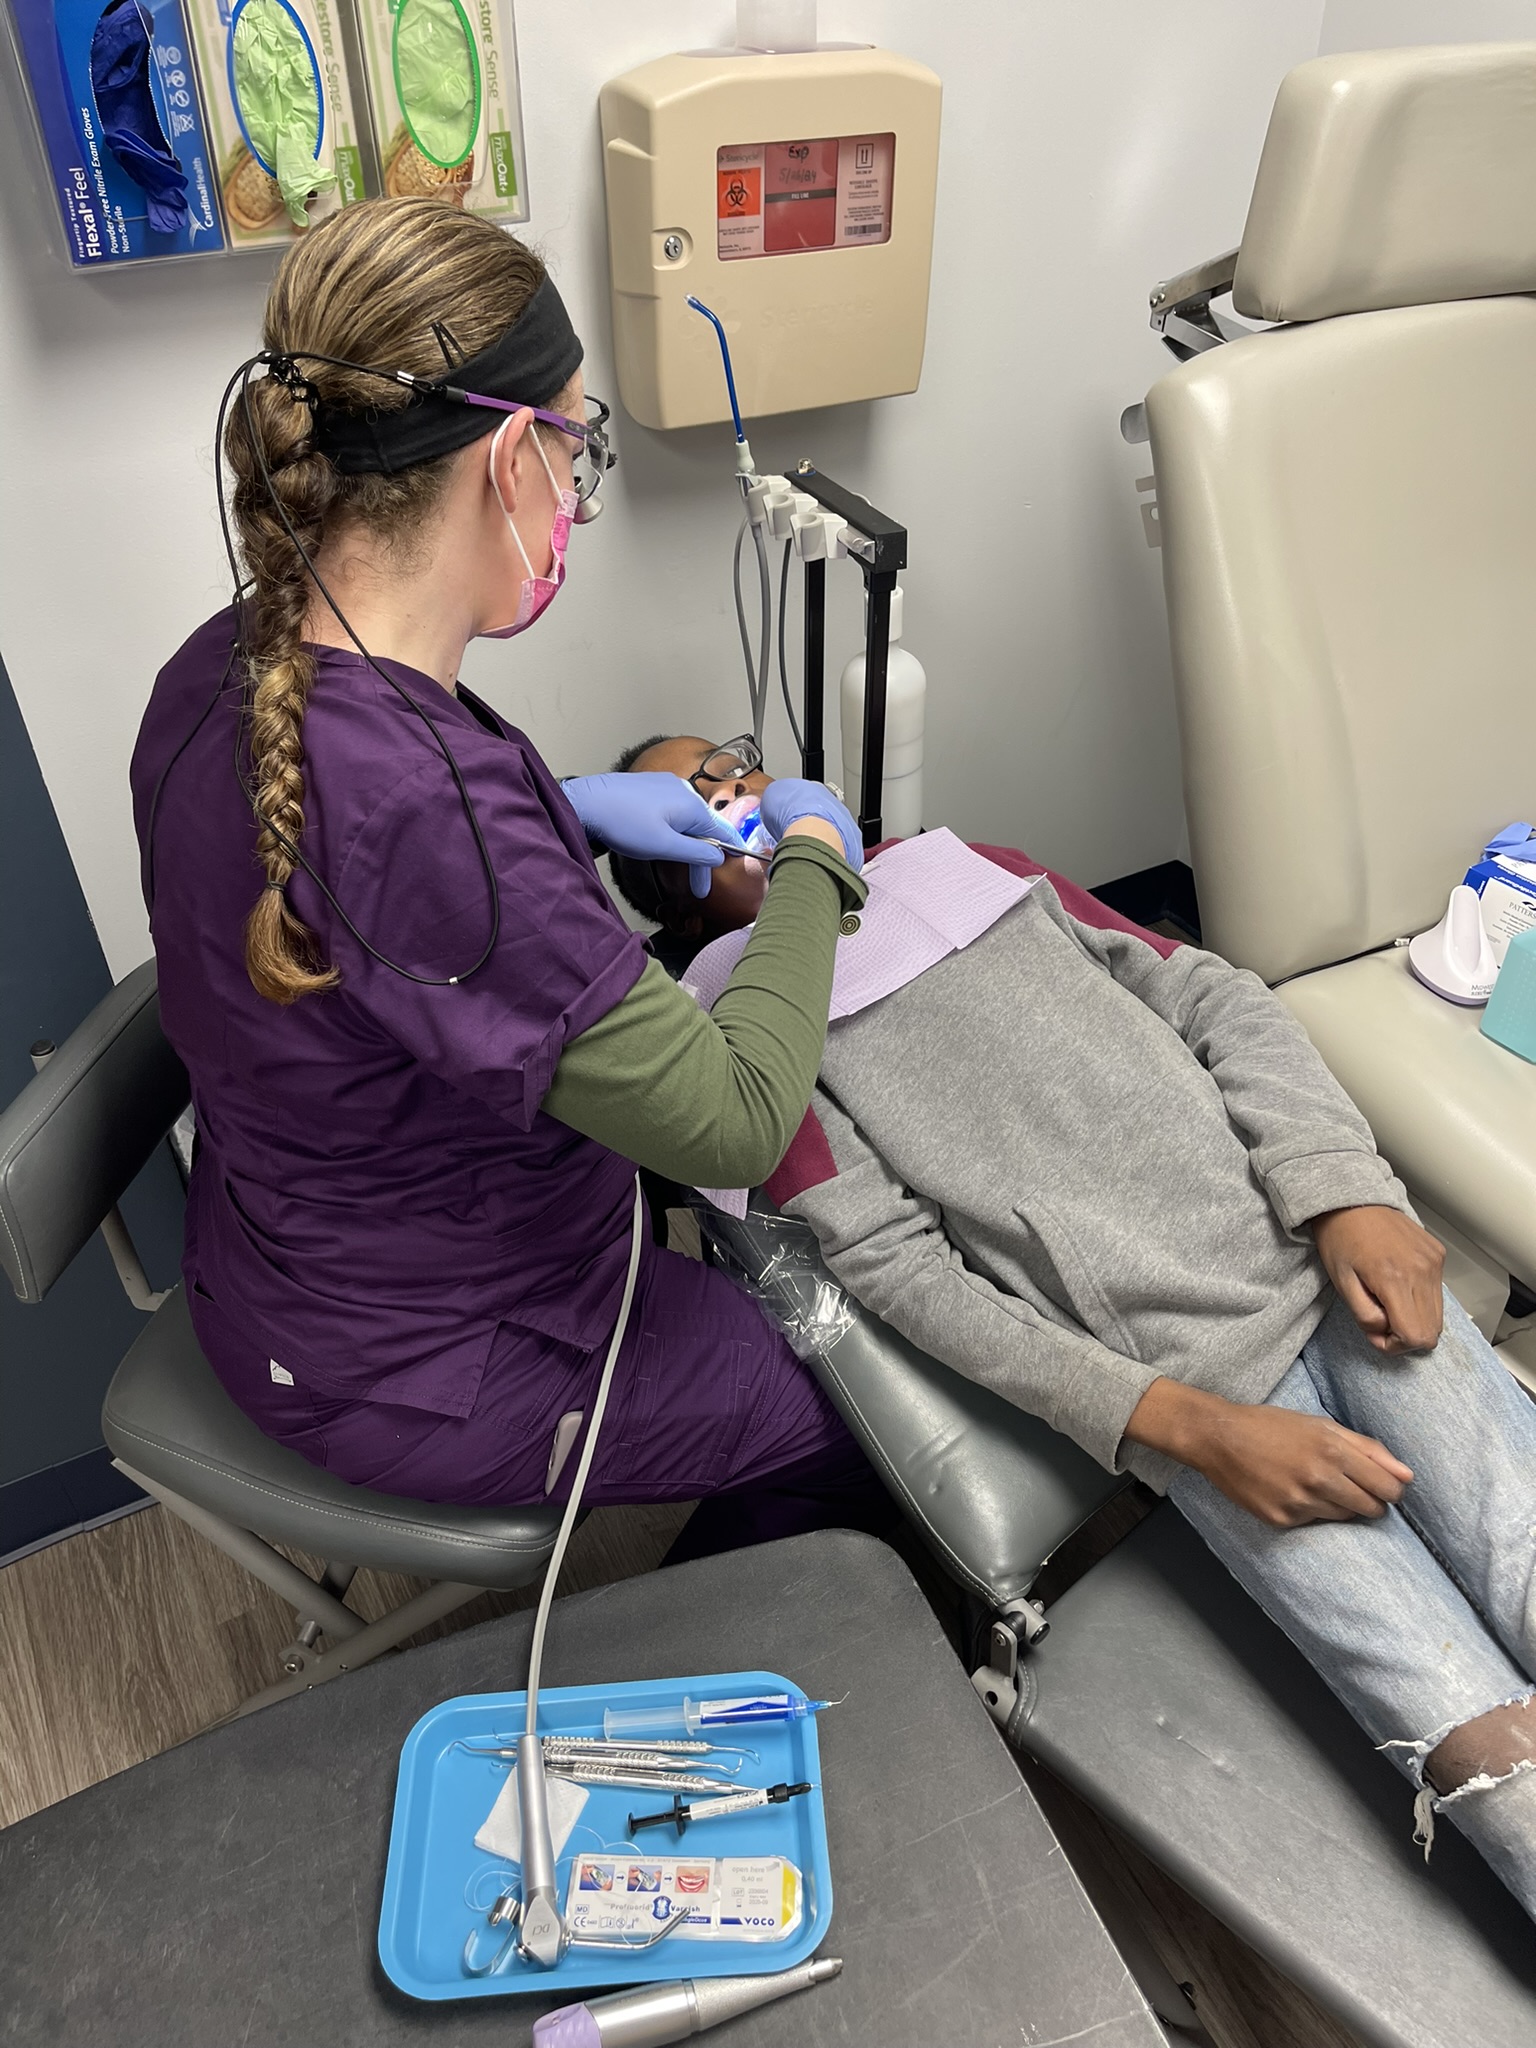
Recognizing the multifaceted benefits of accessible oral healthcare, Marshfield has partnered with Smiles on Wheels to offer monthly dental services—including cleanings, sealants, and fluoride treatments—at their primary care clinic, regardless of insurance. This initiative has been especially beneficial for young children and parents who face financial challenges related to transportation, and helps Marshfield to more effectively ensure high-value care for all patients. It also helps families avoid future costs associated with more complex treatments that may result from a lack of preventive care. The program has received positive feedback from the patient population, with many community members expressing their gratitude for the support it provides.

Figure 1. Smiles on Wheels provides dental care services to Marshfield Medical Center-Dickinson patients during wellness care visits.

photo: Smiles on Wheels providing dental care services to Marshfield Medical Center-Dickinson patient during wellness care visit

Photo courtesy of Marshfield Medical Center-Dickinson

Dr. Alexis Cirilli Whaley, MMC-D Pediatrician said, “We are fortunate to have Smiles on Wheels offering dental care to our local children, particularly for those families needing additional support due to economic stressors. The initiative allows for increased access to dental treatment, conveniently scheduled during wellness care visits."

By partnering with Smiles on Wheels, Marshfield Medical Center-Dickinson is leveraging existing resources to create a meaningful impact. This collaboration optimizes the use of available assets and showcases an effective strategy that harnesses the strengths of community partners. Stories like that of Marshfield Medical Center-Dickinson highlight the power of community partnerships in bridging known gaps in care and making a significant difference.

If your hospital or organization has an initiative they would like to share, please contact the Coordinating Center at Michigan-Value-Collaborative@med.umich.edu – we would love to hear from you.

Off
View Post
MVC Welcomes Its Newest Senior Analyst, Steven Ellinger

MVC Welcomes Its Newest Senior Analyst, Steven Ellinger

I’m ecstatic to join the MVC team as a senior analyst and bring my passion for healthcare analytics to the table! I am joining the team with over a decade of experience in healthcare analytics, pricing adjudication, reimbursement analysis, and provider network management. I’ve spearheaded projects to optimize network-level claims reporting and streamline data processes in every role. My background in economics and finance from Western Michigan University has helped me develop a strong analytical mindset, which I’ve applied in roles at Michigan Medicine-Sparrow, IBM Watson Health, McLaren Health Plan, and beyond. Healthcare large data manipulation is a passion of mine and you’ll see me smile each time a question is asked, as I am eager to find the answer.

Prior to joining the MVC team, I enjoyed five years as a pricing analyst at University of Michigan Health Plan (formerly Physicians Health Plan). I was responsible for establishing and maintaining provider fee schedules, ensuring competitive and compliant compensation across a vast provider and facility network. My expertise in SQL, Microsoft Excel, claims processing, and financial reporting have been instrumental in automating adjudication processes and enhancing financial forecasting. I also worked closely with provider relations, contract negotiations, and system configuration, making data-driven decisions to enhance efficiency.

Outside of work, my two kids under five keep me very busy with not a lot of free time. When I do find that time, I love staying active—backpacking, running marathons, and formerly teaching swing dancing. You will find me every year at the Indycar Detroit Grand Prix, at the paddock, pit line, or at the box suites, wishing the race was back at Belle Isle. I am thrilled to be on board and look forward to working with MVC’s members to make an impact on healthcare.

5

MVC Coordinating Center Looking Back at 2021 and Forward to 2022

Let me begin the first MVC blog of 2022 by wishing you all a very happy new year on behalf of everyone at the MVC Coordinating Center. I’ve started my last two recaps with this line and ended with the hope of seeing you all in-person sometime soon. Since we still haven’t quite managed to get together in-person yet, I’d like to reiterate our thanks and gratitude to each of our collaborative members and those hospitals and physician organizations across the country who have continued to work tirelessly against the ongoing pandemic.

The MVC team has remained remote throughout 2021 and not only have we mastered the Zoom mute button, but we’ve continued to provide support to help MVC’s 100 hospital members and 40 physician organizations during this time.  In 2021, the MVC team held two virtual collaborative wide meetings, conducted 62 tailored registry webinars, undertook 58 virtual site visits, delivered 56 custom analytic requests, facilitated 34 workgroups, disseminated 21 push reports, and held five virtual regional networking events. As a result of this activity, the collaborative has welcomed 13 new hospital members to the collaborative.

In addition to these efforts, the MVC Coordinating Center has continued to adhere to our commitment to provide hospitals and POs with increased access to meaningful benchmarked performance data. In May of this year, MVC’s data portfolio grew with the addition of Michigan Medicaid data, and this was recently refreshed in early October. The data range for this data source currently covers 1/1/2015 – 9/30/2020, reflecting index admissions from 1/1/2015 – 6/30/2020. MVC Medicaid claims (Fee-for-Service and Managed Care) account for a total of 319,140 episodes (19.4% of all MVC episodes) and cover 256,889 beneficiaries. Overall, MVC data sources now comprise over 80% of Michigan’s insured population.

We look forward to continuing this growth in 2022 as we strive to improve the health of Michigan through sustainable high-value healthcare. There are a number of new developments in the pipeline for the coming year and I excited to be able to share some of these with you.

New Hospital Push Reports

A number of new reports will be added to MVC’s suite of reporting in 2022, focusing on topics such as COVID-19, Pneumonia, and Health Equity. The Coordinating Center will work closely with members, the wider CQI community, and other stakeholders to ensure the introduction of other new and novel approaches to sharing our data.

New Physician Organization Reporting

Driven by continued communication with members, the Coordinating Center disseminated its first PO-specific report focused on joint replacement towards the end of last year and has identified two new conditions of interest for future development (gastroenterology and hysterectomy). The Coordinating Center will also be working closely with PO members to inform the development of new metrics for the MVC online registry.

Increased Custom Analytics

Over the last year, the MVC team has devoted effort to raising awareness of MVC’s custom analytic offering to members. This has proved successful, with 56 custom projects undertaken for members in 2021 alone. This support will continue into 2022 – if you are interested in learning more, please contact the MVC Coordinating Center (michiganvaluecollaborative@gmail.com).

Emphasizing Equity in Healthcare

Most measures of overall health are worse in the US compared to any other developed country. The state of Michigan in particular ranks poorly in measures of population health, including tobacco use and the inter-related issues of inactivity, poor nutrition, and obesity. The relationship between these poor health behaviors and social determinants of health are closely interlinked and represent a huge opportunity to improve health and healthcare outcomes for targeted patients. In the coming year, MVC will be exploring how best to use its data and engagement platforms to emphasize equity in healthcare.

Collaborative Wide Meetings

The MVC team will continue to hold two flagship semi-annual collaborative wide meetings. These will take place on Friday, May 13th and on Friday, October 28th. The MVC team will also be holding five regional networking events throughout the year and plans to pilot a new ‘Northern Meeting’ in Summer 2022. More details to come.

New MVC Workgroups

The Coordinating Center’s suite of peer-to-peer virtual workgroups will continue to provide a highly accessible online platform for hospital and PO leaders to come together, collaborate, and share practices. In addition to MVC’s Chronic Disease Management, Sepsis, Joint, and Diabetes workgroups, two new groups will be added in 2022. This includes forums focused on ‘Health Equity’ and ‘Health in Action’.

As these activities and other planned developments come to fruition, we will be sure to share updates with you through our various engagement platforms. If you have any questions in the meantime, please do not hesitate to contact the MVC Coordinating Center at michiganvaluecollaborative@gmail.com. Happy New Year, and we look forward to a great 2022 together.

1
View Post
MVC Semi-Annual Meeting May 2021 – Virtual Meeting Recap

MVC Semi-Annual Meeting May 2021 – Virtual Meeting Recap

The Michigan Value Collaborative (MVC) held its first virtual semi-annual meeting of 2021 on Friday, May 7th. A total of 221 leaders from a variety of healthcare disciplines attended Friday’s virtual meeting, representing 74 different hospitals and 30 physician organizations (POs) from across the State of Michigan. These participants came together to hear about the planned adjustments to the MVC Component of the BCBSM P4P Program for Program Years (PY) 2022/23 and to discuss variations in transitions of care and ED utilization practices across Michigan.

MVC’s Director, Dr. Hari Nathan, started Friday’s meeting with an update from the MVC Coordinating Center, welcoming the eleven new hospital members who have joined the collaborative since the turn of the year and highlighting recent improvements to MVC data sources and push reporting. This included the “soft launch” of Medicaid data. MVC has now added Medicaid data to our data portfolio, meaning that MVC data sources now comprise over 80% of Michigan’s insured population. The Coordinating Center is in the final stages of validation and will have this new data source live for use by members in the coming months.

Dr. Mike Thompson, MVC’s Co-Director, then shared information on the MVC Component of the BCBSM P4P Program with attendees. An overview of PY20 was first provided, showing that participants earned an average of six points during this program year, an increase of around one point from the 2019 program year average. In an effort to continually improve the MVC Component, the Coordinating Center has introduced two methodological changes for the next two-year cycle (PY22 & PY23). Dr. Thompson walked through each of these changes, which include placing “Improvement” and “Achievement” on the same scoring scale, and introducing a new qualitative questionnaire for earning bonus points. The MVC Coordinating Center will be sharing further information on these changes and disseminating service line selection reports for the next program cycle with members in early June. Two dedicated P4P webinars will also be held around this time to assist members with selection.

Attention was then turned to looking at transition variations in Michigan hospitals, highlighting payment and ED utilization differences across MVC members, as well as the top reasons for readmission within the collaborative. To expand on this further, we were joined by guest speakers from the hospital, physician organization, and CQI setting to share their insights and learning. Dr. Robert Nolan and Michael Getty from Spectrum Health Lakeland were the first guest speakers of the day, discussing their organization’s efforts to reduce the cost of ED utilization and readmission rates. This highlighted the importance of real time data visuals, integrating documentation tools with best practices, and ensuring an effective longitudinal plan of care that is blended into natural work flows to enable physician buy-in. Dr. Nolan and Mike Getty were also able to spotlight the use of MVC data in these efforts, a custom option available to all MVC members.

Representing Professional Medical Corporation (PMC) and the Consortium of Independent Physician Associations (CIPA), Dr. Kyle Enger then shared how both entities have worked to promote appropriate emergency care in recent years. Again, this emphasized the importance of monthly data report cards to provide physicians with actionable data to guide activity, as well as the need to continue promoting urgent care as a viable alternative in certain situations. Our last guest speaker of the day was Dr. Keith Kocher, Director of the Michigan Emergency Department Improvement Collaborative (MEDIC). As well as providing a brief overview of the purpose of MEDIC and sharing some vital statistics relating to ED utilization across the US, Dr. Kocher discussed how best to approach the “ED readmission problem” and how local solutions can be used to minimize its impact.

To conclude Friday’s meeting, MVC’s Site Engagement Coordinator, Jeff Jameel, provided a synopsis of the day and highlighted key upcoming activities. The slides from Friday’s meeting are available here and a recording of the meeting can also be viewed here. If you have any questions on anything that was discussed at Friday’s semi-annual or are interested in finding out more about MVC’s offering, please reach out to the MVC Coordinating Center (michiganvaluecollaborative@gmail.com.) In the meantime, we look forward to seeing you all in-person again soon.

2

MVC Launches New Physician Organization Reports

The goal of the Michigan Value Collaborative (MVC) is to improve the health of Michigan through sustainable high-value healthcare. The primary focus at inception in 2013 was the development of hospital based metrics to improve patient outcomes, reduce healthcare costs, and encourage hospitals to collaborate in best practice sharing. With the knowledge that hospitals are not the healthcare entity capable of such changes, MVC invited Physician Organizations (POs) to join the collaborative towards the end of 2018.

To date, PO members have been able to see hospital level data for their attributed facilities. This has proved helpful for our PO members but we have heard consistent feedback that being able to view metrics that display a PO’s specific attributed patient population would be welcome. This value added request was appreciated by MVC, and so the Coordinating Center began a collaboration with representatives from the Blue Cross Blue Shield of Michigan (BCBSM) Physician Group Incentive Program (PGIP) to develop new PO patient specific metrics. MVC has also engaged other parties in the development of these new metrics, including the Michigan Data Collaborative (MDC) and hearing directly from our PO members.

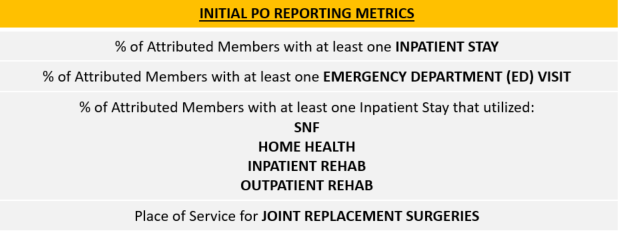
As a result of this collaboration, the first MVC PO population level report, containing data for both BCBSM PPO Commercial (Comm) and BCBSM Medicare Advantage (MA) between 1/1/19 and 12/31/19, was sent out to all 40 MVC PO members on Tuesday, April 20, 2021. The report contains data on health care utilization and allows POs to benchmark themselves against all MVC participating physician organizations for the metrics listed in Table 1.

Table 1. Initial PO Reporting Metrics

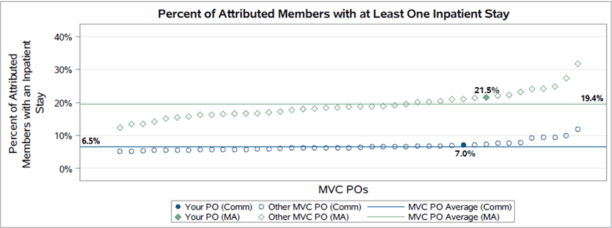
Each metric was stratified by payer to account for differences in patient populations, as well as to serve as a proxy for age stratification (Figure 1).

Figure 1. Sample PO Metric: Percent of Attributed Members with at Least One Inpatient Stay

As engagement with our PO members builds, and further feedback and requests are processed, MVC plans to continue to build on the metrics highlighted in this report. As the most recent reports are at a population level, the Coordinating Center intends to delve further into the metrics for more granular level detail.

If you are interested in sharing feedback about the PO reports, have any specific analytic requests, and/or would like more information about the Michigan Value Collaborative,  please reach out to the Coordinating Center at michiganvaluecollaborative@gmail.com.


2

Long COVID-19, Just One Aftereffect of COVID-19

With continued COVID-19 surges occurring worldwide despite the availability of a number of variations of vaccines, some patients continue to experience what is now being dubbed as “Long COVID-19” or “Post COVID-19 Syndrome”. Symptoms that are commonly experienced include a persistent cough, dyspnea, chest and/or joint pain, neuralgia, and headaches. These symptoms can last up to 12 weeks and in some cases, even longer. The more people that develop long COVID-19, the greater the strain on the healthcare system and need for appropriate diagnosis and treatment options.

A recent paper by A.V. Raveendran from January 2021 proposed diagnostic criteria to help confirm a diagnosis of long COVID-19. Depending on clinical symptomology, duration criteria and the presence or absence of a positive swab or antibodies, a long COVID-19 diagnosis can be categorized as confirmed, probable, possible or doubtful. Having an appropriate diagnosis will allow the practitioner to prescribe the relevant treatment plan.

In the United Kingdom, where the number of people exhibiting long COVID-19 continues to increase, a guideline has been developed by the National Institute for Health and Care Excellence to provide recommendations to help identify, assess, and manage the effects. As more evidence is collected, the plan is to update the document on a continuous basis to maintain its validity. The guideline takes into consideration clinical symptomology, duration criteria, and the presence or absence of a positive SARS-Cov-2 test. It also provides guidelines for suggested referrals, and a plan of care with follow-up and monitoring.

While the guideline manual has many useful suggestions, there are a number of gaps where further detailed information will be needed.  As new information is discovered, the goal is to include comprehensive reviews of symptomology, and pathology of the disease process and a better understanding of the variation in impact. Simultaneously, there needs to be an increase in rehabilitation and community resources to allow for individualized evidenced based care for those suffering from the debilitating effects of long COVID-19.

The Michigan Value Collaborative continues to assess data related to COVID-19 and will be sharing a dedicated COVID-19 push report with members in the coming months. If you would like access to the MVC registry, please request it here or via email michiganvaluecollaborative@gmail.com

0

Cardiac Rehab Stakeholder Meeting Motivates Improvements in Care

On Monday, March 22, 2021, a “stakeholder meeting” was hosted by the Michigan Value Collaborative (MVC) Coordinating Center with multiple key players in cardiac rehabilitation (CR) from around Michigan. As MVC has written about before, cardiac rehabilitation is a highly valuable but underutilized service and is the focus of one of MVC’s ongoing value coalition campaigns. The goal of the stakeholder meetings is to bring together key constituents to work towards solving the problem of underutilization. Attendees included managers of cardiac and pulmonary rehab facilities, quality improvement leaders and executives from  several MVC members, our payer partners from Blue Cross Blue Shield of Michigan, and representatives from the Michigan Society for Thoracic and Cardiovascular Surgeons (MSTCVS), the Michigan Society for Cardiovascular and Pulmonary Rehab (MSCVPR), and the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2).

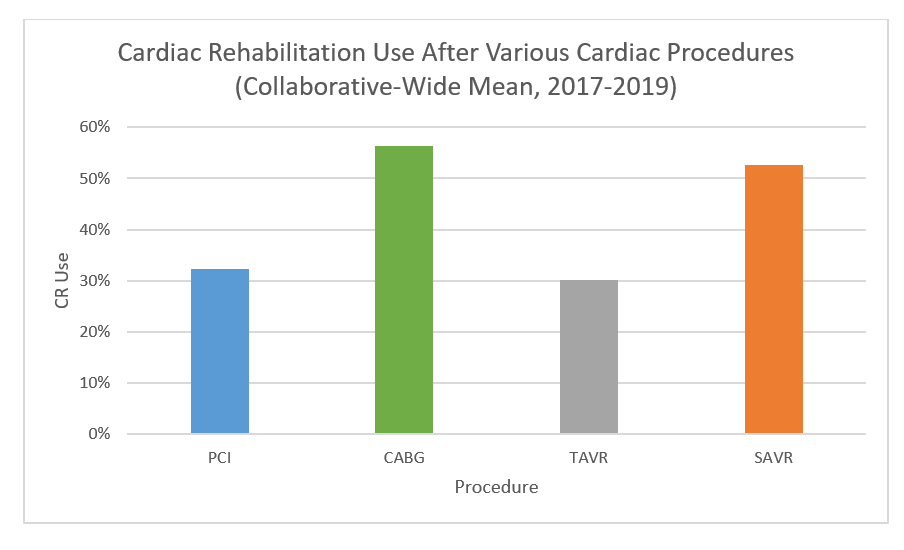
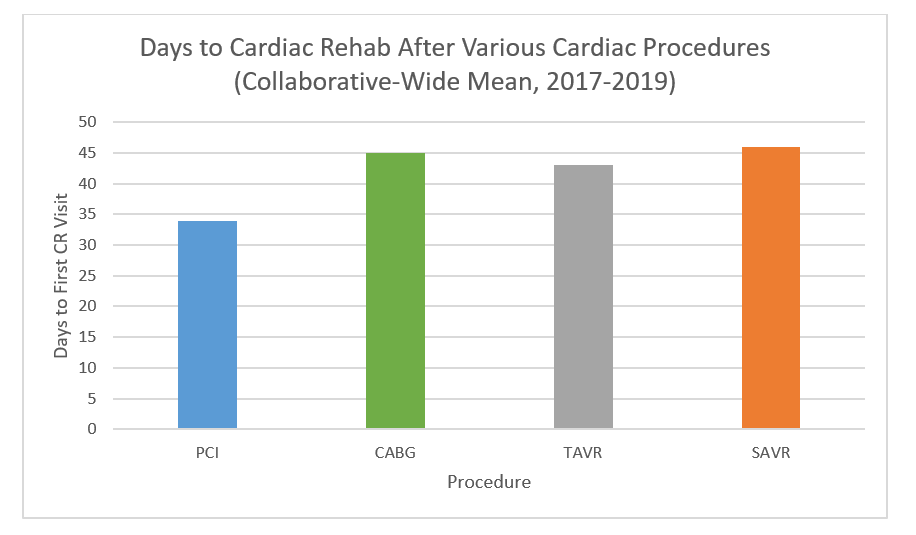
The stakeholder meeting occurred the week after MVC distributed new Master Cardiac Rehab reports, which detail several metrics on cardiac rehabilitation after percutaneous coronary intervention (PCI), coronary artery bypass grafting (CABG), transcatheter aortic valve replacement (TAVR), and surgical aortic valve replacement (SAVR) procedures. The collaborative-wide average cardiac rehab utilization varied by procedure: 52.6% for SAVR, 30.1% for TAVR, 56.3% for CABG, and 32.3% for PCI (see Figure 1). The mean days to first cardiac rehab visit also varied by procedure: 46 days for SAVR patients, 43 days for TAVR patients, 45 days for CABG patients, and 34 days for PCI patients (see Figure 2).

Figure 1

Figure 2

The Master Cardiac Rehab reports were also distributed by our partners at MSTCVS and BMC2. The aim is to increase awareness of hospital-level CR utilization and encourage as many players as possible (cardiologists, cardiac surgeons, cardiac rehab staff, quality improvement staff, and executive leadership) to work together to increase CR utilization at every hospital. These reports were well-received at the March 22nd stakeholder meeting, with one attendee emphasizing that the information contained in the reports was “the envy of other states,” speaking to the utility of MVC data and the success of BCBSM Value Partnerships. Attendees also provided excellent suggestions for improvement which will be taken into account during the next report refresh later this year.

The data is distributed, and the stakeholder meeting is over, but the value coalition campaign is just getting started.  There’s still a lot of work to do in order to equitably increase cardiac rehabilitation use in our state, including studying barriers to entry, exploring the intricacies of benefit design, and making various operational changes hospital by hospital, health system by health system. Nevertheless, that Monday afternoon showed that sometimes, when you have the right people around the same (virtual) table, everyone can walk away connected, motivated, and ready to carry out their respective roles to improve health care.

The next cardiac rehab stakeholder meeting is scheduled for Monday, June 28, 2021 from 4:00-5:00pm. If you have an interest in joining this group, or if you have not received your Master Cardiac Rehab report, please email michiganvaluecollaborative@gmail.com.