Off
View Post
February Workgroups Highlight Hybrid Cardiac Rehab Delivery and Patient Journey Mapping

February Workgroups Highlight Hybrid Cardiac Rehab Delivery and Patient Journey Mapping

In February, MVC hosted two virtual workgroup presentations – the first focused on hybrid cardiac rehab program delivery and the second a health in action session focused on patient journey mapping. The MVC Coordinating Center hosts workgroup presentations twice per month with topics rotating between post-discharge follow-up, sepsis, cardiac rehabilitation, rural health, preoperative testing, and heath in action (ad hoc focused topics). Each month, the MVC Coordinating Center publishes key highlights from the past month’s presentations to support practice sharing across the state.

Cardiac Rehab Workgroup February 11, 2025

MVC’s first cardiac rehab workgroup of 2025 featured a presentation by Dr. Steven Keteyian, PhD, Director of Cardiac Rehabilitation/Preventive Cardiology at Henry Ford Health System. The presentation focused on the development and implementation of a non-traditional hybrid model of care delivery.

During the COVID-19 pandemic many healthcare facilities had to transition to virtual platforms to continue providing essential medical care to patients. Henry Ford Health’s cardiac rehabilitation programs, like many other services, pivoted to meet the needs of patients by establishing an evidence-based hybrid delivery model.

Dr. Keteyian emphasized that cardiac rehabilitation is more than just physical exercise. It is a comprehensive health improvement plan containing several core components (Figure 1) such as nutritional counseling, psychosocial management, weight management and body composition, tobacco cessation counseling, and more. All of these components are combined to establish an individualized treatment plan for the patient.

Figure 1. AACVPR/AHA Cardiac Rehab Performance Measures
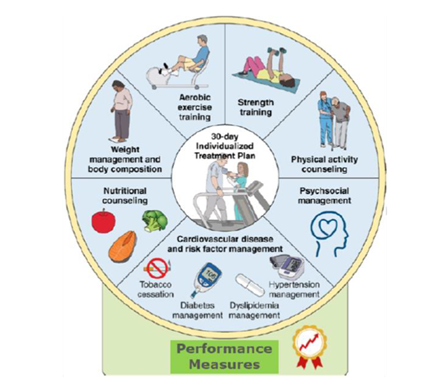
seven AACVPR/AHA Cardiac Rehab Performance Measures

Dr. Keteyian explained that their patients begin their program in-person to establish baseline assessments and a treatment plan. Once established, cardiac rehab patients have the option to participate virtually for remaining sessions or return on-site depending on their preferences and the need to assess them in-person. Dr. Keteyian noted several factors that drive the use of hybrid cardiac rehab such as patient needs (returning to work, family care responsibilities, travel distance/transportation limitations), limited resources within the health system for a fully on-site program, and limited patient availability during the on-site hours of operation.

To be eligible for participation in cardiac rehabilitation, patients need to have a qualifying event such as acute coronary syndrome (ACS), heart valve repair/replacement (TAVR), cardiac transplant, or stable heart failure (with less than 35% ejection fraction). Henry Ford uses MVC data to track the percent of eligible patients enrolled in cardiac rehab within 90 days, and compares rates across different qualifying events (e.g., AMI, CHF, TAVR, etc.) to see where cardiac rehab is being underutilized compared to averages for the state and Centers for Medicare & Medicaid Services (CMS). The Henry Ford team began incorporating virtual cardiac rehab delivery as a strategy to increase enrollment and attendance among eligible patients.

Dr. Keteyian also discussed some common questions and concerns he hears when discussing hybrid program delivery, such as needed equipment, patient safety, and program efficacy. He shared information from the iAttend randomized control trial that Henry Ford Health participated in from 2019 – 2024, which tracked cardiac patient demographic data, eligibility, participation, and outcomes for hybrid and facility-based cardiac rehab programming (Keteyian, 2024). Data showed that none of the hybrid participants were required to go on-site due to clinical concerns, no virtual visits required physician intervention, and there were no mechanical falls requiring medical attention indicated in either group. A second randomized trial, HF-ACTION, tracked 2,331 heart failure (HFrEF) patients and found that hospitalizations during or within 3 hours after exercise occurred for 2% of the hybrid participants versus 3% for on-site patients. The mortality rate for patients in both study groups was very low (approximately 0.4%) indicating safety was not an issue. Though the data did show hybrid patients not progressing as quickly through the program as on-site patients, this lag became a teaching moment for cardiac rehab staff and an opportunity for improvement.

Attendance for both programs was comparable, and patient outcomes were statistically similar with patients showing improvement in desired performance measures such as peak oxygen uptake, exercise duration, and walking distance (Keteyian, 2024). Staff burden as a result of running a hybrid program was a key concern. To mitigate the potential for burnout, Henry Ford Health aligned services and materials with how the on-site cardiac rehab program is managed.

Dr. Keteyian closed by pointing out that the number of patients who qualify for cardiac rehabilitation each year outnumbers the available spaces in on-site programs throughout the United States. Even if these programs were running at full capacity, only ~ 50% of the eligible patients could be seen. He argued, therefore, that there is a significant need to increase the number of best-practice cardiac rehabilitation programs and the methods available to patients to access them (Balady, 2011).

MVC Cardiac Rehab Workgroup Feb. 11, 2025

Health in Action Workgroup February 27, 2025

MVC’s health in action workgroup this month included a presentation and workshop on patient journey mapping with MVC’s Associate Program Manager Jana Stewart, MS, MPH. This workshop was a continuation from the October 2024 collaborative-wide meeting’s post-discharge follow-up breakout session. Following the fall workshop, MVC collated member feedback on common barriers to follow-up for heart failure patients, which Stewart summarized as part of the February workgroup presentation. Participants of the workgroup also engaged in polls and two guided breakout discussions aimed at improving outcomes for patients with congestive heart failure.

Using Patient Journey Mapping to Improve Patient Outcomes

Stewart explained that the purpose of patient journey mapping is to understand the patient’s experience and pain points as they manage their health. This practice looks at service delivery by providers as well as the patients’ steps beyond healthcare appointments, providing useful data for root cause analyses and developing effective interventions. Stewart shared examples of patient journey maps that described what a patient might do, think, and feel as they seek healthcare services as well as maps illustrating a hospital’s workflow for enrolling eligible cardiac rehab patients. By generating maps from both the patient and provider perspective, one can identify opportunities for efficiencies and necessary interventions points.

Figure 2. Sample Patient Journey Map for Enrollment in Cardiac Rehab Following a Heart Procedure
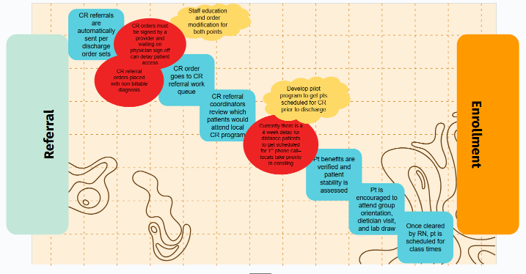
Sample Patient Journey Map for Enrollment in Cardiac Rehab Following a Heart Procedure

In the first of two breakout sessions, attendees provided feedback and edits on a patient journey map for cardiac rehab enrollment following heart surgery. Attendees reimagined how the patient experience and hospital steps might change for a heart failure patient. Some interventions that were discussed included staff reviewing discharge lists frequently to keep track of patients, having a nurse navigator to help patients prepare for cardiac rehab, and keeping a consistent treatment plan between inpatient and outpatient providers.

Patient Experience – Key Barriers That Impact Patients

Stewart also outlined some key considerations regarding a patient’s experience and some of the barriers that may impact their ability to manage their health. One key barrier discussed was the limitations of our brain's processing capacity and the ways in which mental fatigue make it harder to remember and cope with information. Famed environmental psychologist George Miller once posited that a typical person is able to process and store to memory 5 – 9 pieces of information at a time. When a person is mentally fatigued (e.g., sleep deprived, burned out, cognitively burdened), their ability to understand and store information decreases.

Stewart cited a research study on patient recall after specialty care visits (Laws et al, 2018), which found only half of patients remembered the recommendations they received from a provider, and only about half of what they remembered was recalled correctly. This can have a significant impact on how well a patient follows their treatment plan after they are discharged or sent home. These recall difficulties are further exacerbated in patients with more extensive mental fatigue, such as those experiencing minority stress, unmet social needs, older age, lower health literacy, and other factors. Stewart argued that a patient’s current mental capacity and literacy are key considerations when journey mapping, as they are often the culprit for not following treatment plans.

One strategy Stewart shared that can reduce cognitive burden is the use of storytelling. Used as a framework for delivering information, stories allow patients to better understand and remember details. This can be done through patient story videos as well as case studies that demonstrate the progression of an illness or treatment plan. During one of the breakout discussions, participants brainstormed how they might use storytelling to communicate information to CHF patients. Ideas included establishing private community groups on social media for patients to share their stories, patient story pamphlets, and videos to play on hospital televisions or linked in patient discharge materials.

The feedback and ideas generated by participants during February's health in action workgroup will be used to draft resources for MVC member sites. MVC plans to bring those draft materials to future meetings or workgroups to gather feedback prior to dissemination. Participants also received a copy of the patient journey mapping template so they can utilize this approach at their site(s).

MVC Health in Action Workgroup Feb. 27, 2025

If you are interested in pursuing a healthcare improvement initiative, MVC has a robust registry of claims data that can be utilized as well as site specialists who can help facilitate connections with peers doing similar work. Please reach out to us here if you would like to learn more about MVC data or engagement offerings.

Off
View Post
MVC Publishes its 2024 QECP Annual Report as a Qualified Entity

MVC Publishes its 2024 QECP Annual Report as a Qualified Entity

Recently, the MVC Coordinating Center published its annual Qualified Entity Certification Program (QECP) public report for 2024. This report [PDF] was published in a new QECP section on the MVC website’s Data/Registry page and is an annual requirement for MVC as a qualified entity with the Centers for Medicare & Medicaid Services (CMS). This was MVC’s third public QECP report and continued to provide unidentified aggregated data about Michigan hospital performance on two measures: rates of 30-day rehospitalizations following start of home health care, and rates of outpatient follow-up received after hospitalization for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD).

All measures in the report were created using data from MVC claims-based episodes of care initialized by inpatient hospitalizations or surgeries between Jan. 1, 2018 and Dec. 31, 2022. Claims were incorporated from all MVC payer sources, including Medicare Fee-for-Service, Blue Cross Blue Shield of Michigan, Blue Care Network, and Michigan Medicaid.

The reported overall rate of 30-day unplanned rehospitalizations after the start of post-acute home health care among episodes beginning at MVC hospitals in Michigan was 11.6% for 2018-2022. Risk-adjusted rates by index hospital ranged from 2.5% to 17.2%. By home health provider, risk-adjusted rates ranged from 0.0% to 23.5% (Figure 1). Patients whose episode of care began with an index event for endocarditis, COPD, CHF, or percutaneous coronary intervention (PCI) were more likely than patients with other index conditions to experience an unplanned rehospitalization in the 30 days after they started home health care. Patients with a joint replacement episode of care were least likely to have an unplanned rehospitalization following the start of home health care.

Figure 1. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by Home Health Provider

Results for the outpatient follow-up metrics remained similar to findings from previous annual reports. Across episodes of care for index events in 2018-2022 at the 106 MVC hospitals in Michigan, the unadjusted rate of patients receiving outpatient follow-up within 7 days after hospitalization for CHF was 44% (Figure 2). Following index hospitalizations for COPD, 36% of patients received outpatient follow-up within 7 days (Figure 3). For both conditions, there was wide variation across hospitals in Michigan in their 7-day follow-up rates after hospitalization, with rates ranging between less than 10% to over 60%. Rates of follow-up were fairly steady over time.

Figure 2. 7-Day Follow-Up After CHF Hospitalization by MVC Hospital

Figure 3. 7-Day Follow-Up After COPD Hospitalization by MVC Hospital

For more information and the entire set of findings we invite you to read the full 2024 report, available here.

QE certification status allows MVC to provide hospital members with additional data from Medicare Fee-for-Service (FFS) claims at a level of granularity which would not otherwise be available under standard CMS data use agreements. Reports located under the “QE Medicare” icon on the MVC registry allow hospital registry users to see unsuppressed Medicare data including case counts <11 as well as utilization rates and average payments based on case counts <11. In addition, on any QE Medicare registry report, members can click on specific data points to load a list of all episodes underlying that data point. From that episode list it is possible to view drilldown information on individual episodes to learn more about the claims and price-standardized payments comprising that episode.

Members may contact the MVC Coordinating Center by emailing Michigan-Value-Collaborative@med.umich.edu to learn more about data available through MVC’s QECP reports and to receive the forms necessary to gain access on the registry.

Off
View Post
Refreshed Hospital-Level, ED-Based Episode Push Reports Coming Soon to Members

Refreshed Hospital-Level, ED-Based Episode Push Reports Coming Soon to Members

The MVC Coordinating Center will soon distribute refreshed hospital-level versions of its push report utilizing emergency department-based episodes (“ED-based episodes”). MVC generated separate versions for acute care hospitals and Critical Access Hospitals (CAHs) with tailored comparison groups. In addition to reflecting more recent data across all included payers, these refreshed hospital-level reports differ from prior versions due to the addition of three high-volume ED conditions and the incorporation of Michigan Medicaid claims.

Each page of the report is dedicated to a specific condition with the same metrics throughout, such as risk-adjusted, price-standardized 30-day total episode spending, inpatient admission rates, and rates of post-ED utilization. Reports feature each hospital’s own attributed ED-based episode data for eight high-volume ED conditions: abdominal pain, cellulitis, chest pain (nonspecific), congestive heart failure (CHF), chronic obstructive pulmonary disease (COPD), diabetes with long-term complications (including renal, eye, neurological, or circulatory), diabetes with short-term complications (including ketoacidosis, hyperosmolarity, or coma), and urinary tract infection (UTI). The three new conditions included in this year’s refresh include diabetes with long-term complications, diabetes with short-term complications, and UTI.

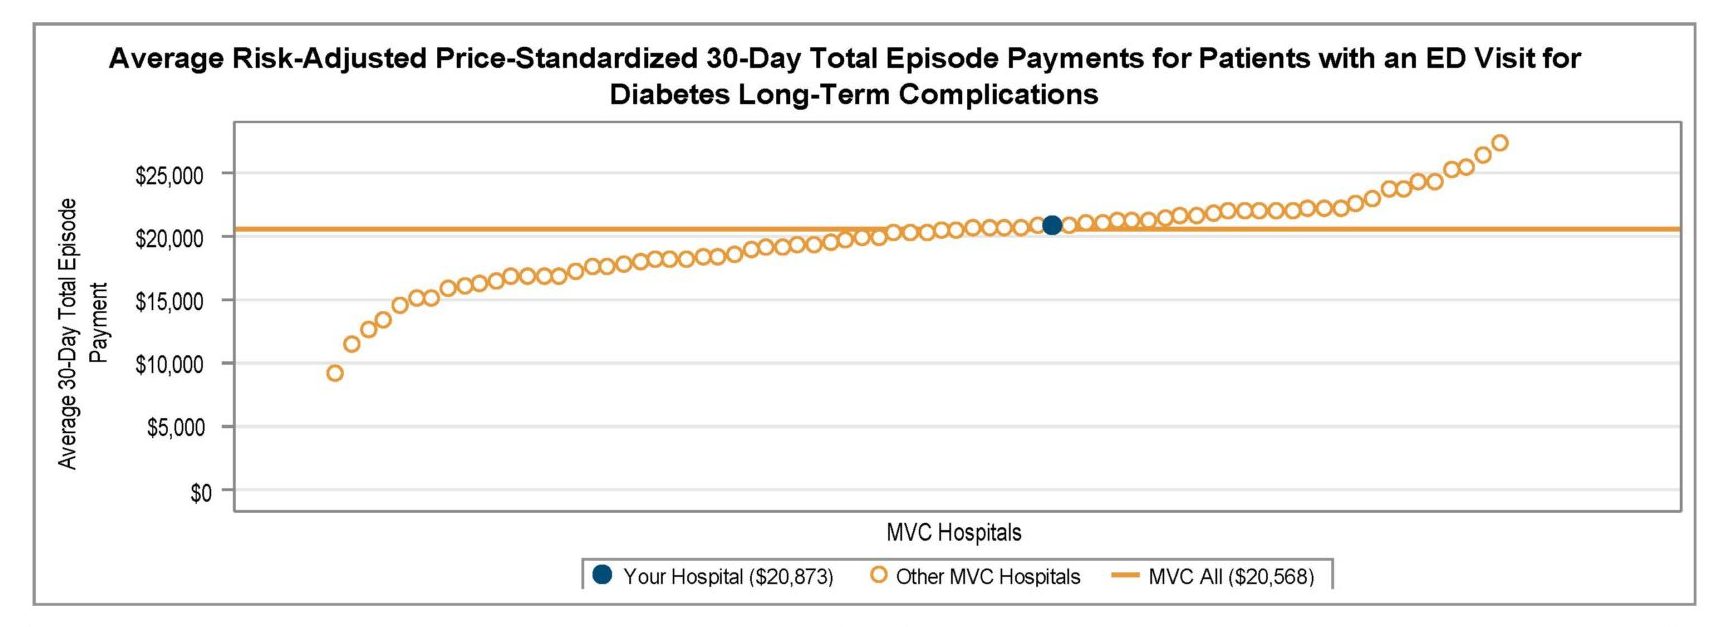
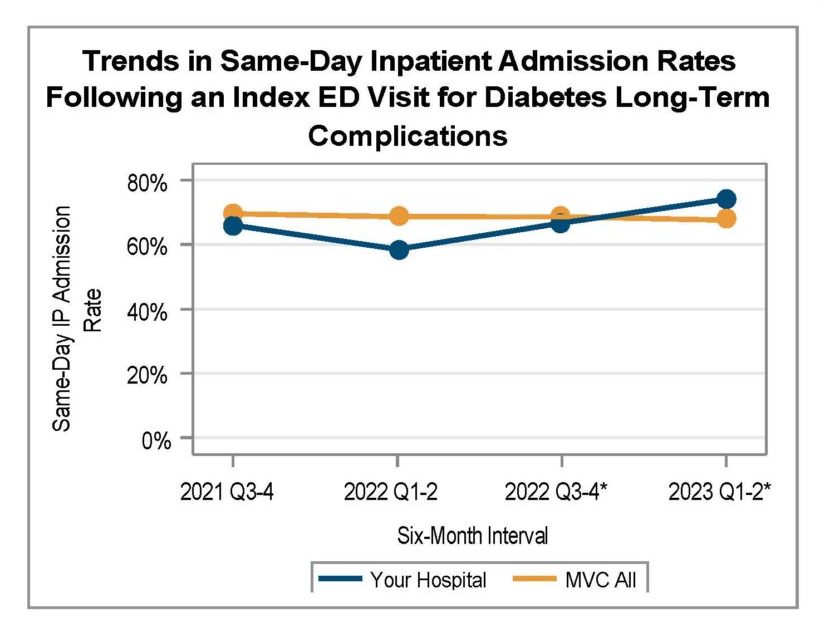
Among general acute care hospitals receiving a report, the average risk-adjusted, price-standardized 30-day total episode payment (Figure 1) for the reported conditions is highest for diabetes with long-term complications ($20,568), CHF ED-based episodes ($17,245), diabetes with short-term complications ($12,087), and COPD ED-based episodes ($10,289). The collaborative-wide average is lowest for chest pain ($3,111) and abdominal pain ($3,123) ED-based episodes. Within each condition, MVC 30-day total episode payments are consistently higher for episodes in which the patient had a same-day inpatient admission compared to episodes in which the patient did not have an inpatient stay beginning on the date of their ED visit. With that information in mind, hospital members can also use their individualized reports to track their same-day inpatient admission rate at six-month intervals using trend graphs for each included ED-based condition (Figure 2).

Figure 1.

Figure 2.

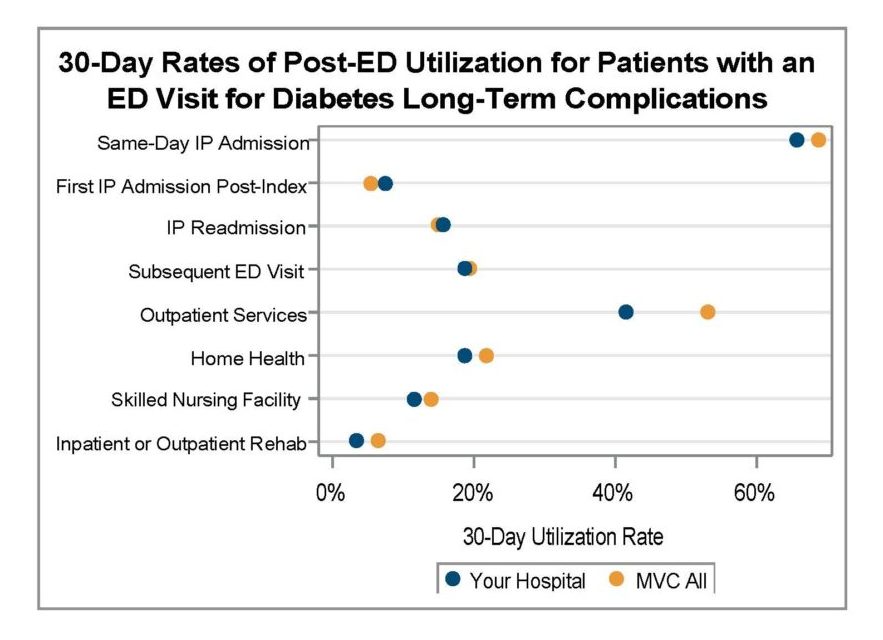
A key goal for these ED-based episode reports is to provide insight into healthcare utilization following index ED visits. Therefore, reports continue to include a dot plot (Figure 3) comparing patient post-ED utilization at a member hospital against their peer comparison group. Dot plots provide information on what percent of episodes had a same-day inpatient admission, what percent did not have a same-day inpatient admission but did see the patient admitted in the 1 to 30 days following the index ED visit, and the percent of patients who had two or more inpatient admissions (thus, at least one readmission) during the episode of care. Also provided are rates of subsequent ED visits, receipt of outpatient services, home health, skilled nursing facility care, and inpatient or outpatient rehab.

Figure 3.

These ED-based episodes are built using MVC’s most recent medical claims data from Medicare FFS, Blue Cross Blue Shield of Michigan PPO Commercial and Medicare Advantage plans, Blue Care Network HMO Commercial and Medicare Advantage plans, and Michigan Medicaid.

ED-based episodes utilize MVC’s newest episode of care data structure, which was developed last year in collaboration with the Michigan Emergency Department Improvement Collaborative (MEDIC), a BCBSM-funded Collaborative Quality Initiative with the goal of improving care and patient outcomes in Michigan emergency departments. MVC and MEDIC team members worked closely to develop 30-day episodes of care initialized by a patient’s visit to the ED and including all claims-documented care received in the 30 days following a patient’s index ED visit.

Please share your feedback with the MVC team if certain report measures are helpful or if you wish to see additional ED-based episode reporting for certain conditions and metrics. MVC is now also accepting custom report requests using its new ED-based data. Contact MVC to learn more.

Off
View Post
MVC’s Refreshed Common Conditions Report Coming to Hospital Members Soon

MVC’s Refreshed Common Conditions Report Coming to Hospital Members Soon

MVC members will receive their next batch of updated push reports in the coming days with a refreshed version of MVC’s common conditions report. These reports provide insight into episodes of care for eight medical and surgical conditions that are commonly a focus for quality improvement efforts at MVC hospitals: acute myocardial infarction (AMI), chronic obstructive pulmonary disease (COPD), colectomy (non-cancer), congestive heart failure (CHF), coronary artery bypass graft (CABG), total knee and hip (joint) replacement, pneumonia, and spine surgery. MVC’s general acute care hospital and Critical Access Hospital (CAH) members will receive tailored versions of the report, with each group receiving benchmark data specific to their own category of hospitals.

Although the metrics provided vary by condition and case count, report pages generally focus on 30-day total episode payments, readmission rates, common reasons for readmissions, and post-acute care utilization. MVC price standardizes total episode payments to Medicare FFS amounts so that comparisons can be made across hospitals and over time. Payments are risk adjusted for patient age, gender, payer, comorbidities, and high or low prior healthcare utilization/payments.

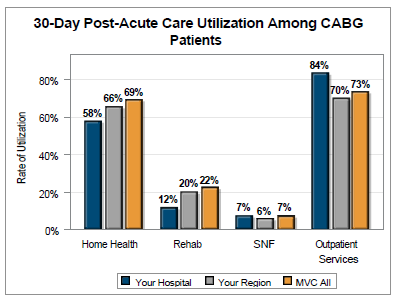
Post-acute care utilization benchmarking for each of the eight medical and surgical conditions includes graphs displaying the percentage of each hospital’s patients who used home health care, inpatient/outpatient rehab, skilled nursing facility care, outpatient services, or emergency department care in the 30 days following their index hospitalization or surgery. Across the collaborative, reports show high use of 30-day home health care and outpatient services for these common conditions. For patients initiating their episode of care at a general acute care hospital within the collaborative, the home health care utilization rate was highest following CABG (69%) and joint replacement (50%).

Patients with a CABG episode were also high utilizers of outpatient services in the 30 days post-index (Figure 1), with a 73% average utilization rate. Patients with episodes for CHF (58%) and AMI (53%) were also high utilizers of outpatient services. Across conditions, use of outpatient services in the 30 days post-index was generally higher among episodes originating at CAHs than among episodes originating at general acute care hospitals.

Figure 1.

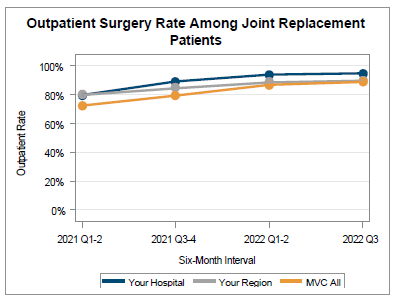
Reports also assess the setting of care for joint replacements and spine surgeries. For total knee and hip replacements, MVC data shows that the percent of joint replacements performed in an outpatient setting at general acute care hospitals across Michigan continued to rise from January 2021 through September 2022 (Figure 2).

Figure 2.

The patient population in these reports comprises adult patients who had surgery or an inpatient hospitalization at an MVC-participating hospital between January 2021 and September 2022. Measures are based on 30-day inpatient and surgical-based episodes of care data, incorporating paid claims from Blue Cross Blue Shield of Michigan and Blue Care Network Commercial and Medicare Advantage plans as well as paid claims from Medicare Fee-for-Service. Episodes meeting any of the following criteria were excluded from calculations: patients transferred to another acute care hospital or to hospice, patients who died during their index stay, and patients with a primary diagnosis of COVID-19 received in an inpatient setting at any point during their 30-day episode.

We hope our collaborative participants find these reports valuable, and as always, we welcome MVC members to contact MVC with any questions or analytic requests.

Off
View Post
MVC’s 2023 Chronic Disease Management Follow-Up Reports Coming to Members Soon

MVC’s 2023 Chronic Disease Management Follow-Up Reports Coming to Members Soon

MVC will soon distribute the 2023 version of its chronic disease management follow-up reports to members. This refreshed version provides summary data on patients eligible for follow-up care after discharge from hospitalizations for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD).

MVC defines timely follow-up care as receipt of an in-person or remote outpatient follow-up visit within 30 days of hospital discharge to home or home health care and before any readmission, emergency department (ED) visit, or procedure. Patients admitted to a skilled nursing facility, long-term acute care hospital, or inpatient rehab within the 30-day episode were excluded. MVC’s follow-up analyses was performed using claims-based episodes of care with index hospital admissions between 7/1/2019 and 06/30/2022 for Blue Cross Blue Shield of Michigan (BCBSM) PPO Commercial and Medicare Advantage (MA), Blue Care Network (BCN) HMO Commercial and MA, and Medicare Fee-for-Service insurance plans. For each of the two chronic conditions included in the report, hospitals with at least 11 episodes per year for a given condition received that condition-specific data.

The report offers a comparison of demographic characteristics for CHF and COPD patients who received a follow-up visit within 30 days versus those who did not receive follow-up. Demographic characteristics tabulated for each condition include the percent of patients living in “at-risk” or “distressed” Zip codes as defined by the Economic Innovation Group’s Distressed Community Index, patients’ average number of comorbidities, the mean age of patients, and the distribution of race and ethnicity. MVC recently refined and expanded its reporting of race and ethnicity identities, and these updates were reflected in the report. Patients are grouped as Hispanic if their insurance provider categorized their combined race/ethnicity as Hispanic or their ethnicity as Hispanic. Additionally, MVC no longer combines smaller groups and discontinued its use of the terms “other” and “unknown.”

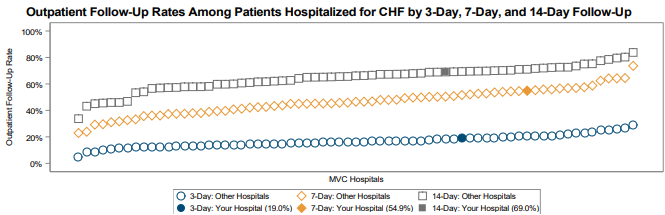
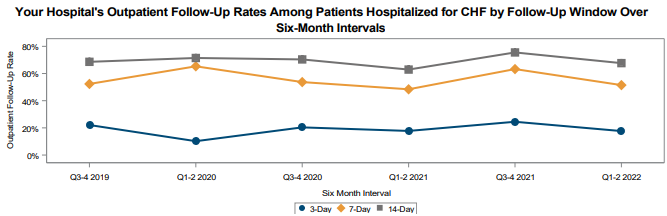
On the first page provided for each condition, hospital follow-up rates are provided for three windows of time compared to those at other MVC hospitals (Figure 1), as well as trends over time for each follow-up window (Figure 2). For CHF, follow-up rates are provided in 3-day, 7-day, and 14-day time windows. For COPD, follow-up rates are provided in 7-, 14-, and 30-day time windows.

Figure 1.

Figure 2.

The second page of condition-specific feedback includes a summary of average 30-day risk-adjusted, price-standardized total episode payments by follow-up status compared to statewide and regional averages. Among general acute care hospitals included in the analysis, the statewide total average payment for CHF episodes was $17,235 for patients who received follow-up and $20,069 for those who did not; for COPD episodes, the statewide average payments were $13,815 among those with follow-up and $16,056 among those without. In reports generated for Critical Access Hospitals (CAHs), payments were compared to averages across all MVC CAH members. Rates of 30-day follow-up were also compared by payers across the same groups.

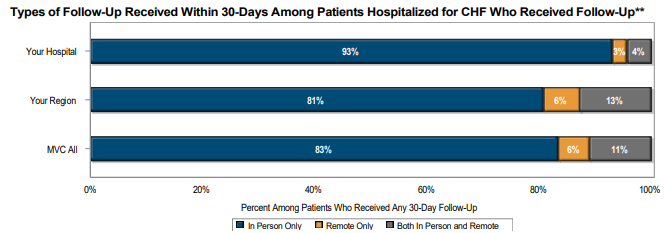
The final figure (Figure 3) in the report for each condition is a summary of follow-up method among those who received any follow-up care. Patients who received follow-up were categorized as having received only in-person follow-up visit(s), only remote follow-up, or both in-person and remote follow-up. MVC found that more than 80% of CHF and COPD patients statewide exclusively received in-person follow-up after a hospitalization.

Figure 3.

If you have any questions or feedback about this report, please contact the MVC Coordinating Center.

Off
View Post
MVC Publishes its 2023 QECP Public Report as a Qualified Entity

MVC Publishes its 2023 QECP Public Report as a Qualified Entity

Today the MVC Coordinating Center published its annual Qualified Entity Certification Program (QECP) public report for 2023. One of the requirements of being a qualified entity (QE) with the Centers for Medicare & Medicaid Services (CMS) through the QECP is the annual dissemination of a public report created using claims data. MVC shared its first public report last year, making the 2023 report the second iteration.

As with last year, the 2023 MVC QECP Public Report provides unidentified aggregated data on Michigan hospitals for two measures: rates of 30-day rehospitalizations following start of home health care, and rates of outpatient follow-up received after hospitalization for congestive heart failure (CHF) or chronic obstructive pulmonary disease (COPD). Both measures were created using data from episodes of care initialized by inpatient hospitalizations or surgeries between 1/1/2018 and 12/31/2021.

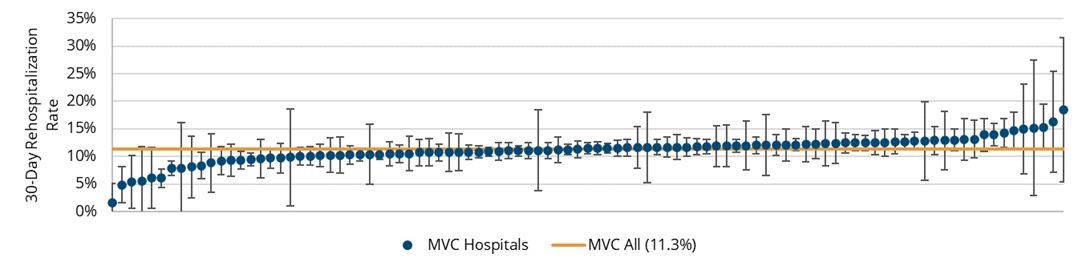
For 2018-2021, the overall rate of 30-day unplanned rehospitalizations from home health among MVC member hospitals in Michigan was 11.3%. Risk-adjusted rates by index hospital ranged from 1.6% to 18.5% (Figure 1). By home health provider, risk-adjusted rates ranged from 2.0% to 23.6%. Patients whose episode of care began with an index event for endocarditis, COPD, CHF, or percutaneous coronary intervention (PCI) were more likely than patients with other index conditions to experience an unplanned rehospitalization in the 30 days after they started home health care.

Figure 1. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by MVC Hospital

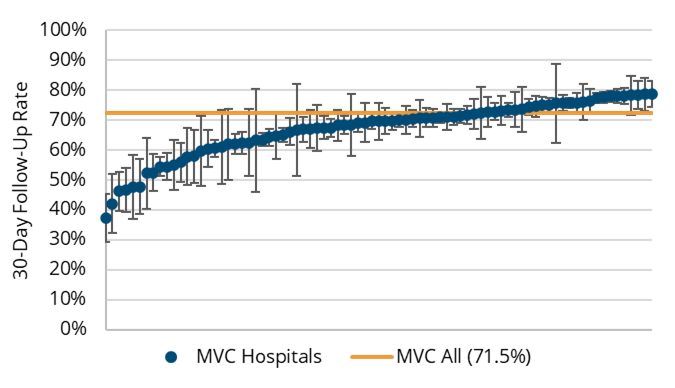
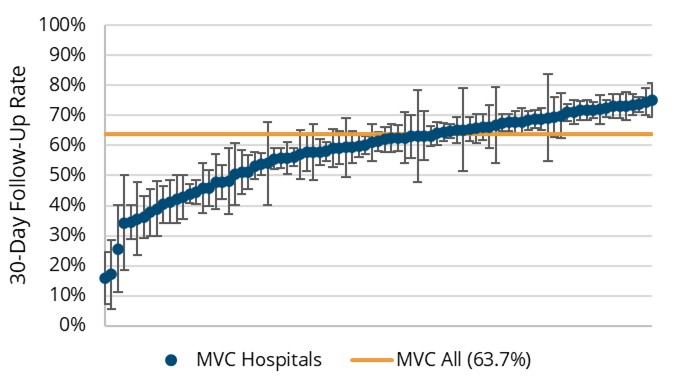
Across the 102 MVC hospitals with attributed episodes of care data underlying this report, the unadjusted rates of patients receiving outpatient follow-up were higher following index hospitalizations for CHF than for COPD (Figures 2 and 3). This was the case whether follow-up occurred three days (16% vs. 13%), seven days (45% vs. 37%), 14 days (63% vs. 54%), or 30 days (72% vs. 64%) after discharge.

Figure 2. 30-Day Follow-Up After CHF by MVC Hospital

Figure 3. 30-Day Follow-Up After COPD by MVC Hospital

For more information and the entire set of findings, we invite you to read the full report, which is available online to any member of the public on the MVC Resources page or directly here.

QE certification status allows MVC to provide hospital members with additional data from Medicare Fee-for-Service (FFS) claims at a level of granularity not otherwise available under standard CMS data use agreements. Reports located under the “QE Data” icon on the MVC registry allow hospital registry users to see unsuppressed data that include case counts <11 as well as utilization rates and average payments based on case counts <11. In addition, on any QE Data registry report, members can click on specific data points to load a list of all episodes underlying that data point. From that episode list, it is possible to view drill-down information on any individual listed episode to learn more about the claims and price-standardized payments comprising that episode.

MVC members representing one or more MVC-participating hospitals can send an email to Michigan-Value-Collaborative@med.umich.edu to learn more about data available through MVC’s QECP reports and to receive the forms necessary to gain access to those registry reports.

Off

The Michigan Value Collaborative’s Refreshed Cardiac Service Line Reports

The Michigan Value Collaborative (MVC) Coordinating Center disseminated it’s long-running customized cardiac service line report to hospital and physician organization (PO) members on February 23, 2021. These reports provide hospital-level information on congestive heart failure (CHF), acute myocardial infarction (AMI), and coronary artery bypass graft (CABG) conditions. To receive information on any one of these conditions, a hospital must have at least 20 cases per year over the three-year reporting period (1/1/17 – 12/31/19).

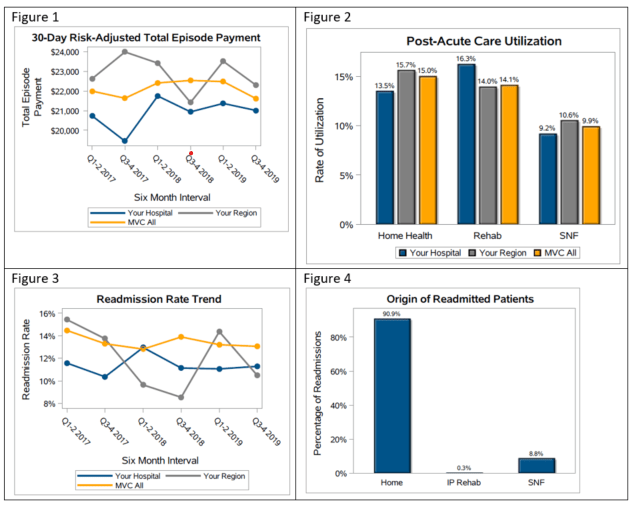
Since the last iteration of the cardiac service line report sent in June 2020, the Coordinating Center has defined four distinct regions within Michigan, allowing members to make regional comparisons. These comparisons have been incorporated into the 30-day risk-adjusted total episode payment trend chart, the post-acute care utilization bar graph, and the 30-day readmission rate trend chart of the reports as shown in the following AMI figures for a fictional institution, Hospital A.

Acute Myocardial Infarction Figures. Hospital A

Figure 1 shows the 30-day risk-adjusted total episode payments broken up into six-month intervals, illustrating that episode payments for AMI hold steady across the Collaborative at an average of around $22,000. Please note that as with all MVC reports, this represents price standardized dollars to allow for fair comparisons between hospitals. The price standardized dollars can be thought of as a measure of utilization as opposed to true dollar amounts.

Figure 2 displays the percentage of AMI patients who utilized home health (15.0% across MVC), rehab (14.1% across MVC), or skilled nursing facilities (9.9% across MVC). Figure 3 illustrates that, between 2017 and 2019, approximately 14% of AMI patients were readmitted within 30 days. Finally, Figure 4 shows Hospital A that based on the most recent claim before a readmission occurred, 90.9% of readmitted patients were coming from home, 8.8% were coming from Skilled Nursing Facilities (SNF), and very few were coming from inpatient rehabilitation (0.3%). Hospitals can use this information to observe if they are an outlier in any of the categories and where they may have an opportunity to improve, to benchmark themselves against the MVC all and regional averages, and to notice trends in their performance

These combined-payer push reports are distributed twice a year, meaning the next iteration is likely to be sent out in the summer of 2021. In the meantime, single-payer information is always available on the MVC registry, allowing for continued monitoring of these metrics. Data is added every month for Blue Cross payers and quarterly for Medicare. Michigan Medicaid data will be live on the registry at the start of Q2 this year.

If you need registry access, if you have ideas on how these reports can be made more versatile, or if you are using these data for a quality improvement project at your institution, please contact michiganvaluecollaborative@gmail.com. Additionally, please reach out if you want further information in the way of custom analytics.

Off
View Post
Henry Ford Health System – Cardiac Rehab

Henry Ford Health System – Cardiac Rehab

At the most recent congestive heart failure MVC workgroup, Dr. Steven Keteyian, Section Head of the Cardiac Rehabilitation/Preventive Cardiology Unit at Henry Ford Medical Group, presented on exercise-based cardiac rehabilitation in patients with heart failure. Dr. Keteyian started out by discussing the importance of cardiac rehabilitation and adhering to a program in order to improve exercise tolerance and disease-specific outcomes. Exercise intolerance is measured and the information gathered can be used to stratify a patient’s future risk. If the measurement improves over time, Dr. Keteyian discussed the potential for a decrease in risk of death and re-hospitalization. This shows a tie to directly improving outcomes and symptoms in cardiac rehabilitation. Also, in the words of Dr. Keteyian, “functionally, the more they don’t do, the less they can do.”

Cardiac rehab is a Class I recommendation from The American College of Cardiology for all of the traditional cardiac disorders. Henry Ford has a 36-visit program that is anchored on exercise training. Between four and fifteen people are in each class and each person receives an individual treatment plan with a focus on bio-behavioral components. Six core components make up the program which include outcome assessments, supervised exercise, dietary/weight management, tobacco abuse, psychological support, and medication adherence. All participants participate in 30-minute behavioral education sessions which cover topics such as nutrition, dining out, proper exercise, medication compliance, and other relevant disease-management self-care activities. These same topics are also available on YouTube and can be found here, all of which are available for use in your cardiac rehab program. Currently, Henry Ford is working on bringing their time to enrollment after hospital discharge to less than 21 days and increasing adherence to the 36-visit program. The goal is to achieve a participation rate of 70% or more in cardiac rehab for Henry Ford’s patient population.

After discussing the program specifics at Henry Ford, Dr. Keteyian discussed the barriers that one may face in relation to participation in cardiac rehab. These barriers include:

  • Demographic
  • Difficulty contacting patient after hospitalization
  • Return to work demands
  • Transportation
  • Co-payment obligations
  • Dependent care responsibilities

Henry Ford is working at a system level in order to increase the percent of patients who gain access to cardiac rehab. This includes increasing the use of electronic medical record (EMR) driven automatic referrals, with an option for users to opt-out if necessary. Additionally, a member of the cardiac rehab team goes to the inpatient setting and talks to patients to establish a touchpoint before they leave the hospital. This five-minute conversation is all some patients need in order to see the importance and benefits of rehab. Lastly, Henry Ford is working to shorten the discharge to start time. Each day after discharge, the chance of getting patients started in rehab decreases by 1% for each day that passes. Henry Ford is working diligently in order to help decrease this risk.

In 2016, Henry Ford launched a hybrid home-based cardiac rehabilitation service. This includes some visits at the clinic and other virtual sessions. Previously being tied to a single visit at a time on their current streaming platform, Henry Ford will roll out a WebEx model in February 2021 that will allow up to six cardiac rehab appointments to occur at one time. This will provide more of a group setting. Currently, a randomized controlled trial is being done on center based cardiac rehab versus hybrid cardiac rehab. Improvements in fitness and the number of sessions attended are being assessed.

If you are interested in watching the entire workgroup, please click here.  If interested in any information about this workgroup, or other MVC workgroups please email michiganvaluecollaborative@gmail.com