
Off
View Post
MVC October Workgroup Highlights MVC Cardiac Rehab Push Report

MVC October Workgroup Highlights MVC Cardiac Rehab Push Report

In October, the Michigan Value Collaborative (MVC) hosted a cardiac rehab workgroup featuring MVC’s newly released cardiac rehabilitation (CR) push report. The MVC Coordinating Center hosts workgroup presentations once or twice per month, covering a variety of topics including cardiac rehab, post-discharge follow-up, rural health, preoperative testing, sepsis, and health in action. View the full MVC event calendar with registration links here.

Cardiac Rehab Workgroup: MVC’s Refreshed Cardiac Rehab Push Report 

Since 2019, MVC has prioritized cardiac rehab as a value coalition campaign providing members with focused workgroups, site visits, and data resources to support quality improvement. Since then, MVC has continuously offered multi-payer reporting and benchmarking on a variety of cardiac rehab focused measures, first by offering dedicated push reports refreshed twice each year, followed by the launch of multi-payer reports on the MVC registry and the incorporation of cardiac rehab measures in the MVC Component of the BCBSM Pay-for-Performance (P4P) Program.

MVC continued to update data for its members by refreshing cardiac rehab push reports in September (read September 2026 blog for report details). MVC shared a stand-alone cardiac rehab push report this year, whereas recent years incorporated these data within a larger process measures push report.

During this month’s cardiac rehab workgroup, MVC Associate Program Manager Jana Stewart, MPH, provided a report walkthrough to familiarize MVC members with its data and changes relative to prior versions. In addition to traditional measures of enrollment, the latest report included measures of adherence and completion, in alignment with AACVPR performance measures.

Stewart said this expanded approach highlighted important opportunities for quality improvement along the patient care journey, from initial referral and enrollment processes to downstream retention strategies and patient barriers to participation. The measures were defined as:

  • Enrollment: The percentage of eligible patients who attend at least one cardiac rehab session within 90 days (Main 5 patients) or 365 days (CHF patients) of hospital discharge
  • Adherence: The percentage of enrolled patients who completed at least 12 cardiac rehab sessions within 365 days of discharge
  • Completion: The percentage of enrolled patients who completed at least 36 cardiac rehab sessions within 365 days of discharge

Together, Stewart described how these measures can help hospitals and cardiac rehab partners identify where patients may be falling out of the care pathway, starting with initial referral and enrollment through continued program participation and completion. Stewart encouraged members to use the provided patient characteristics table (Figure 1) to assess differences in cardiac rehab outcomes between different patient groups as well as identify patient gaps driven by non-medical drivers of health. The report also provided hospital-level comparisons with statewide averages, allowing members to assess their performance relative to their peers.

Figure 1. Slide highlighting Table 1 patient characteristic data from September 2026 cardiac rehab push reports
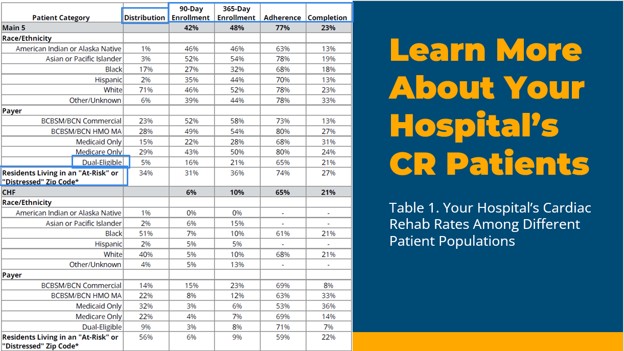
Table infographic titled “Your Hospital’s Cardiac Rehab Rates Among Different Patient Populations,” comparing cardiac rehabilitation metrics across patient categories. Rows cover race/ethnicity, payer, and residence in an at-risk ZIP code, with columns for distribution, 90-day enrollment, 365-day enrollment, adherence, and completion; blue table and orange-on-blue title panel emphasize population differences.

After reviewing the specifics of the updated push report, Stewart provided a brief look at statewide performance on each of these measures for the Main 5 and CHF patient populations. Overall, the findings demonstrated some progress in enrollment while highlighting opportunities to strengthen adherence and completion.

The Michigan Cardiac Rehab Network (MiCR) reported on cardiac rehab adherence and completion rates one year ago at its fall 2025 meeting, which compared participant adherence and completion rates across CR programs. This data presentation revealed a positive association between adherence rate and completion rate, with more consistently higher adherence rates observed amongst sites with higher completion rates (Figure 2). However, there were also sites with high adherence rates and low completion rates, suggesting a high adherence rate does not guarantee a high completion rate.

Figure 2. Cardiac Rehab Adherence and Completion Rates at Centers Across Michigan
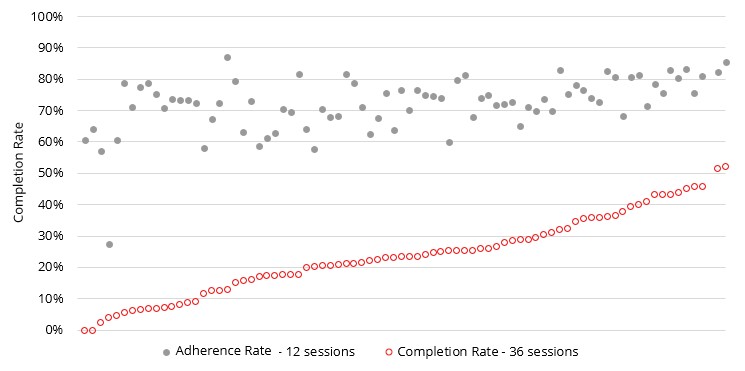
Scatter plot compares adherence rate across 12 sessions with completion rate across 36 sessions, using gray filled dots and red open circles against a 0%–100% completion-rate axis. Gray adherence values remain mostly 60%–85%, while red completion values rise steadily from 0% to about 52%, with labels and legend identifying each series.

Benchmarking Statewide Enrollment, Adherence, and Completion

The statewide cardiac rehab enrollment rate provided for Main 5 conditions was 34%, up from approximately 24% when focused improvement efforts began in 2019. However, this remains below the MiCR statewide goal of 40% and well below the Million Hearts goal of 70% for all eligible cardiac rehab participants.

For patients with CHF, the statewide enrollment rate of 6% also still falls short of MiCR’s 10% goal. Unlike enrollment for the Main 5 conditions, CHF enrollment rates have seen little improvement over the last few years. These findings reinforced the importance of an effective referral process, patient education, and continued engagement on the initiation of cardiac rehab for CHF patients. During the discussion, participants emphasized that heart failure patients may need additional time and repeated referrals before they initiate cardiac rehab.

Stewart emphasized how the additional measures of adherence and completion rates offered further insight into patient participation and full benefit from the program after enrollment. For the Main 5 conditions, the statewide adherence rate was 75% for the report's timeframe, meaning that approximately three-quarters of enrolled patients completed at least 12 sessions. However, the statewide completion rate among Main 5 patients was just 24%, reflecting the proportion of enrolled patients who completed 36 sessions within one year. For CHF, rates were similar to those of the Main 5 population—the statewide CHF adherence rate was 68%, while the completion rate was 24%.

Identifying Barriers and Supporting Patient Participation

During the workgroup discussion, members explored several factors that may affect enrollment, adherence, and completion. Common themes of the discussion included:

  • Provider endorsement and patient education: A clear recommendation from a physician can help patients understand why cardiac rehab is an important part of their recovery journey.
  • Financial and transportation barriers: Copays and the challenges of traveling to multiple appointments are known barriers for certain patient populations that may show up as low adherence or completion rates. Further analysis of cardiac rehab performance across payer and demographic groups could help better understand where additional support may be needed.
  • Flexible scheduling and delivery options: Flexible appointment times and hybrid cardiac rehab delivery models may help patients overcome scheduling and transportation challenges to improve adherence and completion.
  • Patient stories and testimonials: Participants discussed that patients may not feel ready to participate in cardiac rehab immediately after discharge, making continued outreach and education especially valuable. For patients with CHF in particular, the timing of referrals and reminders can be important. MiCR’s newest Heart-to-Heart initiative offers patient-story videos and testimonials that programs can use to help recruit patients for cardiac rehab, available on MiCR’s YouTube page.

These strategies offer starting points for local quality improvement. Stewart encouraged members to use their new cardiac rehab report findings to identify opportunities, engage relevant clinical and operational partners, and determine which approaches may be most appropriate for their patient populations. Members can also use the MVC registry to explore additional breakdowns of their data. For hospitals interested in more detailed analyses, MVC is available to discuss custom report opportunities.

MVC Cardiac Rehab Workgroup: Oct. 20, 2026

MVC welcomes workgroup presenters from across Michigan to share their expertise, success stories, initiatives, and solution-focused ideas with MVC members. Please reach out to the Coordinating Center by email if you are interested in being a workgroup presenter or submit a presentation proposal here.

Off
View Post
MVC Push Report Benchmarks Cardiac Rehab Enrollment, Adherence, and Completion Rates

MVC Push Report Benchmarks Cardiac Rehab Enrollment, Adherence, and Completion Rates

Since 2019, the MVC Coordinating Center has emphasized the value and importance of cardiac rehab with its member hospitals, offering claims-based data reporting, workgroup presentations by experts and peers, incentive-based metrics, and other resources to drive improvement. MVC distributed refreshed cardiac rehab push reports this month that continued to benchmark utilization among MVC member hospitals—reports that complement the multi-payer registry pages by incorporating adherence and completion metrics not available on the registry.

The primary motivator behind this work is the ever-growing cohort of patients with cardiovascular disease. Every year in the US, for example, nearly 6.7 million adults manage congestive heart failure (CHF) and more than one million patients undergo cardiac surgical procedures. Cardiac rehab can help patients regain strength and confidence, manage their cardiovascular health, and return to a healthier, more active life. It also has a dose-response relationship—attending more cardiac rehab sessions is associated with lower mortality and morbidity.

The evidence of benefit is clear in the literature, and patient stories affirm its impact and benefit.

“In a sense, the initial heart surgery saved my life the first time, but cardiac rehab saved it a second time,” shared John, a former cardiac rehab participant. “The rehab people performed a small miracle by restoring my self-confidence.”

Another patient, Belinda, shared that her cardiac rehab care at Henry Ford Hospital in Detroit helped her to improve across a variety of health behaviors. “They are so supportive… it encourages you to be faithful in every area with your medication, the exercise. And plus, it helps to elevate your attitude too. It makes you just feel better; it makes you feel more alive… and then you do have something to look forward to.”

Patients like John and Belinda have continued to inspire the MVC Coordinating Center to continually support quality improvement in cardiac rehab utilization. With its latest push report, MVC continued to focus on eligible patients treated for heart attack (AMI), percutaneous coronary intervention (PCI), heart valve repair or replacement (SAVR or TAVR), or coronary artery bypass grafting (CABG), collectively referred to as the “Main 5,” as well as patients with CHF.

The report included MVC 90-day and 365-day episodes of care for adult patients with index cardiac care encounters for Main 5 or CHF conditions. MVC included all its available payer claims between Jan. 1, 2022, and March 31, 2025 (through Sept. 30, 2024 for Medicare). The report provided hospitals with benchmarking data, allowing comparisons in cardiac rehab performance with other eligible MVC hospitals across the state.

Each eligible hospital’s report included a dedicated page highlighting cardiac rehab rates across different patient populations (Figure 1). This table provided an opportunity to examine variation in cardiac rehab participation by race, insurance payer, and Distressed Community Index (DCI) categories to help hospitals better understand which patient populations were experiencing utilization gaps and may benefit from additional support.

Figure 1. Sample Blinded Table Describing Hospital’s Cardiac Rehab Rates Among Different Patient Populations

Two stacked benchmark scatter charts compare MVC hospitals’ CHF care adherence and completion rates within 365 days after discharge. Teal lines mark collaborative averages of 68% and 24%, hollow blue circles show other hospitals, and red dots mark your hospital at 58% adherence and 17% completion, while peer rates generally rise across both charts.

Following the patient population snapshot, MVC also provided benchmarking figures for the Main 5 and CHF patient cohorts, allowing hospitals to compare their cardiac rehab enrollment rates with those of other eligible MVC hospitals. For the Main 5 conditions, the collaborative-wide average 90-day enrollment rate during the reporting period was 34%, below the statewide goal of 40%. Hospital-level enrollment rates ranged from nearly 0% to nearly 60% (Figure 2). For CHF, the collaborative-wide average 365-day enrollment rate was 6%, also below the statewide goal of 10%, with hospital-level rates ranging from 0% to 16% (Figure 3).

Figure 2. 90-Day Cardiac Rehab Enrollment Rate After Discharge from Main 5 Cardiac Care Encounter (Blinded Report)

Line chart compares enrollment rates within 90 days after discharge from five cardiac care encounters across MVC hospitals. Hollow blue circles show other hospitals, black line marks statewide goal at 40%, teal line marks collaborative average at 34%, and red marker identifies your hospital at 44%, with rates generally rising from near 0% to 55%.

Figure 3. 365-Day Cardiac Rehab Enrollment Rate After Discharge from CHF Cardiac Care Encounter (Blinded Report)

Scatter plot shows CR enrollment rate within 365 days after discharge for CHF cardiac care encounters across MVC hospitals. Hollow blue circles rise from near 0% to 16%, teal line marks collaborative average at 6%, black line marks statewide goal at 10%, and red marker identifies Your Hospital at 10%.

In addition to traditional reporting of enrollment rates, MVC incorporated two new measures in the report—adherence and completion—to provide a more comprehensive view of patients’ engagement with cardiac rehab over time. Adherence is an AACVPR performance measure defined as the percentage of enrolled patients who completed at least 12 cardiac rehab sessions within 365 days of the index cardiac care encounter. Completion was defined as the percentage of enrolled patients who completed at least 36 sessions within 365 days of the index cardiac care encounter. Together, these measures provided insight into whether patients continued participating in cardiac rehab after their initial enrollment.

During the reporting period, the statewide average among Main 5 patients was 75% for adherence, meaning that three in four patients completed at least 12 sessions (Figure 4). The statewide average completion rate was 24%, meaning that nearly one in four enrolled Main 5 patients completed at least 36 sessions. Among patients with CHF, 68% completed at least 12 sessions, while 24% completed at least 36 sessions (Figure 5).

Figure 4. Cardiac Rehab Adherence and Completion Rates Within 365 Days After Discharge from Main 5 Cardiac Care Encounters (Blinded Report)

Two-panel dot chart compares MVC hospitals’ cardiac rehabilitation adherence and completion rates within 365 days after discharge from a main five cardiac care encounter. Open circles show other hospitals, blue lines mark collaborative averages of 75% adherence and 24% completion, and red markers show Your Hospital at 77% and 27%, with rates generally increasing across hospitals.

Figure 5. Cardiac Rehab Adherence and Completion Rates Within 365 Days After Discharge from CHF Cardiac Care Encounter (Blinded Report)

Two stacked benchmark scatter charts compare MVC hospitals’ CHF care adherence and completion rates within 365 days after discharge. Teal lines mark collaborative averages of 68% and 24%, hollow blue circles show other hospitals, and red dots mark your hospital at 58% adherence and 17% completion, while peer rates generally rise across both charts.

For hospitals with insufficient case counts, some figures and tables were omitted from the report. Hospitals interested in exploring their cardiac rehab enrollment data further can use the MVC Registry to analyze their hospital’s enrollment rates over time, average number of sessions completed within 90 days, and average time to enrollment (mean days to cardiac rehab). Hospitals interested in examining their cardiac rehab data beyond the information included in the report and the registry can reach out to MVC to request a custom report.

In addition to providing data on cardiac rehab, the MVC Coordinating Center offers a cardiac rehab workgroup where members and partners share strategies and insights to help improve performance. The next workgroup will take place on Tues., Oct. 20, from 12-1 p.m., focused on the content and applications of this push report. More information about upcoming MVC events can be found on the MVC events page.

MVC is a contributing partner of the Michigan Cardiac Rehab Network (MiCR), which is co-led by MVC and the Blue Cross Blue Shield of Michigan Cardiovascular Consortium (BMC2). MiCR aims to increase statewide 90-day cardiac rehab enrollment rates to 40% among Main 5 patients, and 365-day cardiac rehab rates to 10% among eligible CHF patients. To learn more about MiCR and its resources visit https://michigancr.org/.