
Background
In 2021, the Regents of the University of Michigan were awarded a data use agreement with the Centers for Medicare & Medicaid Services (CMS) as a qualified entity (QE). The Michigan Value Collaborative (MVC) is the entity within the University that undertakes all QE reporting. The QE will henceforth be referred to as the Michigan Value Collaborative or MVC in this document.
MVC is a Collaborative Quality Initiative (CQI) working in partnership with Michigan hospitals, physician organizations, and Blue Cross Blue Shield of Michigan (BCBSM) / Blue Care Network (BCN) with the goal of improving the health of Michigan residents through sustainable, high-value healthcare. Since 2013, MVC has used claims-based episodes of care for health insurance payers in the state of Michigan to support and inform hospital quality improvement assessments and initiatives.
As a QE, MVC is required to disseminate a public report on provider performance annually, incorporating QE Medicare and other payer data. This report provides measures of 30-day unplanned rehospitalization from post-discharge home health for high-volume medical and surgical conditions, as well as measures of post-discharge outpatient follow-up for congestive heart failure (CHF) and chronic obstructive pulmonary disease (COPD). As part of the report development, MVC gathered stakeholder feedback on the proposed measures, which was incorporated into the final measure definitions, as appropriate.
Methods
MVC creates 30- and 90-day episodes of care for over 40 high-volume medical and surgical conditions using paid health insurance claims from BCBSM PPO Commercial, BCBSM PPO Medicare Advantage (MA), BCN HMO Commercial, BCN HMO MA, BCN Other, Medicare FFS, and Medicaid. Each episode begins with an index event (e.g., hospital admission or surgery, including outpatient-based procedures) for one of MVC’s 40+ conditions and includes up to 90 days of post-index utilization.
Index hospitalizations for conditions are identified by ICD-10-CM diagnosis codes, ICD-10-PCS procedure codes, and HCPCS/CPT codes. For index hospitalizations that include an inpatient transfer, the hospitalizations at both the original and receiving hospitals are included in the index event and the episode is attributed to the initial hospital. Episodes are created for patients with a qualifying index event, who are at least 18 years of age, and who were continuously enrolled with their insurance provider for at least 180 days prior to the index admission.
A patient can be in only one 90-day MVC episode at a time. Episodes are created chronologically; therefore, if a patient has multiple potential index events in a short time period, an episode is created for the index event that happened first. If a patient meets the eligibility requirements for more than one index condition event on the same day, a hierarchical logic is applied – based on the average payment for each condition – to initialize one condition/episode per patient per date. For the condition hierarchy implementation logic see Appendix A. For claim categorization rules of episode components see Appendix B.
Each episode is attributed to a single year or quarter according to the index hospital admission date. The following report contains episodes with index admissions between January 1, 2018, and December 31, 2024, that have been attributed to MVC member hospitals in the state of Michigan.
Each episode is attributed to one hospital according to the organization NPI on the index facility claim. When joining MVC as a member, each hospital self-identifies the organization NPIs to attribute to their hospital. Episodes for analysis are then limited to episodes attributed to MVC member hospitals in the state of Michigan, n=107 hospitals. All providers (hospital or home health agency) shown in this report are unidentified.
Rates are calculated as the number of episodes meeting criteria for the outcome of interest, divided by the number of qualifying episodes, multiplied by 100. Both unadjusted and risk-adjusted rates are shown where indicated, and 95% Wald confidence intervals for proportions are calculated for unadjusted and adjusted rates.
Unadjusted rate = (N episodes with outcome / N total episodes) * 100
The reference population serving as a benchmark in this report is MVC All, which is a weighted rate comprised of episodes attributed to all MVC member hospitals.
At each level of reporting, measures and figures presented in this report do not show any data points based on a denominator of fewer than 30 episodes, in accordance with QECP guidelines. For example, rates by home health agency will not display any rates for home health agencies with fewer than 30 episodes in any reported time window. However, the calculation of overall measures includes all otherwise qualifying episodes regardless of their inclusion in more granular data points.
Unplanned Rehospitalization During First 30 Days of Home Health
This measure assesses unplanned rehospitalizations in the first 30 days of home health among patients who received home health care following an inpatient hospital discharge.
The underlying population for this measure consisted of episodes for patients with a qualifying inpatient index hospitalization for an MVC condition and who were discharged to home or home health per index discharge disposition. Following CMS guidelines, qualifying index hospitalizations were assessed according to the single-level diagnosis clinical classification software (CCS) category for a hospitalization’s principal diagnosis code, and excluded hospitalizations for treatment of cancer, psychiatric disease, or rehabilitation care (e.g., fitting of prostheses and adjustment devices). All episodes for cancer-related conditions and episodes for childbirth delivery were further excluded from the denominator. To be included in the analytic cohort, each patient was required to have started home health within 0 to 5 days following their index hospitalization discharge. Episodes meeting either of the following criteria were also excluded from analysis: those involving a home health transfer or for which inpatient-type care (i.e., inpatient hospitalization, inpatient rehabilitation, skilled nursing facility, or long-term acute care hospitalization) was received between index discharge and the start of home health. After applying exclusions, episodes for 29 inpatient index conditions (see Appendix A for the full list) were included in the measure.
The measured outcome for this metric was the presence of an unplanned inpatient hospitalization that begins within 1 to 30 days following the start of a patient’s post-discharge home health care. Inpatient hospitalization claims were categorized as planned or unplanned according to ICD-10-CM diagnosis codes, ICD-10-PCS procedure codes, and HCPCS/CPT codes in accordance with the 2026 CMS planned readmission algorithm (CMS, 2026 All-Cause, Unplanned Hospital-Wide Readmission Measure). Unadjusted and risk-adjusted prevalence rates were calculated for this measure as described below.
All rates shown for combined conditions have been risk adjusted to account for differences between index hospitalization conditions/patients. Expected probabilities of each outcome were generated for each episode using a logistic regression model adjusting for patient age, sex, payer, condition, DRG complication level, prior six months of payments, and 79 hierarchical condition categories. Rates were generated for each unit of analysis (by quarter, home health provider, and hospital of the index hospitalization) and then risk adjusted as follows, where the population expected rate was the overall expected rate for all eligible episodes at MVC member hospitals.
Observed or unadjusted rate = N episodes with outcome / N total episodes * 100
Risk-adjusted rate = (observed rate/expected rate) * population expected rate
Outpatient Follow-Up Within 3, 7, 14, and 30 Days of CHF/COPD Hospitalization
This measure assesses the proportion of patients with episodes for CHF and COPD who received outpatient follow-up following their index hospital discharge.
The underlying population for this metric was comprised of patients insured by payers in the MVC database who had 90-day CHF and COPD episodes of care at MVC member hospitals. Only index hospitalizations resulting in discharge to home or home health, as assessed according to the discharge disposition on the claim, were included. Patients receiving care at a skilled nursing facility or inpatient rehabilitation unit or who had a long-term acute care hospitalization during the 30 days post-discharge were further excluded from the denominator of this measure.
Follow-up visits were defined by the presence of M1 Berenson-Eggers Types of Service (BETOS) category of office visits or CPT codes for transitions of care (99495 and 99496) found on professional claims. Remote follow-up received by phone or video (CPT: 99441, 99442, 99443, 98000-98015) was also considered a positive indication of outpatient follow-up. Receipt of follow-up was assessed beginning the day after index discharge. In this measure, patients were not considered to have received timely follow-up if the patient had an outpatient procedure, ED visit, or inpatient readmission between index discharge and their first post-discharge office visit. Four different follow-up windows are shown for CHF and COPD episodes: three days, seven days, 14 days, and 30 days. This measure was originally designed to show follow-up within 14 days for CHF and 30 days for COPD; however, MVC stakeholders requested the inclusion of additional follow-up windows.
This measure was not risk adjusted. In a sensitivity analysis, risk adjustment had little effect on follow-up rates. Additionally, MVC believes that timely follow-up is a service that all patients should receive regardless of their demographic characteristics and comorbidities, which makes comparison of unadjusted rates more beneficial to hospital members.
Findings
Unplanned Rehospitalization During First 30 Days of Home Health
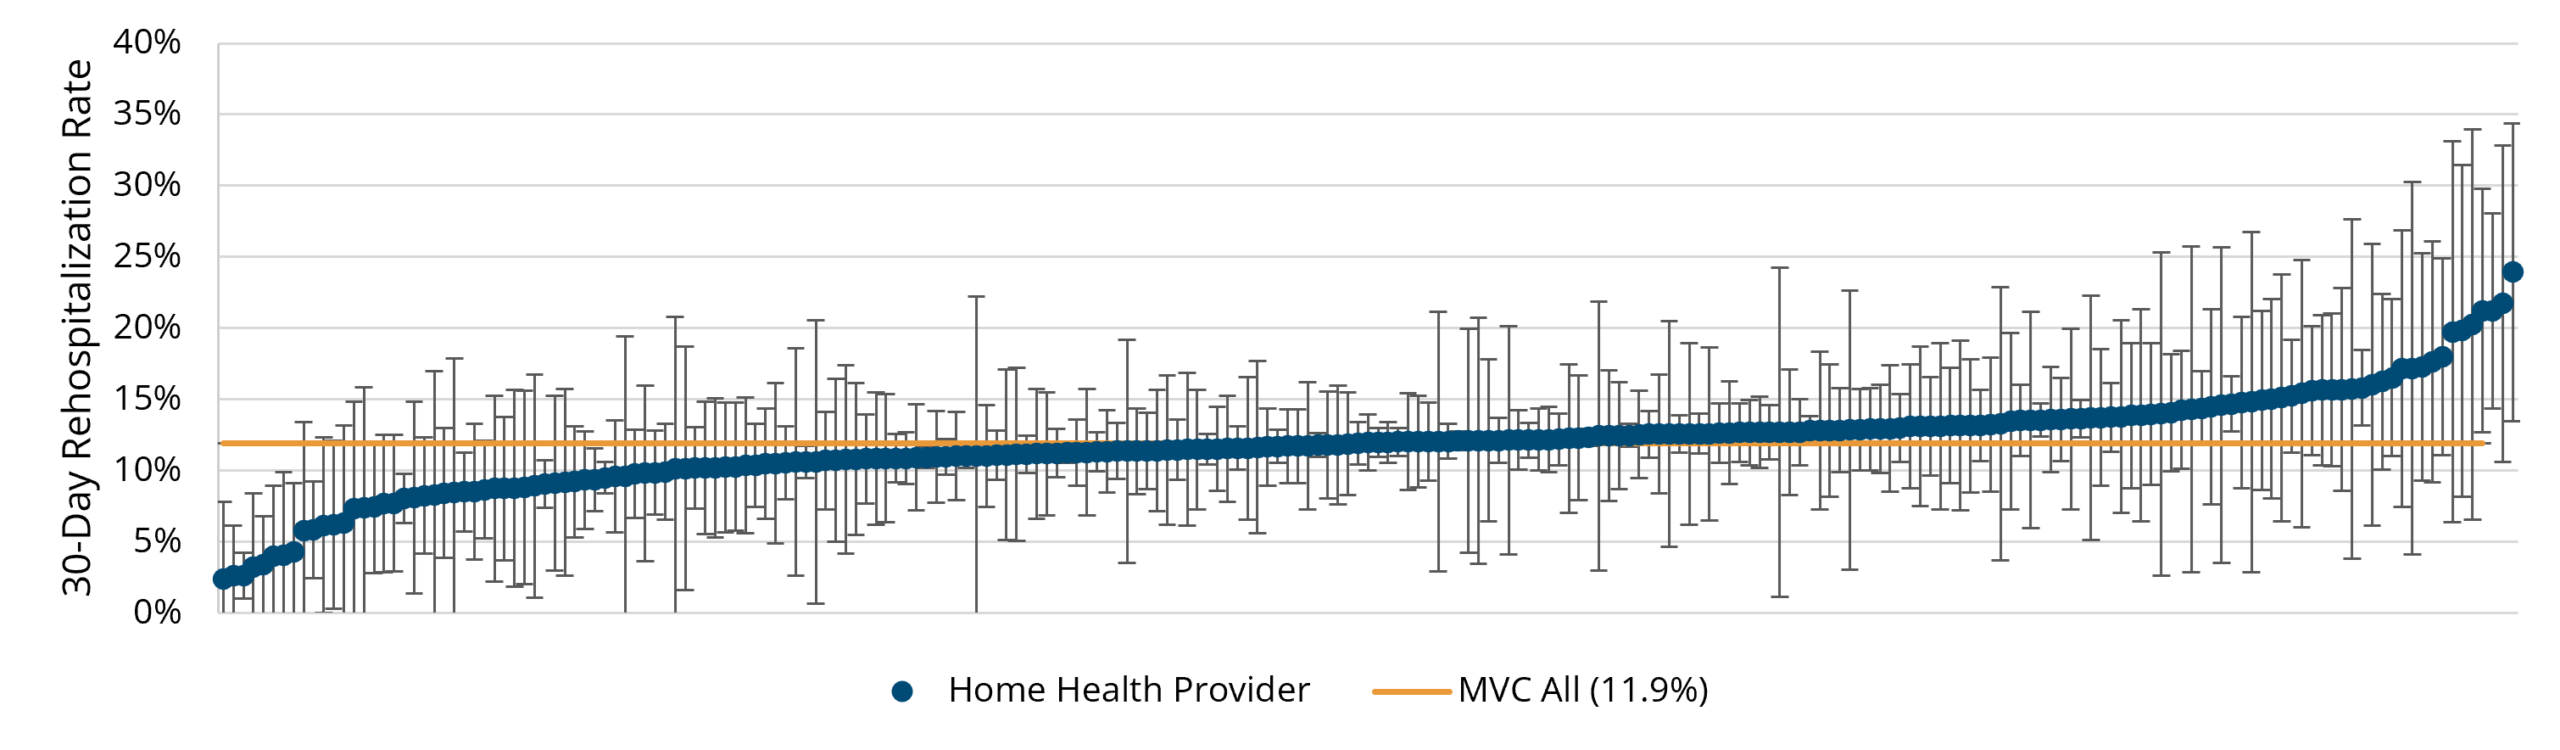
In 2018-2024, the overall risk-adjusted rate of unplanned rehospitalization during the first 30 days of home health was 11.9%. Risk-adjusted rates varied from 10.8% to 13.4% in each calendar quarter (Figure 1). By the hospital of the index inpatient stay, risk-adjusted rates for MVC member hospitals across 2018-2024 ranged from 4.5% to 16.4% (Figure 2). By home health provider, risk-adjusted rates of rehospitalization ranged from 2.4% to 23.9% (Figure 3). For the majority of attributed hospitals and home health providers, the risk-adjusted rate of unplanned rehospitalization during the first 30 days of home health did not differ significantly from the overall collaborative rate of 11.9%.
The index condition with the highest unadjusted 30-day rehospitalization rate following the start of home health care was endocarditis (22.4%) followed by COPD and CHF each with an unplanned rehospitalization rate of 19.9% (Figure 4). Knee and hip replacement episodes had the lowest unadjusted rehospitalization rate (3.0%).
Figure 1. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by Quarter
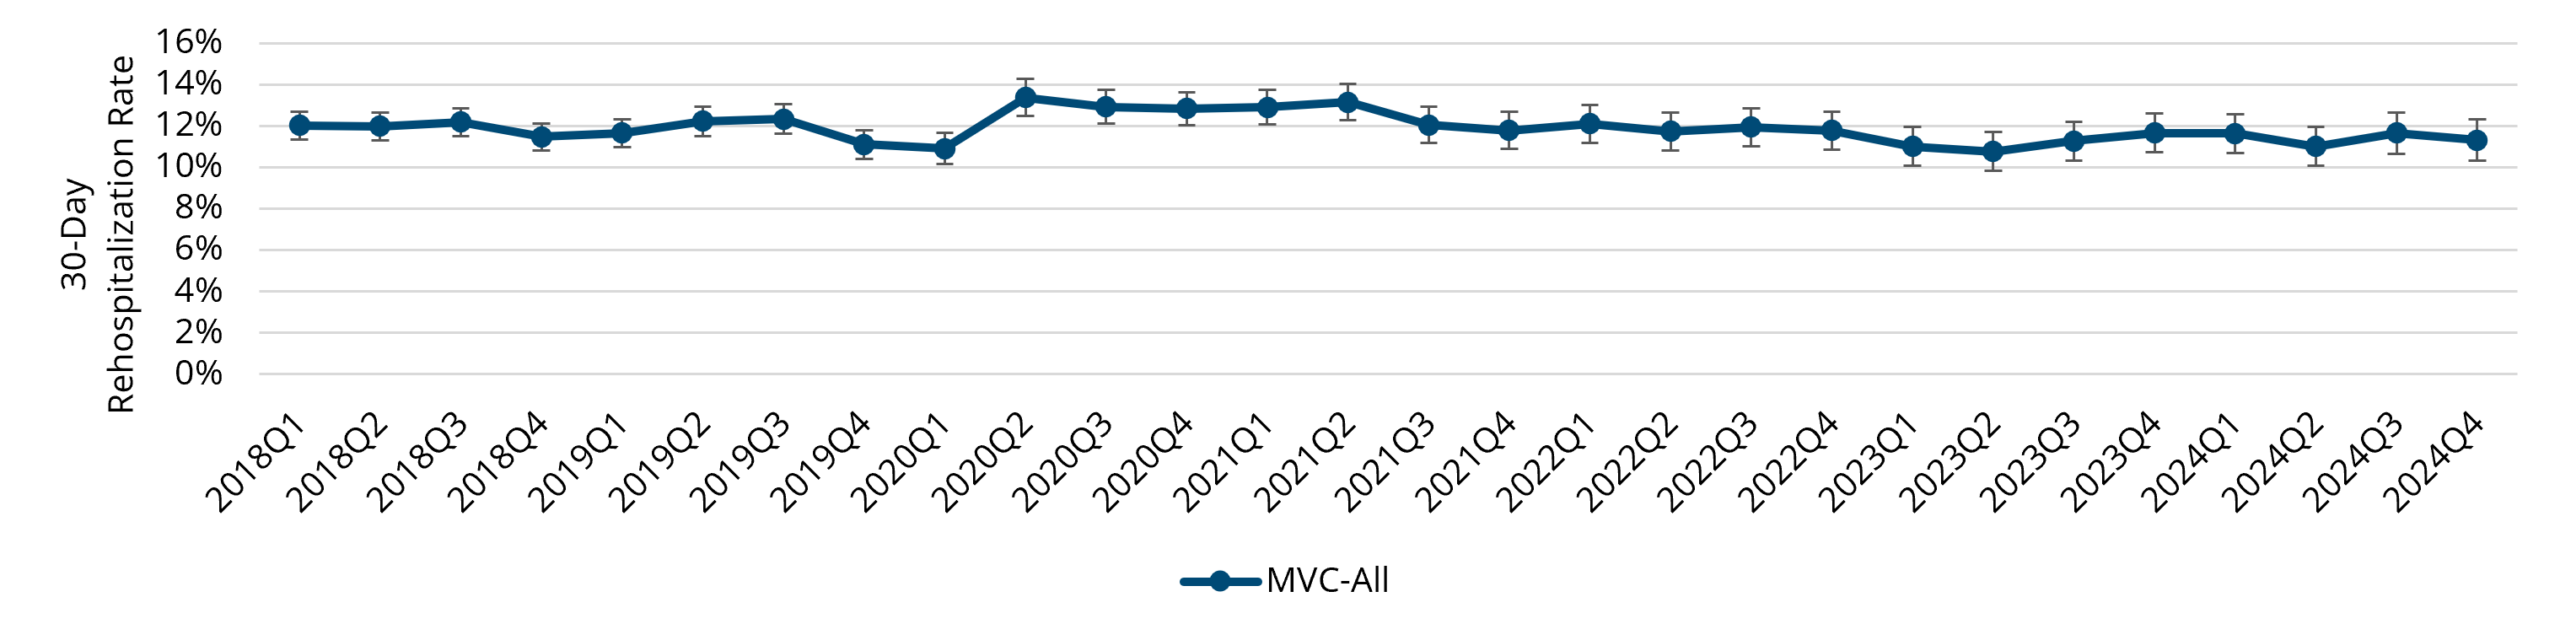
Figure 2. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by MVC Hospital
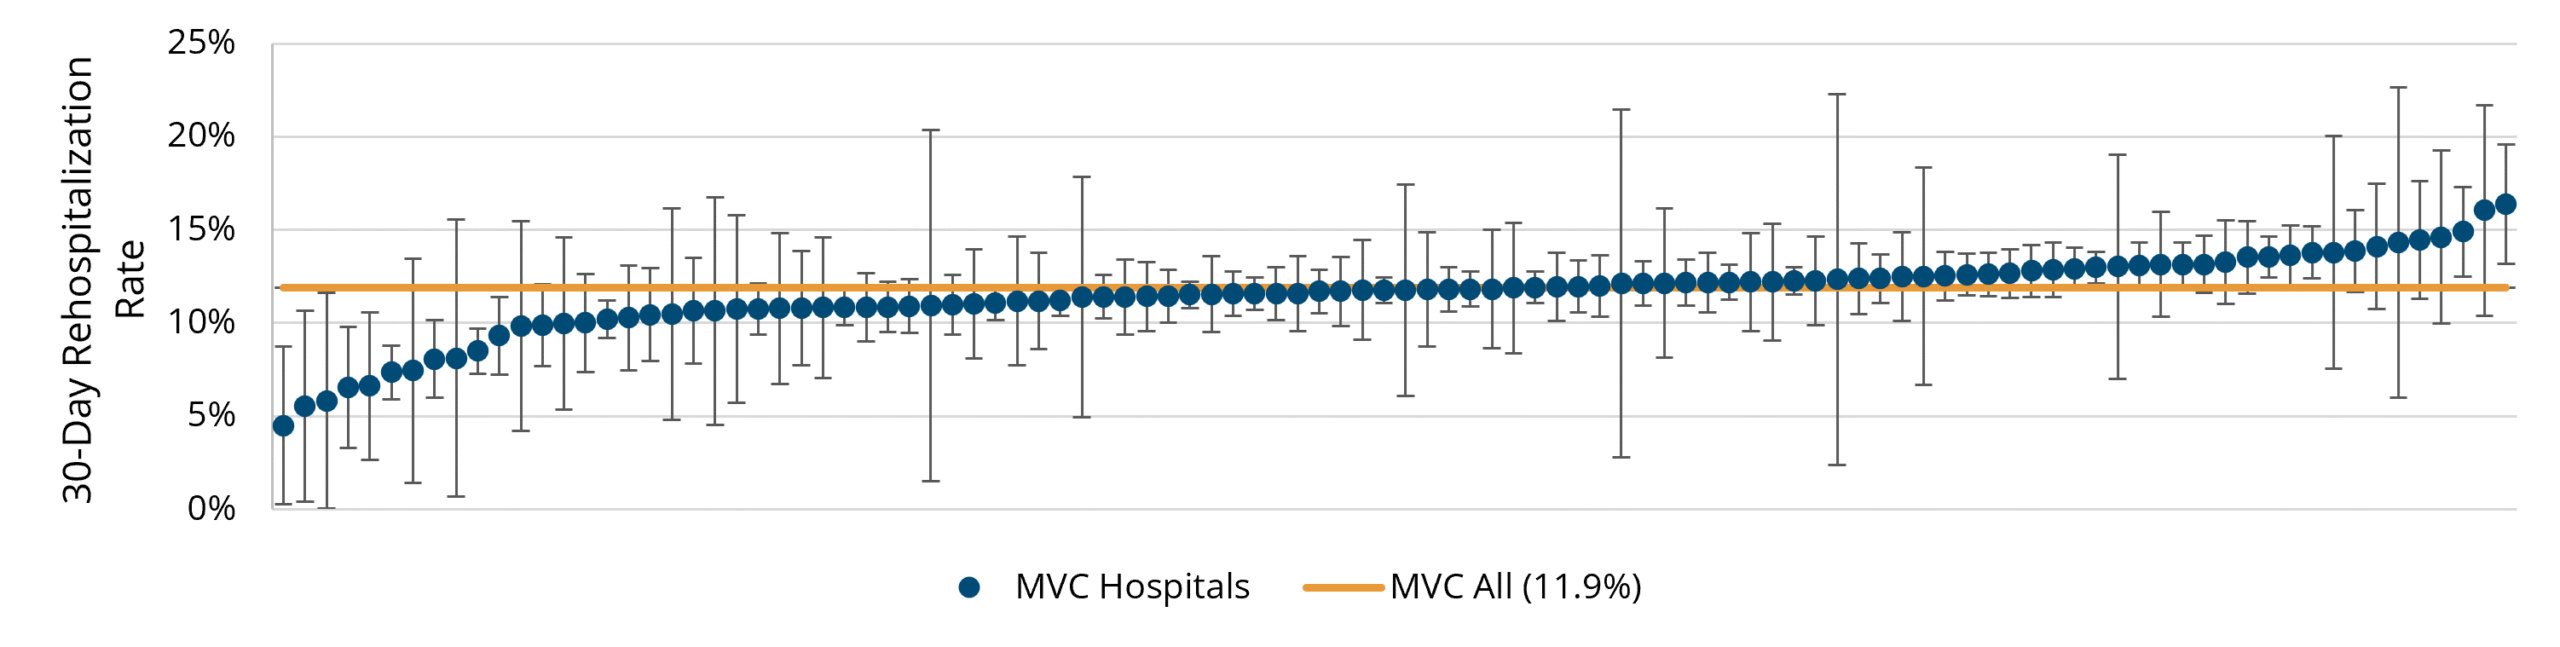
Figure 3. Risk-Adjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by Home Health Provider
The index condition with the highest unadjusted 30-day rehospitalization rate following the start of home health care was endocarditis (22.4%) followed by COPD and CHF each with an unplanned rehospitalization rate of 19.9% (Figure 4). Knee and hip replacement episodes had the lowest unadjusted rehospitalization rate (3.0%).
Among high-volume conditions, the condition-specific unadjusted 30-day rate of unplanned rehospitalization from home health remained fairly consistent by quarter from 2018 Q1 through 2024 Q4 (Figure 5). High-volume conditions with the largest amount of variation in unadjusted rate by quarter were COPD and pneumonia.
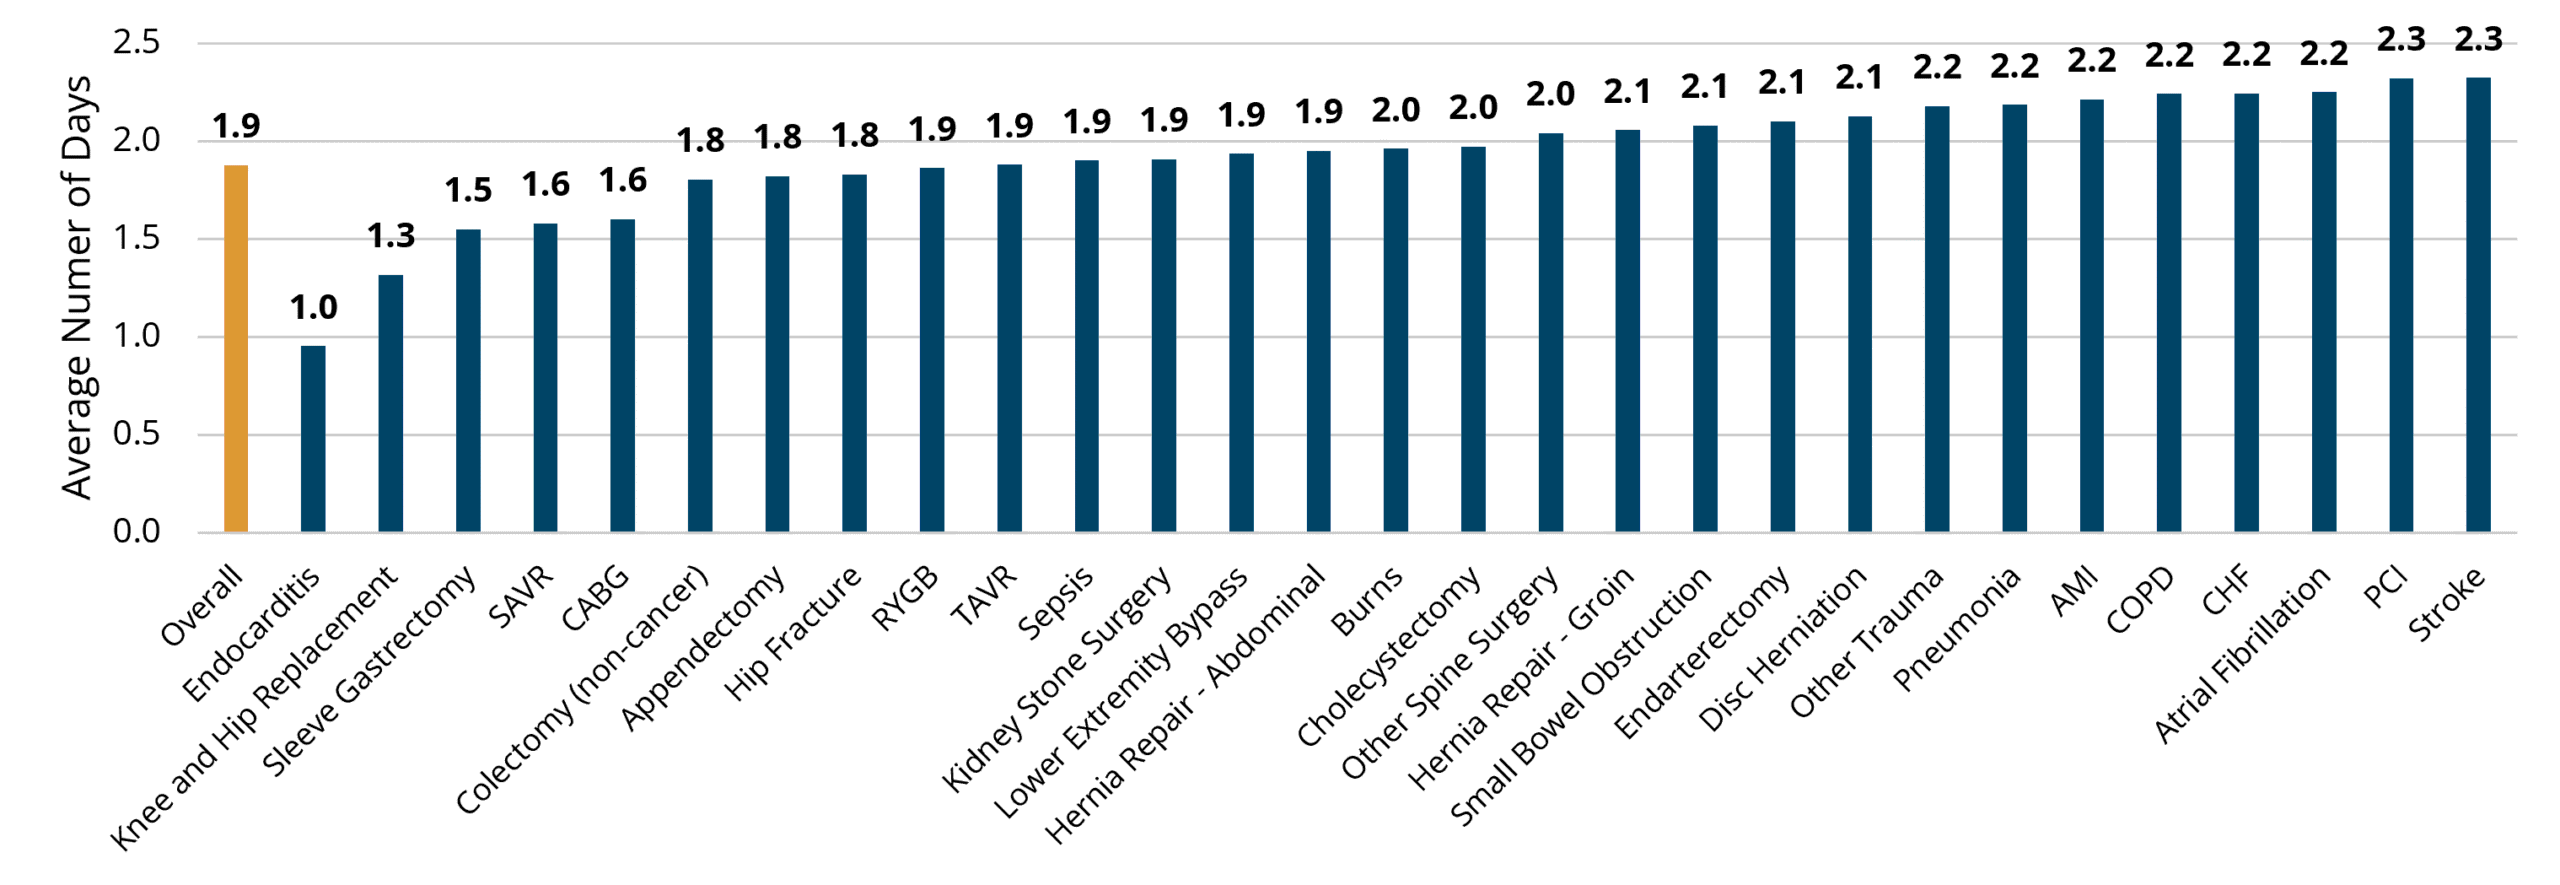
Among episodes in which home health care began within 0 to 5 days following the index hospitalization discharge, the majority (47.4%) began home health care one day following index discharge (Figure 6). The average number of days to the start of home health care was 1.9 days (Figure 7). Home health care began earliest for episodes of endocarditis with an average of 1.0 days, and latest for PCI and stroke with an average of 2.3 days until the start of home health care.
Figure 4. Unadjusted Rates of 30-Day Unplanned Rehospitalization from Home Health, by Condition
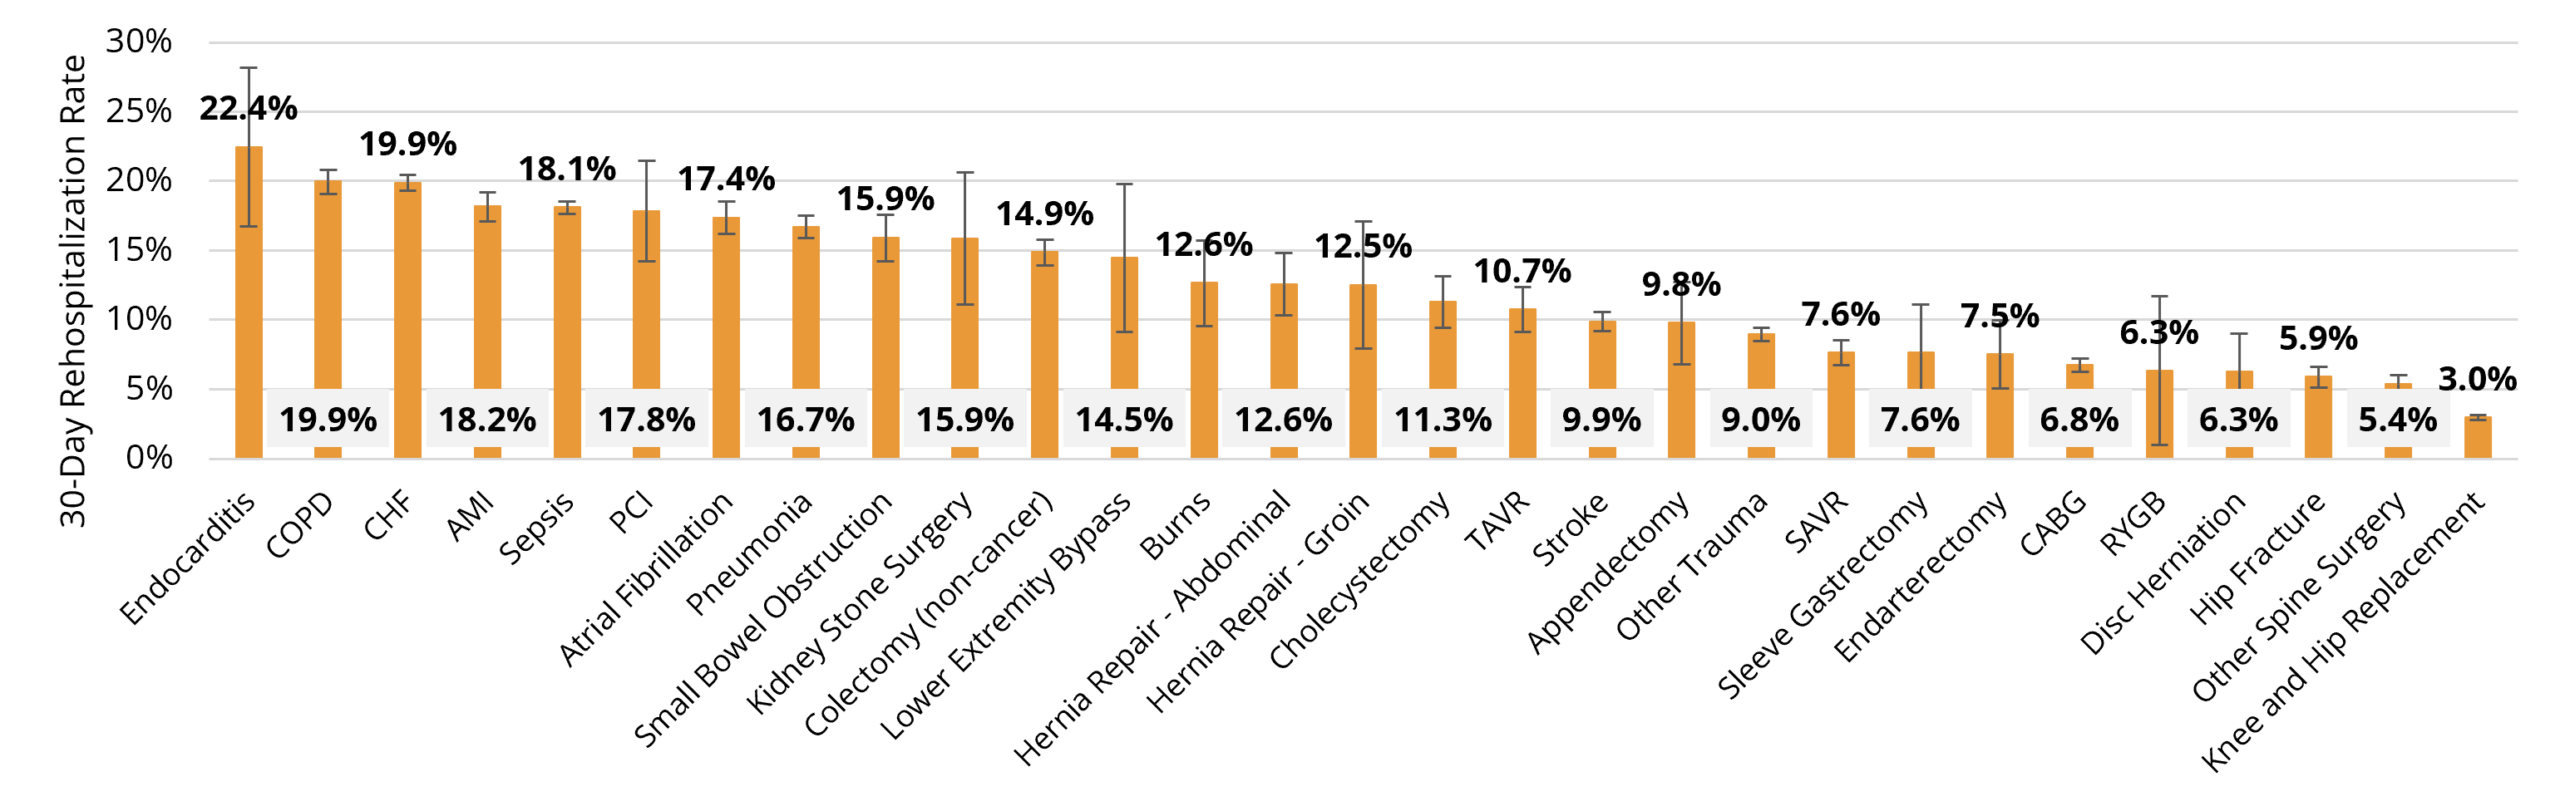
Figure 5. Unadjusted Rates of 30-Day Rehospitalization from Home Health, by Quarter, for High Volume Conditions
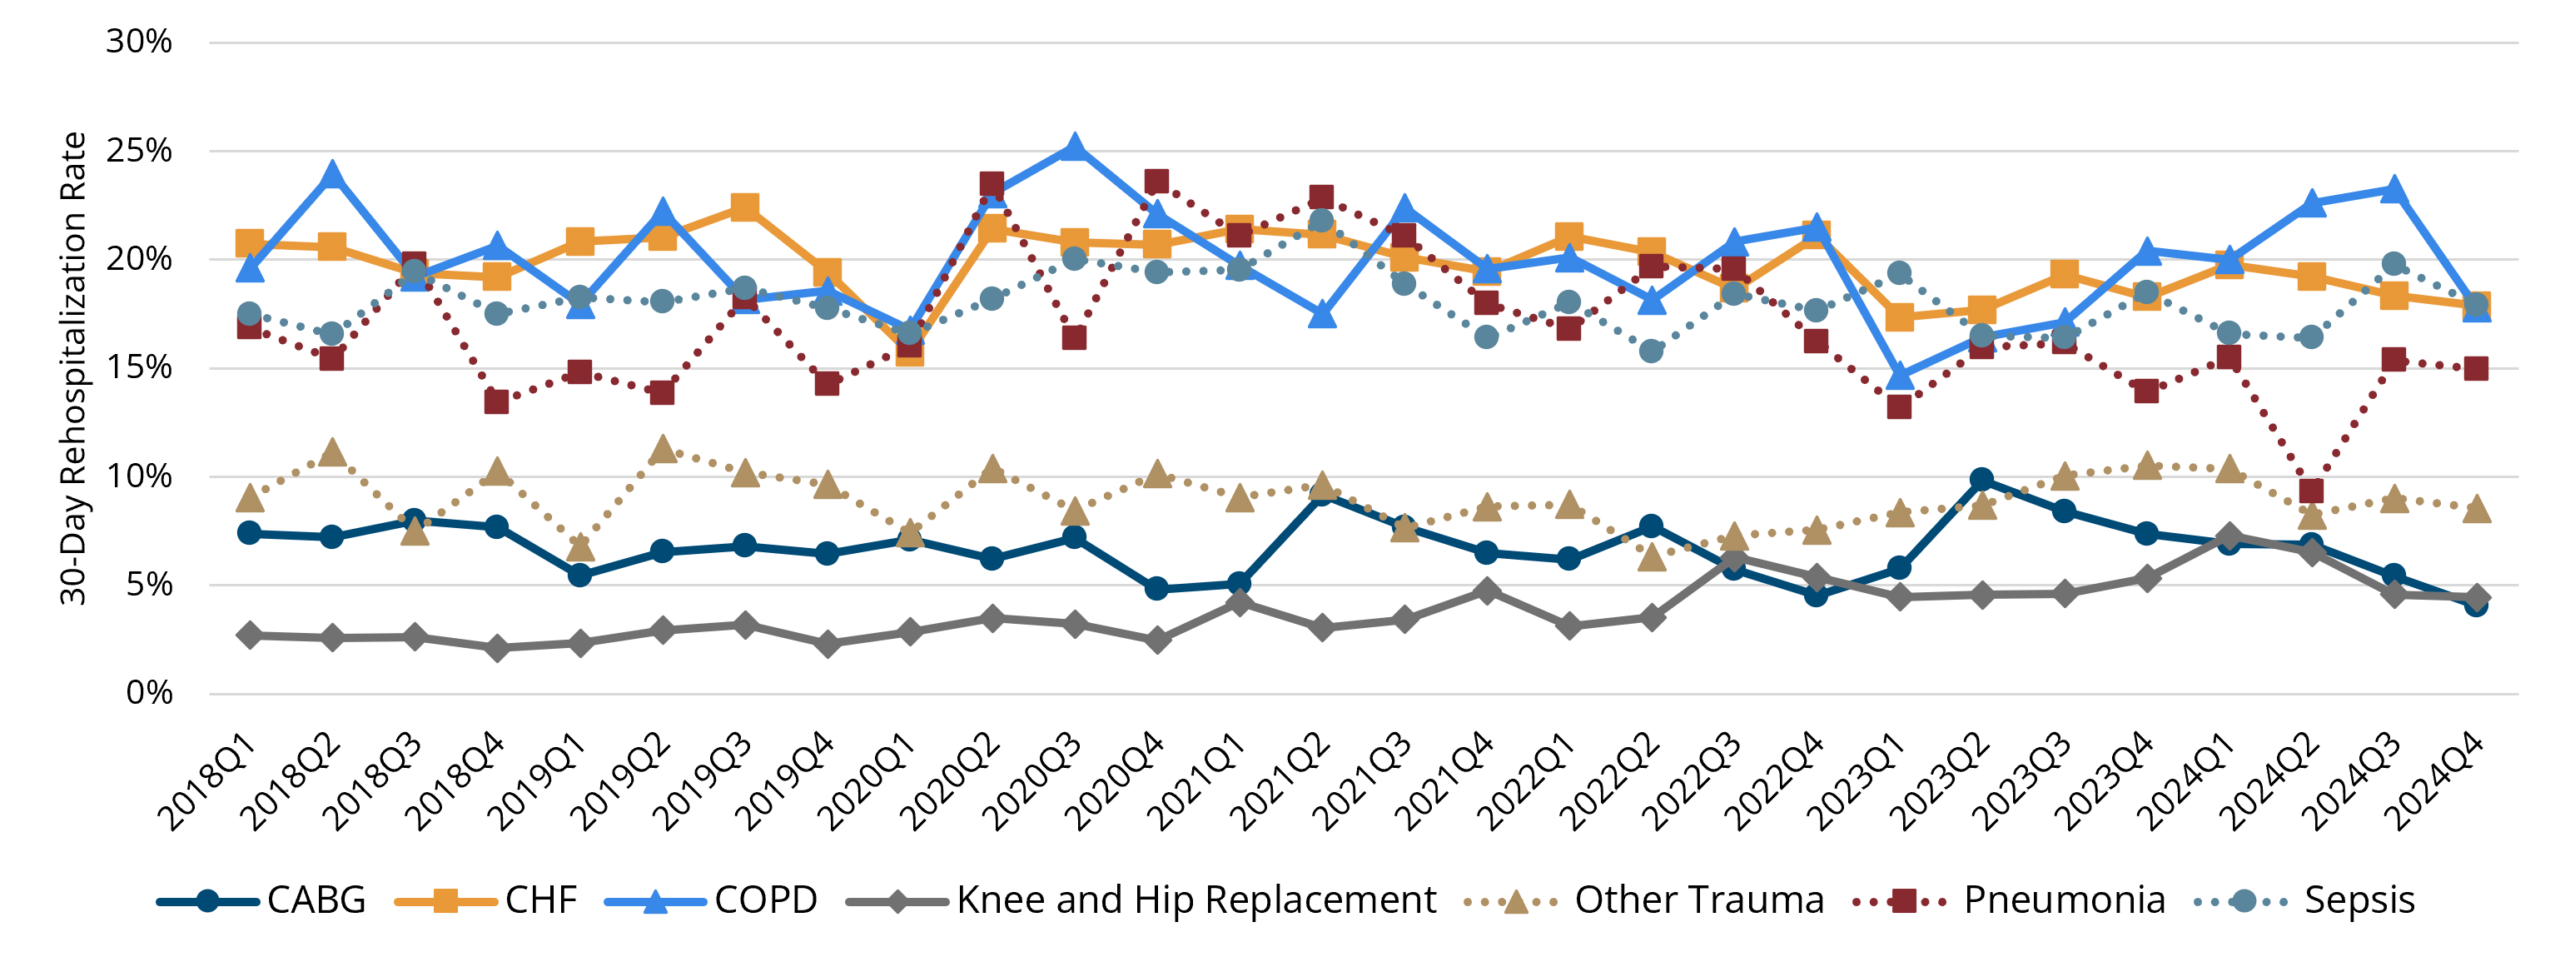
Figure 6. Distribution of Number of Days from Index Discharge to Start of Home Health, All Conditions
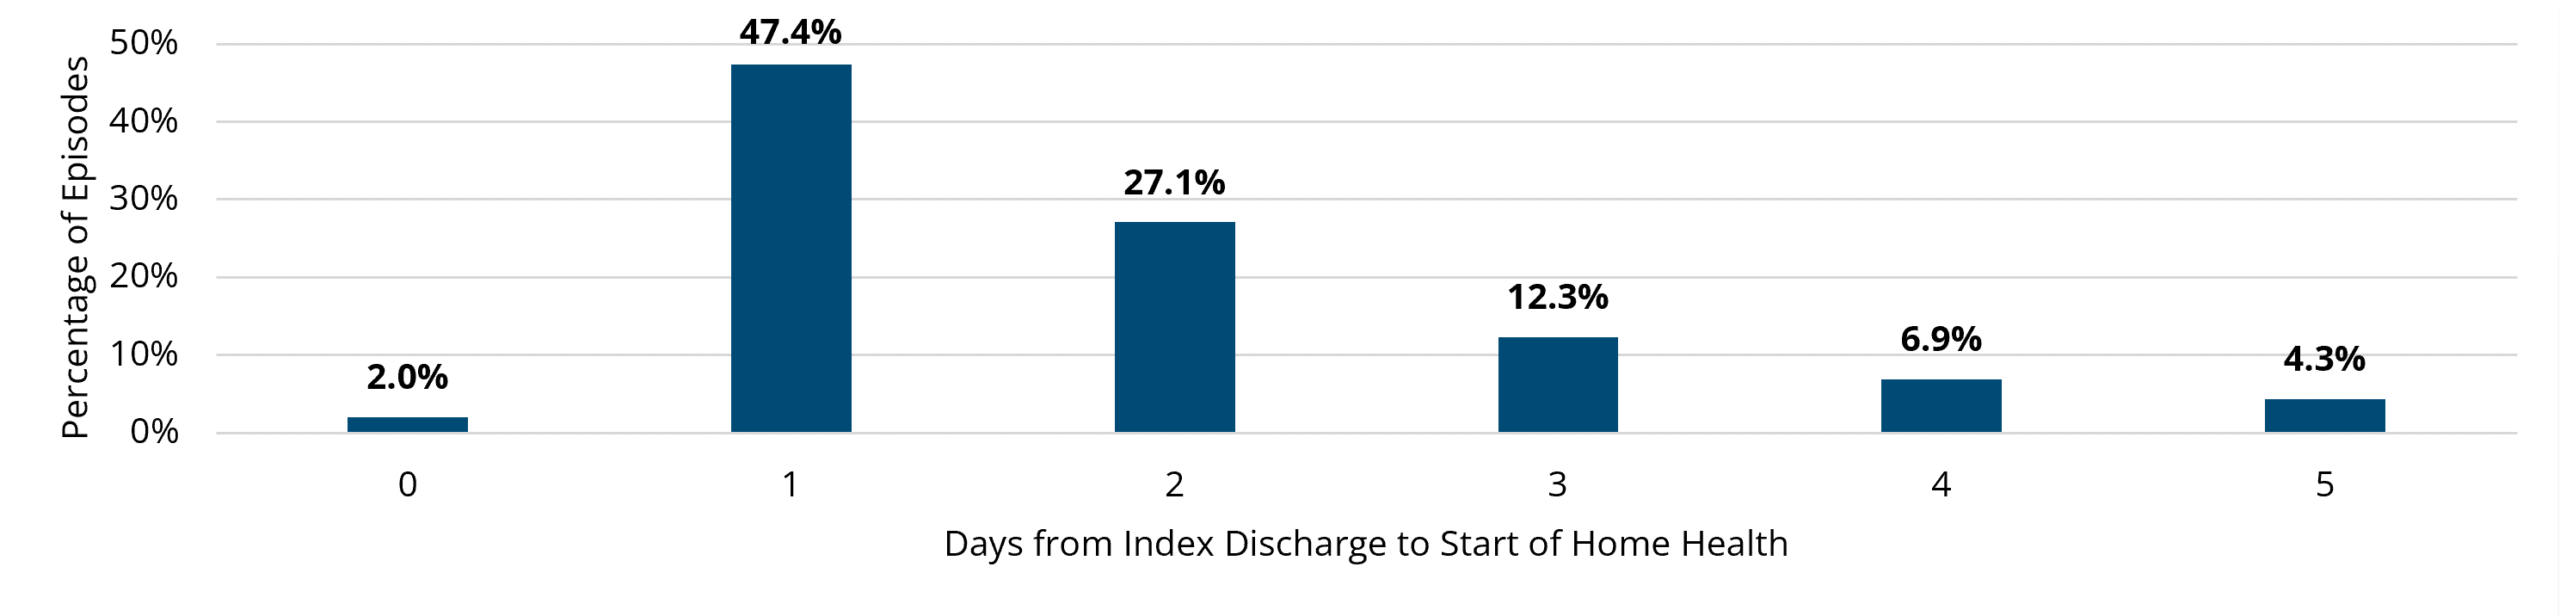
Figure 7. Average Number of Days from Index Discharge to Start of Home Health (Range of 0 to 5 Days), Overall and by Condition
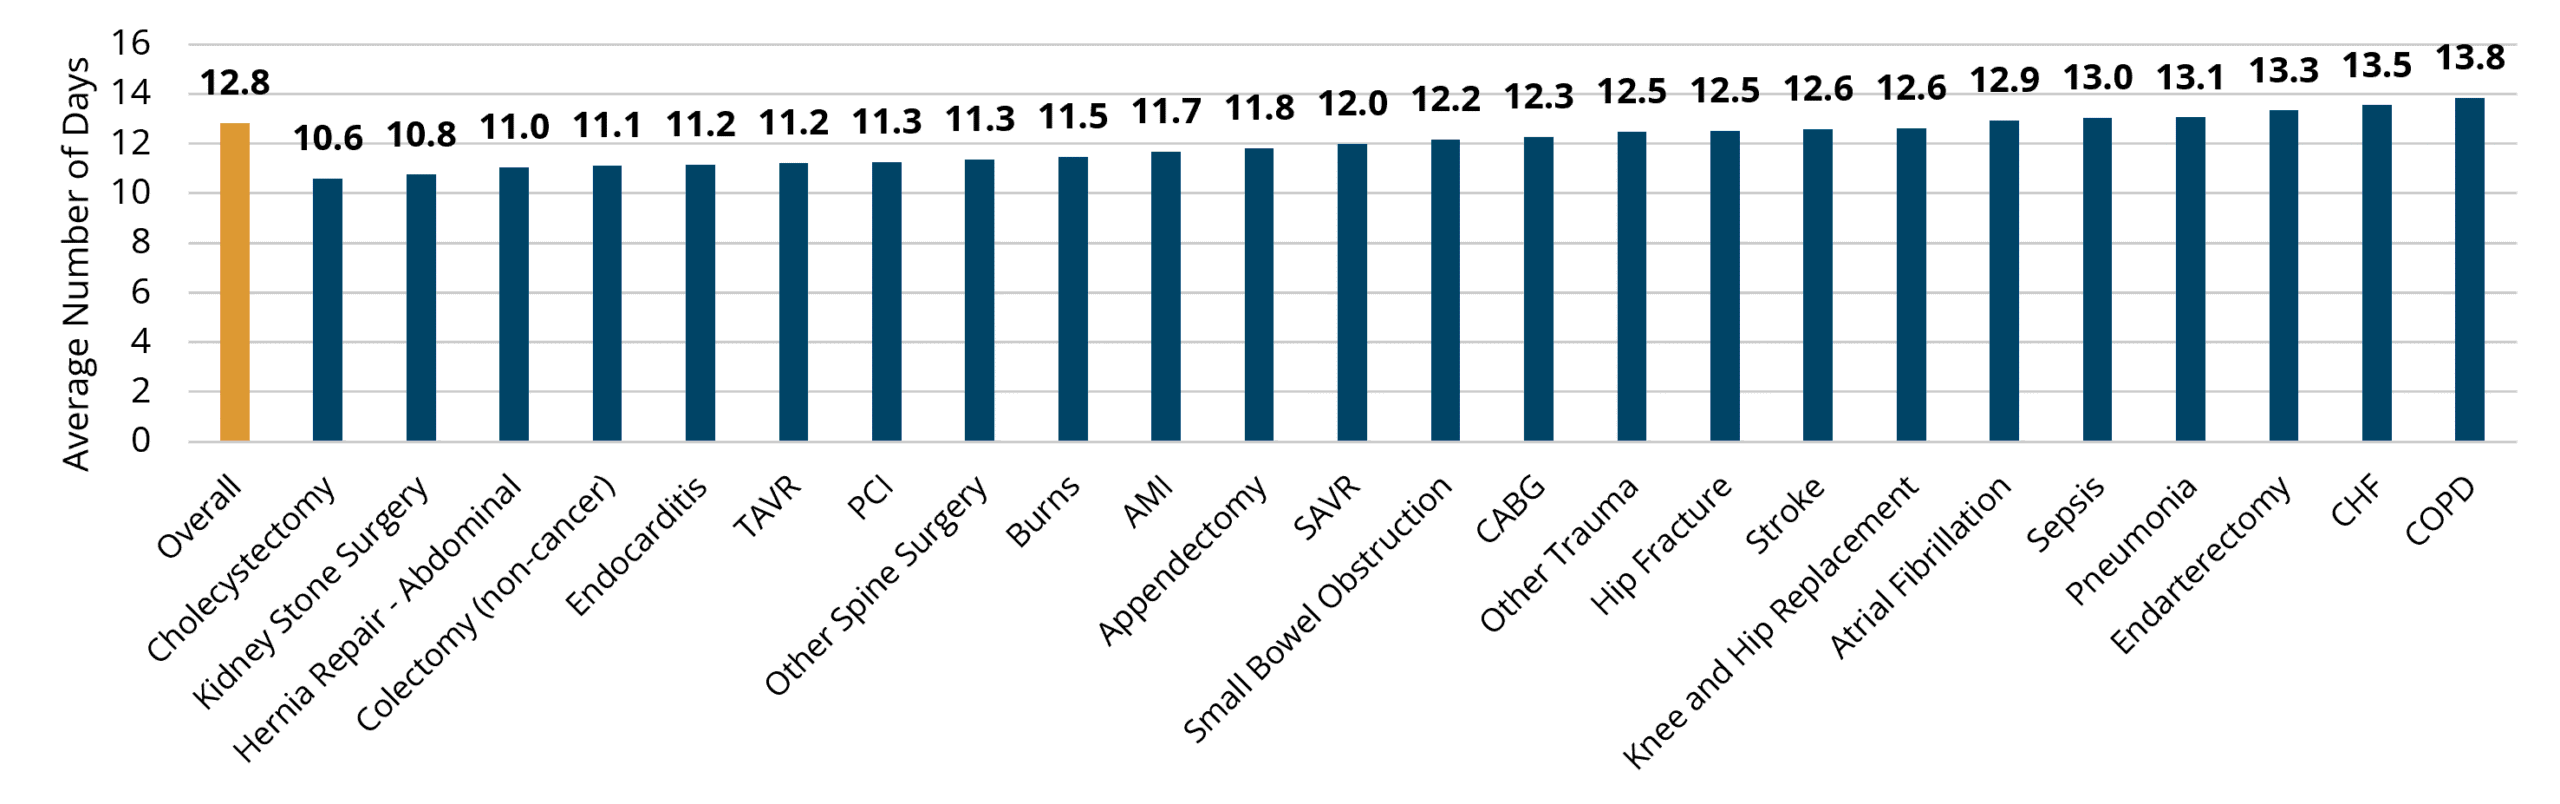
Over 60% of unplanned rehospitalizations occurred within the first 14 days of home health care (Figure 8). The average number of days from the start of home health care to first unplanned rehospitalization was 12.8 days (Figure 9). By index hospitalization condition, the average number of days to first unplanned rehospitalization ranged from 10.6 days (episodes for Cholecystectomy) to 13.8 days (episodes for COPD).
Figure 8. Distribution of Number of Days from Start of Home Health to First Unplanned Rehospitalization, All Conditions
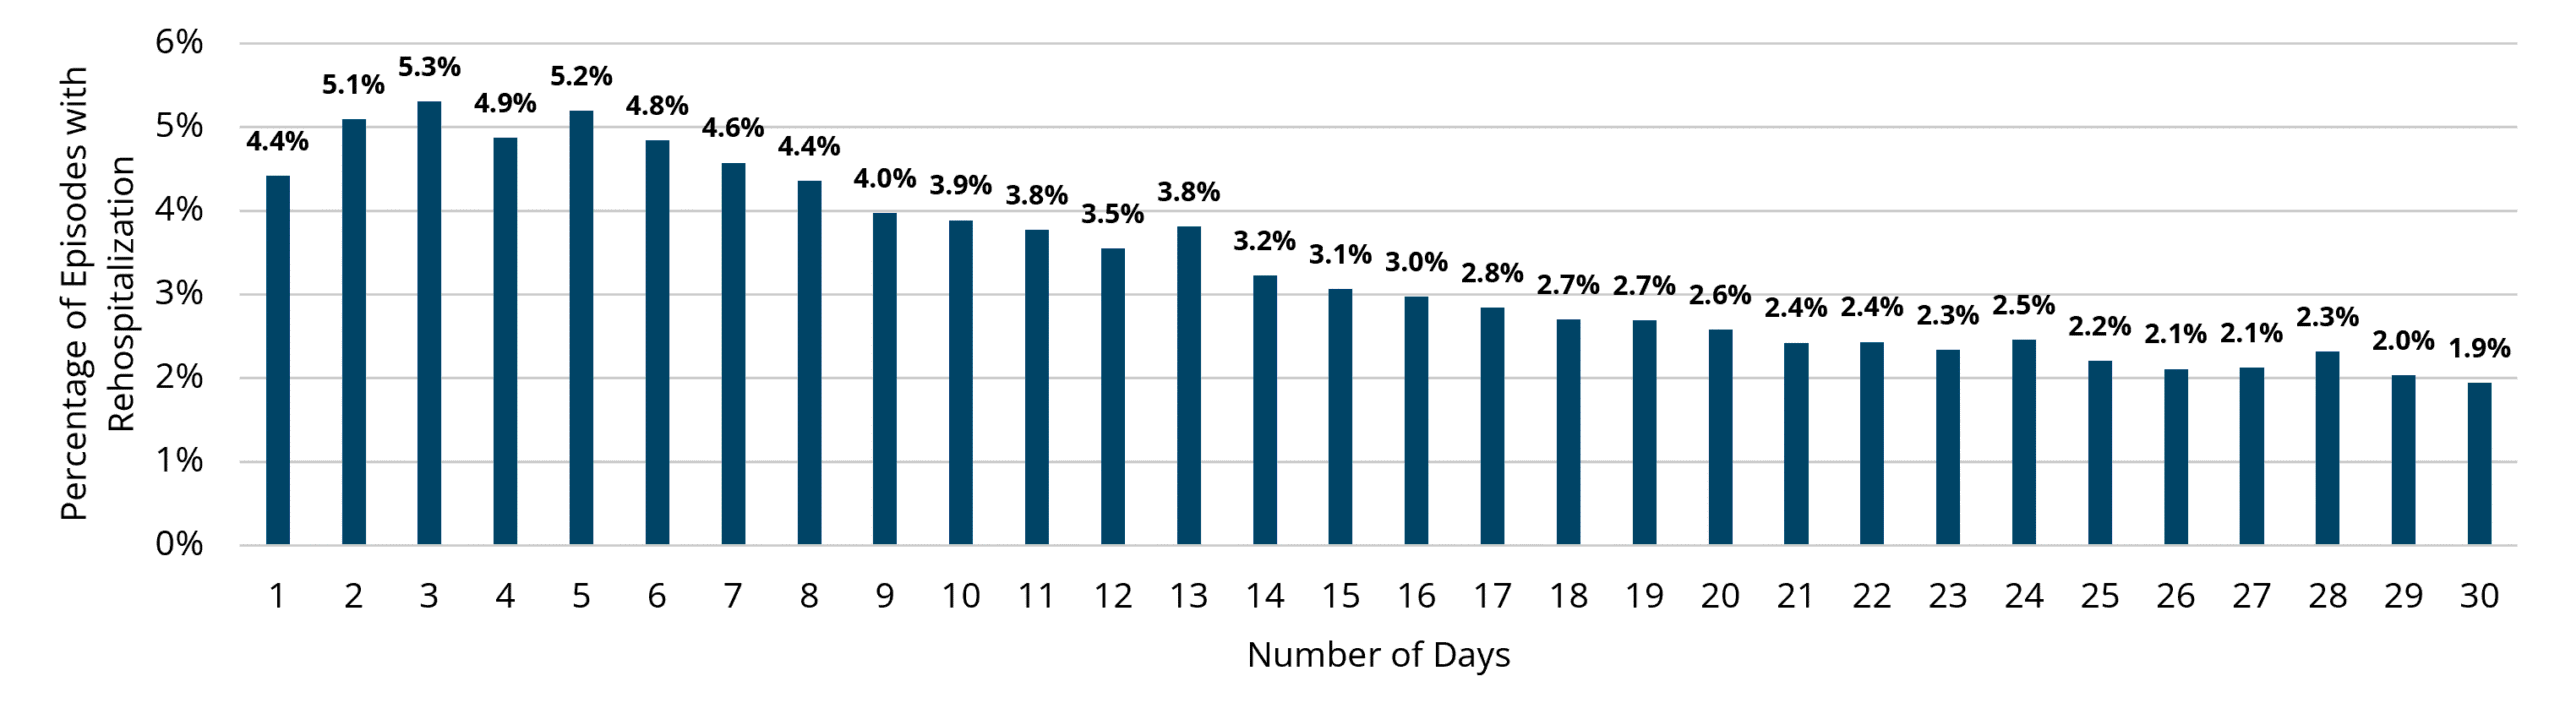
Figure 9. Average Number of Days from Start of Home Health to First Unplanned Rehospitalization, Overall and by Condition
Outpatient Follow-Up Within 3, 7, 14, and 30 Days of CHF Hospitalization
The outpatient follow-up rates among MVC hospitals in Michigan varied greatly by index hospital. While many hospitals were near the overall MVC rate, all follow-up windows had hospitals that had significantly higher or lower rates. The MVC overall rate for 3-, 7-, 14-, and 30-day follow-up measures following CHF hospitalization were 15.5%, 43.6%, 60.9% and 69.7% (Figures 10-13).
Figure 10. 3-Day Follow-Up After CHF Hospitalization, by MVC Hospital
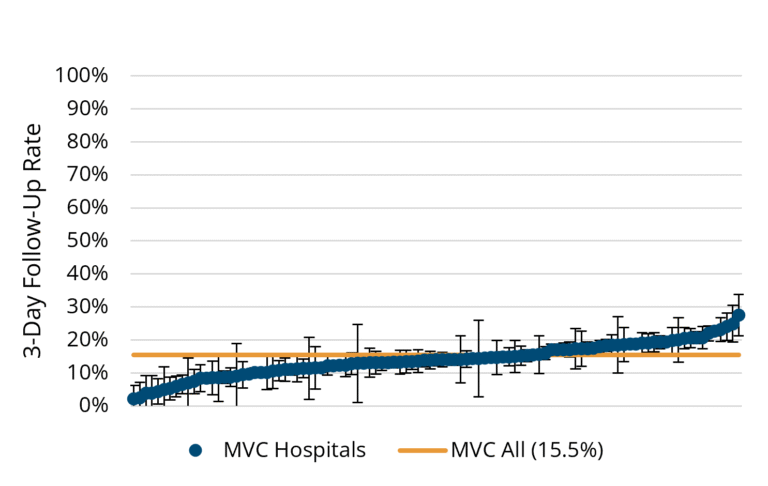
Figure 11. 7-Day Follow-Up After CHF Hospitalization, by MVC Hospital
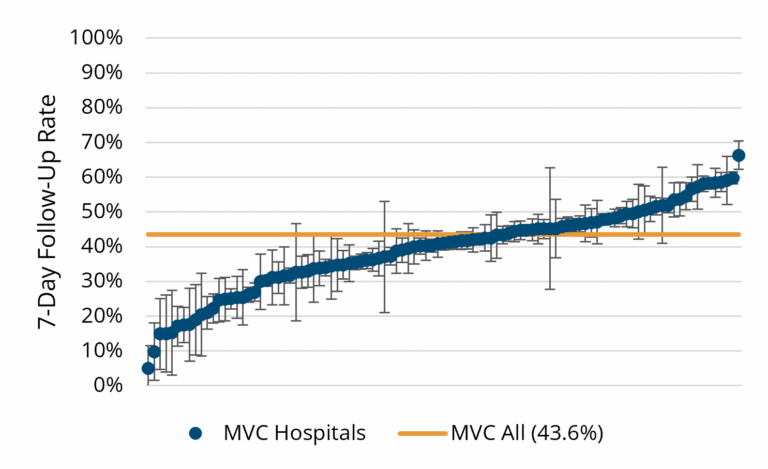
Figure 12. 14-Day Follow-Up After CHF Hospitalization, by MVC Hospital
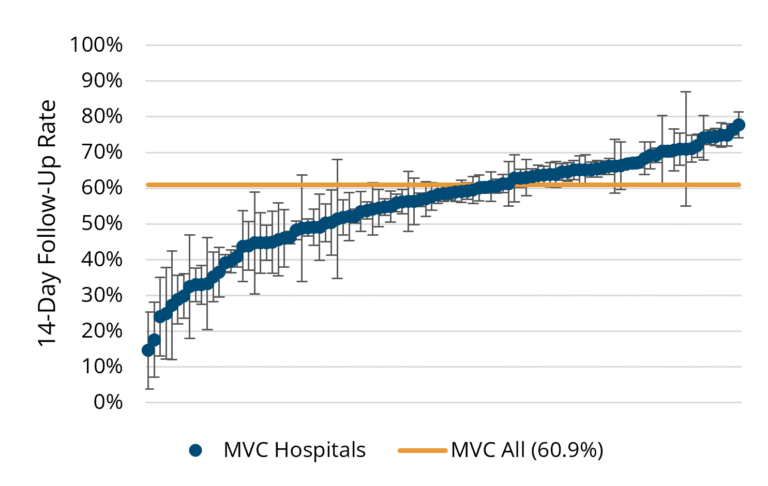
Figure 13. 30-Day Follow-Up After CHF Hospitalization, by MVC Hospital
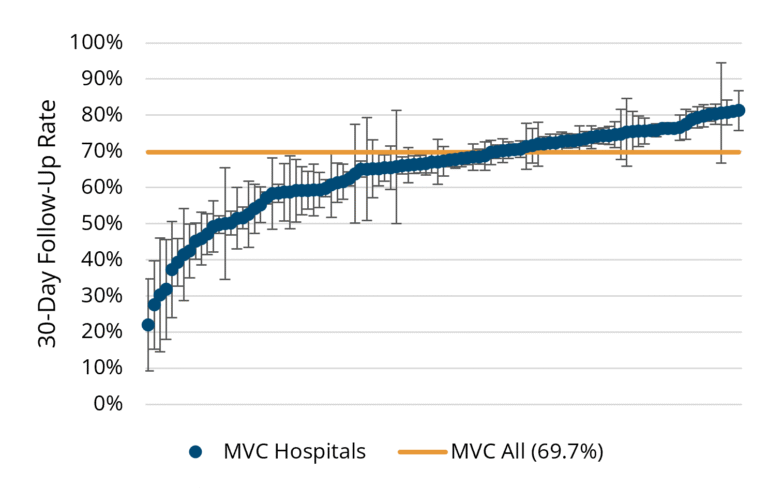
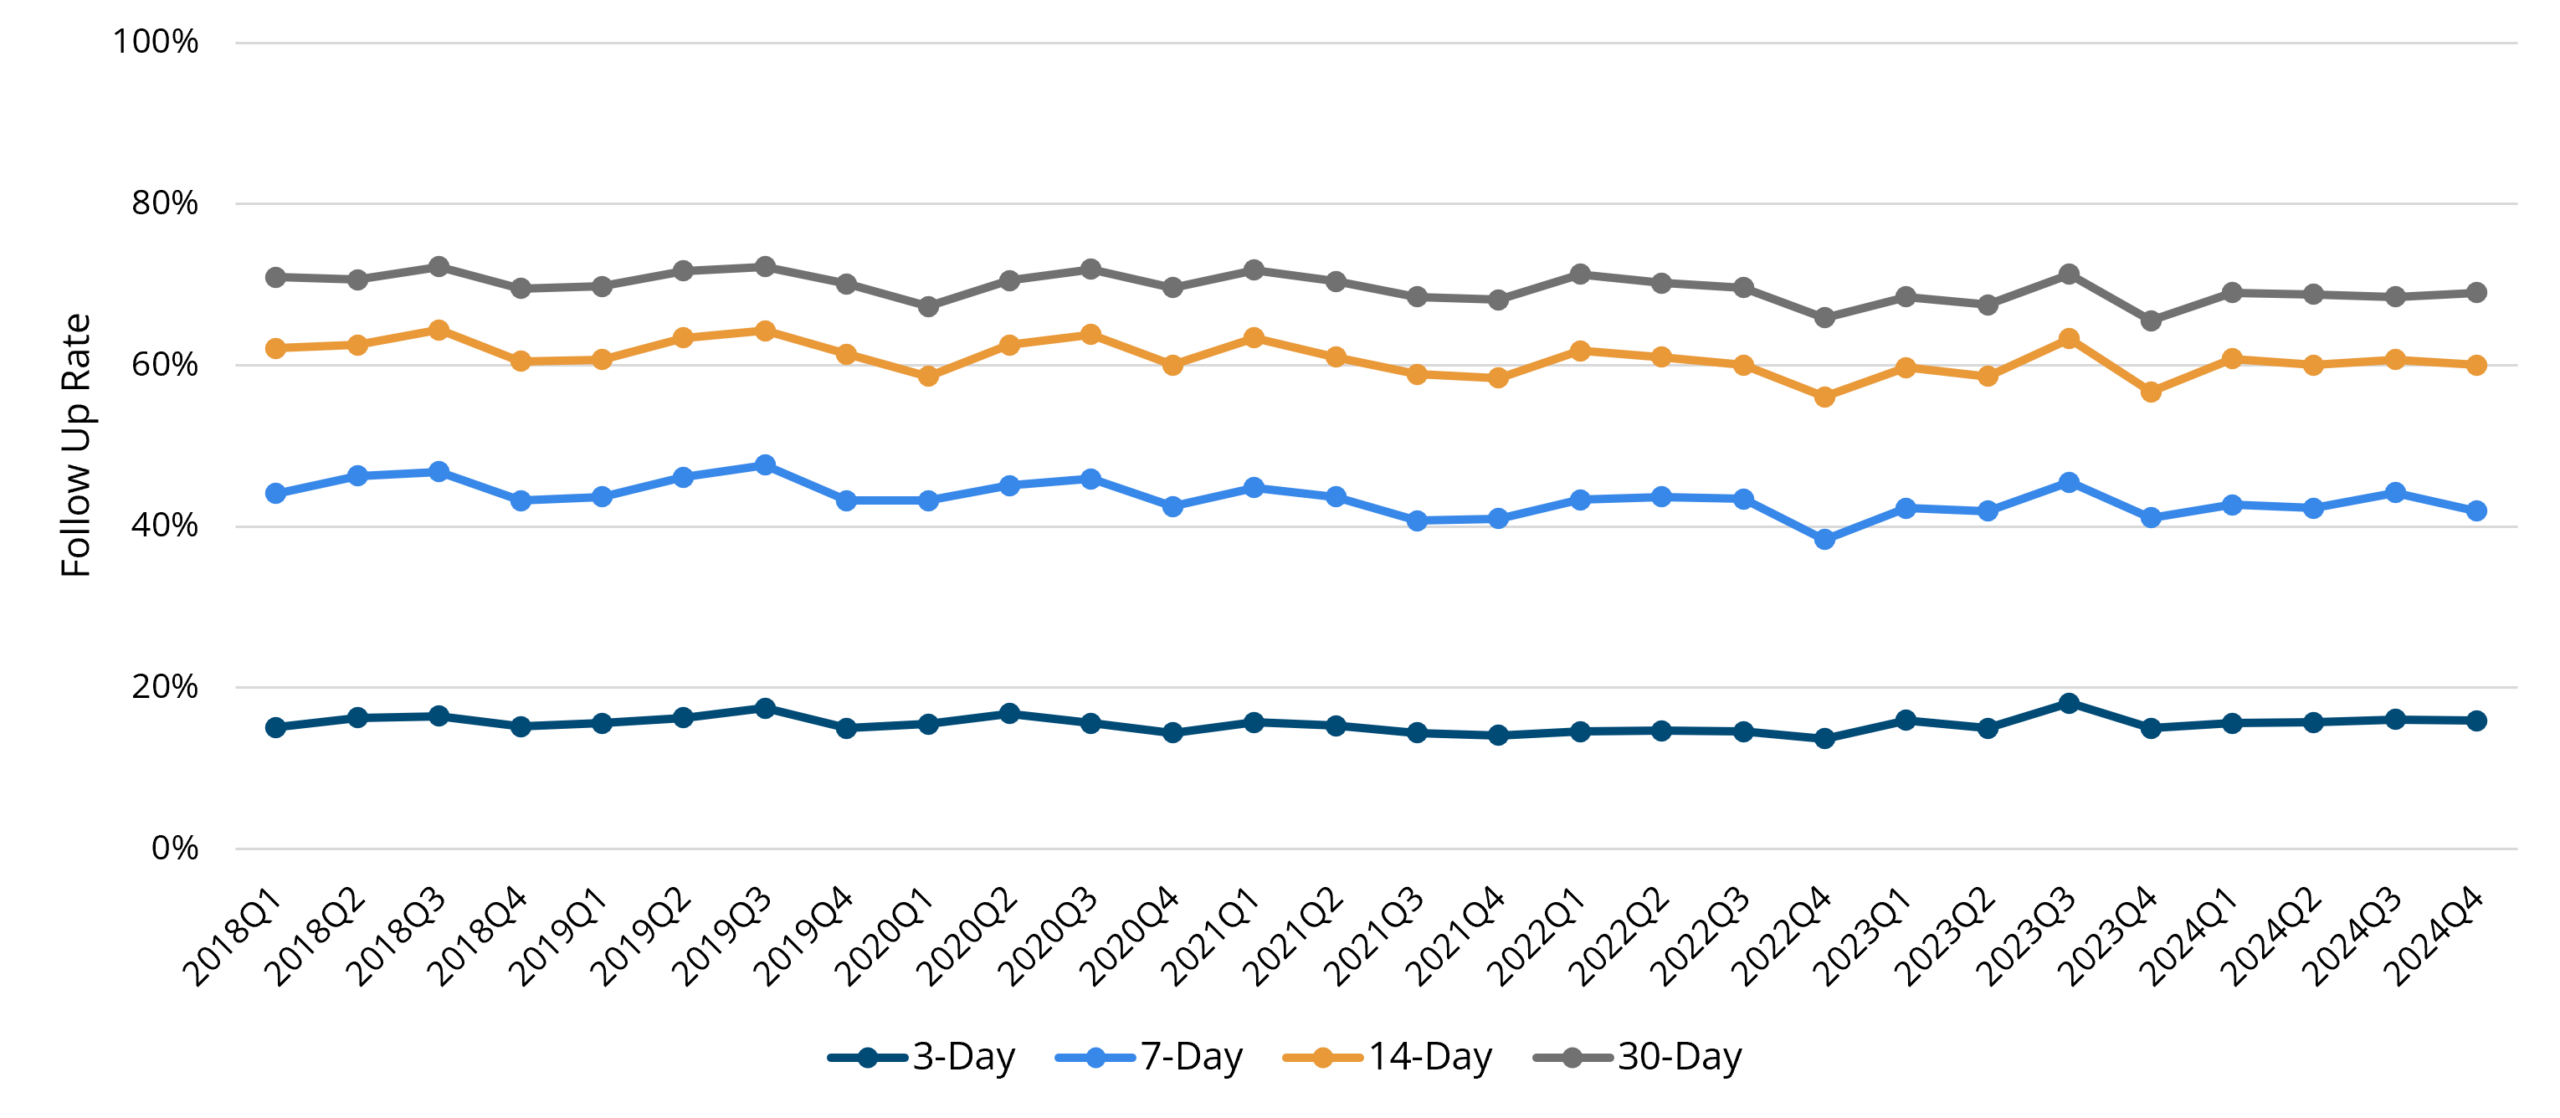
There was little overall change in the CHF follow-up rates over time across all MVC hospitals. In general, rates of follow-up showed a subtle annual pattern, with slightly lower follow-up rates in the fourth quarter of each year (Figure 14). From 2018 through 2024, the rates of patients receiving outpatient follow-up for CHF did not vary substantially.
Figure 14. Outpatient Follow-Up After CHF Hospitalization at MVC Hospitals, by Quarter
Outpatient Follow-Up Within 3, 7, 14, and 30 Days of COPD Hospitalization
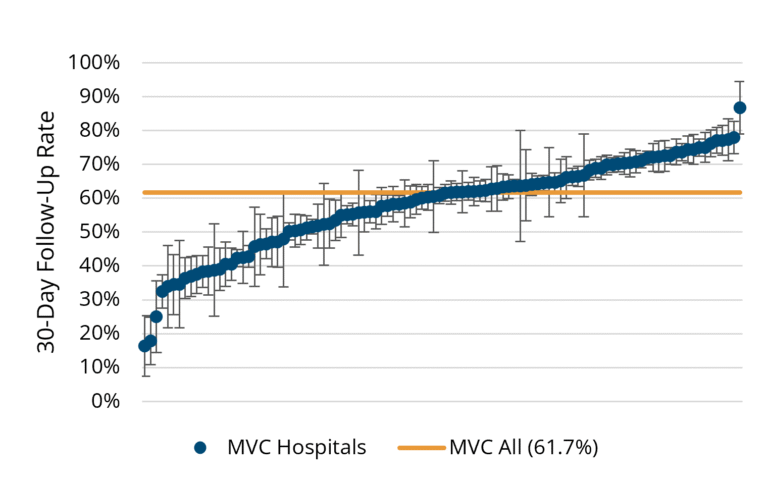
As with CHF, there was substantial variation across hospitals in follow-up rates for COPD. In general, the follow-up rates were lower for COPD than for CHF. The MVC collaborative-wide rates of 3-, 7-, 14-, and 30-day follow-up after COPD hospitalization were 12.8, 35.5%, 51.9% and 61.7%, respectively (Figures 15-18).
Figure 15. 3-Day Follow-Up After COPD Hospitalization, by MVC Hospital
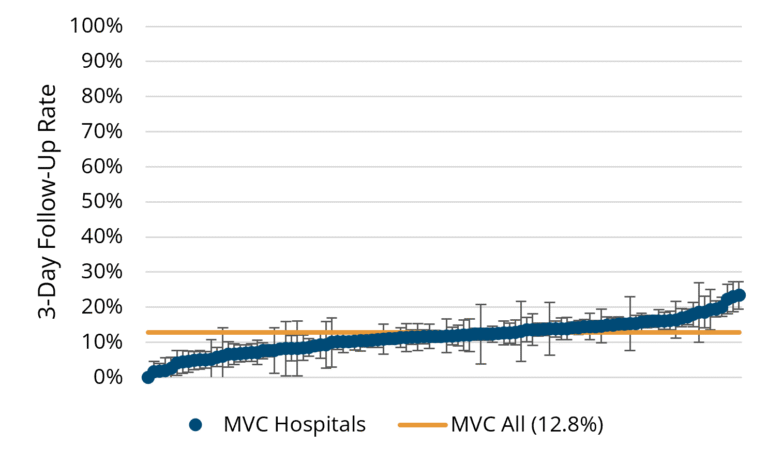
Figure 16. 7-Day Follow-Up After COPD Hospitalization, by MVC Hospital
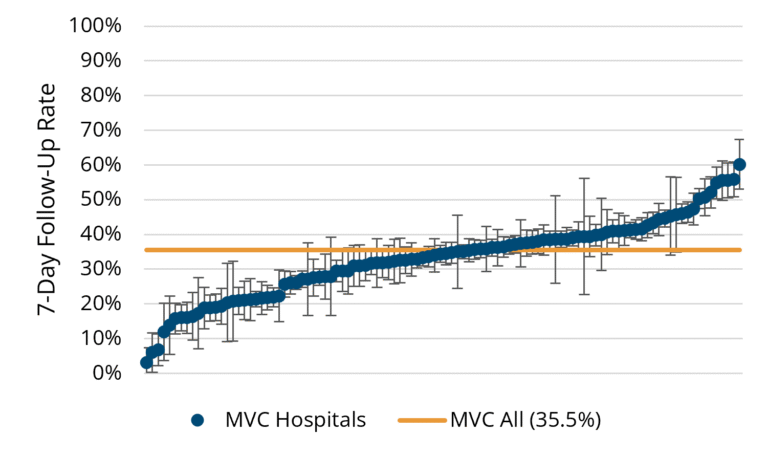
Figure 17. 14-Day Follow-Up After COPD Hospitalization, by MVC Hospital
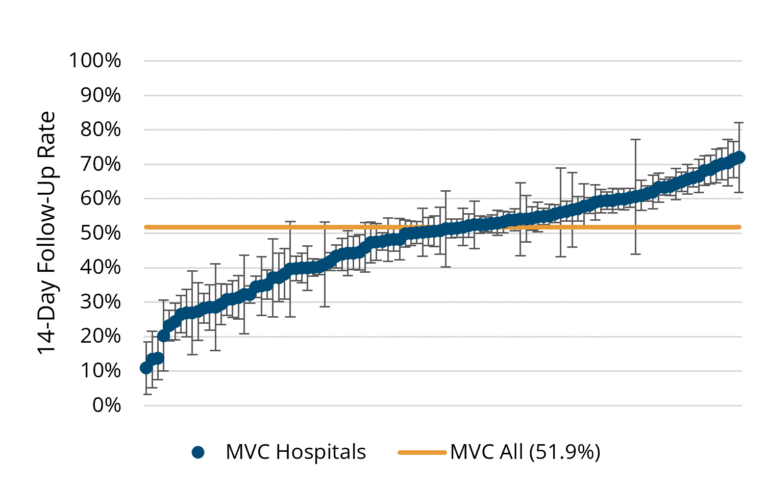
Figure 18. 30-Day Follow-Up After COPD Hospitalization, by MVC Hospital
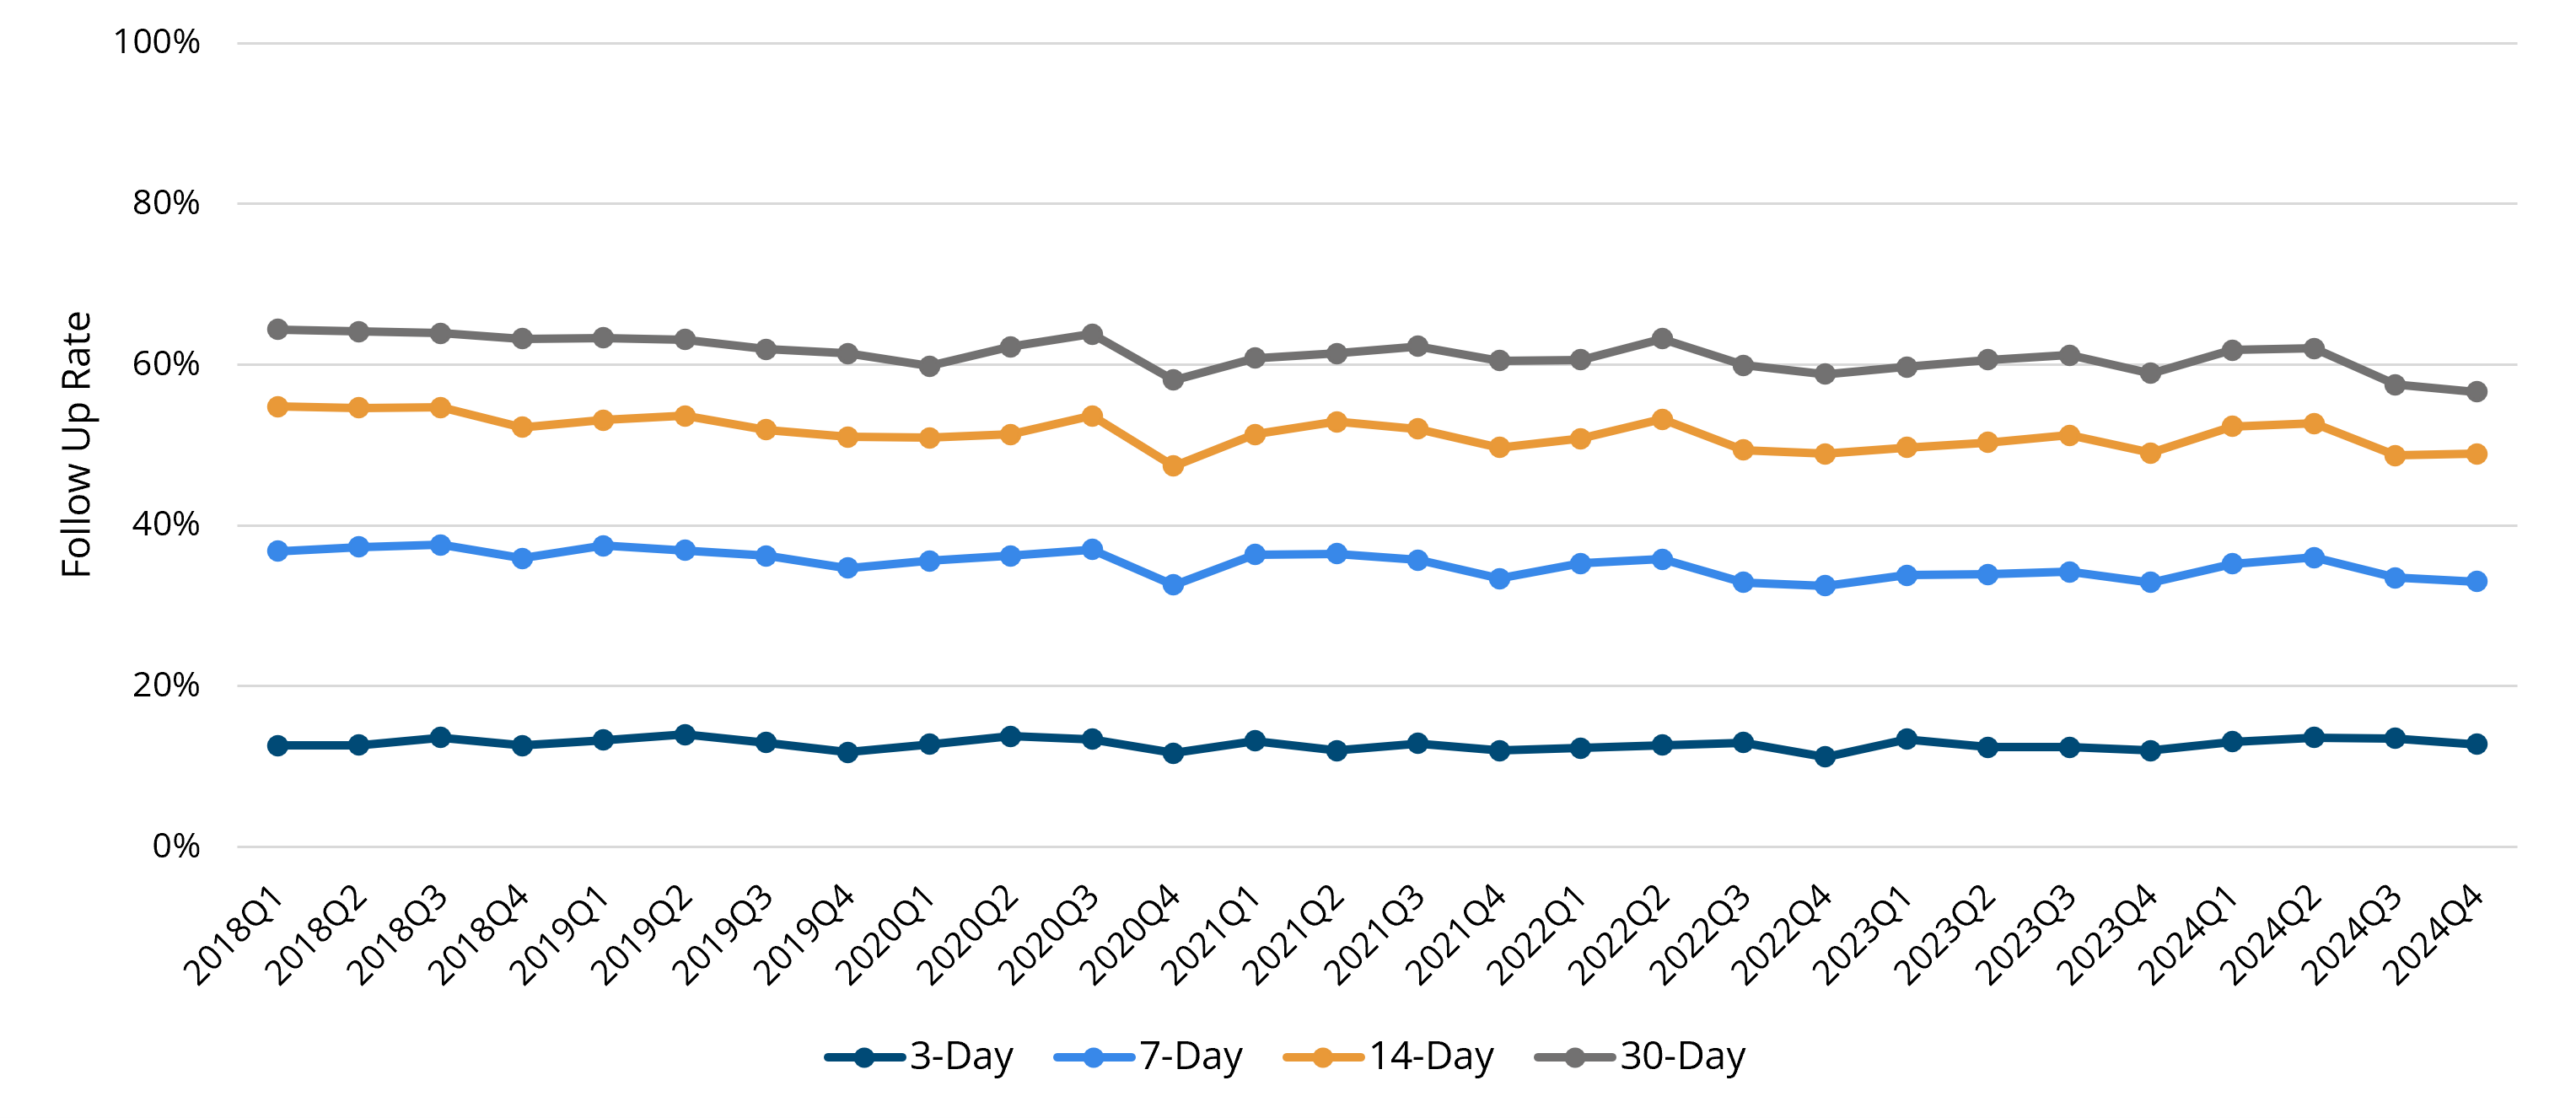
Outpatient follow-up rates after COPD hospitalizations did not vary substantially within any calendar year. From 2018 through 2024, 14-day and 30-day outpatient follow-up show a slight decrease in completion rates while 3-day and 7-day follow-up rates show less variability (Figure 19). Overall, follow-up rates were lower for COPD episodes compared to CHF episodes across all evaluated follow-up windows.
Figure 19. Outpatient Follow-Up After COPD Hospitalization at MVC Hospitals, by Quarter
Appendix A. MVC Condition List and Hierarchy
Specific to 2026 QE Public Report Measures
| Condition | Hierarchy |
| Acute Myocardial Infarction (AMI) | 6 |
| Appendectomy | 19 |
| Atrial Fibrillation | 22 |
| Burn | 27 |
| Cholecystectomy | 16 |
| Chronic Obstructive Pulmonary Disorder (COPD) | 11 |
| Colectomy (non-cancer) | 5 |
| Congestive Heart Failure (CHF) | 10 |
| Coronary Artery Bypass Graft (CABG) | 3 |
| Disc Herniation | 14 |
| Endarterectomy | 20 |
| Endocarditis | 28 |
| Hernia Repair - Abdominal | 24 |
| Hernia Repair - Groin | 23 |
| Hip Fracture | 4 |
| Kidney Stone Surgery | 21 |
| Knee & Hip Replacement | 15 |
| Lower Extremity Bypass | 26 |
| Other Spine Surgery (Cervical Disc Degeneration; Cervical Spinal Stenosis; Lumbar Spinal Stenosis; Lumbar Spondylosis) | 9 |
| Percutaneous Coronary Intervention (PCI) | 12 |
| Pneumonia | 8 |
| Roux-en-Y gastric bypass (RYGB) | 17 |
| Sepsis | 25 |
| Sleeve Gastrectomy | 18 |
| Small Bowel Obstruction | 29 |
| Stroke | 13 |
| Surgical Aortic Value Replacement (SAVR) | 1 |
| Transcatheter Aortic Valve Replacement (TAVR) | 2 |
| Trauma (Other than hip fracture or burns) | 7 |
Appendix B. MVC Claim Categorization Rules
| Facility Claim Type | Definition | |
| Inpatient | (1) Bill Type = 11 (or 12 if DRG present) and (2) DRG* is not a rehab code (945, 946, 949, 950) and (3) Revenue code is not an IP rehab code (118, 128, 138, 148, 158) and (4) Billing facility does not have LTACH taxonomy code (282E00000X) |
|
| SNF | Bill Type in (18, 21) | |
| Emergency Dept. | (1) Bill Type = 1x or Bill Type = 85 and (2) Revenue code is an ED code (450, 451, 452, 456, 459) |
|
| Home Health | Bill Type in (31, 32, 33, 34) | |
| Inpatient Rehab | (1) Bill Type = 11 and (2) DRG* is a rehab DRG (945, 946, 949, 950) or revenue code is an IP rehab code (118, 128, 138, 148, 158) |
|
| Outpatient Rehab | (1) Revenue code is an OP rehab code (41X, 42X, 43X, 44X, 940, 941, 943, 944, 945, 948) or (2) CPT is a rehab CPT or (3) Bill Type in (74, 75) |
|
| LTACH | (1) Bill Type = 11 and
(2) Billing facility primary taxonomy code = 282E00000X |
|
| Outpatient / Other | Everything else |